SMARCA4 / SWI/SNF-related matrix-associated actin-dependent regulator of chromatin subfamily A member 4 · IHC design guide

Design Immunohistochemistry for SMARCA4

Plan paraffin-section SMARCA4 IHC around the expected nuclear pattern (HPA tissue IHC). This guide covers fixation consistency, antibody selection, detection, and scoring, with high-staining cell populations as reference points (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for SMARCA4 (IHC for SMARCA4): expected localisation Nuclear staining is observed in tissue IHC (HPA tissue IHC)., antibody M00223, validated IHC image, and IHC protocol steps
Printable SMARCA4 IHC protocol sheet — expected localisation Nuclear staining is observed in tissue IHC (HPA tissue IHC)., antibody M00223, controls and protocol steps. Open the full SMARCA4 IHC guide →

SMARCA4 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nuclear staining is observed in tissue IHC (HPA tissue IHC).
Staining pattern Widespread nuclear staining across tissues (HPA tissue IHC).
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet M00223)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ None in HPA (detected in all 44 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific). Selected-image fixative and duration unreported (datasheet M00223); verify before use.
Caveat Broad nuclear expression limits negative tissue controls (HPA tissue IHC).
Regulation Low tissue specificity (HPA tissue IHC).
Isoform / epitope 5 isoforms; check epitope coverage across variants (UniProt).
Section 1

Recommended SMARCA4 IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol (datasheet M00223) with a published SMARCA4 protocol for paraffin-embedded tumor sections (PMC4752399).

Recommended immunohistochemistry (IHC-P) protocol parameters
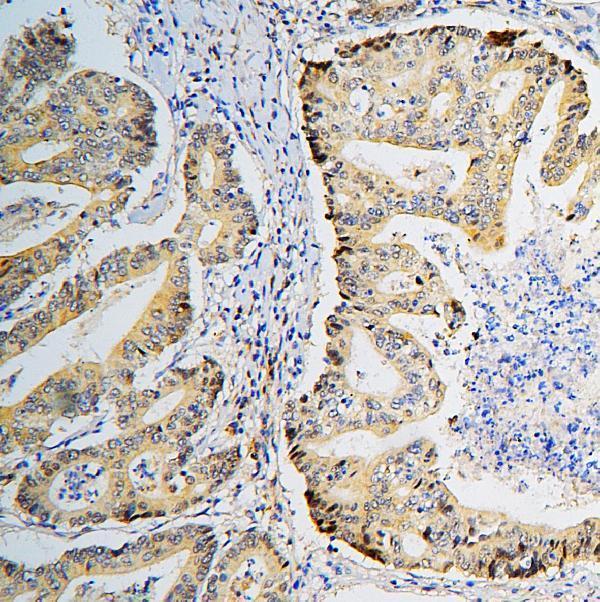
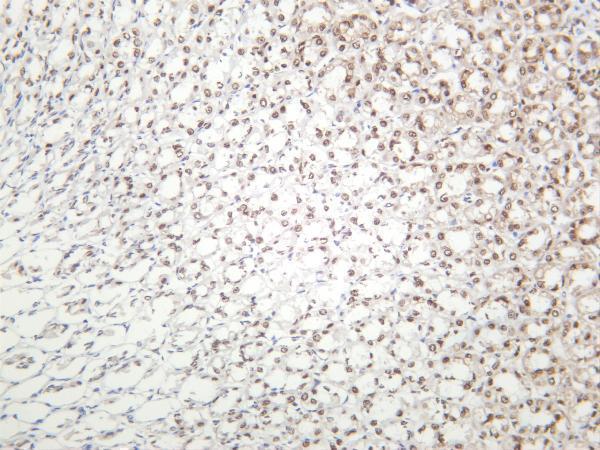
SampleParaffin-embedded human colon cancer tissue; fixative not specified (datasheet M00223)
FixationImage fixative and duration unreported (datasheet M00223); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet M00223); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet M00223)
Primary antibodyRabbit monoclonal (clone GFB-19) anti-SMARCA4, 1:50 (datasheet M00223)
Primary incubationOvernight at 4 °C (datasheet M00223)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet M00223)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultSMARCA4-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Ubiquitous nuclear expression. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet M00223); the published protocol used heat-based EDTA retrieval for 30 minutes (PMC4752399).
Section 2

What Is the Expected SMARCA4 Staining Pattern?

SMARCA4 is a nuclear protein with no transmembrane segment (UniProt P51532). In paraffin section IHC, expect nuclear staining across many cell types: HPA describes ubiquitous nuclear expression and high staining in sampled glandular, hematopoietic, respiratory epithelial, adipocyte and glial cells. HPA rates its tissue IHC profile Supported, citing consistency between antibody staining and RNA expression (HPA tissue IHC).

What am I looking at on my slide?
Distinct nuclear staining in appendix glandular cells, bronchial respiratory epithelium, marrow hematopoietic cells or cortical glia.This matches the reported compartment and examples of High staining (HPA tissue IHC). Compare nuclei within the same section before interpreting intensity; HPA's profile is broad, so staining across several cell populations can be expected (HPA tissue IHC).
Strong cytoplasmic staining with little or no nuclear signal in paraffin section IHC.A cytoplasmic-only IHC result conflicts with nuclear localization (UniProt P51532; HPA tissue IHC). Check morphology, detection background and the antibody control before calling it SMARCA4; HPA also lists cytosol as an additional ICC-IF location, which does not establish a cytoplasmic-only IHC pattern (HPA subcellular).
Prominent staining restricted to a cell population while adjacent expected positive cells lack nuclear staining.Consider cross-reactivity or endogenous detection activity, but do not assign either cause from appearance alone (general IHC practice). HPA reports ubiquitous nuclear expression and High staining in its listed cell populations; it provides no negative tissue in this payload (HPA tissue IHC).
Diffuse color across nuclei, cytoplasm and extracellular areas, with poor nuclear contrast.Treat this as background until a compartment-specific signal can be resolved (general IHC practice). Broad tissue expression does not make diffuse extracellular staining a positive result: the reported IHC pattern is nuclear (HPA tissue IHC; UniProt P51532).
No nuclear signal in a section containing an HPA-listed, high-staining cell population.An absent result conflicts with that reference pattern, but a failed assay and a sample-specific biological difference remain possible (HPA tissue IHC; general IHC practice). Check the positive control and detection run before interpreting the specimen as SMARCA4-negative.
💡Expected SMARCA4 appearanceCall a positive IHC result when cell nuclei show clear, often High staining in HPA-listed positive populations; diffuse extracellular color or cytoplasmic-only staining is suspect (HPA tissue IHC; UniProt P51532; general IHC practice).
How each factor affects the staining
Compartment and topologySMARCA4 is nuclear and has no transmembrane segment (UniProt P51532). Score nuclear signal for paraffin section IHC (HPA tissue IHC); membrane staining alone does not fit those annotations. This is a localization expectation, not a claim about antigen retrieval or fixation sensitivity.
Breadth of tissue expressionHPA calls the tissue IHC profile ubiquitous and RNA tissue specificity low (HPA tissue IHC). Its supplied examples are positive and High; no negative or low-staining tissues are listed. Use those examples as positive references without treating unlisted cell types as established negatives.
Antibody evidenceCAB004208 is Supported for IHC and ICC, whereas HPA048340 is Supported for ICC with no IHC status supplied (HPA antibodies). This distinction matters when selecting evidence for a paraffin section result; ICC support alone does not validate an IHC pattern.
Isoforms and antibody epitopeUniProt lists 5 SMARCA4 isoforms and domains including an ATP-binding region and bromodomain (UniProt P51532). The payload gives no antibody epitope or isoform coverage, so it cannot predict whether a particular antibody detects every isoform or explain a tissue difference.
IF/ICC Q: where should signal appear?A: HPA reports mainly nucleoplasm, nucleoli fibrillar center and nucleoli rim, with cytosol listed as an additional location (HPA subcellular). These are ICC-IF observations; use the separate IF/ICC guide for that application, without transferring its compartment details into an IHC protocol.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No staining in a sampled positive cell population.The positive tissue reference and observed result disagree; HPA alone cannot identify the technical cause (HPA tissue IHC).Confirm that the run's positive control stains nuclei, then review reagent activity, detection steps and the recorded antigen retrieval conditions (general IHC practice). Do not infer SMARCA4-specific retrieval sensitivity from this result.
Nuclear signal is weak and difficult to distinguish from counterstain.Low contrast can prevent reliable compartment scoring (general IHC practice); the supplied sources give no catalog antibody dilution or target-specific retrieval condition.Review the IHC-validated antibody's actual datasheet and run controls; adjust counterstain or detection conditions only within the validated workflow (general IHC practice). Compare with an HPA-listed high-staining cell population (HPA tissue IHC).
Cytoplasmic-only or membrane-like staining dominates IHC.This disagrees with the nuclear IHC profile and UniProt localization; the image alone cannot distinguish off-target binding from background (HPA tissue IHC; UniProt P51532; general IHC practice).Check nuclear focus and tissue morphology, then compare the antibody control and an independent validated IHC result if available (general IHC practice). Do not score compartment-mismatched color as a positive nuclear result.
Diffuse staining obscures cell boundaries or nuclei.Nonspecific binding, inadequate washing or endogenous detection activity can produce background in chromogenic IHC (general IHC practice).Inspect the no-primary and detection controls, then review blocking, washes and detection chemistry (general IHC practice). Retain only interpretable nuclear staining when comparing with the HPA tissue profile (HPA tissue IHC).
One cell population stains strongly while an adjacent HPA-listed positive population does not.Technical variation or sample biology may contribute; HPA's broad profile does not establish a negative call for every cell on an individual slide (HPA tissue IHC; general IHC practice).Identify the cell populations by morphology and compare a matched positive control before considering cross-reactivity (general IHC practice). Document the discrepancy rather than assuming that every stained cell is specific.
An ICC-IF image shows nucleolar detail or some cytosol, unlike a simpler nuclear IHC readout.HPA reports supported nucleoplasmic and nucleolar locations plus additional cytosol in ICC-IF (HPA subcellular); its tissue IHC summary is ubiquitous nuclear expression (HPA tissue IHC).Interpret each image within its application and antibody validation status (HPA antibodies; general IHC practice). For paraffin section scoring, use the IHC nuclear pattern and its tissue controls (HPA tissue IHC).

Sample controls for SMARCA4 IHC & IF

🧪Run appendix first and confirm nuclear staining in its glandular cells (HPA: High in appendix glandular cells; UniProt P51532: nucleus). HPA detects SMARCA4 in all 44 scored tissues, so there is no supported negative tissue; use no-primary and isotype controls, and expect any cells without target staining on the positive slide to retain counterstained nuclei without nuclear DAB signal, without assuming a particular cell type is negative (HPA: no negative rows; standard IHC practice).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: None in HPA: SMARCA4 is detected in all 44 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show SMARCA4 in A-431, U-251MG, U2OS, PC-3, KOLF2.1J, NIH 3T3, with annotated localisation: Nucleoplasm (supported), Nucleoli fibrillar center (supported), Nucleoli rim (supported) (HPA subcellular).
Technical controls: Run a no-primary, secondary-only control and a concentration-matched rabbit IgG isotype control matched to the primary’s clonality class; use SMARCA4-knockout material as a biological negative when available (selected-SKU caption: rabbit primary and anti-rabbit secondary; standard IHC practice). Quench endogenous peroxidase and check inflammatory cells for background in appendix sections before HRP/DAB scoring (selected-SKU caption: HRP/DAB detection; standard IHC practice).
⚠️Feasibility: The selected-SKU paraffin-section caption reports heat retrieval in EDTA at pH 8.0 and nuclear SMARCA4 detection is the expected readout, but its fixative is unreported (selected-SKU caption; UniProt P51532: nucleus). No target-specific fixation window or fixation effect is reported in the supplied evidence, and the evidence does not establish whether frozen sections or IF/ICC would be easier; the direct application example is paraffin-section IHC (selected-SKU caption). In appendix, assess glandular nuclei against local mucus and inflammatory-cell background when scoring DAB (HPA: High in appendix glandular cells; standard IHC practice).

HPA tissue IHC evidence for SMARCA4

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — High consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Glandular cells High Protein (IHC) HPA →
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Breast Adipocytes High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: SMARCA4 is detected in all 44 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced SMARCA4 IHC Tips

Troubleshoot SMARCA4 staining in paraffin sections by checking nuclear localisation, the catalog antibody’s documented retrieval conditions, and appropriate controls.

What should I change when SMARCA4 nuclear staining is weak after retrieval?
Start with heat-mediated retrieval in EDTA at pH 8.0 (datasheet M00223). The catalog antibody detected SMARCA4 in a paraffin-embedded human colon cancer section after that retrieval, followed by 1:50 primary antibody overnight at 4°C (datasheet M00223). If nuclei remain weak, adjust heating and cooling consistently across sections before treating a different buffer as a fallback (standard IHC practice). Compare each change with an identically processed control section and assess nuclear signal alongside tissue damage and background (standard IHC practice). The caption does not report a fixative, so it cannot establish retrieval performance for a particular fixation method (datasheet M00223).
Could fixation explain weak or patchy SMARCA4 staining?
SMARCA4-specific fixation sensitivity is unknown from the supplied evidence; the paraffin-section caption does not state its fixative (datasheet M00223). Record the fixative and fixation duration for each specimen, then compare sections processed with the same EDTA pH 8.0 retrieval (datasheet M00223; standard IHC practice). Check whether weak nuclei cluster in thick, damaged, or poorly preserved regions before changing antibody concentration (standard IHC practice). Include an on-slide tissue control and compare its nuclear staining between runs to identify processing drift (standard IHC practice). Neither the tissue expression profile nor protein topology establishes a SMARCA4-specific fixation effect (HPA: ubiquitous nuclear expression; UniProt P51532: no transmembrane segment).
How should I assess SMARCA4 signal outside the nucleus?
Score nuclear staining first: SMARCA4 is reported in the nucleus, and tissue IHC shows ubiquitous nuclear expression (UniProt P51532 subcellular location; HPA tissue IHC). Nucleoplasmic signal is also supported by subcellular imaging, although that imaging includes additional nucleolar and cytosolic locations (HPA subcellular). In chromogenic sections, compare apparent cytoplasmic colour with adjacent nuclei at the same exposure and counterstain intensity (standard IHC practice). Recheck deparaffinisation, blocking, and detection controls if extranuclear colour dominates while expected nuclei remain blank (standard IHC practice; UniProt P51532 subcellular location). Record nuclear and extranuclear staining separately rather than combining them into one positivity score (standard IHC practice).
Could isoforms or epitope accessibility cause inconsistent nuclear staining?
SMARCA4 has 5 listed isoforms and several annotated domains, including a bromodomain at residues 1453–1564 (UniProt P51532). The supplied caption does not identify the catalog antibody’s epitope, so isoform recognition cannot be assigned from its staining result (datasheet M00223). If staining differs between samples, request an epitope map and check whether the mapped sequence is shared by the isoforms under study (standard antibody validation practice; UniProt P51532 isoforms). Keep retrieval and detection conditions matched while comparing an independent SMARCA4 antibody, if available (standard IHC practice). Avoid attributing a negative nucleus to phosphorylation or acetylation without evidence that the mapped epitope contains the relevant site (UniProt P51532 modified residues; standard antibody validation practice).
How can I check SMARCA4 by IF alongside the chromogenic IHC result?
Use IF as a separate localisation check and retain the paraffin-section IHC result as the chromogenic reference (datasheet M00223; standard IHC practice). Multiplex SMARCA4 with a validated marker for the expected cell type, such as glandular cells in appendix, and inspect whether the SMARCA4 signal occupies their nuclei (HPA tissue IHC: high in appendix glandular cells; UniProt P51532 subcellular location). Choose a fluorophore channel after measuring tissue autofluorescence and include single-stain controls (standard IF practice). For an intracellular nuclear epitope, optimise permeabilisation while preserving nuclear structure; SMARCA4 has no transmembrane segment (UniProt P51532 topology; standard IF practice). Do not carry the IHC antibody dilution into IF without validation (datasheet M00223; standard IF practice).
What causes diffuse DAB colour around otherwise weak SMARCA4 nuclei?
The documented chromogenic example used a peroxidase-conjugated secondary antibody and DAB after 1:50 primary incubation (datasheet M00223). Include a no-primary control to locate signal arising from detection reagents, then check peroxidase quenching and nonspecific secondary binding (standard IHC practice). The example used 10% goat serum for blocking, but its performance should be judged against background in the current tissue (datasheet M00223; standard IHC practice). Compare DAB development on control and test sections together, stopping before diffuse colour obscures nuclear boundaries (standard IHC practice). Report staining as SMARCA4 only when nuclear signal exceeds that background in morphologically intact cells (UniProt P51532 subcellular location; standard IHC practice).
How should I quantify heterogeneous SMARCA4 nuclear staining? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and region of interest before scoring, then count intact nuclei within that region (standard IHC practice; UniProt P51532 subcellular location). Report the percentage of positive nuclei and, when intensity matters, an H-score calculated as the sum of intensity category multiplied by its percentage of cells (standard IHC practice). Normalise positive-cell counts to all evaluable nuclei of the same cell population, or report density per mm² of viable tissue when comparing spatial regions (standard IHC practice). Keep thresholds, counterstain, and DAB development consistent across slides (standard IHC practice). Exclude folds, edges, and necrotic areas from the denominator, and document exclusions (standard IHC practice).
When is apparent SMARCA4 loss a staining artefact?
A convincing positive shows nuclear staining in intact cells, consistent with SMARCA4’s nuclear location and the supported tissue IHC profile (UniProt P51532 subcellular location; HPA tissue IHC). Before calling a cell population negative, check neighbouring evaluable cells on the same section and a concurrently processed control section (standard IHC practice). Treat staining confined to section edges, folds, or necrotic regions as suspect until it reproduces in intact tissue (standard IHC practice). Diffuse colour that persists in a no-primary control can reflect endogenous enzyme activity or detection background rather than target staining (standard IHC practice). Interpret loss within the identified cell population, since SMARCA4 expression is reported across many tissues and cell types (HPA tissue IHC).
Boster reagents

Best SMARCA4 / SWI/SNF-related matrix-associated actin-dependent regulator of chromatin subfamily A member 4 IHC Antibodies

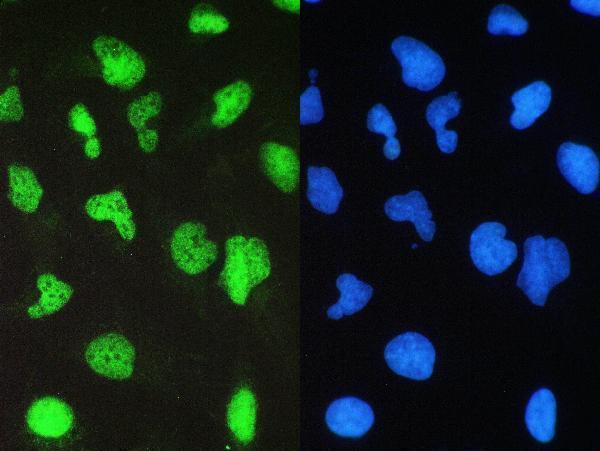
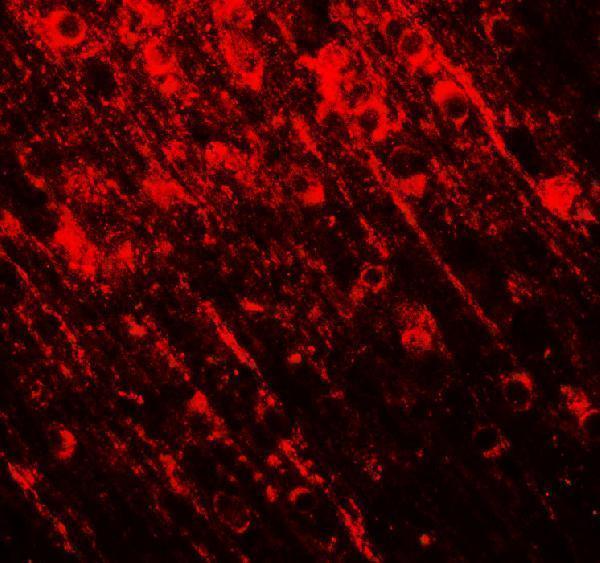
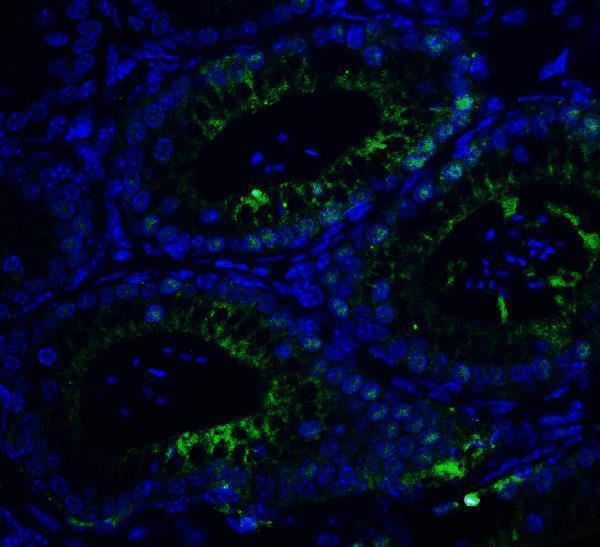
Catalog anti-SMARCA4 antibodies have IHC images from human, mouse and rat tissues, plus IF images from mouse testis and U20S cells (catalog image captions).

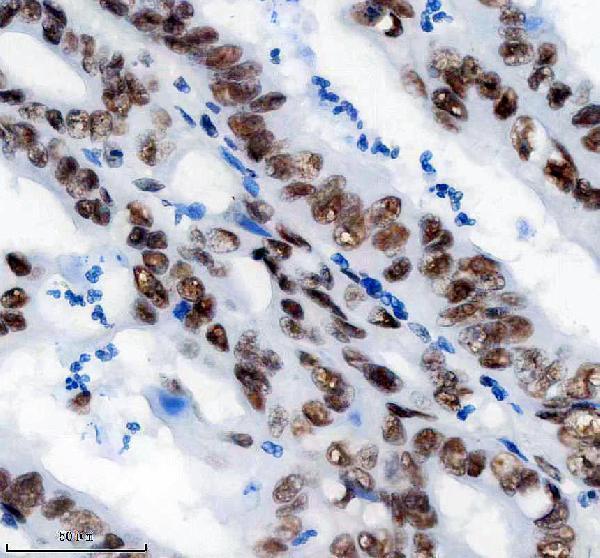
Real IHC data IHC analysis of SMARCA4/BRG1 using anti-SMARCA4/BRG1 antibody (M00223). SMARCA4/BRG1 was detected in a paraffin-embedded section of human colon cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1: 50 rabbit anti-SMARCA4/BRG1 Antibody (M00223) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-BRG1 Rabbit Monoclonal Antibody
Cat # M00223
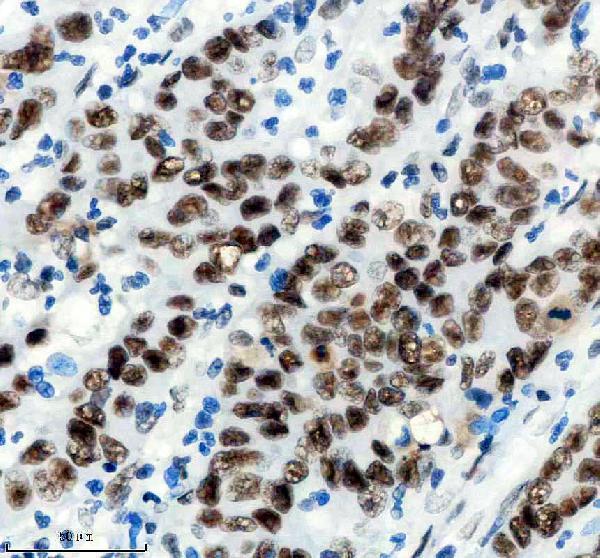
Real IHC data IHC analysis of BRG1 using anti-BRG1 antibody (A00223-1). BRG1 was detected in paraffin-embedded section of human intestinal cancer tissue. Heat mediated antigen retrieval was performed in citrate buffer (pH6, epitope retrieval solution) for 20 mins. The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2μg/ml rabbit anti-BRG1 Antibody (A00223-1) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC)(Catalog # SA1022) with DAB as the chromogen.
Anti-BRG1/SMARCA4 Antibody ®
Cat # A00223-1
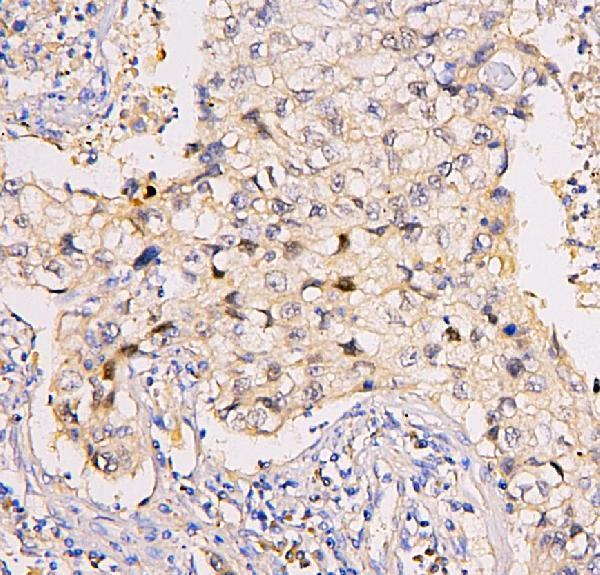
Real IHC data IHC analysis of BRG1 using anti-BRG1 antibody (M00223-1). BRG1 was detected in paraffin-embedded section of human lung cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml mouse anti-BRG1 Antibody (M00223-1) overnight at 4°C. Biotinylated goat anti-mouse IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1021) with DAB as the chromogen.
Anti-BRG1 SMARCA4 Antibody ® (monoclonal, 3F4)
Cat # M00223-1
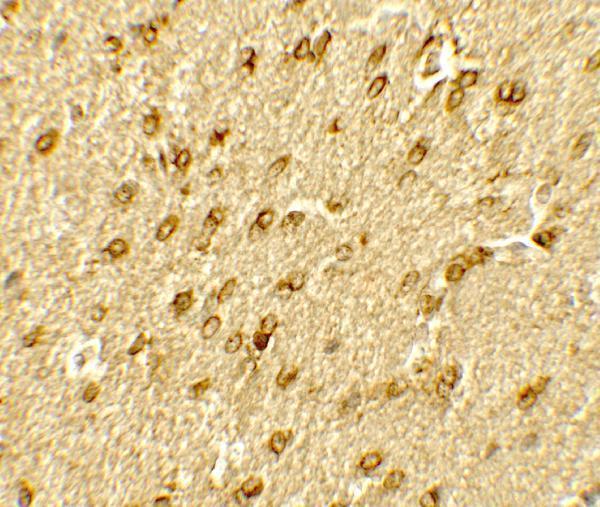
Real IHC data Immunohistochemistry of SMARCA4 in rat brain tissue with SMARCA4 antibody at 5 μg/mL.
Anti-Transcription activator BRG1 SMARCA4 Antibody
Cat # A00223
Real IHC data Rat stomach was stained with anti-BRG1 rabbit antibody
Anti-BRG1 Rabbit Monoclonal Antibody
Cat # M00223-3

M00223 shows paraffin-section IHC in human colon cancer; A00223-1 in human intestinal cancer; and M00223-1 in human lung cancer (respective IHC image captions). A00223 shows IHC in rat brain, while M00223-3 shows staining in rat stomach; the captions do not specify how those tissues were processed (respective IHC image captions).

Which to pick: For paraffin-section IHC, choose rabbit monoclonal M00223 for its human colon cancer example with EDTA retrieval, or mouse monoclonal M00223-1 for its human lung cancer example with EDTA retrieval (catalog antibody details and respective IHC image captions); neither caption reports the fixative. For IF/ICC, A00223-1 has an IF image in U20S cells and an IF/ICC application listing, while A00223 has an IF image in mouse testis (respective IF image captions and catalog applications). For work across human, mouse and rat, M00223 or A00223-1 lists all 3 species and includes IHC and IF/ICC applications (catalog reactivity and applications).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P51532 (SMCA4_HUMAN, SWI/SNF-related matrix-associated actin-dependent regulator of chromatin subfamily A member 4).
  2. Human Protein Atlas. SMARCA4 tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. SMARCA4 subcellular location (ICC-IF): Mainly localized to the nucleoplasm, nucleoli fibrillar center and nucleoli rim..
  4. Human Protein Atlas. SMARCA4 antibody validation summary (2 antibodies).
  5. Loss of SMARCA4 Expression Is Both Sensitive and Specific for the Diagnosis of Small Cell Carcinoma of Ovary, Hypercalcemic Type. The American journal of surgical pathology 2016 — PMC4752399.
  6. [Analysis of Clinicopathologic Features of 9 Cases of SMARCA4-deficient Non-small Cell Lung Cancer]. Zhongguo fei ai za zhi = Chinese journal of lung cancer 2022 — PMC9411953.
  7. Esophageal carcinoma with SMARCA4 mutation: a narrative review for this rare entity. Translational gastroenterology and hepatology 2024 — PMC11074479.
  8. Comprehensive genomic profiling of Finnish lung adenocarcinoma cohort reveals high clinical actionability and SMARCA4 altered tumors with variable histology and poor prognosis. Neoplasia (New York, N.Y.) 2022 — PMC9391575.
  9. PubMed PMID:8232556 — UniProt-cited evidence.
  10. PubMed PMID:8208605 — UniProt-cited evidence.
  11. PubMed PMID:11085541 — UniProt-cited evidence.