SOCS5 / Suppressor of cytokine signaling 5 · IHC design guide

Design Immunohistochemistry for SOCS5

Plan SOCS5 paraffin-section IHC around broadly cytoplasmic staining (HPA tissue IHC). The catalog antibody’s human IHC-P range is 2–5 μg/mL (datasheet A05989-1); compare staining by cell type because some are undetected (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for SOCS5 (IHC for SOCS5): expected localisation Cytoplasmic staining in tissue sections (HPA tissue IHC), antibody A05989-1, validated IHC image, and IHC protocol steps
Printable SOCS5 IHC protocol sheet — expected localisation Cytoplasmic staining in tissue sections (HPA tissue IHC), antibody A05989-1, controls and protocol steps. Open the full SOCS5 IHC guide →

SOCS5 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic staining in tissue sections (HPA tissue IHC)
Staining pattern Broad cytoplasmic staining across many cell types (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A05989-1)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Cervix+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Some cell types are undetected despite broad staining (HPA tissue IHC)
Regulation Cytokine feedback; induction unreported (UniProt)
Isoform / epitope 0 isoforms listed; no TM-defined epitope split (UniProt)
Section 1

Recommended SOCS5 IHC & IF Protocols

The catalog antibody uses EDTA pH 8.0 retrieval (datasheet: A05989-1). One published SOCS5 IHC protocol meets the parameter criteria below (PMC4388447).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human ovarican cancer tissue; fixative not specified (datasheet A05989-1)
FixationImage fixative and duration unreported (datasheet A05989-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A05989-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A05989-1)
Primary antibodyRabbit anti-SOCS5, 2-5μg/ml (datasheet A05989-1)
Primary incubationOvernight at 4 °C (datasheet A05989-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A05989-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultSOCS5-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Ubiquitous cytoplasmic expression. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 for the catalog antibody (datasheet: A05989-1). Use citrate pH 6.0 when reproducing the published protocol with its stated antibody (PMC4388447).
Section 2

What Is the Expected SOCS5 Staining Pattern?

In paraffin IHC, expect predominantly cytoplasmic SOCS5 staining, including strong signal in adrenal and prostate glandular cells, testicular cells in seminiferous ducts, and bladder urothelial cells (HPA: ubiquitous cytoplasmic expression; High in these cell types). HPA rates its tissue IHC pattern Approved, pending external verification (HPA: reliability). SOCS5 has no annotated transmembrane segment (UniProt O75159: topology).

What am I looking at on my slide?
Cytoplasmic staining in adrenal or prostate glandular cells, testicular cells in seminiferous ducts, or bladder urothelial cells.This fits the reported strong tissue IHC pattern (HPA: High in these cell types). Compare cell types within the section; intensity alone does not establish specificity (general IHC practice).
Predominantly nuclear staining, or a crisp membrane-only rim, in paraffin IHC.Recheck specificity and detection background: the tissue IHC profile is cytoplasmic (HPA: tissue profile). Additional nucleoplasmic and plasma-membrane locations come from ICC-IF, so they do not establish a membrane-only IHC pattern (HPA: subcellular ICC-IF).
Strong signal in cardiomyocytes or cervical glandular cells while expected positive cells stain.These cells were reported as Not detected (HPA: heart muscle cardiomyocytes; cervix glandular cells). Consider cross-reactivity or endogenous detection activity, then check controls; Not detected is an observed pattern, not proof that every specimen must be negative (general IHC practice).
Diffuse chromogen across tissue, stroma, and empty spaces without clear cellular boundaries.The pattern is hard to interpret as SOCS5 because HPA describes cellular cytoplasmic expression (HPA: tissue profile). In chromogenic IHC, inadequate blocking, excess detection reagent, or residual endogenous enzyme activity can produce background (general IHC practice).
No signal in an adequately preserved adrenal, prostate, testis, or bladder section.That conflicts with the reported High staining in the specified cells (HPA: tissue IHC). Check the antibody and staining run with a positive control; a failed run cannot establish biological absence (general IHC practice).
💡Expected SOCS5 appearanceA convincing positive is cellular cytoplasmic chromogen, strongest in the listed High cell populations (HPA: tissue IHC); widespread cell-independent haze or dominant membrane-only staining is a specificity or detection concern (HPA: tissue profile; general IHC practice).
How each factor affects the staining
Tissue and cell typeHigh staining is reported in adrenal and prostate glandular cells, seminiferous-duct cells, and urothelium; several other populations are Medium, Low, or Not detected (HPA: tissue IHC). Score the relevant cells rather than the whole section (general IHC practice).
Compartment and applicationTissue IHC is described as cytoplasmic (HPA: tissue profile). ICC-IF places SOCS5 mainly in cytosol, with additional nucleoplasm and plasma membrane (HPA: subcellular ICC-IF); assess each application against its own evidence.
Antibody evidenceHPA020884 and CAB025510 each have Approved IHC status (HPA: antibody validation). The supplied record gives no IHC Enhanced designation; Approved tissue reliability remains pending external verification (HPA: reliability).
Protein topology and processingNo transmembrane segment, signal peptide, propeptide, glycosylation site, or annotated isoform is listed (UniProt O75159: topology, processing, glycosylation, isoforms). These annotations do not establish fixation sensitivity or a required retrieval condition.
Chromogenic detection backgroundEndogenous enzyme activity and nonspecific reagent binding can mimic cellular signal (general IHC practice). Interpret weak or unexpected staining alongside matched detection controls; HPA tissue levels do not identify its cause (HPA: tissue IHC).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
The expected High cell population is blank.The run may have failed, or staining conditions may be unsuitable; HPA reports High signal in the specified populations (HPA: tissue IHC; general IHC practice).Check a known-positive section, reagent performance, and the catalog antibody's IHC-P instructions; evaluate retrieval only as a general IHC variable, without assuming SOCS5-specific fixation sensitivity (general IHC practice).
All cells and surrounding tissue appear brown.Diffuse signal can reflect excessive detection background or endogenous enzyme activity (general IHC practice).Inspect a no-primary control, blocking and enzyme-quenching steps, and chromogen development; retain a counterstain that lets cell boundaries be assessed (general IHC practice).
A reported Not detected population stains strongly.Cross-reactivity or detection activity is possible; HPA lists cardiomyocytes and cervical glandular cells as Not detected (HPA: tissue IHC; general IHC practice).Compare a positive tissue on the same run and review no-primary controls; repeat with an independently validated antibody if available (HPA: two antibodies have Approved IHC status; general IHC practice).
Signal is nuclear-only or forms a uniform membrane rim in IHC.That does not match the reported cytoplasmic tissue profile (HPA: tissue IHC); ICC-IF reports additional nuclear and membrane localisation, but does not validate this IHC pattern (HPA: subcellular ICC-IF).Recheck compartment boundaries, detection controls, and antibody specificity before scoring the signal as SOCS5 (general IHC practice).
Adjacent fields differ in apparent staining intensity.The section may contain cell populations with different reported levels; HPA includes High, Medium, Low, and Not detected populations (HPA: tissue IHC).Identify and score the named cell type in each field, using the counterstain to distinguish cells from background (general IHC practice).
IF/ICC Q: Should cytosol-only fluorescence be expected?Cytosol is the main location, with additional nucleoplasm and plasma membrane reported in ICC-IF (HPA: subcellular ICC-IF).Interpret IF/ICC on its separate guide page using its application-specific controls; do not treat the paraffin IHC pattern as an IF localisation rule (HPA: tissue IHC; HPA: subcellular ICC-IF).

Sample controls for SOCS5 IHC & IF

🧪Run prostate first: its glandular cells should stain (HPA: High in prostate glandular cells). Use cervix glandular cells as the negative tissue comparator (HPA: Not detected); on the prostate slide, assess adjacent stromal cells for little or no cellular DAB staining as an internal background reference, without assuming they are biologically SOCS5-negative.
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Cervix (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show SOCS5 in A-431, U-251MG, U2OS, with annotated localisation: Cytosol (approved) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control; a concentration-matched rabbit IgG isotype control for the captioned rabbit primary antibody; and SOCS5 knockout material as a biological specificity control (selected-SKU IHC caption: rabbit anti-SOCS5). Block endogenous peroxidase and inspect the prostate section for luminal DAB deposits that could be mistaken for cellular staining (selected-SKU IHC caption: HRP/DAB detection).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected-SKU paraffin-section caption does not state a fixative (selected-SKU IHC caption: fixative not stated). The reported IHC procedure uses heat retrieval in EDTA at pH 8.0, but the evidence does not establish that SOCS5 staining requires that retrieval condition (selected-SKU IHC caption: EDTA retrieval). Neither frozen sections nor IF/ICC is shown to be easier; HPA does show mainly cytosolic ICC-IF localisation, while prostate glandular lumina require care when interpreting chromogenic deposits (HPA subcellular: cytosol approved; HPA: High in prostate glandular cells).

HPA tissue IHC evidence for SOCS5

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Prostate Glandular cells High Protein (IHC) HPA →
Testis Cells in seminiferous ducts High Protein (IHC) HPA →
Urinary bladder Urothelial cells High Protein (IHC) HPA →
Appendix Glandular cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Cervix Glandular cells Not detected Protein (IHC) HPA →
Fallopian tube Glandular cells Not detected Protein (IHC) HPA →
Heart muscle Cardiomyocytes Not detected Protein (IHC) HPA →
Lymph node Germinal center cells Not detected Protein (IHC) HPA →
Salivary gland Glandular cells Not detected Protein (IHC) HPA →
Section 3

Advanced SOCS5 IHC Tips

Troubleshoot SOCS5 staining in paraffin sections by checking retrieval, controls, cellular distribution and scoring before assigning biological meaning.

Which retrieval condition should I start with for SOCS5 paraffin-section IHC?
Start with heat-mediated retrieval in EDTA at pH 8.0 for this catalog antibody (datasheet A05989-1). The selected paraffin-section example then used 10% goat serum and 2 μg/ml primary antibody overnight at 4°C (datasheet A05989-1). If staining is weak, first check that sections received uniform heating and cooling, then compare a longer retrieval interval on matched sections while monitoring tissue damage (standard IHC practice). Keep antibody concentration and DAB development consistent across that comparison so retrieval is the variable under test (standard IHC practice). The caption does not report a fixative, so this retrieval result does not establish performance for every fixation condition (datasheet A05989-1).
Could fixation explain weak or patchy SOCS5 staining?
Target-specific fixation sensitivity is unknown here: the selected paraffin-section caption does not state the fixative (datasheet A05989-1). Record fixative, fixation duration and specimen thickness for each block, then compare matched sections under the same retrieval and detection conditions (standard IHC practice). Inspect morphology alongside staining, because poor preservation or uneven processing can make a local loss of signal difficult to interpret (standard IHC practice). If processing differs between specimens, avoid treating their staining intensities as directly comparable until the conditions are matched or independently validated (standard IHC practice). Do not infer fixation tolerance from the reported tissue staining pattern or the absence of a transmembrane segment (HPA: tissue profile; UniProt O75159: topology).
Where should convincing SOCS5 staining appear in a paraffin section?
Look primarily for cytoplasmic staining: tissue IHC is described as ubiquitously cytoplasmic, while cell imaging places SOCS5 mainly in the cytosol (HPA: tissue IHC profile; HPA: subcellular). Additional nucleoplasmic and plasma-membrane localisation is reported in cell imaging, so minor signal there needs contextual review rather than automatic rejection (HPA: subcellular). UniProt does not annotate a subcellular location and reports no transmembrane segment, which limits a claim that sharply outlined membranes alone are diagnostic (UniProt O75159: localisation and topology). Compare positive cells with adjacent unstained cells in the same section and assess whether staining follows intact cellular boundaries (standard IHC practice). Review any predominantly nuclear or extracellular pattern against controls before scoring it as SOCS5 (HPA: subcellular; standard IHC practice).
How should unknown epitope placement affect SOCS5 IHC optimisation?
The supplied record identifies a single 536-residue chain, an SH2 domain at residues 381–476 and a SOCS box at 471–520 (UniProt O75159: processing and domains). It lists 0 isoforms, but that annotation does not locate this antibody's epitope or prove that every possible variant is recognised (UniProt O75159: isoforms; datasheet A05989-1: epitope unspecified). Without an epitope map, do not attribute weak staining to a particular domain being masked by processing (datasheet A05989-1: epitope unspecified). Optimise retrieval and primary-antibody conditions using matched sections, then judge the resulting pattern against cellular morphology and controls (standard IHC practice). If an unexpected compartment dominates, seek independent specificity evidence before assigning it to an SOCS5 variant (HPA: subcellular; standard IHC practice).
How can IF help resolve an ambiguous SOCS5 IHC pattern?
Use IF as a complementary localisation check, pairing SOCS5 with a validated marker for the cell population under study; glandular cells are among the reported tissue-positive populations (HPA: tissue IHC). Choose spectrally separated fluorophores and check an unstained section in each channel, because tissue autofluorescence can resemble weak specific signal (standard IF practice). For a proposed cytosolic pattern, use controlled permeabilisation appropriate to the antibody's unknown epitope, then check whether cell boundaries and marker staining remain interpretable (HPA: subcellular; datasheet A05989-1: epitope unspecified; standard IF practice). Include single-stain controls when multiplexing to assess channel bleed-through (standard IF practice). Interpret any IF colocalisation alongside the paraffin-section morphology and chromogenic controls, since the supplied IHC caption does not validate an IF protocol for this antibody (datasheet A05989-1).
What should I check when SOCS5 DAB staining is widespread?
The selected example uses a peroxidase-linked secondary antibody and DAB, so first inspect a no-primary control for signal arising from the detection workflow (datasheet A05989-1; standard IHC practice). Apply an endogenous peroxidase block and check whether excessive DAB development or incomplete washing accounts for diffuse colour (standard IHC practice). The example used 10% goat serum for blocking and 2 μg/ml primary antibody overnight at 4°C; use these as documented starting conditions, then titrate on matched sections if background persists (datasheet A05989-1). Review pigment, damaged edges and necrotic regions separately from intact cells before scoring (standard IHC practice). Genuine signal should be evaluated as a cellular pattern, chiefly cytoplasmic, rather than uniform deposit across tissue and empty spaces (HPA: tissue IHC profile; standard IHC practice).
How should I quantify SOCS5 staining across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring; the reported tissue IHC pattern is cytoplasmic, and expression varies among listed cell types (HPA: tissue IHC profile). For intact target cells, record the percentage positive and an intensity grade, then calculate an H-score if intensity differences are central to the comparison (standard IHC practice). For a spatial question, report positive-cell density per mm² of evaluable tissue and state how that area was selected (standard IHC practice). Normalise counts to the number of eligible cells or measured tissue area, and compare specimens stained with the same retrieval, antibody and DAB conditions (standard IHC practice). Exclude necrosis, section folds and edge artefacts by a rule set before reviewing group labels (standard IHC practice).
When is a SOCS5-positive result convincing rather than artefactual?
A convincing result combines staining in intact cells, a predominantly cytoplasmic distribution and agreement with independently supported cell-type context (HPA: tissue IHC profile; HPA: subcellular; standard IHC practice). High staining is reported in adrenal and prostate glandular cells, whereas cervix glandular cells are reported as not detected; these observations can inform control selection without guaranteeing performance for this antibody (HPA: tissue IHC). Question signal confined to cut edges, necrotic areas or cell-free deposits, and check a no-primary control for endogenous peroxidase or detection-related colour (standard IHC practice). Predominantly extracellular staining or a membrane-only outline needs additional evidence given the mainly cytosolic localisation and absence of a transmembrane segment (HPA: subcellular; UniProt O75159: topology). Treat the tissue atlas pattern as provisional because its approved reliability is pending external verification (HPA: reliability).
Boster reagents

Best SOCS5 / Suppressor of cytokine signaling 5 IHC Antibodies

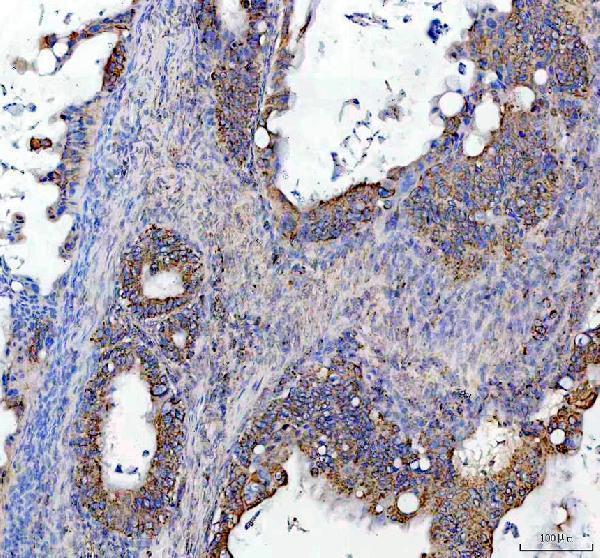
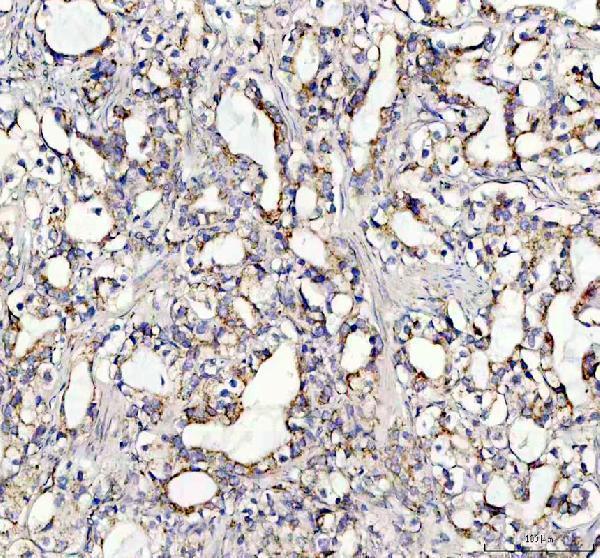
A05989-1 has real IHC data from human paraffin-embedded ovarian cancer and prostatic acinar adenocarcinoma sections; catalog reactivity also lists mouse and rat (IHC image captions; catalog reactivity).

Real IHC data IHC analysis of SOCS5 using anti-SOCS5 antibody (A05989-1). SOCS5 was detected in a paraffin-embedded section of human ovarican cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-SOCS5 Antibody (A05989-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-SOCS5 Antibody ®
Cat # A05989-1

A05989-1 will render with its own IHC figure from a human paraffin-embedded ovarian cancer section (card figure caption). A second catalog caption documents human paraffin-embedded prostatic acinar adenocarcinoma; the application list includes IHC but no IF/ICC (catalog image captions; catalog applications).

Which to pick: Choose A05989-1 for paraffin-section IHC: its caption reports EDTA retrieval at pH 8.0 and 2 μg/ml primary antibody; the fixative is unreported (A05989-1 IHC image caption). No IF/ICC-validated SKU is listed, and A05989-1’s clonality is unreported (catalog applications; catalog clone field). A05989-1 lists mouse and rat reactivity, but its supplied IHC captions document human tissue only, so cross-species tissue IHC requires validation (catalog reactivity; IHC image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry O75159 (SOCS5_HUMAN, Suppressor of cytokine signaling 5).
  2. Human Protein Atlas. SOCS5 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. SOCS5 subcellular location (ICC-IF): Mainly localized to the cytosol. In addition localized to the nucleoplasm and plasma membrane..
  4. Human Protein Atlas. SOCS5 antibody validation summary (2 antibodies).
  5. Mechanistic insights into SOCS5-related DNA damage and cellular senescence in diabetic retinopathy. Cell death discovery 2026 — PMC13168495.
  6. SOCS5 knockdown suppresses metastasis of hepatocellular carcinoma by ameliorating HIF-1α-dependent mitochondrial damage. Cell death & disease 2022 — PMC9626553.
  7. SOCS5 inhibition induces autophagy to impair metastasis in hepatocellular carcinoma cells via the PI3K/Akt/mTOR pathway. Cell death & disease 2019 — PMC6690952.
  8. Suppressor of cytokine signaling (SOCS) genes are silenced by DNA hypermethylation and histone deacetylation and regulate response to radiotherapy in cervical cancer cells. PloS one 2015 — PMC4388447.
  9. PubMed PMID:10773671 — UniProt-cited evidence.
  10. PubMed PMID:9734811 — UniProt-cited evidence.
  11. PubMed PMID:11230166 — UniProt-cited evidence.