SPA17 / Sperm surface protein Sp17 · IHC design guide

Design Immunohistochemistry for SPA17

Plan SPA17 IHC on paraffin sections with spermatids or ciliated cells as positive comparators (HPA tissue IHC). This guide covers fixation consistency, the 2–5 μg/ml antibody range (datasheet A07969), and interpretation of cytoplasmic and membranous staining (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for SPA17 (IHC for SPA17): expected localisation Cytoplasmic and membranous in seminiferous duct cells and motile cilia (HPA tissue IHC), antibody A07969, validated IHC image, and IHC protocol steps
Printable SPA17 IHC protocol sheet — expected localisation Cytoplasmic and membranous in seminiferous duct cells and motile cilia (HPA tissue IHC), antibody A07969, controls and protocol steps. Open the full SPA17 IHC guide →

SPA17 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic and membranous in seminiferous duct cells and motile cilia (HPA tissue IHC)
Staining pattern Seminiferous duct cells: cytoplasmic/membranous; motile cilia (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A07969)
Positive control ⓘ Bronchus+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Presumed off-target binding may mimic SPA17 staining (HPA tissue IHC)
Regulation Tissue-enhanced RNA in testis and Fallopian tube (HPA tissue RNA)
Isoform / epitope No isoforms; full-length chain, epitope side unresolved (UniProt)
Section 1

Recommended SPA17 IHC & IF Protocols

The catalog antibody protocol is paired with one published chromogenic IHC protocol for SP17 staining in Merkel cell carcinoma sections (PMC8130841).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human placenta tissue; fixative not specified (datasheet A07969)
FixationImage fixative and duration unreported (datasheet A07969); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A07969); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A07969)
Primary antibodyRabbit anti-SPA17, 2-5 μg/ml (datasheet A07969)
Primary incubationOvernight at 4 °C (datasheet A07969)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A07969)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultSPA17-positive staining in ciliated cells (cilia axoneme) of bronchus (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic and membranous expression in cells of seminiferous ducts and in motile cilia. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval (datasheet A07969); the published protocol reports retrieval without specifying conditions (PMC8130841 methods).
Section 2

What Is the Expected SPA17 Staining Pattern?

In paraffin-section IHC, expect SPA17 in late spermatids and along motile cilia, with cytoplasmic and membranous staining in seminiferous ducts (HPA: tissue IHC, Enhanced). UniProt describes SPA17 as membrane-associated despite reporting no transmembrane segment (UniProt Q15506: subcellular location and topology). HPA reports medium agreement between staining and RNA data and notes presumed off-target binding that was disregarded (HPA: reliability description).

What am I looking at on my slide?
Strong staining in elongated or late spermatids, or along cilia in bronchus, nasopharynx, or fallopian tube (HPA: tissue IHC).This matches HPA's High staining in those cells. Assess the relevant cells and structures, since HPA describes a cytoplasmic and membranous pattern in seminiferous ducts and motile cilia (HPA: tissue IHC).
A predominantly nuclear signal replaces the expected spermatid or ciliary pattern (HPA: tissue IHC).Nuclear staining is outside the supplied HPA tissue profile and UniProt membrane annotation (HPA: tissue IHC; UniProt Q15506: subcellular location). Treat it as suspect until controls support specificity; review counterstain and detection controls (general IHC practice).
Strong signal appears in adipocytes of adipose tissue or glandular cells of adrenal gland (HPA: Not detected in those cells).These are discordant cell-level results, not automatic proof of SPA17 expression. Check antibody-dependent staining and endogenous detection activity with appropriate controls (general IHC practice); HPA notes presumed off-target binding in its tissue assessment (HPA: reliability description).
Diffuse colour covers tissue and obscures cell boundaries or cilia (general IHC observation).A diffuse field cannot establish the cell-restricted pattern described by HPA (HPA: tissue IHC). Compare a no-primary control and review blocking, washing, and detection exposure as general IHC workflow checks; the supplied sources do not identify a SPA17-specific cause.
No staining is visible in late spermatids or ciliated bronchial epithelium (HPA: High in those cells).The expected positive reference has failed, so a negative test section is hard to interpret. Confirm that the reference contains the stated cells, then check the antibody's IHC conditions and detection controls (general IHC practice). HPA levels do not diagnose the failure.
💡Expected SPA17 appearanceCall a result convincing when staining is strong in late spermatids or motile cilia, with the reported cytoplasmic and membranous distribution; diffuse or unexpected-cell staining is suspect (HPA: tissue IHC and reliability description).
How each factor affects the staining
Cell identity in the sectionHPA reports High staining in elongated or late spermatids and ciliated cells of bronchus, nasopharynx, and fallopian tube (HPA: tissue IHC). Score those cells specifically; a section lacking them cannot serve as the same positive reference (general IHC interpretation).
Tissue-dependent expressionKidney glomerular cells are High, while endometrial and epididymal glandular cells are Medium (HPA: tissue IHC). Use each tissue's stated cell population and level when comparing sections; a single intensity threshold across these tissues would ignore the reported differences.
Antibody evidence and limitsHPA lists HPA037568 as IHC Enhanced and its overall tissue reliability as Enhanced, while describing medium agreement with RNA and disregarded presumed off-target binding (HPA: antibody validation and reliability description). Interpret isolated unexpected staining cautiously.
Topology and processingSPA17 is annotated as membrane-associated, with no transmembrane segment, signal peptide, propeptide, or listed glycosylation sites; the recorded chain spans residues 1–151 (UniProt Q15506). These annotations alone do not predict antigen retrieval requirements or fixation sensitivity.
IF/ICC Q&A: Where is SPA17 reported?HPA reports Golgi apparatus and sperm principal piece as approved main locations, with vesicles as an additional approved location (HPA: subcellular ICC-IF). These IF observations provide context; they are not a paraffin-section IHC protocol or a substitute for the tissue pattern.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
The positive testis section appears negative (HPA: High in elongated or late spermatids).The examined field may lack the relevant spermatids, or the IHC detection workflow may have failed (general IHC practice). The HPA pattern alone cannot distinguish these causes.Verify the cell population on the counterstained section, then check an established positive control and the IHC-validated antibody's stated conditions (general IHC practice).
Cilia look negative, but nearby respiratory cells stain (HPA: High in bronchial and nasopharyngeal cilia).The signal may be assigned to the wrong structure, or it may be nonspecific; HPA identifies the cilia axoneme as the High-staining site (HPA: tissue IHC).Inspect well-preserved ciliated borders at higher magnification and compare controls before scoring the respiratory signal as SPA17 (general IHC practice).
Adipose adipocytes or adrenal glandular cells stain strongly (HPA: Not detected in those cells).This conflicts with HPA's reported negatives. Antibody cross-reactivity or endogenous detection activity is possible (general IHC practice); HPA also notes presumed off-target binding (HPA: reliability description).Compare a no-primary control and a tissue positive reference, then reassess cell identity and the staining pattern (general IHC practice).
Colour is diffuse across the section and the expected structures are hard to distinguish (general IHC observation).Background from the detection workflow is possible (general IHC practice). Neither HPA nor UniProt identifies a SPA17-specific mechanism for diffuse colour.Check the no-primary control and review blocking, washing, and detection development against the laboratory's IHC procedure (general IHC practice).
Only nuclei stain in an otherwise readable section (general IHC observation).A nuclear-only result does not match HPA's cytoplasmic, membranous, and ciliary tissue profile or UniProt's membrane annotation (HPA: tissue IHC; UniProt Q15506: subcellular location).Recheck the counterstain and negative control, then compare a known positive tissue before assigning the nuclear signal to SPA17 (general IHC practice).
A weak or negative result is attributed to fixation or antigen retrieval (general IHC interpretation).The supplied HPA and UniProt records give no SPA17-specific fixation sensitivity or retrieval requirement. HPA staining levels and UniProt topology do not establish either effect.Report the observed result and controls. If troubleshooting the workflow, follow the IHC-validated antibody's documented conditions; do not infer a SPA17-specific fixation mechanism from these sources.

Sample controls for SPA17 IHC & IF

🧪Run testis first and require staining in elongated or late spermatids (HPA: High in testis elongated or late spermatids). Use adipose tissue as the negative tissue and assess adipocytes for background staining (HPA: Not detected in adipocytes); on the testis slide, compare spermatids with surrounding nonspermatid cells, which should remain at background for a cell-restricted result.
Positive control tissue: Bronchus (Ciliated cells (cilia axoneme), HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show SPA17 in A-431, U-251MG, U2OS, RPTEC/TERT1, hTERT-RPE1 (serum starved), Sperm, with annotated localisation: Golgi apparatus (approved), Principal piece (approved) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and a concentration-matched rabbit IgG isotype control alongside a SPA17 knockout sample or a validated immunizing-peptide block (selected-SKU caption: rabbit primary antibody). Quench endogenous peroxidase before HRP/DAB detection and inspect testis pigment or deposits that could be mistaken for chromogen (selected-SKU caption: HRP/DAB detection).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected-SKU paraffin-section caption does not state the fixative (selected-SKU caption: fixative not stated). Its documented IHC procedure uses heat retrieval in EDTA at pH 8.0, so start there and assess retrieval dependence experimentally (selected-SKU caption: EDTA heat retrieval); frozen sections have no supplied matched protocol, while ICC-IF images exist without evidence that tissue IF is easier (HPA: subcellular ICC-IF images). In testis, distinguish staining of elongated or late spermatids from nonspecific staining across the seminiferous tubule (HPA: High in elongated or late spermatids).

HPA tissue IHC evidence for SPA17

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data. Presumed off target binding observed and disregarded. Protein expression in respiratory epithelia can be correlated with lung RNA-seq data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Bronchus Ciliated cells (cilia axoneme) High Protein (IHC) HPA →
Fallopian tube Ciliated cells (cilia axoneme) High Protein (IHC) HPA →
Kidney Cells in glomeruli High Protein (IHC) HPA →
Nasopharynx Ciliated cells (cilia axoneme) High Protein (IHC) HPA →
Testis Elongated or late spermatids High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Caudate Glial cells Not detected Protein (IHC) HPA →
Section 3

Advanced SPA17 IHC Tips

Troubleshoot SPA17 staining in paraffin sections by checking retrieval, controls, cellular localisation and scoring before interpreting chromogenic signal.

Which retrieval conditions should I start with for SPA17 IHC?
Start with heat-mediated antigen retrieval in EDTA buffer at pH 8.0 for paraffin sections (datasheet A07969). The selected SPA17 tissue-IHC example used this retrieval before an overnight incubation at 4°C with 2 μg/ml primary antibody (datasheet A07969). If staining is weak, vary heating duration on matched sections while keeping EDTA at pH 8.0 as the reference condition (standard IHC practice). Include a testis section with late spermatids and a no-primary control in the same run (HPA: High in elongated or late spermatids; standard IHC practice). Excessive retrieval can damage section morphology and make localisation difficult to assess (standard IHC practice).
How should I investigate a weak SPA17 result after fixation?
The selected caption describes a paraffin-embedded section but does not state its fixative, so target-specific fixation sensitivity is unknown (datasheet A07969: fixative not stated). Record the fixative and fixation time for every specimen, then compare matched sections processed with the same retrieval and detection settings (standard IHC practice). Start with EDTA at pH 8.0 and 2 μg/ml primary antibody overnight at 4°C, as documented for the catalog antibody (datasheet A07969). Check tissue preservation and staining in late spermatids before changing antibody concentration (HPA: High in elongated or late spermatids; standard IHC practice). Report any fixation comparison as an experiment on your specimens, rather than an established SPA17-specific effect.
Where should convincing SPA17 chromogenic staining appear?
Assess the stained cell and its internal pattern together: HPA describes cytoplasmic and membranous expression in seminiferous ducts and motile cilia (HPA: tissue IHC profile). High staining is reported in testicular elongated or late spermatids and ciliated cells of the bronchus, fallopian tube and nasopharynx (HPA: tissue IHC). UniProt calls SPA17 membrane associated but lists no transmembrane segment, so a sharply outlined cell membrane is not a required IHC pattern (UniProt Q15506: subcellular location and topology). HPA subcellular imaging also places SPA17 at the Golgi apparatus, sperm principal piece and vesicles (HPA: subcellular). Compare compartments at the same magnification and retrieval setting before calling diffuse DAB signal positive (standard IHC practice).
Could an isoform or hidden epitope explain discordant SPA17 staining?
The supplied UniProt record lists one 151-amino-acid chain and 0 annotated isoforms, glycosylation sites or modified residues (UniProt Q15506: processing, isoforms and PTMs). Those annotations do not identify the catalog antibody’s epitope or establish how fixation affects its accessibility (UniProt Q15506; datasheet A07969: epitope and fixative not supplied). Compare adjacent sections using the documented EDTA pH 8.0 retrieval and a controlled change in heating duration (datasheet A07969; standard IHC practice). If antibodies to different documented epitopes are available, compare their cell-level patterns without assuming either is isoform specific (standard IHC practice). Preserve late-spermatid morphology when judging discordance (HPA: High in elongated or late spermatids).
How can IF help resolve an ambiguous SPA17 IHC pattern?
Use IF/ICC as a separate localisation check, while keeping the chromogenic paraffin-section result anchored to the catalog antibody’s documented IHC conditions (datasheet A07969). Multiplex SPA17 with a validated ciliated-cell marker or a late-spermatid marker, chosen for the specimen, to test the expected cell identity (HPA: High in ciliated cells and elongated or late spermatids; standard IF practice). Choose spectrally separated fluorophores and inspect an unstained section for tissue autofluorescence before interpreting overlap (standard IF practice). Because SPA17 has no annotated transmembrane segment, first establish whether the antibody epitope is accessible without permeabilisation; compare that condition with mild permeabilisation if intracellular staining is sought (UniProt Q15506: topology; standard IF practice). The IHC caption does not provide IF fixation conditions (datasheet A07969).
What should I adjust when SPA17 DAB staining looks widespread?
Run no-primary and secondary-only controls to identify detection-system background before changing the SPA17 primary antibody (standard IHC practice). The selected example used 10% goat serum blocking, 2 μg/ml primary antibody overnight at 4°C, and a peroxidase-based DAB readout (datasheet A07969). Check that the routine peroxidase block, washes and DAB development are controlled across matched sections (standard IHC practice). HPA reports presumed off-target binding that was disregarded, so widespread staining deserves comparison with the documented cell-level pattern (HPA: reliability description and tissue IHC profile). Evaluate background in an HPA-listed undetected cell population alongside late spermatids in the same run when suitable specimens are available (HPA: tissue IHC; standard IHC practice).
How should I score SPA17 staining across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the compartment and cell population before scoring: late spermatids and ciliated-cell axonemes are reported high-staining populations (HPA: tissue IHC). For a cellular comparison, record the percentage of positive eligible cells and an H-score from staining intensity and percentage; for discrete ciliated profiles, consider positive-profile density per mm² of evaluable epithelium (standard IHC practice). Normalise to eligible cells or intact epithelial area, rather than total section area, and exclude folds, missing tissue and necrosis (standard IHC practice). Keep retrieval at EDTA pH 8.0 and detection timing consistent across the scored batch (datasheet A07969; standard IHC practice). Report compartment-specific scores separately because HPA describes both cytoplasmic and membranous staining (HPA: tissue IHC profile).
When is an apparent SPA17-positive focus likely to be artefact?
Prioritise staining in morphologically identifiable late spermatids or motile cilia, where HPA reports high SPA17 signal, and assess cytoplasmic or membranous localisation in context (HPA: tissue IHC profile). A positive focus confined to a section edge, fold or necrotic region needs review on an adjacent section before interpretation (standard IHC practice). Diffuse DAB staining in a no-primary control points to detection background, including residual endogenous enzyme activity, rather than SPA17-specific binding (standard IHC practice). HPA assigns enhanced reliability but also notes presumed off-target binding and only medium consistency with RNA data (HPA: reliability description). Record unexpected cell types and compartments separately, then seek agreement with tissue morphology and an independent control (standard IHC practice).
Boster reagents

Best SPA17 / Sperm surface protein Sp17 IHC Antibodies

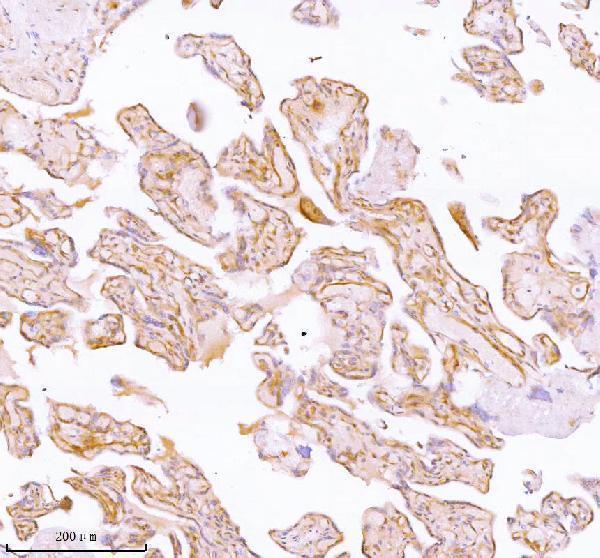
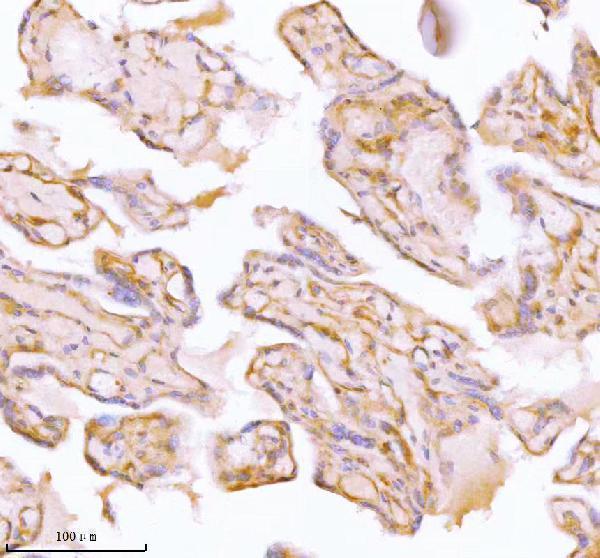
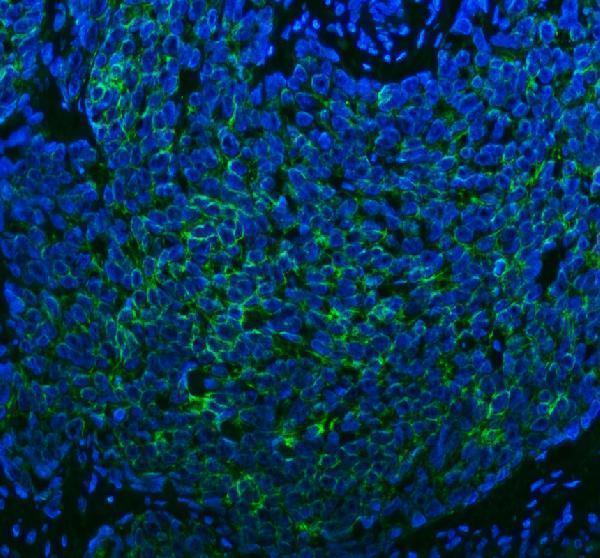
A07969 has IHC images from human paraffin sections of placenta and rectum adenocarcinoma, plus IF images from human cervical cancer and ovarian sections (A07969 image captions).

Real IHC data IHC analysis of SPA17 using anti-SPA17 antibody (A07969). SPA17 was detected in a paraffin-embedded section of human placenta tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-SPA17 Antibody (A07969) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-SPA17 Antibody ®
Cat # A07969

A07969 is listed for IHC and IF, with human, mouse and rat reactivity (catalog applications and reactivity). Its IHC images show human placenta and rectum adenocarcinoma; its IF images show human cervical cancer and ovarian tissue (A07969 image captions).

Which to pick: For tissue IHC, choose A07969: its paraffin-section images used EDTA retrieval at pH 8.0 and 2 μg/ml primary antibody; the fixative is unreported (A07969 IHC captions). For IF, A07969 has human tissue images at 5 μg/ml; ICC validation is not listed (A07969 IF captions; catalog applications). For cross-species IHC, A07969 lists human, mouse and rat reactivity, though its supplied IHC images show human tissue only; it is rabbit-hosted, and clonality is unreported (catalog host and reactivity; A07969 IHC captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q15506 (SP17_HUMAN, Sperm surface protein Sp17).
  2. Human Protein Atlas. SPA17 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. SPA17 subcellular location (ICC-IF): Mainly localized to the Golgi apparatus and principal piece. In addition localized to vesicles..
  4. Human Protein Atlas. SPA17 antibody validation summary (1 antibodies).
  5. Sperm Protein Antigen 17 Expression Correlates With Lymph Node Metastasis and Worse Overall Survival in Patients With Breast Cancer. Frontiers in oncology 2019 — PMC6685407.
  6. The SPA17-AXL axis drives melanoma aggressiveness and SPA17-targeting vaccination exhibits antitumor efficacy. Frontiers in immunology 2026 — PMC13597369.
  7. Cancer-testis antigens as biomarkers for Merkel cell carcinoma: Pitfalls and opportunities. Journal of cutaneous pathology 2019 — PMC8130841.
  8. PubMed PMID:8688458 — UniProt-cited evidence.
  9. PubMed PMID:12393185 — UniProt-cited evidence.
  10. PubMed PMID:14702039 — UniProt-cited evidence.