SRI / Sorcin · IHC design guide

Design Immunohistochemistry for SRI

Plan SRI staining in paraffin sections using brain glia and fallopian tube ciliated cells as positive tissue controls (HPA tissue IHC). The IHC-validated antibody has a paraffin-section range of 0.5–1 µg/ml (datasheet A00222).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for SRI (IHC for SRI): expected localisation Tissue: cytoplasmic and nuclear; SR membrane: molecular (HPA tissue IHC; UniProt), antibody A00222, validated IHC image, and IHC protocol steps
Printable SRI IHC protocol sheet — expected localisation Tissue: cytoplasmic and nuclear; SR membrane: molecular (HPA tissue IHC; UniProt), antibody A00222, controls and protocol steps. Open the full SRI IHC guide →

SRI Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Tissue: cytoplasmic and nuclear; SR membrane: molecular (HPA tissue IHC; UniProt)
Staining pattern Brain glia and ciliated cells show cytoplasmic/nuclear staining (HPA tissue IHC)
Antigen retrieval Citrate pH 6 HIER, heat-mediated (datasheet A00222)
Positive control ⓘ Appendix+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep paraffin-section fixation consistent (standard IHC practice; not target-specific); Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A00222)
Caveat Heart: UniProt detection versus HPA IHC non-detection (UniProt; HPA tissue IHC)
Regulation No expression regulator specified (UniProt)
Isoform / epitope 3 isoforms; epitope coverage is unspecified (UniProt)
Section 1

Recommended SRI IHC & IF Protocols

The catalog antibody protocol (datasheet A00222) is accompanied by three published SRI IHC protocols (PMC13115428; PMC12257818; PMC11241191).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human intestinal cancer tissues; fixative not specified (datasheet A00222)
FixationImage fixative and duration unreported (datasheet A00222); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: Citrate pH 6, 20 min (datasheet A00222)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A00222)
Primary antibodyRabbit anti-SRI, 0.5-1μg/ml (datasheet A00222)
Primary incubationOvernight at 4 °C (datasheet A00222)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A00222)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultSRI-positive staining in enterocytes - Microvilli of appendix (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic and nuclear expression expression in the brain, urinary bladder, fallopian tube and the gastrointestinal tract. No signal in the no-primary control.
💡Decision noteStart with heat retrieval in citrate at pH 6 (datasheet A00222). Tris at pH 9 is a published alternative (PMC13115428).
Section 2

What Is the Expected SRI Staining Pattern?

SRI is cytoplasmic and can relocate to the sarcoplasmic reticulum membrane as calcium rises; it has no transmembrane segment (UniProt P30626). In tissue IHC, expect staining in selected glial, ciliated, enterocyte, endocrine, and decidual cells (HPA tissue IHC: High). HPA also reports nuclear expression in some tissues, with Enhanced IHC reliability but only medium agreement between staining and RNA data (HPA tissue IHC).

What am I looking at on my slide?
Strong signal in glial cells of caudate, cerebral cortex, or hippocampus, with staining centered on the cell body.This matches high SRI staining in those glial populations (HPA tissue IHC: High). Check cellular context before scoring nearby unstained cells as a failed run; the HPA result describes specific cells within each tissue.
Strong staining at enterocyte microvilli in appendix, in ciliated cell bodies of fallopian tube or nasopharynx, or in rectal endocrine cells.These are reported high-staining sites (HPA tissue IHC: High). Record the named cell population and visible compartment: a positive tissue section does not imply that every cell in that section should stain.
Nuclear signal appears alongside cytoplasmic staining in an appropriate tissue and cell population.Nuclear expression is described in the tissue profile (HPA tissue IHC); nucleoplasm is uncertain in ICC-IF, whereas cytosol is supported (HPA subcellular). Interpret isolated nuclear signal cautiously rather than treating every nucleus as a definitive SRI positive.
A compartment or cell population outside the reported pattern stains strongly, including cells scored Not detected by HPA.First suspect nonspecific binding, endogenous chromogenic activity, or a scoring error (general IHC practice). Compare with a no-primary control and tissue morphology; HPA's cell-specific calls provide a reference, not proof that every unexpected signal is artefactual.
The known-positive cell population is blank while the section and counterstain remain interpretable.A negative result in that run is inconclusive. Check antibody dilution, retrieval, detection reagents, and control tissue together (general IHC practice). Choose a reported high-staining population, such as caudate glia, for comparison (HPA tissue IHC: High).
💡Expected SRI appearanceCall a section positive when the reported cell population shows distinct, predominantly cytoplasmic staining, such as high signal in caudate glia or ciliated cell bodies (HPA tissue IHC: High); diffuse staining across HPA-negative populations is a possible false positive (HPA tissue IHC: Not detected; general IHC practice).
How each factor affects the staining
Which tissue and cell population anchor interpretation?Use a reported high-staining population as a positive reference, such as appendix enterocyte microvilli or hippocampal glia (HPA tissue IHC: High). Adipocytes and esophageal squamous epithelial cells are reported Not detected and can help assess unwanted staining (HPA tissue IHC).
How should the heart result be read?Sorcin is detected in cardiac myocytes and participates in cardiac calcium handling (UniProt P30626), yet HPA scores heart muscle cardiomyocytes Not detected by tissue IHC (HPA tissue IHC). Do not require a positive heart section to validate this IHC run.
How strong is the pattern evidence?HPA assigns Enhanced IHC status to HPA019004 and HPA073666 (HPA antibodies). The tissue profile reports medium agreement with RNA expression and support from similar staining by paired antibodies (HPA tissue IHC). These ratings support the reported pattern without making every compartment call equally certain.
IF/ICC: where should fluorescence appear?Expect supported cytosolic signal; nucleoplasmic localization is marked uncertain in the ICC-IF record (HPA subcellular). UniProt also places SRI in the cytoplasm and describes calcium-responsive association with the sarcoplasmic reticulum membrane (UniProt P30626). Interpret IF/ICC on its separate guide page.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No chromogenic signal in caudate glia or fallopian tube ciliated cell bodies.These populations are reported High (HPA tissue IHC); a blank control section could reflect a run or detection problem (general IHC practice).Check the no-primary and positive tissue controls, then verify retrieval, antibody dilution, and detection steps against the assay instructions (general IHC practice). No SRI-specific retrieval condition is supplied.
Brown deposit spreads across the section, obscuring individual cells.Diffuse signal can arise from inadequate blocking, excess reagent, or incomplete washing (general IHC practice); it cannot establish SRI localization.Inspect a no-primary control, review blocking and wash steps, and score only cell-associated signal that remains distinguishable from background (general IHC practice).
Adipocytes or esophageal squamous epithelial cells stain strongly.Both populations are scored Not detected (HPA tissue IHC). Unexpected signal warrants checking nonspecific binding or endogenous chromogenic activity (general IHC practice).Compare a no-primary control and cell morphology, then review blocking and detection controls before assigning that signal to SRI (general IHC practice).
Only nuclei stain, including nuclei throughout otherwise negative tissue.The tissue profile includes nuclear expression (HPA tissue IHC), but ICC-IF labels nucleoplasmic localization uncertain (HPA subcellular); widespread nuclear signal needs validation.Compare staining in reported positive and negative cell populations, inspect the no-primary control, and avoid scoring nuclei alone as definitive positives (HPA tissue IHC; general IHC practice).
Heart muscle cardiomyocytes are negative despite an interpretable slide.HPA reports these cells as Not detected by tissue IHC (HPA tissue IHC), although UniProt reports Sorcin in cardiac myocytes (UniProt P30626).Use a reported high-staining population to assess assay performance; document the heart result as a source-specific discrepancy rather than assuming technical failure (HPA tissue IHC; UniProt P30626).
The positive tissue stains, but the apparent signal lies in a different cell population than expected.HPA's High and Not detected calls apply to named cell populations (HPA tissue IHC); mistaken cell identification or nonspecific staining can mislead interpretation (general IHC practice).Recheck morphology and counterstain, compare a no-primary control, and record the precise stained population and compartment before scoring (general IHC practice).

Sample controls for SRI IHC & IF

🧪Run appendix first: enterocyte microvilli should stain (HPA: High in appendix enterocytes–microvilli). Use esophagus as the negative tissue: its squamous epithelial cells are listed as not detected (HPA: Not detected in esophageal squamous epithelial cells). On the positive slide, neighboring cells without specific staining should show background-level signal; the supplied HPA rows do not establish a particular internal negative cell type.
Positive control tissue: Appendix (Enterocytes - Microvilli, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show SRI in A-431, U-251MG, U2OS, NIH 3T3, with annotated localisation: Nucleoplasm (uncertain), Cytosol (supported) (HPA subcellular).
Technical controls: Include no-primary (secondary-only) and concentration-matched rabbit IgG isotype controls, matching clonality if known (datasheet caption: rabbit anti-SRI antibody; clonality unreported). An SRI knockout specimen or a validated peptide-block condition can test target specificity; check endogenous peroxidase and biotin background when using the caption’s biotin–SABC/DAB detection in appendix tissue (A00222 caption: biotinylated secondary, SABC and DAB).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A00222 tissue-IHC caption does not state a fixative (A00222 caption: fixative unreported). The reported paraffin-section result used citrate retrieval at pH 6 for 20 minutes, but the evidence does not establish that retrieval is required or that frozen sections or IF are easier (A00222 caption: citrate retrieval, pH 6, 20 minutes). For appendix, inspect intestinal luminal material and background when scoring microvillar staining; endogenous biotin can affect the reported biotin-based detection method (HPA: High in appendix enterocytes–microvilli; A00222 caption: SABC/DAB detection).

HPA tissue IHC evidence for SRI

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data. Paired antibodies with high similarity supports the protein expression.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Appendix Enterocytes - Microvilli High Protein (IHC) HPA →
Caudate Glial cells High Protein (IHC) HPA →
Cerebral cortex Glial cells High Protein (IHC) HPA →
Fallopian tube Ciliated cells (cell body) High Protein (IHC) HPA →
Hippocampus Glial cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Esophagus Squamous epithelial cells Not detected Protein (IHC) HPA →
Gallbladder Glandular cells Not detected Protein (IHC) HPA →
Heart muscle Cardiomyocytes Not detected Protein (IHC) HPA →
Kidney Cells in glomeruli Not detected Protein (IHC) HPA →
Section 3

Advanced SRI IHC Tips

Use matched paraffin sections and compartment aware controls to troubleshoot SRI chromogenic IHC; interpret IF observations separately.

Which retrieval condition should I start with for SRI in paraffin sections?
Start with heat mediated antigen retrieval in citrate buffer at pH 6 for 20 minutes (datasheet A00222). The selected paraffin section example then used 10% goat serum and 1 μg/mL primary antibody overnight at 4°C (datasheet A00222). Keep section thickness, heating device, cooling interval, and detection settings constant while comparing adjacent sections (standard IHC practice). If staining remains weak, compare another retrieval condition on matched sections after checking the antibody and DAB detection steps (standard IHC practice). Judge improvement against tissue preservation and cytoplasmic signal, rather than staining intensity alone (UniProt P30626 localisation; standard IHC practice).
Could fixation explain weak or inconsistent SRI staining?
The selected paraffin section caption does not state its fixative, so target specific fixation sensitivity for SRI is unknown (datasheet A00222). Record fixative, duration, tissue thickness, processing, and storage before comparing specimens (standard IHC practice). For a fixation comparison, process matched samples consistently, use citrate retrieval at pH 6, and keep antibody incubation and detection constant (datasheet A00222; standard IHC practice). Assess morphology alongside staining, because tissue damage or weak signal alone does not establish a fixation effect (standard IHC practice). Include one reference section across runs to detect changes in the staining procedure (standard IHC practice).
How should I assess nuclear and cytoplasmic SRI staining?
Assess cytoplasmic staining first, because SRI is annotated in the cytoplasm and can relocate to the sarcoplasmic reticulum membrane when calcium rises (UniProt P30626 localisation). Tissue IHC also describes cytoplasmic and nuclear expression in several organs, including the gastrointestinal tract (HPA tissue IHC). However, the subcellular assessment supports cytosol while marking nucleoplasm as uncertain (HPA subcellular). Score nuclear and cytoplasmic staining separately, using the same counterstain and scoring thresholds across matched sections (standard IHC practice). Treat nuclear only staining cautiously until it repeats with appropriate controls and preserved morphology (HPA subcellular; standard IHC practice).
Can this antibody distinguish SRI isoforms or membrane associated SRI?
SRI has 3 listed isoforms, but the supplied product caption does not map this antibody’s epitope to any isoform (UniProt P30626 isoforms; datasheet A00222). Therefore, do not label a stained compartment or cell population as isoform specific from this IHC result alone (standard IHC interpretation). The annotated protein has no transmembrane segment and contains 4 EF hand regions (UniProt P30626 topology and domains). Its calcium responsive association with sarcoplasmic reticulum membrane does not identify which antibody epitope is accessible after processing (UniProt P30626 localisation; standard IHC practice). Seek an independently mapped epitope before making isoform or epitope specific claims (standard IHC practice).
How should I check SRI localisation by multiplex IF?
On a separate IF assay, pair SRI with a validated marker for the expected cell type, such as glial cells in brain sections (HPA tissue IHC: High in glial cells; standard IF practice). Choose spectrally separated fluorophores and inspect unstained tissue for autofluorescence before assigning a weak SRI signal (standard IF practice). Because supported localisation includes cytosol, optimise permeabilisation for intracellular access while preserving morphology (HPA subcellular; standard IF practice). SRI can associate with sarcoplasmic reticulum membrane, but the supplied evidence does not define this antibody’s epitope side (UniProt P30626 localisation; datasheet A00222). Confirm apparent overlap in individual channels and matched controls (standard IF practice).
What should I change if SRI IHC shows diffuse background?
First compare a no primary control with the stained section to locate background from secondary detection or tissue chemistry (standard IHC practice). The selected example used 10% goat serum, biotinylated secondary antibody, streptavidin biotin detection, and DAB (datasheet A00222). With that detection chemistry, check endogenous peroxidase and biotin contributions using appropriate controls, then optimise blocking and washes (standard IHC practice). If background persists, titrate the primary around the documented 1 μg/mL condition on adjacent sections (datasheet A00222; standard IHC practice). Retain a positive reference while adjusting detection so reduced background does not conceal genuine cytoplasmic staining (UniProt P30626 localisation; standard IHC practice).
How can I quantify SRI staining across tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, then report an H score or percentage of positive cells for chromogenic SRI staining (standard IHC practice). If comparing spatial abundance, count positive cells per mm² of viable tissue and report the analysed area (standard IHC practice). Normalise to the number of eligible cells or viable tissue area, as appropriate, rather than the whole image field (standard IHC practice). Score cytoplasmic and nuclear signals separately because cytosol is supported while nucleoplasm remains uncertain (HPA subcellular). Keep retrieval, DAB development, imaging, and thresholds consistent, with blinded review of matched sections (standard IHC practice).
Which SRI staining patterns warrant a specificity check?
A reproducible cytoplasmic pattern in an expected cell population is more persuasive than isolated staining at section edges or damaged tissue (UniProt P30626 localisation; standard IHC practice). High staining is reported in rectal endocrine cells and brain glial cells, whereas cardiomyocytes were not detected in the cited tissue IHC dataset (HPA tissue IHC). That cardiomyocyte result should be interpreted alongside the separate report of SRI detection in cardiac myocytes (UniProt P30626 tissue specificity). Check nuclear only staining carefully because nucleoplasm is marked uncertain (HPA subcellular). Exclude necrosis, edge effects, and endogenous enzyme signal with morphology and staining controls before calling a positive result (standard IHC practice).
Boster reagents

Best SRI / Sorcin IHC Antibodies

A00222 has human paraffin-section IHC images, while both antibodies have cell IF images (catalog image captions). Both list Human, Mouse, and Rat reactivity (catalog reactivity).

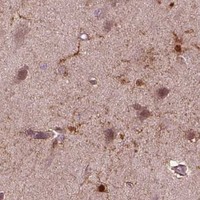
Real IHC data IHC analysis of SRI using anti-SRI antibody (A00222). SRI was detected in paraffin-embedded section of human intestinal cancer tissues. Heat mediated antigen retrieval was performed in citrate buffer (pH6, epitope retrieval solution) for 20 mins. The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml rabbit anti-SRI Antibody (A00222) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC)(Catalog # SA1022) with DAB as the chromogen.
Anti-SRI Antibody ®
Cat # A00222
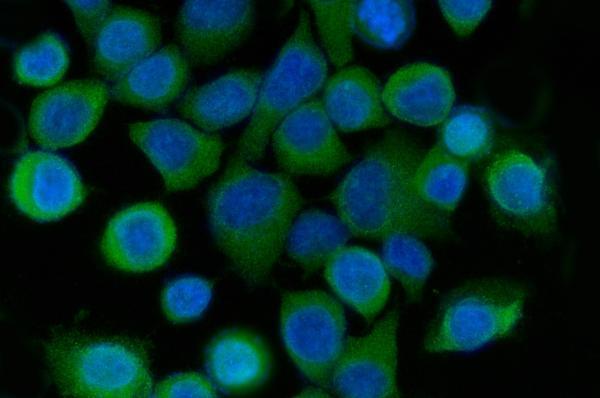
Real IF data IF analysis of SRI using anti-SRI antibody (A00222-2). SRI was detected in an immunocytochemical section of SiHa cells. Enzyme antigen retrieval was performed using IHC enzyme antigen retrieval reagent (AR0022) for 15 mins. The cells were blocked with 10% goat serum. And then incubated with 5 μg/mL rabbit anti-SRI Antibody (A00222-2) overnight at 4°C. DyLight®488 Conjugated Goat Anti-Rabbit IgG (BA1127) was used as secondary antibody at 1:100 dilution and incubated for 30 minutes at 37°C. The section was counterstained with DAPI. Visualize using a fluorescence microscope and filter sets appropriate for the label used.
Anti-SRI Antibody ®
Cat # A00222-2

A00222 lists IHC and IF/ICC; its images show paraffin sections of human intestinal, lung, and mammary cancer tissues and IF in U20S cells (A00222 applications; image captions). A00222-2 lists IF/ICC, with an IF image in SiHa cells (A00222-2 applications; IF image caption).

Which to pick: Choose A00222 for tissue IHC: its own captions document paraffin sections, but do not report the fixative (A00222 IHC image captions). For IF/ICC, both list those applications; A00222 has a U20S cell image and A00222-2 has a SiHa cell image (catalog applications; IF image captions). Both list Mouse and Rat reactivity, but neither has a supplied Mouse or Rat tissue IHC image; clonality is unreported for both (catalog reactivity; image captions; clone fields).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P30626 (SORCN_HUMAN, Sorcin).
  2. Human Protein Atlas. SRI tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. SRI subcellular location (ICC-IF): Localized to the nucleoplasm and cytosol..
  4. Human Protein Atlas. SRI antibody validation summary (2 antibodies).
  5. Protein Expression Analysis and Functional Characterization of Sorcin in Gallbladder Cancer. Cells 2026 — PMC13115428.
  6. Human epidermal growth factor receptor-2 gene expression positivity determined by silver in situ hybridization/immunohistochemistry methods and associated factors in a cohort of Sri Lankan patients with gastric adenocarcinoma: a prospective study. The Journal of international medical research 2023 — PMC9950620.
  7. Biochemical and Histological Characterization of Sorcin Overexpression in Patients Who Underwent Radical Prostatectomy. Urology research & practice 2025 — PMC12257818.
  8. Sorcin Inhibits Mitochondrial Apoptosis by Interacting with STAT3 via NF-κB Pathway. International journal of molecular sciences 2024 — PMC11241191.
  9. PubMed PMID:7873602 — UniProt-cited evidence.
  10. PubMed PMID:8561500 — UniProt-cited evidence.
  11. PubMed PMID:14702039 — UniProt-cited evidence.