This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan SRR chromogenic IHC in paraffin sections using 2–5 μg/ml catalog antibody (datasheet A02660-2). Assess cytoplasmic and nuclear staining with HPA-listed positive and undetected cell types as references (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic and nuclear tissue staining (HPA tissue IHC) | |
| Staining pattern | Purkinje cells stain; cytoplasmic/nuclear pattern across tissues (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet A02660-2) | |
| Positive control | Adipose tissue+4 more · see all | |
| Negative control | Oral mucosa+4 more · see all |
| Fixation | Keep fixation consistent across paraffin sections (standard IHC practice; not target-specific) | |
| Caveat | Cell-type variation: oral squamous cells are undetected (HPA tissue IHC) | |
| Regulation | Higher in schizophrenia DLPFC (UniProt) | |
| Isoform / epitope | One 1–340 chain; no isoforms or signal peptide annotated (UniProt) |
The catalog antibody uses EDTA pH 8.0 heat retrieval (datasheet: A02660-2). The published brain IHC protocols below use pH 6.0 retrieval (PMC10090982; PMC11337596).
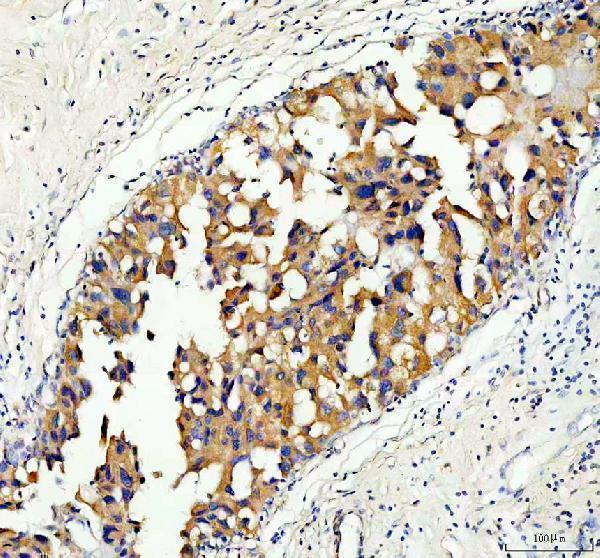
| Sample | Paraffin-embedded human breast cancer tissue; fixative not specified (datasheet A02660-2) |
| Fixation | Image fixative and duration unreported (datasheet A02660-2); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet A02660-2); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet A02660-2) |
| Primary antibody | Rabbit anti-SRR, 2-5 μg/ml (datasheet A02660-2) |
| Primary incubation | Overnight at 4 °C (datasheet A02660-2) |
| Detection | HRP-conjugated secondary, DAB chromogen (datasheet A02660-2) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | SRR-positive staining in adipocytes of adipose tissue (HPA tissue IHC: Medium). HPA tissue profile: Cytoplasmic and nuclear expression in several tissues. No signal in the no-primary control. |
In paraffin IHC, expect cytoplasmic and nuclear SRR staining in selected cells, including cerebellar Purkinje cells, caudate glia and cerebral cortical neurons (HPA tissue IHC: Medium; Approved, pending external verification). SRR has no transmembrane segment (UniProt Q9GZT4 topology). HPA’s separate ICC-IF record reports vesicles (HPA subcellular: approved); that finding does not define the paraffin IHC pattern.
| Purkinje cells, caudate glia or cortical neurons show discernible cytoplasmic and nuclear staining. | This fits HPA’s reported Medium staining in those cell populations and its broader cytoplasmic and nuclear IHC profile (HPA tissue IHC: Approved, pending external verification). Judge the identified cells against nearby tissue background; Medium is an HPA category, not a required numeric intensity. |
| A sharp cell-surface rim dominates while cytoplasmic and nuclear staining is absent. | A membrane-dominant result departs from the reported IHC profile (HPA tissue IHC: cytoplasmic and nuclear). SRR lacks a transmembrane segment (UniProt Q9GZT4 topology). Treat the rim as suspect, then compare control sections and antibody performance before assigning it to SRR. |
| Strong staining appears in oral squamous epithelium, ovarian stroma or smooth muscle cells. | HPA lists these specific cell populations as Not detected (HPA tissue IHC). Unexpected staining raises possible cross-reactivity or detection background; it does not, by itself, prove either. Confirm the cell identity and examine a detection-only control before interpreting a new biological pattern. |
| Brown signal spreads evenly across unrelated cells, extracellular areas and the section edge. | This distribution is difficult to reconcile with HPA’s cell-specific observations (HPA tissue IHC). Diffuse deposit can arise from nonspecific binding or chromogenic detection background (general IHC practice). Check background controls before scoring cytoplasmic or nuclear signal. |
| No staining is visible in a well-preserved cerebellar section containing identifiable Purkinje cells. | Purkinje cells are a reported Medium-positive population (HPA tissue IHC), so a blank result warrants a technical check. It is not definitive evidence that the sample lacks SRR: HPA rates its tissue profile Approved while noting that external verification is pending (HPA tissue IHC). |
| Tissue and cell selection | Choose an identifiable reported positive population when evaluating the stain: Purkinje cells, caudate glia and cortical neurons are Medium (HPA tissue IHC). Oral squamous epithelium, ovarian stroma and smooth muscle cells are listed as Not detected (HPA tissue IHC); these labels apply to those cells, not every cell in each organ. |
| Assay-specific localisation | Paraffin tissue IHC is reported as cytoplasmic and nuclear, whereas ICC-IF localisation is approved for vesicles (HPA tissue IHC; HPA subcellular). Keep the readouts distinct when interpreting a chromogenic section. UniProt gives no subcellular annotation for SRR (UniProt Q9GZT4). |
| Antibody validation | The supplied antibody list assigns IHC Approved to CAB015343 and ICC Approved to HPA007529 (HPA antibodies). Those statuses are application-specific; ICC approval does not establish paraffin IHC performance for that antibody. The overall tissue IHC profile remains pending external verification (HPA tissue IHC). |
| Topology and processing | SRR has no transmembrane segment, signal peptide or propeptide; the annotated chain spans residues 1–340 (UniProt Q9GZT4 topology and processing). These facts help flag a membrane-only interpretation, but they do not identify the catalog antibody’s epitope or predict how retrieval will affect staining. |
| Retrieval and chromogenic detection | Use the selected antibody’s documented paraffin IHC conditions as the starting point, and include controls for background and endogenous detection activity (general IHC practice). The supplied HPA and UniProt evidence establishes no SRR-specific retrieval requirement or fixation sensitivity; avoid attributing a weak result to either without comparative evidence. |
| Situation | Likely cause | Next action |
|---|---|---|
| A reported positive cell population is blank. | Purkinje cells, caudate glia and cortical neurons are Medium in HPA tissue IHC; absence of signal could reflect a staining or detection problem (HPA tissue IHC; general IHC practice). | Verify that the intended cells are present, review the antibody’s documented IHC conditions, and check a concurrently stained positive section and detection controls (general IHC practice). Reassess the result against HPA’s pending external verification status. |
| Signal forms a prominent membrane rim. | The pattern conflicts with HPA’s cytoplasmic and nuclear tissue IHC profile and lacks support from SRR topology (HPA tissue IHC; UniProt Q9GZT4 topology). Its cause remains unestablished. | Compare the rim with no-primary and other detection controls, then inspect whether identified positive cells also show the expected intracellular staining (general IHC practice; HPA tissue IHC). Do not score a rim alone as confirmed SRR. |
| A listed Not detected population stains strongly. | Strong staining in oral squamous epithelium, ovarian stroma or smooth muscle cells diverges from HPA’s cell-specific observations (HPA tissue IHC). Cross-reactivity or endogenous chromogenic activity are possibilities (general IHC practice). | Confirm which cells carry the deposit, inspect a no-primary control, and compare with a reported positive population on the same run (general IHC practice; HPA tissue IHC). Treat the discrepancy as unresolved if controls do not explain it. |
| The whole section has a brown haze. | A uniform haze obscures the cell-specific cytoplasmic and nuclear pattern reported by HPA (HPA tissue IHC). Nonspecific binding or detection background can cause diffuse colour (general IHC practice). | Review blocking, antibody concentration, washes and chromogen development; use a no-primary control to locate background introduced during detection (general IHC practice). Score cells only after their staining is separable from the haze. |
| Only one intracellular compartment is convincing. | HPA describes cytoplasmic and nuclear expression across several tissues, but does not require both compartments to be equally intense in every cell (HPA tissue IHC). A compartment difference alone has no established SRR-specific technical cause in the supplied evidence. | Record cytoplasmic and nuclear staining separately in identified cells, compare a reported positive population, and check background controls (HPA tissue IHC; general IHC practice). Avoid converting the ICC-IF vesicle call into an IHC scoring requirement (HPA subcellular). |
| Q: Should vesicular ICC-IF staining define a positive paraffin IHC result? | A: HPA approves vesicular localisation for ICC-IF, while its tissue IHC profile is cytoplasmic and nuclear (HPA subcellular; HPA tissue IHC). The supplied antibodies also carry separate ICC and IHC validation statuses (HPA antibodies). | Assess the chromogenic section using the tissue IHC cell and compartment pattern (HPA tissue IHC). Use the separate IF/ICC guide for fluorescence-specific interpretation; a vesicle-shaped IHC deposit alone does not establish SRR identity. |

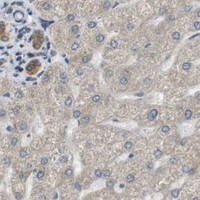


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Medium | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | Medium | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Medium | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | Medium | Protein (IHC) | HPA → |
| Caudate | Glial cells | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Oral mucosa | Squamous epithelial cells | Not detected | Protein (IHC) | HPA → |
| Ovary | Ovarian stroma cells | Not detected | Protein (IHC) | HPA → |
| Smooth muscle | Smooth muscle cells | Not detected | Protein (IHC) | HPA → |
| Spleen | Cells in red pulp | Not detected | Protein (IHC) | HPA → |
| Vagina | Squamous epithelial cells | Not detected | Protein (IHC) | HPA → |
Troubleshoot SRR staining in paraffin sections by checking retrieval, antibody specificity, cell type, and compartment before interpreting chromogenic signal.
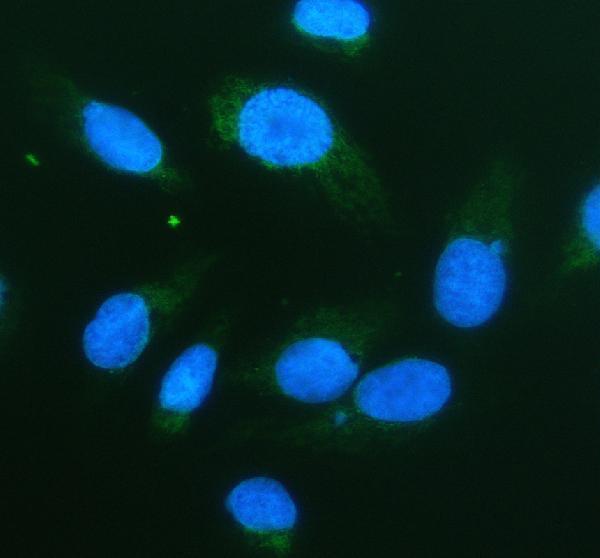
A02660-2 has SRR staining images from human paraffin-embedded breast cancer tissue and U2OS cells (IHC and IF captions). It lists Human, Mouse, and Rat reactivity (catalog: reactivity).
A02660-2 will render with its IHC image from a human breast cancer paraffin section (A02660-2 IHC caption). The same SKU lists IF/ICC applications and has an IF image from U2OS cells (catalog: applications; A02660-2 IF caption).
Which to pick: For tissue IHC, choose A02660-2: its image documents a human breast cancer paraffin section with EDTA retrieval at pH 8.0 and 2 μg/ml primary antibody; the fixative is unreported (A02660-2 IHC caption). For IF/ICC, A02660-2 lists both applications and shows U2OS-cell IF at 5 μg/ml (catalog: applications; A02660-2 IF caption). For cross-species work, A02660-2 lists Human, Mouse, and Rat reactivity, while its IHC-P dilution is specified for Human (catalog: reactivity and dilution).