TAB3 / TGF-beta-activated kinase 1 and MAP3K7-binding protein 3 · IHC design guide

Design Immunohistochemistry for TAB3

Plan TAB3 chromogenic IHC on paraffin sections with a human-reactive antibody validated at 5 μg/mL (datasheet: A05084-1). Assess cytoplasmic and nuclear staining using the reported tissue patterns, while accounting for low agreement between staining and RNA expression (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for TAB3 (IHC for TAB3): expected localisation Cytoplasmic and nuclear in several tissues (HPA tissue IHC), antibody A05084-1, validated IHC image, and IHC protocol steps
Printable TAB3 IHC protocol sheet — expected localisation Cytoplasmic and nuclear in several tissues (HPA tissue IHC), antibody A05084-1, controls and protocol steps. Open the full TAB3 IHC guide →

TAB3 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic and nuclear in several tissues (HPA tissue IHC)
Staining pattern Several cell types show cytoplasmic and nuclear staining (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ None in HPA (detected in all 45 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Low staining–RNA concordance; verify positive staining (HPA tissue IHC)
Regulation Constitutively elevated in some tumors (UniProt)
Isoform / epitope 2 isoforms; epitope coverage is unspecified (UniProt)
Section 1

Recommended TAB3 IHC & IF Protocols

The catalog antibody protocol is paired with a published TAB3 IHC protocol for colorectal cancer and adjacent tissues (PMC5739756).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleTissue sections; selected-image fixative not specified (standard IHC workflow)
FixationImage fixative and duration unreported (datasheet A05084-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-TAB3, 5 μg/mL (datasheet A05084-1)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultTAB3-positive staining in glandular cells of adrenal gland (HPA tissue IHC: Medium). HPA tissue profile: Cytoplasmic and nuclear expression in several tissues. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 HIER at 95–98 °C for 20 min (page retrieval rule). The published protocol specifies 0.01 M citrate without heating details (PMC5739756).
Section 2

What Is the Expected TAB3 Staining Pattern?

TAB3 staining in tissue is reported in the cytoplasm and nucleus across several tissues (HPA tissue IHC). Expect medium staining in the listed glandular, respiratory epithelial, hematopoietic, and neuronal cell populations (HPA tissue IHC). TAB3 has no transmembrane segment (UniProt Q8N5C8 topology). Treat the pattern as provisional: HPA rates the tissue IHC evidence Approved but reports low agreement with RNA data and pending external verification (HPA tissue IHC).

What am I looking at on my slide?
Cytoplasmic staining, with or without nuclear staining, in adrenal or appendix glandular cells.This matches the reported compartments and medium staining in those cells (HPA tissue IHC). Compare the signal with a no-primary control before scoring; chromogenic background can resemble weak cytoplasmic staining (general IHC practice).
Predominantly membrane-rim staining with little cytoplasmic or nuclear signal.A membrane-only pattern is unexpected given the reported tissue compartments (HPA tissue IHC) and absence of a transmembrane segment (UniProt Q8N5C8 topology). Check morphology and controls before calling it TAB3; these sources cannot identify the artefact's cause.
Strong staining restricted to oral mucosa squamous cells or smooth muscle cells.HPA reports low staining in these cell populations (HPA tissue IHC). Consider cross-reactivity or detection-system activity, but do not treat their low staining as proof that every positive cell is false; HPA tissue results have limited consistency (HPA tissue IHC).
Diffuse brown deposit across cells and tissue spaces, including the no-primary control.Signal in a no-primary control points to background from the detection workflow rather than specific primary-antibody binding (general IHC practice). Reassess blocking, washing, and endogenous enzyme activity before interpreting cell compartments (general IHC practice).
No visible signal in bone marrow hematopoietic cells or bronchial respiratory epithelial cells.Both are reported at medium staining intensity (HPA tissue IHC), so a blank slide warrants a run-level check. Their HPA status is Approved with low RNA agreement and pending external verification; one negative specimen alone cannot establish TAB3 absence (HPA tissue IHC).
💡Expected TAB3 appearanceCall a plausible positive when cytoplasmic and/or nuclear staining reaches about medium intensity in an HPA-listed positive cell population; membrane-only staining or strong signal confined to HPA-low cells warrants control review (HPA tissue IHC; UniProt Q8N5C8 topology).
How each factor affects the staining
Tissue and cell selectionAdrenal and appendix glandular cells, bone marrow hematopoietic cells, and bronchial respiratory epithelial cells are listed at medium intensity; oral mucosa squamous and smooth muscle cells are listed as low (HPA tissue IHC).
Evidence strengthThe tissue profile is Approved, but antibody staining has low consistency with RNA expression and awaits external verification (HPA tissue IHC). The listed cell pattern is a working expectation, not an independently established specificity test.
Topology and processingTAB3 has no transmembrane segment or signal peptide, and its annotated chain spans residues 2–712 (UniProt Q8N5C8 topology and processing). These annotations support scrutiny of membrane-only staining; they do not predict antigen-retrieval conditions.
Isoforms and epitopeUniProt lists 2 TAB3 isoforms (UniProt Q8N5C8). No antibody epitope or isoform coverage is supplied, so an isoform-specific staining claim or retrieval recommendation cannot be made from this record.
IF/ICC Q&A: Where is TAB3 seen?HPA reports approved nuclear-speckle and cytosol localisation in ICC-IF, with images from A-431, U-251MG, and U2OS (HPA subcellular ICC-IF). This answers localisation only; tissue IHC reports broader nuclear and cytoplasmic staining (HPA tissue IHC).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
The expected positive cells are blank.A failed staining run or weak detection is possible (general IHC practice); HPA lists medium signal in the specified positive cells (HPA tissue IHC).Check that a positive control stained, then review reagent order, detection chemistry, and retrieval using the validated IHC procedure (general IHC practice). Do not infer TAB3 absence from one blank section.
The entire section has diffuse brown staining.Incomplete blocking or washing, or endogenous detection activity, can raise chromogenic background (general IHC practice).Inspect the no-primary control; review blocking, washes, and the detection system before scoring TAB3 (general IHC practice).
Bone marrow shows signal that obscures individual hematopoietic cells.Endogenous peroxidase can interfere with peroxidase-based detection (general IHC practice); hematopoietic cells are an HPA-listed positive population (HPA tissue IHC).Compare with a no-primary control and verify the workflow's endogenous-peroxidase block; score only cell-associated staining distinguishable from background (general IHC practice).
Signal forms a sharp membrane rim without internal staining.That differs from the HPA cytoplasmic and nuclear tissue pattern (HPA tissue IHC) and TAB3's lack of a transmembrane segment (UniProt Q8N5C8 topology).Review the no-primary control, cell outlines, and detection background before assigning localisation (general IHC practice).
Strong signal appears mainly in HPA-low cell populations.Oral mucosa squamous and smooth muscle cells are reported as low (HPA tissue IHC); cross-reactivity or background is possible, but staining is not disproved by that comparison alone.Compare staining with listed medium-intensity cells and controls; report the mismatch and HPA's low RNA agreement rather than declaring the population TAB3-negative (HPA tissue IHC).
Cytoplasmic and nuclear staining vary between sections.Both compartments occur in the HPA tissue profile (HPA tissue IHC), whose antibody-to-RNA agreement is low (HPA tissue IHC). Variation alone does not identify a technical fault.Compare like cell populations and controls across the same staining run; record compartment and intensity separately, then repeat a discrepant run before drawing a biological conclusion (general IHC practice).

Sample controls for TAB3 IHC & IF

🧪Run appendix first and assess staining in its glandular cells (HPA: Medium in appendix glandular cells). HPA detects TAB3 in all 45 scored tissues, so there is no supported negative tissue; use no-primary and isotype controls, and expect cells without specific staining on the positive slide to show only counterstain or background, without treating them as validated TAB3-negative cells (HPA: no negative rows; TAB3 detected in all 45 tissues).
Positive control tissue: Adrenal gland (Glandular cells, HPA Medium)
Negative control tissue: None in HPA: TAB3 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show TAB3 in A-431, U-251MG, U2OS, with annotated localisation: Nuclear speckles (approved), Cytosol (approved) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only slide and an isotype control matched to the primary antibody’s host species, clonality and concentration; use TAB3 knockout material or a validated peptide-block experiment as a biological specificity control (standard IHC practice). Block endogenous peroxidase and inspect inflammatory cells for residual chromogen when staining appendix with peroxidase detection (standard IHC practice; HPA: Medium in appendix glandular cells).
⚠️Feasibility: A target-specific fixation window and retrieval dependence are unreported in the supplied evidence; the A05084-1 human-kidney IHC caption gives 5 μg/mL but does not state a fixative (caption: fixative not stated). The evidence does not establish whether frozen sections or IF are easier; HPA reports ICC-IF localization to nuclear speckles and cytosol in its imaged cell lines (HPA: approved nuclear speckles and cytosol). In appendix, residual endogenous peroxidase in inflammatory cells can complicate chromogenic interpretation (standard IHC practice).

HPA tissue IHC evidence for TAB3

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells Medium Protein (IHC) HPA →
Appendix Glandular cells Medium Protein (IHC) HPA →
Bone marrow Hematopoietic cells Medium Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Medium Protein (IHC) HPA →
Caudate Neuronal cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: TAB3 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced TAB3 IHC Tips

Use compartment, cell type and matched controls to evaluate TAB3 staining in paraffin sections; reserve IF/ICC for the separate guide.

How should I retrieve TAB3 in paraffin sections when staining is weak?
Start with citrate buffer at pH 6.0, heated to 95–98 °C for 20 min (page retrieval setting). Let sections cool in buffer, then compare staining with a matched section processed without primary antibody to assess detection background (standard IHC practice). The selected A05084-1 kidney image reports 5 μg/mL antibody but does not state its retrieval conditions (selected tissue-IHC caption). If signal remains weak, test an alternative retrieval condition on adjacent sections while holding antibody concentration and detection constant (standard IHC practice). Judge improvement by cellular staining and preserved morphology; stronger diffuse colour alone does not establish TAB3 specificity (standard IHC practice).
Could fixation account for weak or uneven TAB3 staining?
Target-specific TAB3 sensitivity to fixation is unknown from the supplied evidence; the A05084-1 kidney caption does not state a fixative (selected tissue-IHC caption). Record the fixative, fixation duration and processing history for each specimen, then compare sections processed together before attributing intensity differences to biology (standard IHC practice). For routine paraffin IHC, inspect morphology and section adhesion after retrieval, since damaged or detached regions cannot support reliable scoring (standard IHC practice). Include a matched no-primary control and a consistently stained reference section in each run (standard IHC practice). Do not infer a TAB3 fixation requirement from its modifications or reported tissue staining (UniProt Q8N5C8; HPA tissue IHC).
Should TAB3 staining be cytoplasmic, nuclear or both?
Assess cytoplasmic and nuclear staining separately: tissue IHC reports both in several tissues, while cell imaging places TAB3 in cytosol and nuclear speckles (HPA tissue IHC; HPA subcellular). UniProt does not annotate a subcellular location for TAB3, so neither compartment alone is a universal acceptance criterion (UniProt Q8N5C8). Check whether nuclear colour resolves within intact cells and whether cytoplasmic colour follows cell boundaries, using the counterstain to identify nuclei (standard IHC practice). Compare the same compartment across matched sections and cell populations rather than pooling all brown signal (standard IHC practice). Treat staining confined to section edges or damaged regions as suspect until controls support it (standard IHC practice).
How can isoforms or epitope accessibility affect TAB3 IHC?
TAB3 has 2 listed isoforms and a CUE domain spanning residues 8–51 (UniProt Q8N5C8). The supplied A05084-1 caption does not identify its epitope, so staining cannot be assigned to one isoform from this image alone (selected tissue-IHC caption). Review the antibody's documented immunogen or epitope before comparing specimens, and avoid assuming that a modification changes binding without direct evidence (standard IHC practice). TAB3 has recorded phosphoserines at residues 60, 101, 103 and 385, but their effect on this antibody is unspecified (UniProt Q8N5C8). Keep retrieval and detection conditions matched when investigating differing staining patterns (standard IHC practice).
How should I investigate TAB3 localisation by multiplex IF?
On the separate IF/ICC guide, multiplex TAB3 with an independently validated marker for the cell population being examined, and interpret overlap at the single-cell level (standard IF practice). Select a TAB3 fluorophore in a channel with low measured tissue autofluorescence, and acquire unstained and single-colour controls before combining channels (standard IF practice). TAB3 has no annotated transmembrane segment, while cell imaging reports cytosol and nuclear speckles; use permeabilisation appropriate to intracellular epitopes (UniProt Q8N5C8 topology; HPA subcellular). Optimise permeabilisation on matched samples because the antibody epitope and its accessibility are not supplied (selected tissue-IHC caption). Confirm apparent speckles against the nuclear counterstain and optical background (standard IF practice).
What should I check when TAB3 sections show diffuse brown background?
Compare a no-primary section and a detection-only control with the TAB3-stained section to locate background from the detection system (standard IHC practice). For peroxidase and DAB workflows, block endogenous peroxidase and check whether pigment or precipitated chromogen persists in controls (standard IHC practice). Titrate primary antibody and adjust blocking or washes on matched sections while keeping retrieval fixed; the A05084-1 kidney caption reports 5 μg/mL, without establishing an optimum for every specimen (selected tissue-IHC caption; standard IHC practice). Assess cytoplasmic and nuclear signal within intact cells because both patterns have tissue support (HPA tissue IHC). Reject colour concentrated at folds, edges or necrotic areas as a basis for positive scoring (standard IHC practice).
How should I score TAB3 staining across tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the scored cell population and compartment before analysis, then record the percentage of positive cells and an intensity-based H-score separately for cytoplasm and nucleus (standard IHC practice). An H-score uses intensity classes 0–3 multiplied by the percentage of cells in each class, producing a 0–300 scale (standard IHC practice). Normalise counts or positive area to the number of eligible cells or analysed tissue area, such as cells per mm², and exclude folds and necrosis (standard IHC practice). Keep section thickness, retrieval, detection and imaging settings consistent across comparisons (standard IHC practice). Report cell type and compartment because TAB3 tissue staining includes both cytoplasmic and nuclear expression (HPA tissue IHC).
How can I distinguish convincing TAB3 staining from artefact?
Look for reproducible cellular staining in intact tissue, with cytoplasmic or nuclear patterns assessed against the matched no-primary control (HPA tissue IHC; standard IHC practice). TAB3 is reported as widely expressed, so a positive result requires cell-level specificity and suitable controls rather than positivity in one tissue alone (UniProt Q8N5C8; standard IHC practice). Check the identity of stained cells against morphology; staining restricted to the wrong cell population, cut edges, folds or necrosis warrants investigation (standard IHC practice). In peroxidase IHC, exclude endogenous enzyme signal with an appropriate block and control (standard IHC practice). HPA calls its tissue IHC data Approved but notes low agreement with RNA expression and pending external verification, limiting certainty from that reference alone (HPA tissue IHC).
Boster reagents

Best TAB3 / TGF-beta-activated kinase 1 and MAP3K7-binding protein 3 IHC Antibodies

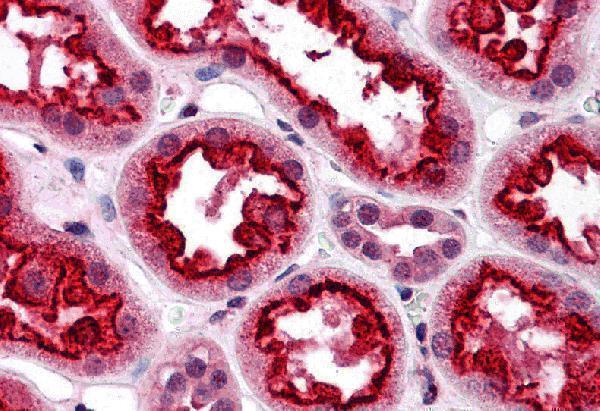
A05084-1 has an IHC image from human kidney tissue (catalog image caption); M05084 lists human and mouse ICC/IF use, with no IF image supplied (catalog applications, reactivity, and image alts).

Real IHC data Immunohistochemistry of TAB3 in human kidney tissue with TAB3 antibody at 5 μg/mL.
Anti-TAB3 Antibody
Cat # A05084-1

Only A05084-1 will render as a card (cards payload). Its IHC image shows human kidney tissue stained at 5 μg/mL (catalog image caption).

Which to pick: Choose polyclonal A05084-1 for human paraffin-section IHC (catalog: IHC-P and human reactivity); its kidney image caption does not report the fixative (catalog image caption). For ICC/IF, consider monoclonal M05084, clone 22T62 (catalog: ICC/IF and clone); no IF figure is supplied (catalog image alts). M05084 also lists mouse reactivity, but IHC is absent from its application list (catalog: reactivity and applications).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q8N5C8 (TAB3_HUMAN, TGF-beta-activated kinase 1 and MAP3K7-binding protein 3).
  2. Human Protein Atlas. TAB3 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. TAB3 subcellular location (ICC-IF): Localized to the nuclear speckles and cytosol..
  4. Human Protein Atlas. TAB3 antibody validation summary (2 antibodies).
  5. TAB3 O-GlcNAcylation promotes metastasis of triple negative breast cancer. Oncotarget 2016 — PMC5008402.
  6. Macrophage-derived exosomes modulate wear particle-induced osteolysis via miR-3470b targeting TAB3/NF-κB signaling. Bioactive materials 2023 — PMC9999169.
  7. TAB3 upregulates Survivin expression to promote colorectal cancer invasion and metastasis by binding to the TAK1-TRAF6 complex. Oncotarget 2017 — PMC5739756.
  8. Hsa-microRNA-27b-3p inhibits hepatocellular carcinoma progression by inactivating transforming growth factor-activated kinase-binding protein 3/nuclear factor kappa B signalling. Cellular & molecular biology letters 2022 — PMC9502615.
  9. PubMed PMID:14633987 — UniProt-cited evidence.
  10. PubMed PMID:14670075 — UniProt-cited evidence.
  11. PubMed PMID:14766965 — UniProt-cited evidence.