This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan TET3 IHC-P around cytoplasmic tissue staining (HPA tissue IHC) and its annotated nuclear localisation (UniProt). Start the catalog antibody at 2.5 μg/mL (datasheet), using esophageal squamous epithelial cells as a high-staining reference (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic in tissue (HPA tissue IHC); nuclear by annotation (UniProt) | |
| Staining pattern | Strong cytoplasmic staining in squamous epithelial and smooth muscle cells (HPA tissue IHC) | |
| Antigen retrieval | Tris-EDTA pH 9.0 HIER, 95–98 °C, 20 min (rule: nuclear antigen) | |
| Positive control | Esophagus+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
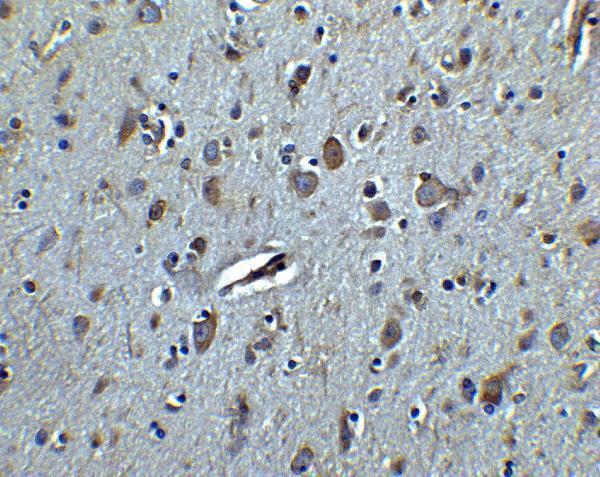
| Fixation | Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A03371) | |
| Caveat | Tissue staining has low consistency with RNA expression (HPA tissue IHC) | |
| Regulation | Tissue-enhanced RNA: bone marrow, skin (HPA RNA) | |
| Isoform / epitope | 3 isoforms (UniProt); epitope coverage unspecified (datasheet) |
The catalog antibody’s IHC-P protocol is accompanied by published TET3 IHC methods for human ovarian tissue microarrays and tumor sections (PMC4855705; PMC13169958).
| Sample | Tissue sections; selected-image fixative not specified (standard IHC workflow) |
| Fixation | Image fixative and duration unreported (datasheet A03371); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in Tris-EDTA buffer, pH 9.0, 20 min at 95–98 °C (standard rule: nuclear antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-TET3, 2.5 μg/mL (datasheet A03371) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | TET3-positive staining in squamous epithelial cells of esophagus (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in several different tissue types, highly abundant in squamous epithelial and smooth muscle cells. No signal in the no-primary control. |
TET3 is annotated in the nucleus, cytoplasm and chromosomes, with no transmembrane segment (UniProt O43151). In tissue IHC, expect mainly cytoplasmic staining in selected cells, especially squamous epithelial and smooth muscle cells (HPA: tissue IHC profile). Treat that pattern as provisional: HPA rates the tissue IHC result Uncertain because antibody staining has low consistency with RNA expression (HPA: tissue IHC reliability).
| Clear cytoplasmic stain in esophageal or oral squamous epithelial cells, with nearby structures remaining distinct. | This fits a documented high staining pattern (HPA: esophagus and oral mucosa, High). Record the stained cell population and compartment alongside intensity; HPA's overall tissue IHC reliability remains Uncertain (HPA: tissue IHC reliability). |
| Nuclear staining accompanies, or exceeds, cytoplasmic staining in an otherwise plausible cell population. | Nuclear TET3 is biologically plausible (UniProt O43151: nucleus and chromosome; HPA: ICC-IF nucleoplasm, approved). It differs from HPA's mainly cytoplasmic tissue IHC profile, so assess antibody controls before treating the nuclear IHC pattern as confirmed (HPA: tissue IHC profile). |
| Signal outlines cell membranes or appears extracellular, without a convincing intracellular pattern. | That compartment does not match the annotated nuclear or cytoplasmic locations (UniProt O43151; HPA: tissue IHC profile). Consider nonspecific staining or detection artefact; TET3 has no annotated transmembrane segment or signal peptide (UniProt O43151 topology and processing). |
| Strong stain appears in adipocytes or liver cholangiocytes. | HPA reports those cell types as Not detected (HPA: adipose tissue adipocytes; liver cholangiocytes). Check for cross-reactivity or endogenous detection activity before calling the signal TET3; an HPA negative is a reference observation, not proof that every specimen must be negative (HPA: tissue IHC reliability Uncertain). |
| Esophageal squamous epithelium has no detectable stain. | That conflicts with HPA's High observation for this cell population (HPA: esophagus squamous epithelial cells). First assess section quality, retrieval and reagent performance using general IHC controls. A failed control slide cannot establish that the test specimen lacks TET3 (general IHC practice). |
| Cell population and compartment | Compare each compartment within a named cell type: HPA describes abundant cytoplasmic staining in squamous epithelial and smooth muscle cells, while its listed High examples include skin keratinocytes and placental trophoblastic cells (HPA: tissue IHC profile; skin and placenta, High). |
| Strength of the tissue reference | HPA rates tissue IHC reliability Uncertain because staining and RNA expression show low consistency (HPA: tissue IHC reliability). Its single listed antibody, HPA050845, is Uncertain for IHC and Approved for ICC; these are application-specific assessments (HPA: antibody validation). |
| Topology and processing | The annotated TET3 chain spans residues 1–1795; no signal peptide, propeptide or transmembrane segment is annotated (UniProt O43151 topology and processing). These annotations support checking unexpected surface or extracellular signal, but do not identify the antibody's epitope. |
| Isoforms | UniProt lists 3 isoforms (UniProt O43151: isoforms). Without an epitope or isoform-specific antibody record here, a staining difference cannot be assigned to a particular isoform; compare like tissues and controls before making that interpretation. |
| IF/ICC: What pattern should I expect? | HPA reports mainly nucleoplasmic signal, with additional vesicle and cytosol signal, in ICC-IF (HPA: subcellular location, approved). That supports an IF localization check but does not override the mainly cytoplasmic tissue IHC profile (HPA: tissue IHC profile, Uncertain). |
| Situation | Likely cause | Next action |
|---|---|---|
| Positive control is blank or very weak. | The expected High esophageal squamous-cell signal is absent (HPA: esophagus, High); an IHC workflow failure is possible (general IHC practice). | Review section integrity, retrieval conditions, antibody dilution and detection controls using the antibody's IHC-P instructions (general IHC practice). Reassess the specimen only after a control stains as expected. |
| All tissue compartments show diffuse brown color. | Widespread color without cell boundaries does not resemble HPA's cell-selective cytoplasmic profile (HPA: tissue IHC profile); background or nonspecific detection is possible (general IHC practice). | Compare a no-primary control, inspect blocking and washes, and check the chromogen development time (general IHC practice). Score only resolved cellular stain against the counterstain. |
| Membrane rims dominate the positive cells. | A membrane-only pattern conflicts with the annotated nuclear and cytoplasmic locations and lack of a transmembrane segment (UniProt O43151). | Inspect the same cell types on the no-primary control and review edge staining or precipitate under the microscope (general IHC practice). Do not count membrane rims as a TET3 positive without independent support. |
| Cells listed as Not detected stain strongly. | Strong signal in adipocytes or cholangiocytes disagrees with HPA's tissue observations (HPA: adipose tissue; liver). Cross-reactivity or endogenous detection activity is possible (general IHC practice). | Run a no-primary control and, for peroxidase detection, check endogenous peroxidase blocking (general IHC practice). Because HPA rates tissue IHC Uncertain, report the discrepancy rather than automatically rejecting the specimen (HPA: tissue IHC reliability). |
| Nuclear staining is prominent while cytoplasmic staining is faint. | Nuclear localization has support in UniProt and ICC-IF, whereas HPA's tissue IHC summary emphasizes cytoplasm (UniProt O43151 localization; HPA: ICC-IF subcellular and tissue IHC profile). | Document nuclear and cytoplasmic scores separately, review controls, and avoid assigning a nuclear IHC pattern the same confidence as HPA's approved ICC-IF result (HPA: antibody validation and subcellular location). |
| A low-staining tissue is used as the only positive control. | HPA lists only Low staining in adrenal gland glandular cells and lung alveolar cells, for example (HPA: adrenal gland; lung). Weak or absent color there gives a limited check of assay performance. | Include a documented High cell population, such as skin keratinocytes or esophageal squamous epithelial cells, on a control section (HPA: skin and esophagus, High). Judge the assay from the stained cell type, not the tissue label alone. |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Uncertain — Low consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Esophagus | Squamous epithelial cells | High | Protein (IHC) | HPA → |
| Oral mucosa | Squamous epithelial cells | High | Protein (IHC) | HPA → |
| Placenta | Trophoblastic cells | High | Protein (IHC) | HPA → |
| Skin | Keratinocytes | High | Protein (IHC) | HPA → |
| Stomach | Glandular cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Hippocampus | Glial cells | Not detected | Protein (IHC) | HPA → |
| Liver | Cholangiocytes | Not detected | Protein (IHC) | HPA → |
| Parathyroid gland | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Seminal vesicle | Glandular cells | Not detected | Protein (IHC) | HPA → |
Troubleshoot TET3 staining in paraffin sections by checking retrieval, cellular compartment, controls and scoring before interpreting chromogenic signal.
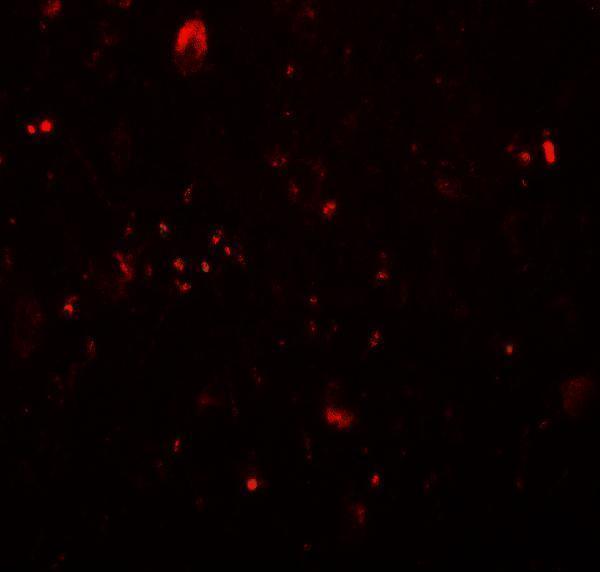
A03371 has IHC and IF images from human brain tissue (catalog image captions) and lists human, mouse, and rat reactivity (catalog reactivity).
A03371 is listed for IHC-P and IF (catalog applications). Its images show IHC at 2.5 μg/mL and IF at 20 μg/mL, both in human brain tissue (A03371 image captions).
Which to pick: Choose A03371 for paraffin-section IHC (catalog applications: IHC-P); its own IHC image shows human brain tissue, but the fixative is unreported (A03371 IHC image caption). For IF, choose A03371 (catalog applications: IF); ICC validation is not listed (catalog applications). For cross-species studies, A03371 lists human, mouse, and rat reactivity (catalog reactivity), though its images show human tissue only (A03371 image captions); clonality is unreported.