TNFRSF6B / Tumor necrosis factor receptor superfamily member 6B · IHC design guide

Design Immunohistochemistry for TNFRSF6B

Use high staining in colon glandular cells and absent staining in adipocytes as IHC reference patterns (HPA tissue IHC). Plan chromogenic staining with the IHC-P validated catalog antibody, starting at 1 μg/mL (datasheet: A04048-1).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for TNFRSF6B (IHC for TNFRSF6B): expected localisation Cytoplasmic tissue staining (HPA tissue IHC); secreted protein (UniProt), antibody A04048, validated IHC image, and IHC protocol steps
Printable TNFRSF6B IHC protocol sheet — expected localisation Cytoplasmic tissue staining (HPA tissue IHC); secreted protein (UniProt), antibody A04048, controls and protocol steps. Open the full TNFRSF6B IHC guide →

TNFRSF6B Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic tissue staining (HPA tissue IHC); secreted protein (UniProt)
Staining pattern GI glandular and CNS cells show cytoplasmic signal (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Cerebellum+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A04048)
Caveat RNA and protein locations may differ for this secreted protein (HPA tissue IHC)
Regulation High in several primary GI tumors (UniProt)
Isoform / epitope 0 annotated isoforms; mature chain spans aa 30–300 (UniProt)
Section 1

Recommended TNFRSF6B IHC & IF Protocols

The catalog antibody protocol (datasheet) is paired with one published TNFRSF6B IHC protocol for paraffin sections (PMC2921593).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human colon t carcinoma tissue; fixative not specified (datasheet A04048)
FixationImage fixative and duration unreported (datasheet A04048); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-TNFRSF6B, 1:100-1:300 (datasheet A04048)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultTNFRSF6B-positive staining in purkinje cells of cerebellum (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in gastrointestinal tract and CNS. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 heat retrieval at 95–98 °C for 20 min (page retrieval rule); compare basic-buffer heat retrieval if needed (PMC2921593).
Section 2

What Is the Expected TNFRSF6B Staining Pattern?

TNFRSF6B is a secreted protein without a transmembrane segment (UniProt O95407 topology). In paraffin-section IHC, expect cytoplasmic staining in gastrointestinal glandular cells and selected CNS cells (HPA tissue IHC: Approved). HPA reports high staining in colon, duodenum, rectum and small-intestine glandular cells, cerebellar Purkinje cells, and cerebral-cortex endothelial cells (HPA tissue IHC). A secreted protein can leave its producing cell, so extracellular signal needs cautious interpretation (UniProt O95407; HPA reliability note).

What am I looking at on my slide?
Cytoplasmic staining in intestinal glandular cells; high signal in colon, duodenum, rectum or small intestine (HPA tissue IHC).This matches the reported tissue and cell pattern (HPA tissue IHC: Approved). Judge signal against adjacent cells and a negative control; cytoplasmic signal alone does not prove which cell made a secreted protein (UniProt O95407).
Staining in Purkinje cells or cerebral-cortex endothelial cells (HPA tissue IHC: High).These are additional reported positive populations (HPA tissue IHC). Assess the named cell population rather than treating all CNS cells as equivalent: caudate glial cells have medium staining (HPA tissue IHC).
Predominantly nuclear or sharply membrane-confined staining, without the expected cytoplasmic pattern (HPA tissue IHC).Treat this as an unexpected compartment pattern and investigate artefact before scoring it positive. TNFRSF6B is secreted and lacks a transmembrane segment (UniProt O95407); HPA describes cytoplasmic tissue expression (HPA tissue IHC).
Strong staining in a cell population reported as not detected, such as adipocytes or bone-marrow hematopoietic cells (HPA tissue IHC).Consider antibody cross-reactivity or endogenous chromogenic activity; inspect the negative control and tissue morphology. HPA's not-detected calls apply to the named cells, not every cell in those tissues (HPA tissue IHC).
Diffuse color across several structures, or no signal in colon glandular cells (HPA tissue IHC: High).Diffuse color is difficult to assign to a cell and may reflect background; loss of a reported positive suggests a staining-run or sample problem. Compare a negative control and a positive control before interpreting the specimen (HPA tissue IHC).
💡Expected TNFRSF6B appearanceCall a convincing positive when cytoplasmic signal is clear in the reported glandular or selected CNS cells, with high staining in the listed high-level populations; isolated nuclear or sharply membrane-confined signal is suspect (HPA tissue IHC; UniProt O95407 topology).
How each factor affects the staining
Secreted location and topology (UniProt O95407).TNFRSF6B has a signal peptide and no transmembrane segment (UniProt O95407). Cytoplasmic IHC is reported (HPA tissue IHC), but extracellular signal need not identify its cell of origin.
Tissue and cell context (HPA tissue IHC).Glandular cells are high in colon, duodenum, rectum and small intestine; appendix glandular cells are medium, and bronchial respiratory epithelial cells are low (HPA tissue IHC). Set expectations for the specific cells examined.
Protein versus RNA location (HPA reliability note).HPA cautions that tissue RNA and protein locations can differ for a secreted protein (HPA tissue IHC). Lung-enhanced RNA does not by itself predict the strongest lung IHC staining (HPA tissue IHC).
Antibody evidence (HPA antibody record).HPA047154 has Approved IHC status (HPA antibodies). The supplied record does not assign it Enhanced status; an unexpected pattern warrants independent checks rather than an automatic TNFRSF6B call.
Processing and modification (UniProt O95407).The annotated chain is residues 30–300 after a 1–29 signal peptide, with one glycosylation site at residue 173 (UniProt O95407). These annotations do not establish an epitope, retrieval condition or fixation sensitivity.
ICC-IF evidence (HPA subcellular record).HPA lists TNFRSF6B as secreted but supplies no main ICC-IF location or cell-line images (HPA subcellular). Tissue IHC observations cannot establish an ICC-IF pattern.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No staining in colon glandular cells despite an expected high pattern (HPA tissue IHC).The run, specimen or detection steps may have failed; the supplied sources do not identify a TNFRSF6B-specific fixation effect.Check the positive-control section and reagent steps, then review the section's morphology and repeat the run if needed (general IHC practice).
Strong nuclear-only staining replaces cytoplasmic staining (HPA tissue IHC).The compartment conflicts with the reported cytoplasmic pattern and secreted topology (HPA tissue IHC; UniProt O95407).Compare with a negative control and confirm the stained structures before assigning TNFRSF6B positivity (general IHC practice).
Color appears broadly in reported negative cell populations (HPA tissue IHC).Cross-reactivity or endogenous chromogenic activity is possible; HPA's negative calls are cell-specific (HPA tissue IHC).Inspect a control lacking primary antibody, review blocking and detection, and score the named cells separately (general IHC practice).
Diffuse chromogen obscures cell boundaries (general IHC practice).Nonspecific background or detection activity may obscure the reported cytoplasmic pattern (HPA tissue IHC).Review blocking, washes, antibody concentration and development time; use a negative control to locate background (general IHC practice).
Bronchus looks weak beside colon (HPA tissue IHC).HPA reports low staining in bronchial respiratory epithelial cells and high staining in colon glandular cells (HPA tissue IHC).Score each named cell population against its own expected level before changing the IHC conditions (HPA tissue IHC).
Can the tissue IHC pattern guide an ICC-IF call?HPA provides no ICC-IF images or assigned main subcellular location for TNFRSF6B (HPA subcellular).Use the separate IF/ICC guide for that application; treat cytoplasmic tissue IHC as context, not ICC-IF validation (HPA tissue IHC; HPA subcellular).

Sample controls for TNFRSF6B IHC & IF

🧪Run colon first: glandular cells should stain (HPA: High in colon glandular cells). Use adipose tissue as the negative tissue; adipocytes are listed as not detected (HPA: Not detected in adipocytes). On the colon slide, compare glandular staining with adjacent nonglandular cells and expect only background signal in the latter, as checked against the no-primary control.
Positive control tissue: Cerebellum (Purkinje cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA carries no ICC-IF cell line for TNFRSF6B; derive a cell-line control from the positive tissue's cell type (Purkinje cells) and confirm it by RNA or western blot first.
Technical controls: Include no-primary (secondary-only) and host-species- and clonality-matched isotype controls, plus a TNFRSF6B peptide-block control; the selected IHC caption reports peptide blocking in a colon carcinoma section (caption: A04048). For chromogenic colon IHC, quench endogenous peroxidase and, if using avidin–biotin detection, control for endogenous biotin (standard IHC practice).
⚠️Feasibility: A target-specific fixation window and retrieval effect are unreported in the supplied evidence; the selected paraffin-section caption does not state its fixative (caption: A04048). Neither frozen sections nor IF is established as easier here, and HPA lists no ICC-IF cell-line images (HPA subcellular: no ICC-IF images). In colon, distinguish glandular staining from luminal mucus or background signal (HPA: High in colon glandular cells; standard IHC practice).

HPA tissue IHC evidence for TNFRSF6B

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Secreted protein, tissue location of RNA and protein is expected to differ.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Cerebellum Purkinje cells High Protein (IHC) HPA →
Cerebral cortex Endothelial cells High Protein (IHC) HPA →
Colon Glandular cells High Protein (IHC) HPA →
Duodenum Glandular cells High Protein (IHC) HPA →
Rectum Glandular cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Cervix Glandular cells Not detected Protein (IHC) HPA →
Section 3

Advanced TNFRSF6B IHC Tips

Troubleshoot chromogenic TNFRSF6B staining in paraffin sections using its secreted topology, reported tissue patterns, and the selected antibody’s tissue image.

What retrieval should I try first for weak TNFRSF6B staining?
Start with citrate buffer at pH 6.0, heated to 95–98 °C for 20 minutes (page retrieval setting). If staining is weak, compare an adjacent section using a modestly longer heating time, while holding antibody dilution and detection conditions constant (standard IHC practice). Let sections cool in retrieval buffer, then compare glandular cell staining in colon with a matched no-primary control (HPA: High in colon glandular cells; standard IHC practice). Excessive retrieval can damage section morphology or increase diffuse staining, so judge signal alongside tissue preservation and background (standard IHC practice).
Could fixation explain inconsistent TNFRSF6B staining between paraffin blocks?
The selected image identifies paraffin-embedded human colon carcinoma but does not state its fixative, so target-specific fixation sensitivity remains unknown (A04048 tissue-IHC caption). Record each block’s fixative, fixation duration, and processing history before comparing staining intensity across cases (standard IHC practice). For a controlled check, stain serial sections from the same block with the same citrate pH 6.0 retrieval and 20-minute heating step (page retrieval setting; standard IHC practice). Include a matched no-primary control and assess morphology; neither a tissue staining pattern nor secreted topology establishes a TNFRSF6B-specific fixation effect (HPA tissue IHC; UniProt O95407 topology).
Should TNFRSF6B appear on cell membranes or in the cytoplasm?
Expect a pattern compatible with a secreted protein: TNFRSF6B has a signal peptide at residues 1–29 and no transmembrane segment (UniProt O95407 topology). Cytoplasmic staining in gastrointestinal tissue is reported, including High staining in colon glandular cells (HPA tissue IHC). Evaluate cytoplasmic staining separately from extracellular deposits, because secreted protein may be encountered away from its producing cells (UniProt O95407 subcellular location; standard IHC interpretation). A crisp, exclusive plasma membrane outline should prompt review of the no-primary control, section edges, and antibody specificity before assigning it to TNFRSF6B (UniProt O95407 topology; standard IHC practice).
How should I interpret epitope-dependent differences between TNFRSF6B antibodies?
UniProt lists 0 isoforms for TNFRSF6B, so an epitope-dependent staining difference should not be assigned to a documented splice isoform (UniProt O95407 isoforms). The precursor has a signal peptide at residues 1–29, whereas the annotated mature chain spans 30–300; an antibody’s mapped epitope matters when interpreting secreted protein (UniProt O95407 processing). TNFRSF6B also has an annotated glycosylation site at residue 173, but its effect on this antibody’s tissue staining is unreported (UniProt O95407 glycosylation; A04048 tissue-IHC caption). Compare epitope information, staining compartments, and peptide-blocked versus unblocked sections where available; the selected tissue image includes a peptide-blocked comparison (A04048 tissue-IHC caption; standard IHC practice).
How can I check TNFRSF6B localisation with multiplex immunofluorescence?
Use IF as a separate assay: the supplied record has no TNFRSF6B ICC/IF images or target-specific IF fixation conditions (HPA subcellular record). Pair TNFRSF6B with a validated glandular cell marker in colon, where glandular cell staining is reported High, and include single-stain controls (HPA tissue IHC; standard IF practice). Choose spectrally separated fluorophores after inspecting tissue autofluorescence, and compare channels without saturation or bleed-through (standard IF practice). Because TNFRSF6B lacks a transmembrane segment, match permeabilisation to the antibody’s known epitope accessibility: test permeabilised sections for intracellular signal and preserve nonpermeabilised sections when assessing accessible extracellular protein (UniProt O95407 topology; standard IF practice).
What should I check when TNFRSF6B staining is diffuse or widespread?
Run a no-primary section to detect reagent background, and apply a peroxidase block before chromogenic detection when using an HRP system (standard IHC practice). Check whether staining concentrates at section edges, folds, or necrotic areas rather than in intact cells (standard IHC practice). Compare colon glandular cells with adipocytes in adipose tissue, which are reported High and Not detected, respectively, while allowing for differences between specimens and assays (HPA tissue IHC). If background persists, titrate the primary antibody and detection reagent, keep wash conditions consistent, and examine the selected antibody’s peptide-blocked image as supporting specificity evidence (A04048 tissue-IHC caption; standard IHC practice).
How should I score TNFRSF6B staining across colon carcinoma sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the analysis compartment before scoring: count intact tumor cells separately from extracellular staining and necrotic areas (UniProt O95407 subcellular location; standard IHC practice). Report the percentage of positive tumor cells and an H-score using intensity categories 0–3, with a possible H-score range of 0–300 (standard IHC scoring practice). If measuring stained area or positive cell density per mm², normalise to viable tumor area and record the number of assessed fields (standard IHC practice). Apply one staining threshold across matched sections and retain no-primary controls; secretion can make extracellular intensity a different readout from tumor-cell positivity (UniProt O95407 subcellular location; standard IHC practice).
How can I distinguish genuine TNFRSF6B signal from staining artefacts?
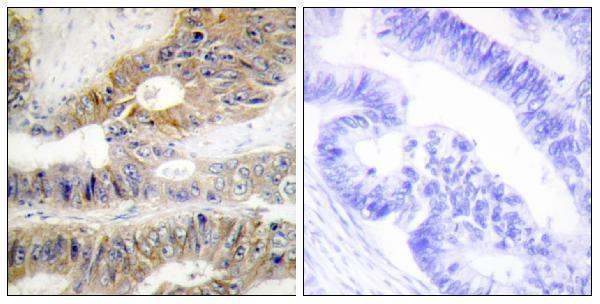
Look for reproducible staining in intact glandular cells, which are reported High in colon, and review the selected colon carcinoma image alongside its peptide-blocked comparison (HPA tissue IHC; A04048 tissue-IHC caption). Interpret cytoplasmic or extracellular signal in light of TNFRSF6B’s secreted status and lack of a transmembrane segment (UniProt O95407 subcellular location and topology). Treat isolated nuclear staining, sharp edge staining, and staining confined to necrotic material as reasons to inspect specificity and section quality (standard IHC practice). Check a no-primary section for endogenous enzyme or detection-system signal before attributing chromogen to TNFRSF6B (standard IHC practice).
Boster reagents

Best TNFRSF6B / Tumor necrosis factor receptor superfamily member 6B IHC Antibodies

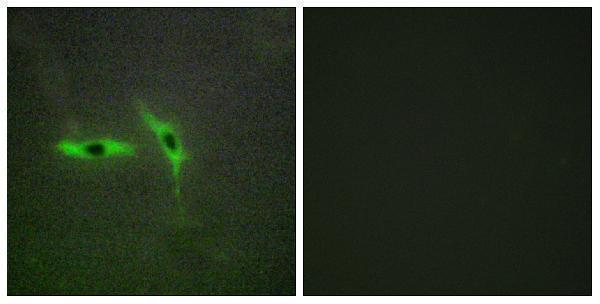
The catalog shows TNFRSF6B IHC figures for human colon carcinoma and heart tissue, plus an IF figure with no specimen identified (A04048 and A04048-1 image captions).

Real IHC data Immunohistochemistryt analysis of paraffin-embedded human colon t carcinoma, using TNFRSF6B Antibody. The lane on the right is blocked with the TNFRSF6B peptide.
Anti-DcR3 Antibody
Cat # A04048
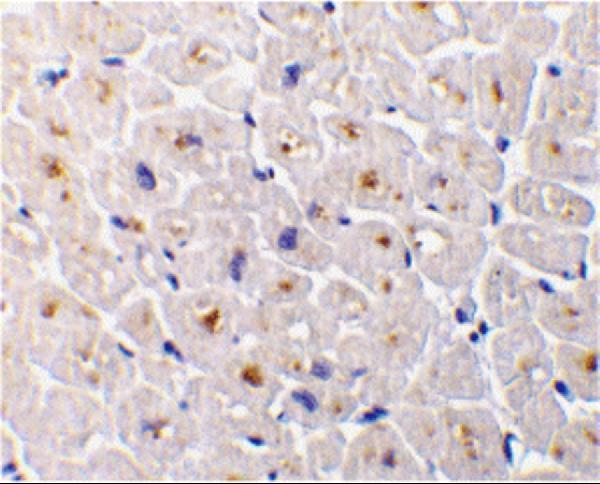
Real IHC data Immunohistochemistry of DcR3 in human heart tissue with DcR3 antibody at 1 μg/mL.
Anti-DcR3 TNFRSF6B Antibody
Cat # A04048-1

A04048 has an IHC image of paraffin-embedded human colon carcinoma and an IF image with no specimen identified (A04048 image captions). A04048-1 has an IHC image of human heart tissue and lists IHC-P for human, mouse and rat reactivity; its figure shows human tissue only (A04048-1 image caption; catalog applications and reactivity).

Which to pick: For paraffin-section IHC, choose A04048 when its human colon carcinoma example fits your use; the caption does not report the fixative (A04048 IHC image caption). For IF, choose the polyclonal A04048, which lists IF and has an IF figure; ICC is not listed (A04048 dilution record, applications and IF image caption). For mouse or rat IHC-P, consider A04048-1 based on its listed reactivity, while recognizing that its IHC figure shows human heart tissue and does not report tissue processing or fixation (A04048-1 catalog applications, reactivity and IHC image caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry O95407 (TNF6B_HUMAN, Tumor necrosis factor receptor superfamily member 6B).
  2. Human Protein Atlas. TNFRSF6B tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. TNFRSF6B subcellular location (ICC-IF): Secreted.
  4. Human Protein Atlas. TNFRSF6B antibody validation summary (1 antibodies).
  5. Protocadherin γ A3 is expressed in follicular lymphoma irrespective of BCL2 status and is associated with tumor cell growth. Molecular medicine reports 2016 — PMC5102029.
  6. The DCBLD2 super-enhancer drives colorectal cancer progression through FOSL2/JUND-mediated activation of the CD146/AKT/TNFRSF6B pathway. Molecular biomedicine 2026 — PMC13601434.
  7. Polymorphic variants of LIGHT (TNF superfamily-14) alter receptor avidity and bioavailability. Journal of immunology (Baltimore, Md. : 1950) 2010 — PMC2921593.
  8. Amelioration of amyloid-β-induced deficits by DcR3 in an Alzheimer's disease model. Molecular neurodegeneration 2017 — PMC5402663.
  9. PubMed PMID:9872321 — UniProt-cited evidence.
  10. PubMed PMID:10318773 — UniProt-cited evidence.
  11. PubMed PMID:10655513 — UniProt-cited evidence.