This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan a TTR Western blot around the catalog-observed 15.9 kDa band, image-backed PB9749 evidence, HPA controls, and verified protocol records.
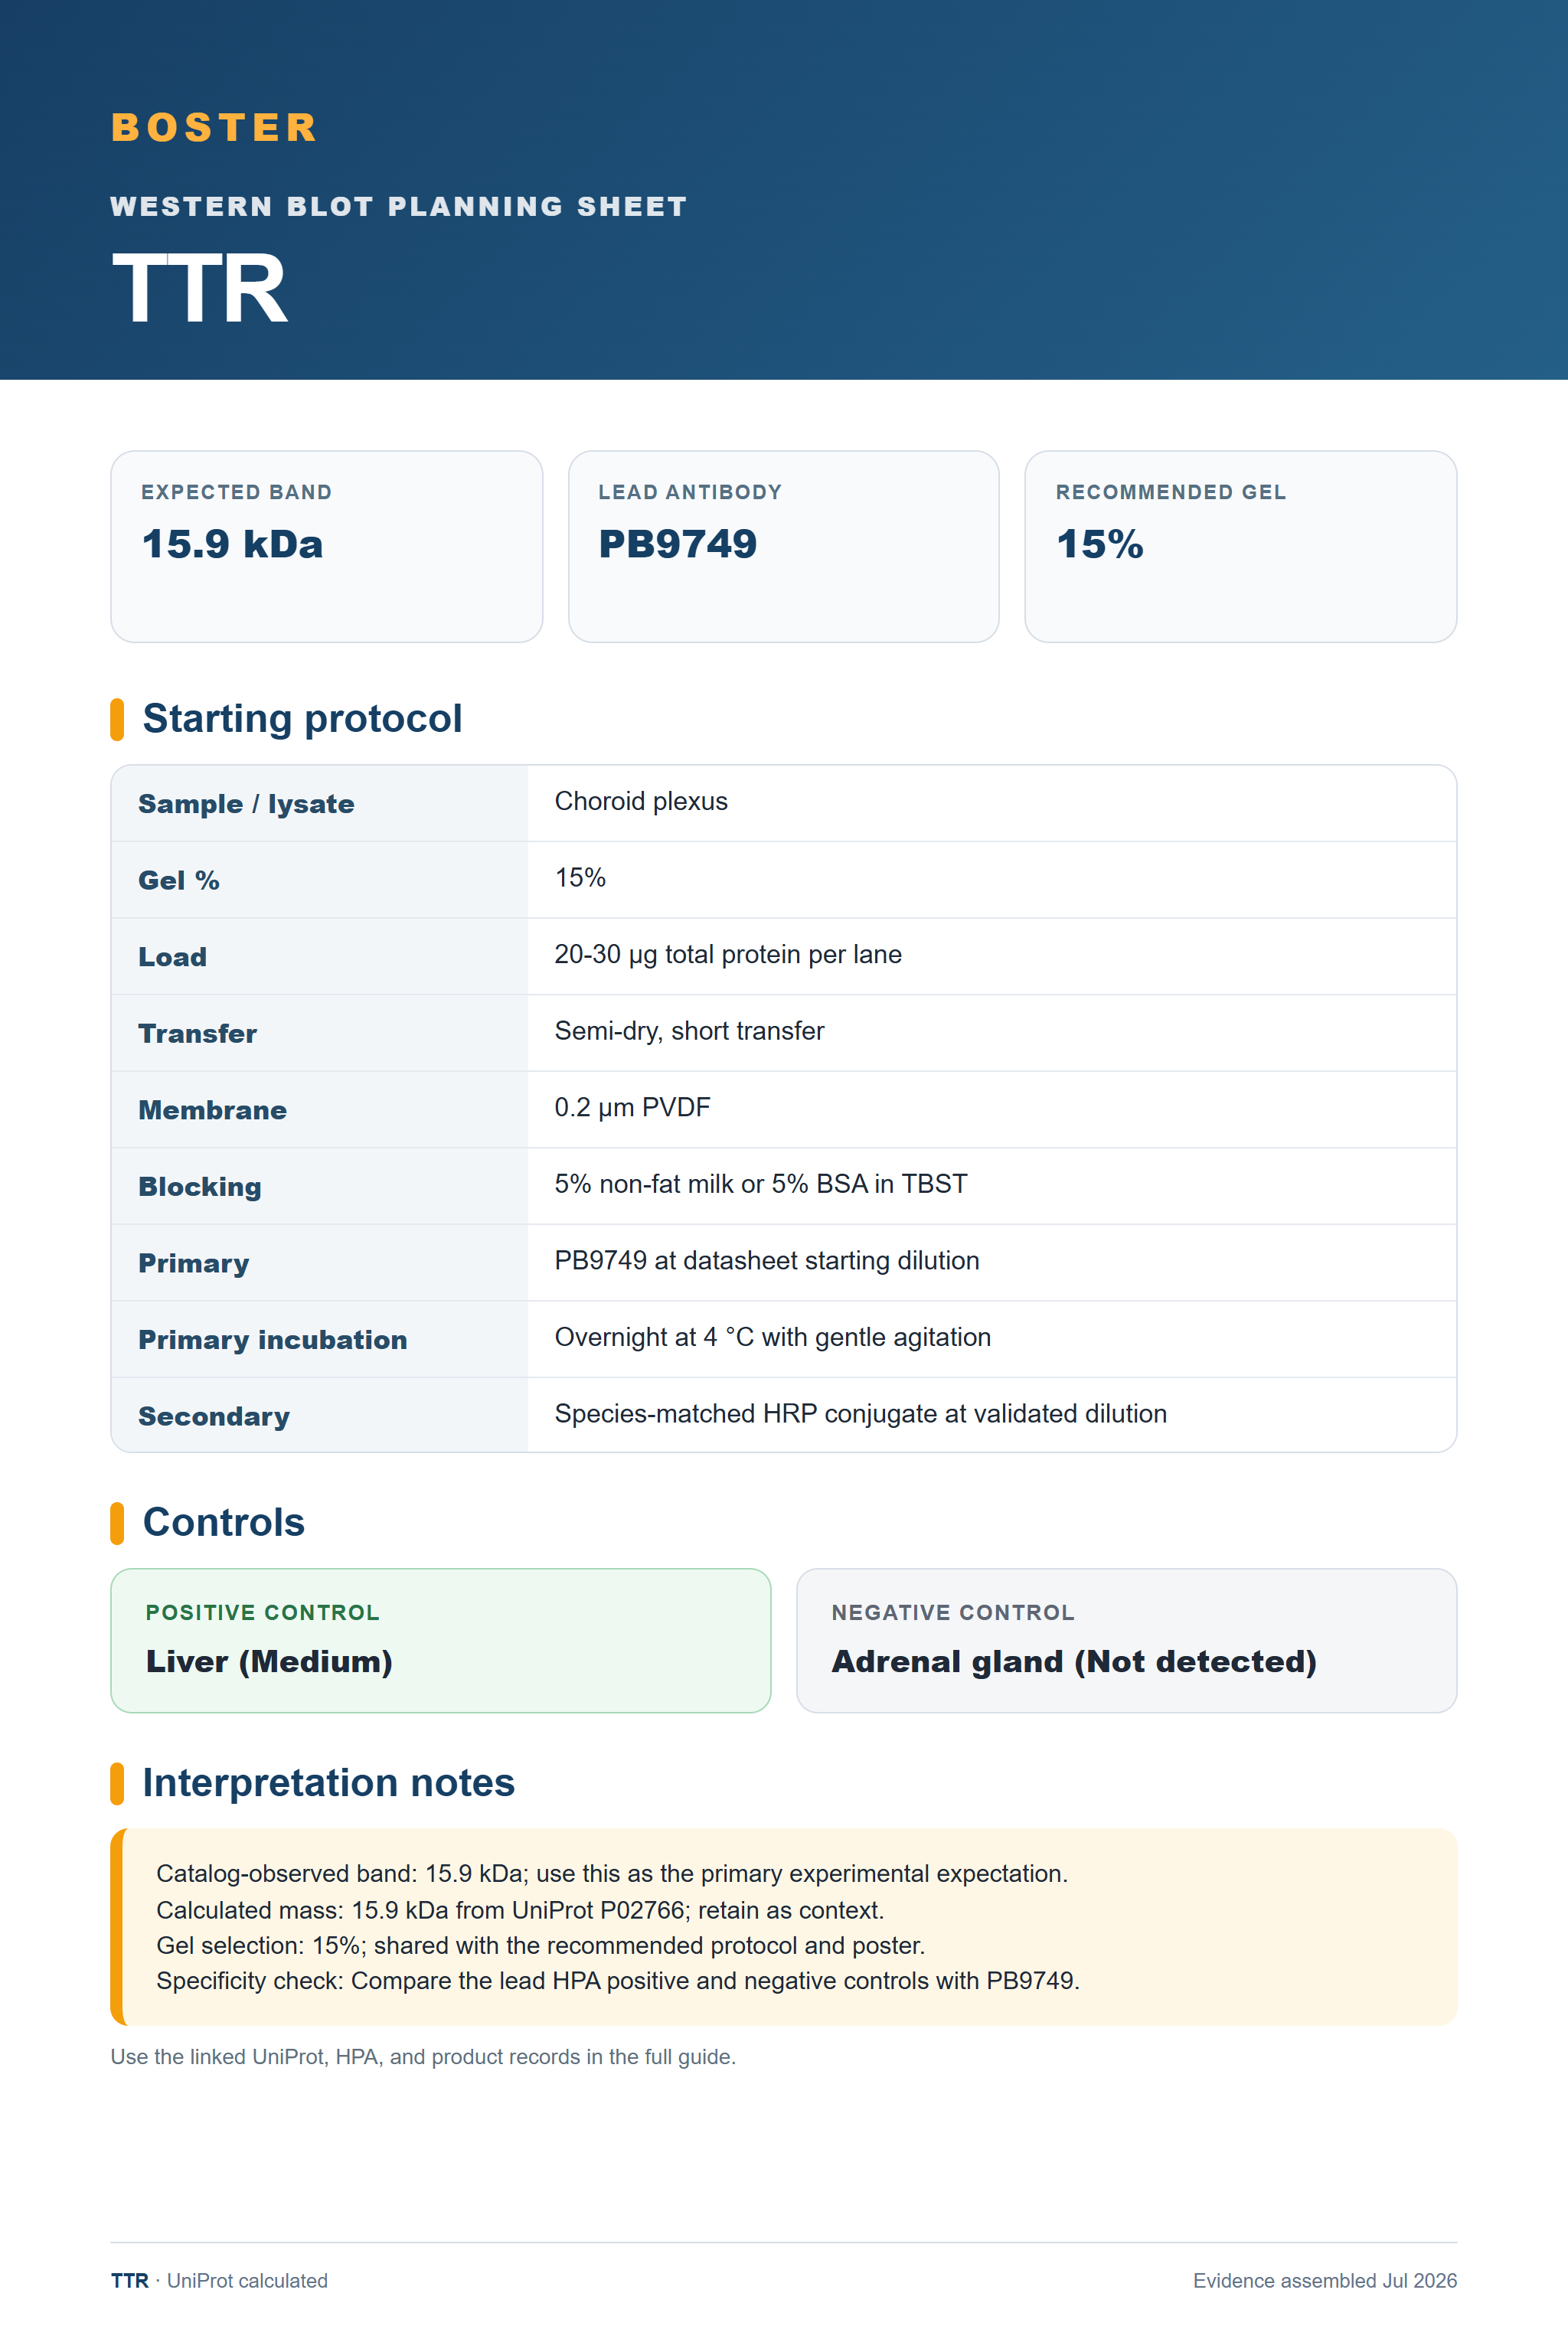
Expected bands, documented protocol parameters, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected band | 15.9 kDa | |
| Observed band | Not reported — verify product WB image | |
| Gel | 15% | |
| Positive control | Liver | |
| Negative control | Adrenal gland |
| ⓘ | Calculated mass | 15.9 kDa |
| ⓘ | Localization | Secreted / Cytoplasm |
| ⓘ | Processing / PTM | Record-dependent |
| ⓘ | Reactivity | Human |
Start with the molecular-weight rule, then compare verified publication-derived conditions.
| Sample / lysate | Choroid plexus |
| Gel % | 15% |
| Load | 20-30 µg total protein per lane |
| Transfer | Semi-dry, short transfer |
| Membrane | 0.2 µm PVDF |
| Blocking | 5% non-fat milk or 5% BSA in TBST |
| Primary | PB9749 at datasheet starting dilution |
| Primary incubation | Overnight at 4 °C with gentle agitation |
| Secondary | Species-matched HRP conjugate at validated dilution |
| Wash | 3 × 5 min in TBST |
| Detection | Chemiluminescent substrate |
| Exposure | Bracket exposures to avoid saturation |
Use the product-observed 15.9 kDa band as the primary planning value and retain the UniProt calculated mass as context.
| 15.9 kDa | Matches the authoritative product WB observation. |
| 15.9 kDa calculated | Use as UniProt context, not as a replacement observed band. |
| Unexpected additional signal | Do not assign identity without orthogonal positive/negative controls. |
| Catalog-observed band | 15.9 kDa; use this as the primary experimental expectation. |
| Calculated mass | 15.9 kDa from UniProt P02766; retain as context. |
| Gel selection | 15%; shared with the recommended protocol and poster. |
| Specificity check | Compare the lead HPA positive and negative controls with PB9749. |
| Situation | Likely cause | Next action |
|---|---|---|
| 15.9 kDa | Matches the authoritative product WB observation. | Confirm with orthogonal controls and the linked product record. |
| Additional band | May reflect processing, modification, or non-specific signal. | Run a dilution series and compare positive/negative controls. |
| Weak signal | Target abundance or transfer may be limiting. | Verify transfer, increase positive-control abundance, and bracket exposure. |

Comprehensive Human Protein Atlas IHC scoring per tissue. Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Liver | Reported tissue cells | Medium | Protein (HPA) | HPA → |
| Pancreas | Reported tissue cells | Medium | Protein (HPA) | HPA → |
| Choroid plexus | Reported tissue cells | Medium | Protein (HPA) | HPA → |
| Kidney | Reported tissue cells | Low | Protein (HPA) | HPA → |
Deeper troubleshooting and optimisation questions for TTR, answered from its protein features.
Human-reactive TTR Western blot reagents with authoritative product imagery.
Only image-backed, WB-validated Human/Mouse/Rat recommendations from the prepared catalog evidence are shown.