This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan XRCC5/Ku80 paraffin-section IHC using the reported ubiquitous nuclear pattern (HPA tissue IHC). Compare staining in high-expression breast glandular cells with the lack of detectable staining in liver cholangiocytes (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Ubiquitous nuclear staining (HPA tissue IHC) | |
| Staining pattern | Nuclear staining; high in breast glandular cells (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet PA1641) | |
| Positive control | Appendix+4 more · see all | |
| Negative control | Liver |
| Fixation | Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific) | |
| Caveat | Liver cholangiocytes have no detectable staining (HPA tissue IHC) | |
| Regulation | Ku70 binding stabilizes Ku80 (UniProt) | |
| Isoform / epitope | No annotated isoforms; mature chain spans residues 2–732 (UniProt) |
The catalog antibody uses EDTA retrieval (datasheet: PA1641). Published XRCC5 IHC protocols cover mouse xenograft tumors (PMC5648251), lung cancer specimens (PMC5354834), and gastric cancer specimens (PMC6137920).
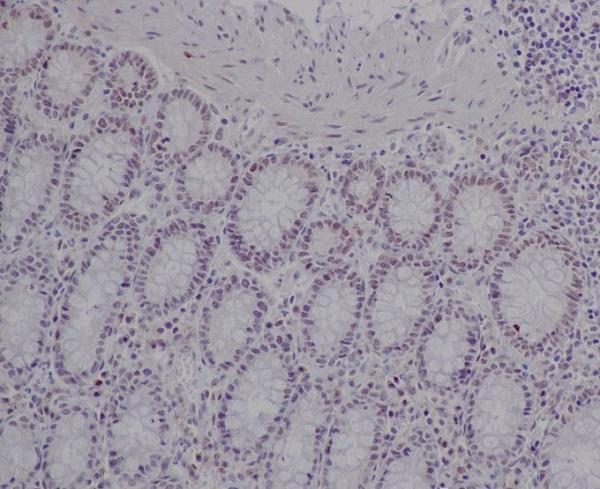
| Sample | Paraffin-embedded human intestinal cancer tissue; fixative not specified (datasheet PA1641) |
| Fixation | Image fixative and duration unreported (datasheet PA1641); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet PA1641); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet PA1641) |
| Primary antibody | Rabbit anti-XRCC5, 0.5-1μg/ml (datasheet PA1641) |
| Primary incubation | Overnight at 4 °C (datasheet PA1641) |
| Detection | Streptavidin-biotin complex (SABC), DAB chromogen (datasheet PA1641) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | XRCC5-positive staining in endocrine cells of appendix (HPA tissue IHC: High). HPA tissue profile: Ubiquitous nuclear expression. No signal in the no-primary control. |
XRCC5 should appear predominantly in nuclei across many cell types (HPA: ubiquitous nuclear expression; UniProt P13010: nucleus). HPA reports high staining in breast glandular cells, bone marrow hematopoietic cells, and several other cell populations (HPA: tissue IHC). Its tissue IHC reliability is Supported, with medium consistency between staining and RNA expression (HPA: tissue IHC). XRCC5 has no transmembrane segment (UniProt P13010: topology).
| Nuclear staining in breast glandular cells or bone marrow hematopoietic cells (HPA: High in both). | This fits the reported tissue pattern when nuclear staining is clearly distinguishable from background (HPA: ubiquitous nuclear expression; standard IHC practice). Compare cells within the section as well as a control section, because HPA reports differing staining levels among cell populations (HPA: tissue IHC). |
| Strong cytoplasmic or membrane staining with little nuclear signal (HPA: expected nuclear pattern). | Treat this as a localisation mismatch requiring investigation, not evidence of the expected XRCC5 pattern (HPA: ubiquitous nuclear expression; UniProt P13010: nucleus, no transmembrane segment). Check the no-primary control and whether the nuclear counterstain identifies intact nuclei (standard IHC practice). |
| Strong staining in liver cholangiocytes, a population reported as Not detected (HPA: tissue IHC). | Consider cross-reactivity or endogenous chromogenic activity and inspect controls (standard IHC practice). The HPA observation applies to cholangiocytes in its liver material; it does not establish that every liver cell or every preparation must be negative (HPA: tissue IHC). |
| Diffuse colour over nuclei, cytoplasm, and empty areas (standard IHC practice). | This obscures a nuclear interpretation and suggests nonspecific background or detection-system activity (standard IHC practice). Compare a no-primary control, review blocking and washing, and assess whether colour extends beyond tissue boundaries (standard IHC practice). |
| No nuclear signal in a section containing breast glandular cells reported High by HPA (HPA: tissue IHC). | First assess section quality and the IHC detection run with controls, then review antibody use and antigen retrieval (standard IHC practice). HPA's High observation supports this as a useful comparison, but does not establish that every specimen will stain strongly (HPA: tissue IHC). |
| Compartment and tissue context (UniProt P13010: nucleus; HPA: tissue IHC). | Expect a predominantly nuclear readout across tissues, with cell-level variation: HPA reports High staining in breast glandular cells and Not detected in liver cholangiocytes (HPA: tissue IHC). Use those observations as context, not universal specimen-level thresholds (HPA: Supported, medium consistency). |
| Antibody evidence (HPA: antibody validation). | HPA lists IHC as Supported for HPA025813 and CAB004468; HPA064685 has ICC Supported but no IHC status listed (HPA: antibody validation). Match any comparison to the antibody and application actually used; an ICC status alone supplies no IHC validation claim (HPA: antibody validation). |
| Antigen retrieval in paraffin-section IHC (standard IHC practice). | Record the retrieval condition and compare runs with the same condition when troubleshooting signal (standard IHC practice). No supplied source establishes an XRCC5-specific retrieval optimum or fixation sensitivity; HPA staining levels and UniProt features cannot determine one (HPA: tissue IHC; UniProt P13010: record). |
| Detection-system background (standard chromogenic IHC practice). | A no-primary control helps identify colour generated without primary-antibody binding; endogenous activity and nonspecific detection can confound interpretation (standard IHC practice). Judge the pattern against nuclear counterstaining and tissue morphology before scoring (standard IHC practice). |
| IF/ICC Q: Where should XRCC5 appear? (HPA: subcellular ICC-IF). | A: Mainly in the nucleoplasm; HPA supports this main location and lists ICC as Supported for HPA025813 and HPA064685 (HPA: subcellular ICC-IF; HPA: antibody validation). That IF observation complements the nuclear IHC expectation but does not supply an IHC protocol (HPA: tissue IHC; HPA: subcellular ICC-IF). |
| Situation | Likely cause | Next action |
|---|---|---|
| Nuclear staining is weak in breast glandular cells (HPA: High in breast glandular cells). | The run may have limited signal, or the specimen may differ from HPA's observed material (standard IHC practice; HPA: tissue IHC). | Check a positive comparison section and detection controls; review the recorded retrieval and primary-antibody conditions before changing them (standard IHC practice). |
| No staining appears anywhere, including expected positive cells (HPA: ubiquitous nuclear expression). | A failed staining or detection step is possible; a blank slide alone cannot establish absent XRCC5 (standard IHC practice). | Confirm tissue is present and preserved, verify the primary and detection steps, and examine a separately processed positive control (standard IHC practice). |
| Cytoplasmic or membrane colour dominates (HPA: expected nuclear expression). | The compartment conflicts with HPA and UniProt localisation; nonspecific binding or detection background is possible (HPA: tissue IHC; UniProt P13010: nucleus; standard IHC practice). | Inspect a no-primary control, nuclear counterstain, and cell boundaries; withhold a positive XRCC5 call until nuclear staining is resolved (standard IHC practice). |
| Strong colour appears in HPA Not detected liver cholangiocytes (HPA: tissue IHC). | Cross-reactivity or endogenous activity is possible, though HPA's observation cannot define every specimen's result (standard IHC practice; HPA: tissue IHC). | Compare no-primary and positive controls, assess whether colour is nuclear, and record the discrepancy without treating cholangiocytes as a universal negative control (standard IHC practice; HPA: tissue IHC). |
| Diffuse colour makes nuclei hard to score (standard IHC practice). | Background from detection chemistry, nonspecific binding, or insufficient washing may obscure the compartment (standard IHC practice). | Compare the no-primary control and review blocking, washing, and chromogen development; score only cells whose nuclear signal can be separated from background (standard IHC practice). |
| IF/ICC looks nucleoplasmic, but the IHC section has no clear nuclear signal (HPA: subcellular ICC-IF; HPA: tissue IHC). | The applications have different preparation and detection workflows; concordant IF localisation does not establish that an IHC run succeeded (standard IHC/IF practice). | Evaluate IHC controls and its antibody's IHC status independently; HPA lists IHC Supported for HPA025813 and CAB004468 (standard IHC practice; HPA: antibody validation). |




Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Appendix | Endocrine cells | High | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | High | Protein (IHC) | HPA → |
| Breast | Glandular cells | High | Protein (IHC) | HPA → |
| Caudate | Glial cells | High | Protein (IHC) | HPA → |
| Cerebellum | Cells in granular layer | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Liver | Cholangiocytes | Not detected | Protein (IHC) | HPA → |
Use nuclear staining as the primary readout for XRCC5 in paraffin section IHC, with retrieval and detection anchored to the PA1641 tissue protocol (HPA tissue IHC; PA1641 tissue IHC caption).
Human paraffin-section IHC is shown for intestinal cancer, lung cancer, and colon (catalog IHC captions); IF is shown in A549 and U20S cells (catalog IF captions).
PA1641 shows IHC in human intestinal cancer paraffin sections and IF in A549 cells (PA1641 image captions); PB9464 shows IHC in human lung cancer paraffin sections and IF in U20S cells (PB9464 image captions). M01275 shows IHC in paraffin-embedded human colon (M01275 IHC caption).
Which to pick: For tissue IHC, choose PA1641 for human intestinal cancer, PB9464 for human lung cancer, or monoclonal M01275 for human colon; each has a paraffin-section IHC image for that sample (respective IHC captions; M01275 catalog: clone FAE-24). For IF/ICC, PA1641 has an A549 IF image and PB9464 has a U20S IF image; M01275 lists IF without an IF image (catalog applications and IF captions). For cross-species planning, PB9464 lists human, mouse, and rat reactivity, while its paraffin-section IHC listing and image document human samples; the fixative is unreported in all three paraffin-section IHC captions (PB9464 catalog reactivity and IHC listing; respective IHC captions).