CTCF / Transcriptional repressor CTCF · IHC design guide

Design Immunohistochemistry for CTCF

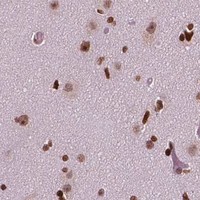
Plan CTCF IHC-P around broadly nuclear tissue staining (HPA tissue IHC). This guide uses the catalog antibody's formaldehyde-fixed paraffin-section example at 1:25 to inform tissue controls and nuclear scoring (datasheet M00132-1).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for CTCF (IHC for CTCF): expected localisation Nuclear staining across tissues (HPA tissue IHC), antibody M00132-1, validated IHC image, and IHC protocol steps
Printable CTCF IHC protocol sheet — expected localisation Nuclear staining across tissues (HPA tissue IHC), antibody M00132-1, controls and protocol steps. Open the full CTCF IHC guide →

CTCF Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nuclear staining across tissues (HPA tissue IHC)
Staining pattern Broad nuclear staining in glandular and hematopoietic cells (HPA tissue IHC)
Antigen retrieval Citrate pH 6 HIER, heat-mediated (datasheet M00132-1)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ None in HPA (detected in all 45 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Use formaldehyde-fixed paraffin sections (datasheet M00132-1). (selected-SKU IHC image M00132-1)
Caveat Cerebellar cells may show cytoplasm/membrane staining (HPA tissue IHC)
Regulation Absent in primary spermatocytes (UniProt)
Isoform / epitope Two isoforms; epitope coverage is unspecified (UniProt)
Section 1

Recommended CTCF IHC & IF Protocols

The catalog antibody uses citrate pH 6 heat retrieval (datasheet M00132-1). The three published IHC protocols below report conditions for breast and adrenal sections (PMC2409935; PMC10585925; PMC7229322).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleFormaldehyde-fixed, paraffin-embedded human colon tissue (datasheet M00132-1)
FixationImage formalin-fixed; duration unreported (datasheet M00132-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: Citrate pH 6 (datasheet M00132-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-CTCF, 1:25 (datasheet M00132-1)
Primary incubation1 hours at 37°C (datasheet M00132-1)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultCTCF-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Ubiquitous nuclear expression. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6 heat retrieval (datasheet M00132-1); the breast tissue protocol specifies microwave treatment in sodium citrate at pH 6.0 for 20 min (PMC2409935).
Section 2

What Is the Expected CTCF Staining Pattern?

CTCF should stain predominantly in nuclei, consistent with its nucleoplasmic and chromosomal localization and lack of a transmembrane segment (UniProt P49711). Expect staining across many cell types rather than one restricted tissue compartment: HPA reports ubiquitous nuclear expression, low tissue specificity, and high consistency between antibody staining and RNA expression (HPA tissue IHC: Supported). Assess the named cell populations and their nuclei, rather than treating all tissue areas as equally informative (standard IHC practice).

What am I looking at on my slide?
Chromogenic signal is concentrated in nuclei across a section, including glandular cells in adrenal gland or appendix and hematopoietic cells in bone marrow (HPA tissue IHC: High).This fits the reported ubiquitous nuclear profile and the named high-staining populations (HPA tissue IHC). Judge whether nuclei are distinctly stained above local background; the supplied HPA levels do not define a numeric intensity threshold (HPA tissue IHC; standard IHC practice).
Signal is chiefly cytoplasmic or membranous, with little nuclear staining.That conflicts with the expected nucleoplasmic localization (UniProt P49711; HPA subcellular: nucleoplasm supported). Consider nonspecific staining or detection artefact (standard IHC practice). HPA separately lists high cytoplasm/membrane staining in cerebellar molecular layer cells; that entry warrants review, not a general cytoplasmic criterion for CTCF (HPA tissue IHC).
A cell population outside the named HPA high-staining examples is positive.Broad staining alone is plausible because CTCF is reported as ubiquitous with low tissue specificity (UniProt P49711; HPA tissue IHC). If the signal is in an unexpected compartment or persists in a detection control, assess cross-reactivity or endogenous detection activity (standard IHC practice); cell type alone cannot establish either cause.
Chromogen is diffuse over tissue, between cells, or in areas without discernible nuclear boundaries.This does not provide a clear nuclear readout (HPA tissue IHC: ubiquitous nuclear expression). Uneven background can obscure genuine positives; review blocking, washing, chromogen development, and detection controls as general IHC checks (standard IHC practice), without inferring CTCF-specific fixation sensitivity.
Nuclei are unstained in a section expected to contain HPA high-staining cells.First verify the identity and preservation of the expected cells and the assay controls (standard IHC practice). HPA names high staining in adrenal or appendix glandular cells and bone marrow hematopoietic cells (HPA tissue IHC); absence there raises an assay question but does not, by itself, prove that CTCF is absent.
💡Expected CTCF appearanceCall positive when identifiable nuclei show clear chromogenic staining in expected cells, such as HPA high-staining glandular or hematopoietic populations; predominant cytoplasmic signal or diffuse chromogen without nuclear definition is suspect (HPA tissue IHC: High; HPA subcellular: nucleoplasm supported; standard IHC practice).
How each factor affects the staining
Cell and tissue choiceCTCF has ubiquitous expression, while primary spermatocytes are reported absent (UniProt P49711). HPA reports low tissue specificity, named high-staining populations, and low staining in liver cholangiocytes; a low-staining population is a poor sole positive control (HPA tissue IHC; standard IHC practice).
Compartment and cell stateThe main expected compartment is nucleoplasm (HPA subcellular: supported). UniProt also records chromosome and centromere association during metaphase and possible nucleolar translocation upon differentiation; these qualifications should be interpreted in cell context, not used to redefine the routine interphase IHC pattern (UniProt P49711).
Antibody evidenceHPA lists IHC as Supported for HPA004122, CAB062550, CAB068181, and CAB068182 (HPA antibodies). The supplied antibody list does not label any of these IHC results Enhanced (HPA antibodies); compare localization and appropriate controls when choosing an IHC-validated antibody (standard IHC practice).
Protein forms and modificationsUniProt reports two isoforms, one chain spanning residues 1–727, no signal peptide, no propeptide, no transmembrane segment, and annotated modified residues (UniProt P49711). These facts alone do not identify an antibody epitope or establish retrieval conditions or fixation sensitivity.
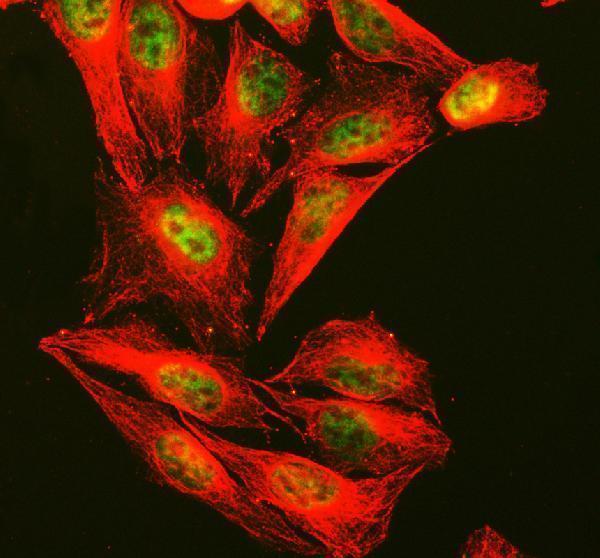
IF/ICC Q: Where should CTCF appear?A: Predominantly in the nucleoplasm; HPA reports supported nucleoplasmic localization and lists A-431, U-251MG, and U2OS ICC-IF image lines (HPA subcellular). This localization answer does not supply an IF/ICC protocol.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Little or no nuclear staining in a known HPA high-staining population.The expected cells may be missing or hard to identify, or an assay step may have failed (HPA tissue IHC: High; standard IHC practice). The supplied sources do not establish CTCF-specific fixation sensitivity.Confirm tissue and cell identity, inspect the counterstain, and check a concurrently processed positive control and reagent steps (standard IHC practice).
Strong cytoplasmic or membranous staining dominates.The predominant compartment conflicts with supported nucleoplasmic localization (HPA subcellular). HPA's cerebellar molecular layer cytoplasm/membrane entry is a tissue-specific observation, not proof that every such signal is specific (HPA tissue IHC).Compare nuclear and extranuclear signal in the same section, review detection controls, and seek concordant staining with another IHC-supported antibody where available (HPA antibodies; standard IHC practice).
Diffuse chromogen obscures nuclear outlines.Excess background may arise from detection reagents, inadequate blocking or washing, or overdevelopment (standard IHC practice); the supplied HPA and UniProt records do not assign a CTCF-specific cause.Inspect a primary-antibody-omission control and optimize blocking, washes, and development time according to the assay system (standard IHC practice).
Signal appears in a cell type absent from the named HPA high-staining list.The list is not exhaustive: HPA reports ubiquitous nuclear expression and low tissue specificity (HPA tissue IHC). An unexpected cell type alone does not demonstrate cross-reactivity.Check that staining is nuclear, identify the cells morphologically, and compare controls before assigning specificity (HPA subcellular: nucleoplasm supported; standard IHC practice).
Liver cholangiocytes stain weakly while other nuclei stain clearly.Low staining is reported for cholangiocytes, whereas the overall tissue profile is ubiquitous nuclear expression (HPA tissue IHC). Weak signal in this population alone does not establish assay failure.Score cholangiocytes separately and judge assay performance using an appropriate HPA high-staining population and controls (HPA tissue IHC; standard IHC practice).
An apparent negative result comes from primary spermatocytes.UniProt reports CTCF absent in primary spermatocytes (UniProt P49711), so this population is unsuitable as the sole positive benchmark.Use a named HPA high-staining cell population to check the assay, then interpret the spermatocyte result in its own tissue context (HPA tissue IHC: High; UniProt P49711; standard IHC practice).

Sample controls for CTCF IHC & IF

🧪Run bronchus first: respiratory epithelial cell nuclei should stain strongly (HPA: High in bronchus respiratory epithelial cells; UniProt P49711: nucleoplasm). HPA detects CTCF in all 45 scored tissues, so there is no supported negative tissue; use no-primary and isotype controls, and expect no defined population of negative cells within the positive section (HPA: detected in all 45 scored tissues).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: None in HPA: CTCF is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show CTCF in A-431, U-251MG, U2OS, with annotated localisation: Nucleoplasm (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only slide and a nonimmune control matched to the primary antibody’s host species, isotype and monoclonal or polyclonal format; use validated CTCF knockout material as a biological negative. For bronchus chromogenic IHC, block endogenous peroxidase and check for endogenous biotin if using the caption’s biotinylated secondary (selected SKU caption: biotinylated secondary).
⚠️Feasibility: No matched evidence reports a CTCF-specific fixation window or fixation effect, and the fixative for the selected M00132-1 tissue-IHC caption is unreported (selected SKU caption: fixative unreported). Heat-mediated citrate retrieval at pH 6 is documented for that paraffin-section example; whether staining depends on retrieval is unreported (selected SKU caption: citrate retrieval, pH 6). The supplied evidence does not establish whether frozen sections or IF are easier; bronchial autofluorescence may complicate IF, while the expected signal is nucleoplasmic (HPA: supported nucleoplasmic localization).

HPA tissue IHC evidence for CTCF

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — High consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Glandular cells High Protein (IHC) HPA →
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Breast Myoepithelial cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: CTCF is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced CTCF IHC Tips

Troubleshoot CTCF staining by assessing nuclear signal, tissue morphology, matched controls and scoring consistency (UniProt P49711; HPA tissue IHC).

What retrieval conditions should I try first if CTCF nuclear staining is weak?
Start with heat-mediated retrieval in citrate buffer at pH 6 (datasheet M00132-1). Keep heating and cooling conditions consistent across sections, then assess nuclear signal alongside tissue morphology and a no-primary control (standard IHC practice; HPA tissue IHC). The selected tissue image used this retrieval with a 1:25 primary antibody dilution for 1 hour at 37°C, so it provides a useful starting combination for this antibody (datasheet M00132-1). If staining remains weak, adjust retrieval duration cautiously on adjacent sections and compare nuclear signal with background before changing several variables at once (standard IHC practice; HPA tissue IHC).
Could fixation explain weak CTCF staining in my paraffin sections?
Target-specific fixation sensitivity is unknown from the supplied evidence; do not infer it from CTCF localisation or tissue staining patterns (UniProt P49711; HPA tissue IHC). In chromogenic IHC, compare sections with documented fixation histories while holding retrieval, antibody dilution and detection conditions constant (standard IHC practice). Inadequate fixation can impair morphology, while extensive fixation can reduce epitope accessibility, so inspect both tissue structure and nuclear signal before changing the staining workflow (standard IHC practice; HPA tissue IHC). Record fixative, fixation duration and processing for each specimen, and interpret any difference as an observed processing effect until controlled sections establish its cause (standard IHC practice).
Where should convincing CTCF staining appear in a paraffin section?
Expect predominantly nuclear chromogenic staining: CTCF is reported in the nucleoplasm and on chromosomes, and tissue IHC shows ubiquitous nuclear expression (UniProt P49711; HPA tissue IHC). Evaluate signal against a nuclear counterstain so brown precipitate outside intact nuclei is not scored automatically as CTCF (standard IHC practice; HPA tissue IHC). UniProt also reports centromere and chromosome-arm association during metaphase and possible nucleolar translocation with differentiation, so unusual nuclear patterns deserve morphological review rather than immediate rejection (UniProt P49711). Predominantly diffuse cytoplasmic staining conflicts with the supported nucleoplasmic location and should prompt checks of background, section quality and antibody specificity (HPA subcellular; standard IHC practice).
Can this antibody distinguish CTCF isoforms or modified epitopes in IHC?
The record lists 2 CTCF isoforms and several modified residues, including phosphothreonines at 289, 317 and 374 (UniProt P49711). No epitope mapping or isoform-specific staining evidence is supplied for the catalog antibody, so a nuclear IHC signal cannot be assigned to either isoform or a particular modification (UniProt P49711; datasheet M00132-1). CTCF also has a CTCFL paralog; assess any claimed discrimination using antibody-specific validation rather than the shared family name (UniProt P49711; standard IHC practice). For the chromogenic readout, report nuclear staining as CTCF immunoreactivity and document the antibody and retrieval conditions without claiming molecular-form resolution (standard IHC practice).
How should I investigate CTCF localisation with multiplex IF alongside this IHC guide?
Treat multiplex IF as a separate assay from this chromogenic IHC workflow; CTCF has supported nucleoplasmic localisation in IF images from A-431, U-251MG and U2OS cells (HPA subcellular). Pair CTCF with a marker for the cell population being examined and a nuclear counterstain, then check whether the signals occupy the expected cells and nuclei (standard IF practice; HPA subcellular). Choose fluorophores after examining tissue autofluorescence and include single-stain controls to assess bleed-through (standard IF practice). CTCF lacks a transmembrane segment, so permeabilisation should provide access to an intracellular nuclear epitope; optimise it for the IF specimen without treating the IHC retrieval conditions as an IF protocol (UniProt P49711; standard IF practice).
How can I reduce diffuse brown staining without losing nuclear CTCF signal?
First compare the stained section with a no-primary control and inspect whether precipitate follows tissue edges, damaged areas or endogenous pigment rather than nuclei (standard IHC practice; HPA tissue IHC). The selected image used 3% BSA blocking for 30 minutes at room temperature and a 1:25 primary antibody dilution; these are documented starting conditions for this antibody (datasheet M00132-1). For peroxidase-based chromogenic detection, include an appropriate endogenous peroxidase block and check secondary-reagent background as general workflow controls (standard IHC practice). If nuclear contrast remains poor, adjust primary concentration or detection exposure on adjacent sections while keeping retrieval and counterstaining consistent (standard IHC practice).
What should I measure when comparing CTCF IHC across sections? ⚠ ANSWER MARKED FOR VERIFICATION
Score CTCF within intact nuclei of a defined cell population, because the supported tissue pattern is nuclear and broadly distributed (HPA tissue IHC). Report the percentage of positive nuclei and staining intensity, or calculate an H-score from intensity categories 0–3 and their percentages, yielding 0–300 (standard IHC practice). Normalise counts to the number of evaluable nuclei in the same compartment; if measuring positive-cell density per mm², define the analysed tissue area and exclude folds or necrosis consistently (standard IHC practice). Apply one threshold, counterstain and imaging setup across comparison groups, and review controls before interpreting small score differences (standard IHC practice).
Which CTCF staining patterns suggest artefact rather than a biological difference?
A convincing positive pattern places chromogenic signal in intact nuclei, consistent with ubiquitous nuclear tissue staining and supported nucleoplasmic localisation (HPA tissue IHC; HPA subcellular). Predominant cytoplasmic colour, signal restricted to section edges or necrotic regions, and colour in a no-primary control point toward artefact requiring review (HPA subcellular; standard IHC practice). Consider endogenous enzyme activity when peroxidase detection produces staining in the control, and compare adjacent intact areas before scoring (standard IHC practice). Apparent differences between cell populations need morphological identification and matched processing controls; HPA reports broad nuclear expression, with low staining in liver cholangiocytes, rather than a universal intensity for every cell (HPA tissue IHC; standard IHC practice).
Boster reagents

Best CTCF / Transcriptional repressor CTCF IHC Antibodies

Anti-CTCF antibodies have IHC images from human colon paraffin sections and mouse and rat kidney (catalog image captions), plus IF images including U2OS cells (catalog image captions).

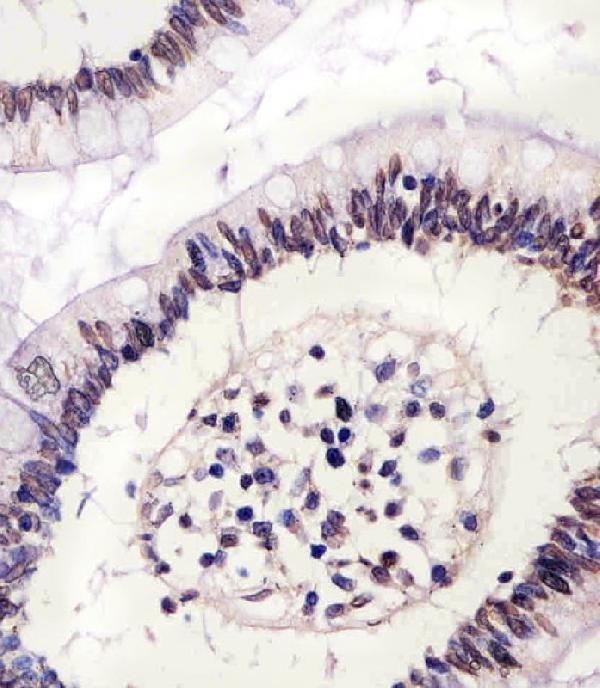
Real IHC data M00132-1 staining CTCF in human colon tissue sections by Immunohistochemistry (IHC-P -paraformaldehyde-fixed, paraffin-embedded sections). Tissue was fixed with formaldehyde and blocked with 3% BSA for 0. 5 hour at room temperature; antigen retrieval was by heat mediation with a citrate buffer (pH6). Samples were incubated with primary antibody (1/25) for 1 hours at 37°C. A undiluted biotinylated goat polyvalent antibody was used as the secondary antibody.
Anti-CTCF Antibody (Center)
Cat # M00132-1
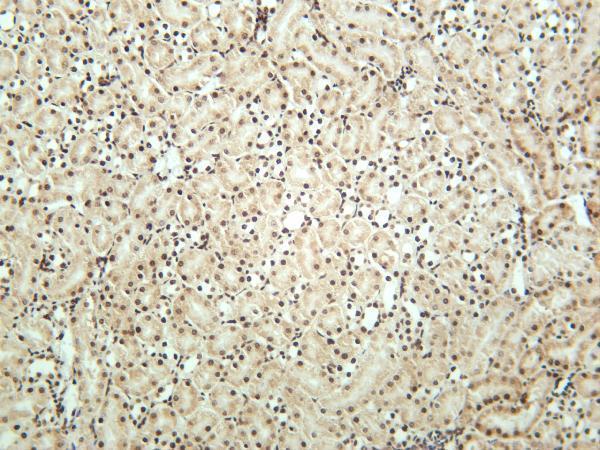
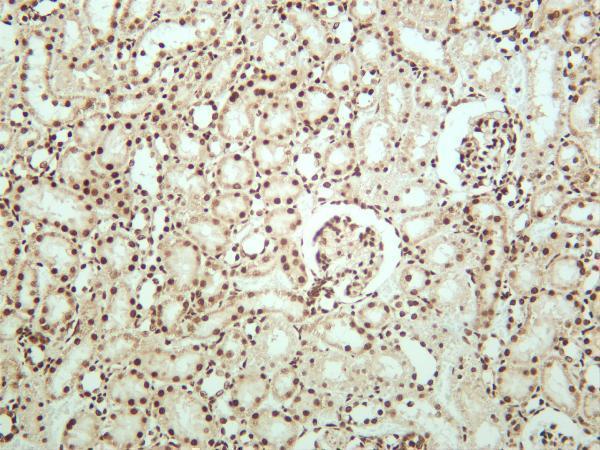
Real IHC data Mouse kidney was stained with anti-CTCF rabbit antibody
Anti-CTCF Rabbit Monoclonal Antibody
Cat # M00132-3
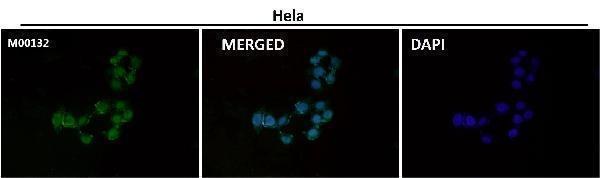
Real IF data Immunofluorescent analysis using the Antibody at 1:50 dilution.
Anti-CTCF Rabbit Monoclonal Antibody
Cat # M00132
Real IF data IF analysis of CTCF using anti-CTCF antibody (PB9493) and anti-Tubulin Alpha antibody (M03989-3). CTCF was detected in immunocytochemical section of U2OS cell. Enzyme antigen retrieval was performed using IHC enzyme antigen retrieval reagent (AR0022) for 15 mins. The cells were blocked with 10% goat serum. And then incubated with 5 μg/mL rabbit anti-CTCF Antibody (PB9493) and mouse anti-Tubulin Alpha antibody (M03989-3) overnight at 4°C. DyLight®488 Conjugated Goat Anti-Rabbit IgG (BA1127) and Cy3 Conjugated Goat Anti-Mouse IgG (BA1031) were used as secondary antibody at 1:500 dilution and incubated for 30 minutes at 37°C. Visualize using a fluorescence microscope and filter sets appropriate for the label used.
Anti-CTCF Antibody ®
Cat # PB9493

M00132-1 shows IHC in human colon paraffin sections (M00132-1 image caption); M00132-3 shows IHC in mouse and rat kidney (M00132-3 image captions). M00132 has IF images with sample type unreported (M00132 image captions); PB9493 shows IF in U2OS cells (PB9493 image caption).

Which to pick: For human paraffin-section IHC, choose M00132-1: its own image reports formaldehyde fixation, citrate retrieval at pH 6, and primary antibody at 1:25 (M00132-1 image caption). For cross-species IHC, consider M00132-3: it is monoclonal and lists human, mouse and rat reactivity, with kidney IHC images from mouse and rat; the image captions do not report fixation or section processing (M00132-3 catalog and image captions). For IF/ICC, M00132 lists both applications and has IF images; PB9493 lists both and shows U2OS cell IF at 5 μg/mL (M00132 catalog and image captions; PB9493 catalog and image caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P49711 (CTCF_HUMAN, Transcriptional repressor CTCF).
  2. Human Protein Atlas. CTCF tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. CTCF subcellular location (ICC-IF): Localized to the nucleoplasm..
  4. Human Protein Atlas. CTCF antibody validation summary (4 antibodies).
  5. Expression of the transcription factor CTCF in invasive breast cancer: a candidate gene located at 16q22.1. British journal of cancer 2004 — PMC2409935.
  6. Transgenerational inheritance of adrenal steroidogenesis inhibition induced by prenatal dexamethasone exposure and its intrauterine mechanism. Cell communication and signaling : CCS 2023 — PMC10585925.
  7. Association of mutation and low expression of the CTCF gene with breast cancer progression. Saudi pharmaceutical journal : SPJ : the official publication of the Saudi Pharmaceutical Society 2020 — PMC7229322.
  8. Expression of CCCTC-binding factor (CTCF) is linked to poor prognosis in prostate cancer. Molecular oncology 2020 — PMC6944131.
  9. PubMed PMID:8649389 — UniProt-cited evidence.
  10. PubMed PMID:9591631 — UniProt-cited evidence.
  11. PubMed PMID:11782357 — UniProt-cited evidence.