CTNNA1 / Catenin alpha-1 · IHC design guide

Design Immunohistochemistry for CTNNA1

Plan CTNNA1 paraffin-section IHC around the membranous and cytoplasmic tissue pattern (HPA tissue IHC). This guide covers fixation, controls and interpretation of variable staining, including unstained adipocytes (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for CTNNA1 (IHC for CTNNA1): expected localisation Membranous and cytoplasmic staining (HPA tissue IHC), antibody PB9137, validated IHC image, and IHC protocol steps
Printable CTNNA1 IHC protocol sheet — expected localisation Membranous and cytoplasmic staining (HPA tissue IHC), antibody PB9137, controls and protocol steps. Open the full CTNNA1 IHC guide →

CTNNA1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Membranous and cytoplasmic staining (HPA tissue IHC)
Staining pattern Variable membranous and cytoplasmic staining across tissues (HPA tissue IHC)
Antigen retrieval Citrate pH 6 HIER, heat-mediated (datasheet PB9137)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Adipose tissue
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific)
Caveat Adipocytes may be unstained despite broad tissue staining (HPA tissue IHC)
Regulation Variable expression across tissues (HPA tissue IHC)
Isoform / epitope 3 isoforms; no transmembrane split; epitope map unknown (UniProt)
Section 1

Recommended CTNNA1 IHC & IF Protocols

The catalog antibody’s IHC-P protocol uses citrate pH 6 heat retrieval (datasheet PB9137). The published liver-tissue protocol provides CTNNA1 dilution and chromogenic detection details (PMC12206905).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded rat intestine tissue; fixative not specified (datasheet PB9137)
FixationImage fixative and duration unreported (datasheet PB9137); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: Citrate pH 6, 20 min (datasheet PB9137)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet PB9137)
Primary antibodyRabbit anti-CTNNA1, 0.5-1μg/ml (datasheet PB9137)
Primary incubationOvernight at 4 °C (datasheet PB9137)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet PB9137)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultCTNNA1-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Membranous and cytoplasmic expression at variable levels in all tissues. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6 heat retrieval (datasheet PB9137); the published liver-tissue excerpt does not specify retrieval conditions (PMC12206905).
Section 2

What Is the Expected CTNNA1 Staining Pattern?

CTNNA1 should show membranous and cytoplasmic staining at variable levels across tissues, especially at cell–cell boundaries (HPA tissue IHC; UniProt P35221 localization). Strong examples include glandular, respiratory epithelial, squamous epithelial, and endothelial cells in the tissues listed below (HPA tissue IHC). The tissue IHC profile is rated Supported, with medium consistency between antibody staining and RNA expression (HPA tissue IHC). CTNNA1 has no transmembrane segment (UniProt P35221 topology).

What am I looking at on my slide?
Distinct cell-boundary staining with accompanying cytoplasmic color in glandular cells of breast or appendix.This fits the reported membranous and cytoplasmic profile; both cell populations are scored High (HPA tissue IHC). Judge the boundary pattern in recognizable cells, since neighboring cell types can stain differently (HPA tissue IHC).
Strong staining confined to nuclei, without convincing membrane or junction staining.This does not match the dominant tissue IHC pattern (HPA tissue IHC). UniProt also lists nuclear localization, so nuclear color alone cannot prove an artefact (UniProt P35221 localization). Check whether the expected boundary signal is present in a known-positive area before interpreting it.
Strong color in adipocytes, with little staining in the expected cells of a positive comparison section.Adipocytes are reported Not detected (HPA tissue IHC). Investigate cross-reactivity or endogenous detection activity as possible explanations (general IHC practice). An adipose section is not a blanket negative control: the HPA observation applies specifically to adipocytes.
Color spreads across extracellular spaces or covers many cell types without crisp boundaries.Diffuse color is less consistent with the reported membranous and cytoplasmic cell pattern (HPA tissue IHC). Nonspecific antibody binding or detection background are possible causes (general IHC practice); avoid scoring the haze as CTNNA1-positive cells.
No detectable color in glandular cells of breast, appendix, or duodenum.Those cells are reported High and provide useful positive comparisons (HPA tissue IHC). A blank result suggests an assay or section problem, but one negative slide cannot establish absent CTNNA1; assess tissue preservation and the run controls (general IHC practice).
💡Expected CTNNA1 appearanceCall a result positive when recognizable cells show crisp membranous or junctional staining with possible cytoplasmic color, including strong staining in the listed High cell populations; diffuse haze or color restricted to unexpected cells is suspect (HPA tissue IHC; UniProt P35221 localization).
How each factor affects the staining
Cell type and tissueExpression varies by cell population: bronchial respiratory epithelium and cervical squamous epithelium are High, while hippocampal neurons and smooth muscle cells are Low (HPA tissue IHC). Score the named cells, rather than assigning one intensity to an entire section.
Evidence behind the patternThe tissue IHC profile has Supported reliability and medium staining–RNA consistency (HPA tissue IHC). Three listed antibodies have Supported IHC status; only HPA063535 also has Supported ICC status (HPA antibody validation). These ratings support the reference pattern without validating every unexpected signal.
Protein location and formsCTNNA1 is associated with adherens junctions and cytoskeleton and has no transmembrane segment (UniProt P35221 localization and topology). Three isoforms are listed, but this record supplies no antibody epitope or isoform-specific staining pattern (UniProt P35221 isoforms). Do not assign a compartmental difference to an isoform from these data.
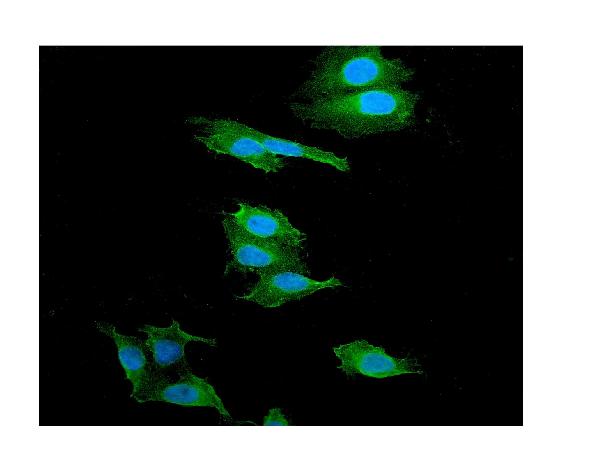
IF/ICC Q&A: What location should be expected?Mainly plasma membrane and cell junction signal, both supported; Golgi and vesicle locations are marked uncertain (HPA subcellular ICC-IF). This is a localization comparison only; IF/ICC procedure belongs in its own guide.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
The positive comparison section is blank.The assay may have failed, or the selected section may lack well-preserved expected cells (general IHC practice).Confirm the named cell type is present, then review the run control, primary-antibody step, chromogenic detection, and counterstain (general IHC practice). Compare with a High reference such as breast glandular cells (HPA tissue IHC).
Only diffuse brown color is visible.Nonspecific binding or detection background may obscure the cell boundaries (general IHC practice).Inspect a no-primary control; review blocking, washing, and detection steps (general IHC practice). Score CTNNA1 only where cell-associated membranous or cytoplasmic staining can be resolved (HPA tissue IHC).
Adipocytes stain strongly.Cross-reactivity or endogenous detection activity is possible (general IHC practice); adipocytes are Not detected in the reference profile (HPA tissue IHC).Check a no-primary control and a known-positive comparison, then reassess whether color belongs to adipocytes or adjacent cells (general IHC practice; HPA tissue IHC).
Signal appears only in nuclei.The slide lacks the dominant membranous and cytoplasmic pattern (HPA tissue IHC), although nuclear localization is listed (UniProt P35221 localization).Compare with a positive section for junctional staining and inspect the no-primary control (general IHC practice). Record the nuclear observation separately rather than treating it as established tissue IHC localization.
A low-staining cell population is scored negative.Hippocampal neuronal cells, smooth muscle cells, splenic red-pulp cells, and marrow hematopoietic cells are reported Low (HPA tissue IHC). Weak color can be hard to distinguish from background (general IHC practice).Use a High cell population and the run controls to judge assay performance (HPA tissue IHC; general IHC practice). Report weak or indeterminate staining at the cell-type level rather than upgrading it to a strong positive.
The slide shows strong signal in an unexpected cell type.The tissue profile varies by cell type, and an unexpected signal may reflect cross-reactivity or detection background (HPA tissue IHC; general IHC practice).Identify the stained cells, compare their HPA cell-specific level, and inspect a no-primary control (HPA tissue IHC; general IHC practice). Do not infer a new CTNNA1 distribution from one discordant section.

Sample controls for CTNNA1 IHC & IF

🧪Run breast first and require staining in its glandular cells (HPA: Breast glandular cells High). Use adipose tissue adipocytes as the negative tissue (HPA: Adipocytes Not detected); no cell type within the breast slide is established as CTNNA1-negative, so cells without junctional staining are local background comparators, not validated biological negatives (HPA: Breast glandular cells High; UniProt P35221: ubiquitously expressed).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show CTNNA1 in CACO-2, SiHa, U2OS, RPTEC/TERT1, hTERT-RPE1 (serum starved), Sperm, with annotated localisation: Plasma membrane (supported), Cell Junctions (supported) (HPA subcellular).
Technical controls: Include no-primary (secondary-only) and concentration-matched rabbit IgG isotype controls for the rabbit catalog antibody, plus a validated CTNNA1 knockout sample or peptide block as a biological specificity control (selected-SKU caption: rabbit antibody PB9137; standard IHC controls). For the breast section, quench endogenous peroxidase and check for endogenous biotin background when using the caption’s biotin-based DAB detection (selected-SKU caption: biotinylated secondary, SABC and DAB; standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected-SKU tissue-IHC caption does not state the fixative (selected-SKU caption: fixative unreported). The caption uses citrate retrieval at pH 6 for 20 minutes, but does not establish that retrieval is required for every specimen (selected-SKU caption: citrate retrieval). The supplied evidence does not establish whether frozen sections or IF are easier; IF images support plasma membrane and cell-junction localisation, while biotin-related background should be checked in the breast IHC section using the caption’s detection method (HPA: plasma membrane and cell junctions supported; selected-SKU caption: biotin-based DAB detection).

HPA tissue IHC evidence for CTNNA1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Glandular cells High Protein (IHC) HPA →
Breast Glandular cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →
Cerebral cortex Endothelial cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Section 3

Advanced CTNNA1 IHC Tips

Troubleshoot CTNNA1 staining in paraffin sections by checking retrieval, compartment-specific signal, controls, and scoring; use the IF guidance when comparing modalities.

What retrieval should I try first if CTNNA1 staining is weak?
Start with heat-mediated retrieval in citrate buffer at pH 6 for 20 minutes (datasheet PB9137). The selected paraffin-section image used that treatment before incubation with 1 μg/ml antibody overnight at 4°C, so keep those conditions together for the first comparison (datasheet PB9137). If signal remains weak, compare a second retrieval condition on adjacent sections while holding antibody concentration, detection, and exposure time constant (standard IHC practice). Judge improvement by sharper staining at cell boundaries, with cytoplasmic signal also possible, rather than by stronger staining everywhere (UniProt P35221 localisation; HPA: membranous and cytoplasmic tissue profile).
How can I assess whether fixation caused weak or patchy CTNNA1 staining?
The selected CTNNA1 image identifies paraffin-embedded rat intestine but does not report its fixative, so target-specific fixation sensitivity is unknown (datasheet PB9137). Record the fixative and processing history for each section before attributing weak signal to fixation, and compare sections processed as similarly as possible (standard IHC practice). Apply the stated citrate pH 6, 20-minute retrieval consistently when assessing this antibody (datasheet PB9137). If patchiness tracks tissue folds, damaged areas, or section edges, check section quality and detection controls before treating it as a biological difference (standard IHC practice).
Should CTNNA1 appear only at cell borders in chromogenic IHC?
Expect a prominent cell-boundary pattern because CTNNA1 participates in adherens junctions, and HPA supports plasma-membrane and cell-junction localisation (UniProt P35221 localisation; HPA subcellular: supported). Cytoplasmic staining can also be plausible: the tissue IHC profile reports membranous and cytoplasmic expression at variable levels (HPA tissue IHC profile). UniProt additionally lists cytoskeleton, cytoplasm, and nucleus, but those annotations alone do not establish that every compartment should stain in a given paraffin section (UniProt P35221 localisation). Compare each compartment with tissue architecture and a negative detection control before scoring diffuse signal as CTNNA1 (standard IHC practice).
Could an isoform or modified epitope explain discordant CTNNA1 staining?
CTNNA1 has 3 annotated isoforms and several modified residues, including phosphoserines at positions 264, 268, 295, and 297 (UniProt P35221 isoforms and modified residues). The supplied product caption does not identify its epitope or establish isoform recognition, so a staining difference cannot be assigned to either cause from this evidence (datasheet PB9137). Review the antibody's epitope documentation before interpreting regional loss as an isoform change, and compare matched sections under identical retrieval conditions (standard IHC practice). Score membrane-associated and cytoplasmic signal separately where morphology permits, since both are reported in tissue IHC (HPA tissue IHC profile).
How should I investigate CTNNA1 localisation with a secondary IF experiment?
Use IF as a separate localisation check, pairing CTNNA1 with a marker for the expected cell type and examining whether its signal follows cell contacts (HPA subcellular: supported plasma membrane and cell junctions; standard IF practice). Choose spectrally separated fluorophores after inspecting unstained tissue autofluorescence, and include single-label controls when multiplexing (standard IF practice). CTNNA1 has no transmembrane segment and associates with the cytoplasmic side of cadherin-containing junctional complexes, so assess whether permeabilisation exposes the intended epitope (UniProt P35221 topology and function; standard IF practice). The paraffin-section caption supplies an IHC retrieval method, not an IF fixation or permeabilisation protocol (datasheet PB9137).
How do I reduce diffuse brown background without losing junctional staining?
First compare a no-primary section with the CTNNA1-stained section to identify signal from detection reagents or endogenous tissue activity (standard chromogenic IHC practice). The selected method used a 10% goat-serum block, biotinylated goat anti-rabbit secondary, avidin–biotin detection, and DAB, so review each step when background is diffuse (datasheet PB9137). Include an appropriate endogenous-peroxidase block for DAB detection, and assess whether the biotin-based system contributes background in the specimen (standard chromogenic IHC practice). Adjust blocking, washing, or antibody concentration one variable at a time while preserving interpretable cell-boundary signal (standard IHC practice; HPA subcellular: supported cell junctions).
What should I measure when comparing CTNNA1 staining between paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, because CTNNA1 tissue staining can be membranous or cytoplasmic at variable levels (HPA tissue IHC profile). For comparable regions, record the percentage of positive cells and staining intensity, or calculate a compartment-specific H-score; use positive-cell density per mm² when cell counts per area answer the question (standard IHC scoring practice). Normalize to the number of evaluable cells or the measured viable tissue area, using the same threshold, region rules, and staining batch across groups (standard IHC scoring practice). Report membrane and cytoplasmic results separately rather than collapsing distinct patterns into one value (HPA tissue IHC profile; standard IHC scoring practice).
When is an apparent CTNNA1-positive focus more likely to be artefact?
Give greatest weight to staining that follows cell contacts with plausible cytoplasmic signal in intact cells, since junctional and cytoplasmic localisation are supported (UniProt P35221 localisation; HPA tissue IHC profile). Treat isolated staining in an unexpected compartment cautiously, especially when the same colour appears in no-primary controls (standard IHC practice). Check whether the focus follows a section edge, damaged or necrotic area, or endogenous enzyme activity rather than cell boundaries (standard chromogenic IHC practice). HPA reports variable expression across tissues and only medium consistency between staining and RNA data, so interpret a single focal result alongside morphology and controls (HPA tissue IHC reliability and profile).
Boster reagents

Best CTNNA1 / Catenin alpha-1 IHC Antibodies

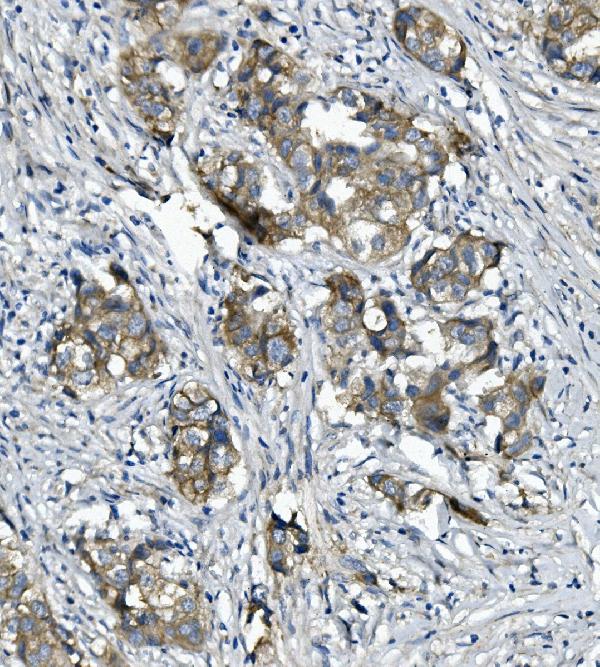
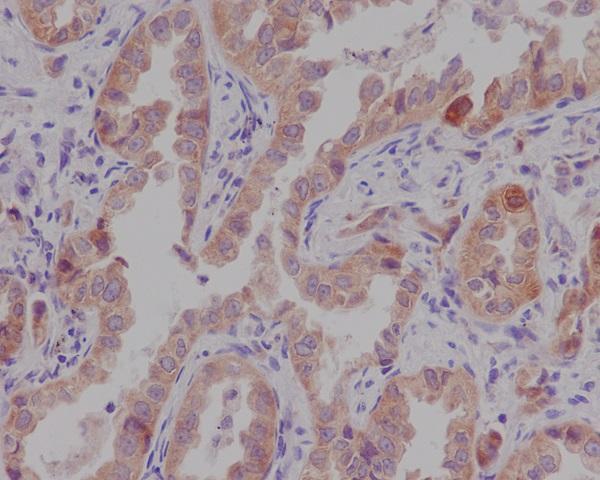
Anti-CTNNA1 IHC images cover paraffin sections of human mammary tissue and cancer, human lung cancer, and mouse and rat intestine (IHC image captions). PB9137 also has cellular IF data (PB9137 IF caption).

Real IHC data IHC analysis of CTNNA1 using anti-CTNNA1 antibody (PB9137). CTNNA1 was detected in paraffin-embedded section of rat intestine tissue. Heat mediated antigen retrieval was performed in citrate buffer (pH6, epitope retrieval solution) for 20 mins. The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml rabbit anti-CTNNA1 Antibody (PB9137) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC)(Catalog # SA1022) with DAB as the chromogen.
Anti-alpha 1 Catenin/CTNNA1 Antibody ®
Cat # PB9137
Real IHC data IHC analysis of CTNNA1 using anti-CTNNA1 antibody (M01617-1). CTNNA1 was detected in paraffin-embedded section of human mammary cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml mouse anti-CTNNA1 Antibody (M01617-1) overnight at 4°C. Biotinylated goat anti-mouse IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1021) with DAB as the chromogen.
Anti-alpha 1 Catenin/CTNNA1 Antibody ® (monoclonal, 10I2)
Cat # M01617-1
Real IHC data Immunohistochemical analysis of paraffin-embedded human lung cancer, using Catenin alpha 1 Antibody.
Anti-Catenin alpha 1 CTNNA1 Rabbit Monoclonal Antibody
Cat # M01617

PB9137 has paraffin-section IHC images from rat and mouse intestine and human mammary tissue, plus an IF image from U20S cells (PB9137 image captions). M01617-1 has a paraffin-section IHC image from human mammary cancer, and M01617 has one from human lung cancer (respective IHC image captions).

Which to pick: For tissue IHC across human, mouse, and rat, choose PB9137: its paraffin-section captions show staining in all three species, but do not report the fixative (PB9137 IHC captions). For human cancer sections, M01617-1 is a mouse monoclonal with a mammary cancer example, while M01617 is a rabbit monoclonal with a lung cancer example; neither caption reports the fixative (catalog host and clone; respective IHC captions). For IF/ICC, choose PB9137 because both applications are listed and its cellular IF image used 2 μg/mL (catalog applications; PB9137 IF caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P35221 (CTNA1_HUMAN, Catenin alpha-1).
  2. Human Protein Atlas. CTNNA1 tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. CTNNA1 subcellular location (ICC-IF): Mainly localized to the plasma membrane and cell junctions. In addition localized to the Golgi apparatus, vesicles, connecting piece, mid piece and principal piece..
  4. Human Protein Atlas. CTNNA1 antibody validation summary (3 antibodies).
  5. Loss-of-function variants in CTNNA1 detected on multigene panel testing in individuals with gastric or breast cancer. Genetics in medicine : official journal of the American College of Medical Genetics 2020 — PMC7200596.
  6. Role of germline aberrations affecting CTNNA1, MAP3K6 and MYD88 in gastric cancer susceptibility. Journal of medical genetics 2018 — PMC6161648.
  7. Exploration and Validation of Key Genes and Immune Infiltration in Alcoholic Hepatitis. Journal of inflammation research 2025 — PMC12206905.
  8. α-E-Catenin (CTNNA1) Inhibits Cell Proliferation, Invasion and EMT of Bladder Cancer. Cancer management and research 2020 — PMC7751797.
  9. PubMed PMID:8404069 — UniProt-cited evidence.
  10. PubMed PMID:8323564 — UniProt-cited evidence.
  11. PubMed PMID:7945318 — UniProt-cited evidence.