This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic DIS3 IHC in paraffin sections using the catalog antibody's 2–5 μg/mL range (datasheet A01736-2). Assess mainly nuclear staining (HPA tissue IHC) and consider high-staining bronchial respiratory epithelium as a positive control (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Mainly nuclear staining in tissue (HPA tissue IHC) | |
| Staining pattern | Widespread, mainly nuclear staining across tissue cells (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet A01736-2) | |
| Positive control | Bronchus+4 more · see all | |
| Negative control | None in HPA (detected in all 45 tissues); use no-primary + isotype controls |
| Fixation | Keep fixation conditions consistent across sections (standard IHC practice; not target-specific) | |
| Caveat | Nucleolar localisation differs between studies (UniProt) | |
| Regulation | Widely expressed (UniProt) | |
| Isoform / epitope | 2 isoforms; epitope effects are unestablished (UniProt) |
The catalog antibody has a datasheet IHC-P protocol (datasheet A01736-2). One published DIS3 IHC protocol uses paraffin sections of rectal adenoma and carcinoma (PMC3533962).
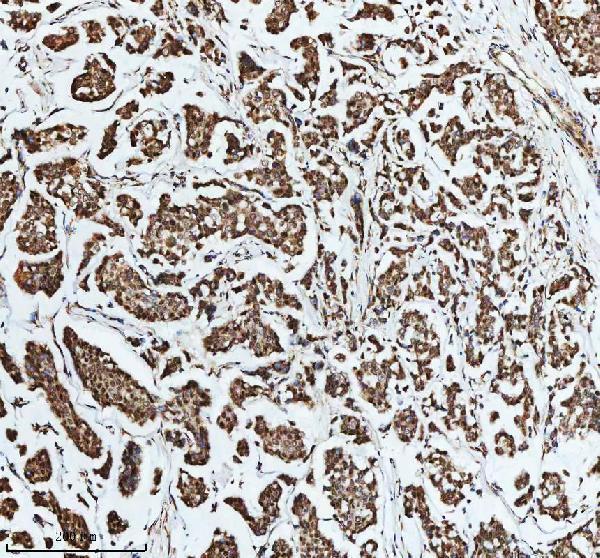
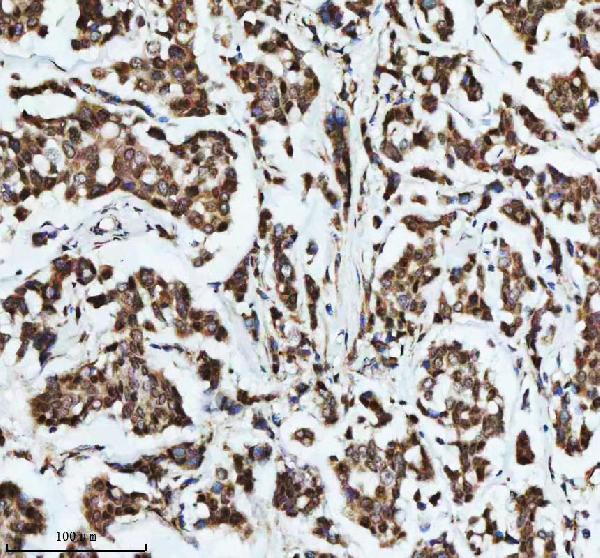
| Sample | Paraffin-embedded human breast cancer tissue; fixative not specified (datasheet A01736-2) |
| Fixation | Image fixative and duration unreported (datasheet A01736-2); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet A01736-2); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet A01736-2) |
| Primary antibody | Rabbit anti-DIS3, 2-5 μg/ml (datasheet A01736-2) |
| Primary incubation | Overnight at 4 °C (datasheet A01736-2) |
| Detection | HRP-conjugated secondary, DAB chromogen (datasheet A01736-2) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | DIS3-positive staining in respiratory epithelial cells of bronchus (HPA tissue IHC: High). HPA tissue profile: Ubiquitous mainly nuclear expression. No signal in the no-primary control. |
DIS3 staining should be mainly nuclear across many cell types, with stronger staining in selected epithelial, glandular, and trophoblastic cells (HPA: ubiquitous mainly nuclear tissue IHC; HPA: listed High cells). Cytosolic signal is also supported by ICC/IF (HPA: supported cytosol). DIS3 has no transmembrane segment, so a membrane rim is not the expected pattern (UniProt Q9Y2L1 topology). HPA rates its tissue IHC profile Approved, with medium consistency against RNA expression data (HPA: tissue IHC reliability).
| Predominantly nuclear staining in respiratory epithelial cells of bronchus or squamous epithelial cells of cervix, with clear cell boundaries. | This matches the reported mainly nuclear tissue pattern and two High cell populations (HPA: tissue IHC profile; HPA: High in bronchus respiratory epithelium and cervix squamous epithelium). Assess the stain in identified cells rather than treating every part of the section as equally informative (general IHC practice). |
| Staining forms a crisp plasma-membrane rim, extracellular deposit, or isolated surface outline while nuclei are unstained. | That distribution conflicts with the mainly nuclear tissue pattern and with DIS3 having no transmembrane segment (HPA: tissue IHC profile; UniProt Q9Y2L1 topology). Review morphology and detection controls before calling it DIS3; the compartment mismatch alone does not identify the source of the stain (general IHC practice). |
| Strong staining appears in a population expected to be low, while a listed High population on the same run is weak or unstained. | For example, HPA reports low staining in lung alveolar cells and High staining in bronchial respiratory epithelial cells (HPA: tissue IHC levels). Misidentified cells, cross-reactivity, or endogenous detection activity are possible explanations; neither tissue is a universal negative or positive control for every specimen (general IHC practice; HPA: no negative tissues listed). |
| Color spreads over stroma, empty spaces, and several compartments without discernible nuclear enrichment. | Diffuse background makes the expected mainly nuclear pattern difficult to score (HPA: tissue IHC profile). Uneven blocking, insufficient washing, or excess detection reagent can produce nonspecific chromogenic signal; inspect a reagent-control section and the slide morphology before interpreting intensity (general IHC practice). |
| A well-preserved bronchus section shows no signal in its respiratory epithelial cells. | Those cells are listed as High, so absent staining warrants a run-level check (HPA: High in bronchus respiratory epithelial cells). Confirm that tissue and nuclei are present, then review retrieval, primary-antibody application, and chromogenic detection using the assay's controls (general IHC practice). One negative section does not establish that DIS3 is absent (HPA: Approved, medium consistency). |
| Tissue and cell selection | DIS3 is widely expressed, while HPA reports different staining levels by cell type (UniProt Q9Y2L1 tissue specificity; HPA: tissue IHC levels). Use a listed High population to judge whether the run can reveal nuclear signal; HPA supplies no negative tissue here (HPA: High cells; HPA: negative list empty). |
| Nucleolar interpretation | UniProt reports both nucleolar localization and a study finding DIS3 excluded from nucleoli (UniProt Q9Y2L1 subcellular notes). HPA supports nucleoplasm as the main ICC/IF location (HPA: subcellular). Do not require nucleolar enrichment to accept a mainly nuclear IHC result (HPA: tissue IHC profile). |
| Isoforms and antibody epitope | UniProt lists two DIS3 isoforms and several domains, but the supplied records do not locate an antibody epitope or show isoform-specific IHC staining (UniProt Q9Y2L1 isoforms and domains; HPA: supplied antibody records). An unexpected pattern cannot be assigned to one isoform from these data. |
| Antibody validation | HPA039281 is Approved for IHC, whereas no IHC status is supplied for HPA058762; both have Enhanced ICC validation (HPA: antibody validation records). The tissue profile itself is Approved with medium consistency, so compare compartment and cell identity alongside intensity (HPA: tissue IHC reliability and profile). |
| Detection chemistry | Endogenous enzyme activity and nonspecific reagent binding can add chromogenic color, independently of DIS3 localization (general IHC practice). Blocking and reagent controls help distinguish these signals from the mainly nuclear tissue pattern (general IHC practice; HPA: tissue IHC profile). No DIS3-specific fixation sensitivity is reported in the supplied sources (UniProt Q9Y2L1; HPA: supplied records). |
| Situation | Likely cause | Next action |
|---|---|---|
| No staining in a listed High cell population. | The section or assay may have failed; absence alone does not establish loss of DIS3 (HPA: High cell levels; general IHC practice). | Check tissue preservation and cell identity, then review retrieval, antibody application, and detection controls for the IHC run (general IHC practice). |
| Strong cytoplasmic color obscures nuclei. | Cytosol is a supported additional ICC/IF location, but tissue IHC is mainly nuclear; excessive background is also possible (HPA: subcellular; HPA: tissue IHC profile; general IHC practice). | Compare nuclear enrichment with morphology and reagent controls before scoring; do not count diffuse color alone as a specific positive (general IHC practice). |
| Only the cell surface or extracellular material stains. | This conflicts with the mainly nuclear profile and absence of a transmembrane segment (HPA: tissue IHC profile; UniProt Q9Y2L1 topology). | Inspect the section for deposits, review control staining, and avoid assigning the surface signal to DIS3 without independent support (general IHC practice). |
| Many cell types stain equally, including a listed low-staining population. | Broad expression is plausible, but HPA reports cell-level differences; excess background or loss of contrast may mask them (UniProt Q9Y2L1 tissue specificity; HPA: tissue IHC levels; general IHC practice). | Score identified cell populations separately and compare their nuclear signal with the run's controls (general IHC practice). |
| Is nucleolar staining required for a positive call? | UniProt's nucleolar reports differ, and HPA supports nucleoplasm as the main ICC/IF location (UniProt Q9Y2L1 subcellular notes; HPA: subcellular). | Use predominant nuclear staining as the IHC criterion; describe nucleolar staining separately if visible (HPA: tissue IHC profile; general IHC practice). |
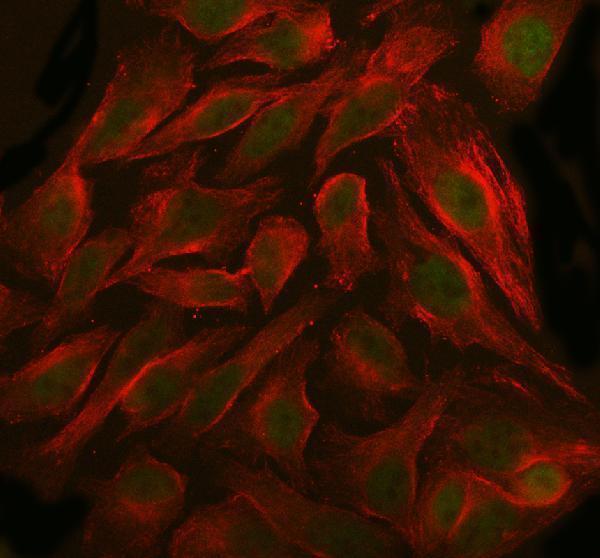
| Can an ICC/IF image settle an uncertain chromogenic IHC result? | HPA supports nucleoplasmic and additional cytosolic ICC/IF localization, while its tissue IHC profile is mainly nuclear (HPA: subcellular; HPA: tissue IHC profile). | Use ICC/IF as compartment context, then assess the IHC section with its own morphology and controls; consult the separate IF/ICC guide for that application (general IHC practice). |

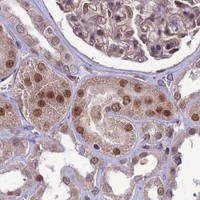


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Bronchus | Respiratory epithelial cells | High | Protein (IHC) | HPA → |
| Cervix | Squamous epithelial cells | High | Protein (IHC) | HPA → |
| Esophagus | Squamous epithelial cells | High | Protein (IHC) | HPA → |
| Gallbladder | Glandular cells | High | Protein (IHC) | HPA → |
| Nasopharynx | Respiratory epithelial cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| None in HPA: DIS3 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead. | ||||
Troubleshoot DIS3 staining in paraffin sections by checking retrieval, nuclear localisation, and matched controls before interpreting differences in signal (datasheet A01736-2; HPA tissue IHC).
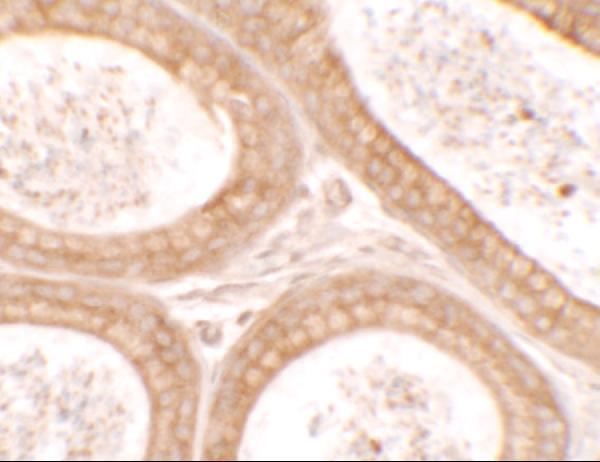
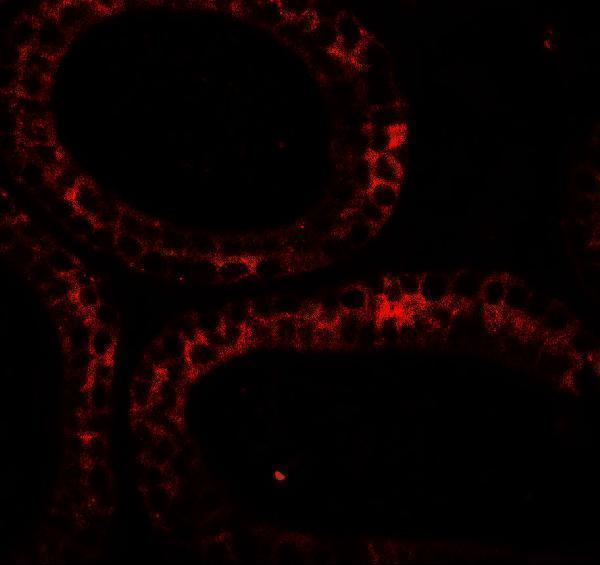
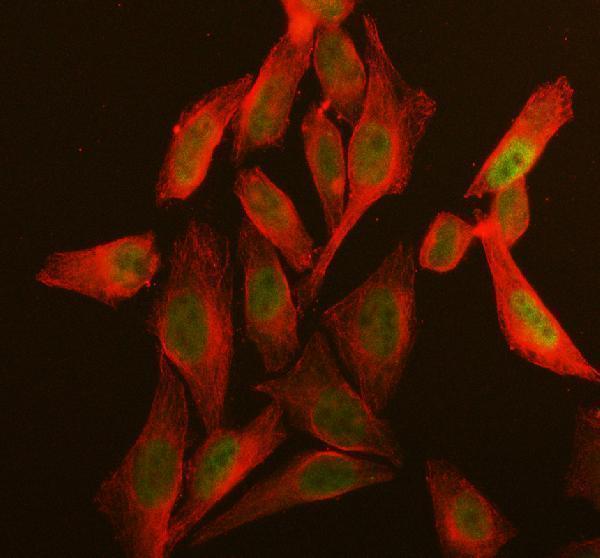
DIS3 IHC images cover paraffin-embedded human breast and colon cancer sections (A01736-2 image captions) and mouse testis (A01736 image caption); IF images include HeLa cells (A01736-1 image caption).
A01736-2 has IHC images from human breast and colon cancer sections and an IF image from HeLa cells (catalog image captions); A01736 has IHC and IF images from mouse testis (catalog image captions). A01736-1 has IF images from HeLa cells and a paraffin-embedded human breast cancer section (catalog image captions).
Which to pick: For tissue IHC, choose A01736-2 for human paraffin sections (A01736-2 IHC captions: breast and colon cancer; datasheet: 2–5 μg/ml) or A01736 for mouse testis (A01736 IHC caption: 2.5 μg/ml); neither IHC caption reports a fixative (catalog IHC captions). For IF/ICC, A01736-1 has a HeLa cell image and lists both applications (A01736-1 IF caption; catalog applications). For cross-species IHC planning, A01736-2 lists human, mouse and rat reactivity, though its own IHC images show human sections (catalog reactivity; A01736-2 IHC captions); clone identity is unreported for all three (catalog clone fields).