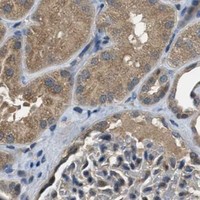
DUSP6 / Dual specificity protein phosphatase 6 · IHC design guide

Design Immunohistochemistry for DUSP6

Plan DUSP6 IHC in paraffin sections around the cytoplasmic pattern reported across most tissues (HPA tissue IHC). This guide pairs the catalog antibody’s IHC-P conditions (datasheet A02157-2) with cell-level staining evidence for selecting controls (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for DUSP6 (IHC for DUSP6): expected localisation Cytoplasmic staining in tissue (HPA tissue IHC), antibody A02157-2, validated IHC image, and IHC protocol steps
Printable DUSP6 IHC protocol sheet — expected localisation Cytoplasmic staining in tissue (HPA tissue IHC), antibody A02157-2, controls and protocol steps. Open the full DUSP6 IHC guide →

DUSP6 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic staining in tissue (HPA tissue IHC)
Staining pattern Cytoplasmic staining across diverse tissue cell types (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A02157-2)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Staining and RNA show medium consistency (HPA tissue IHC)
Regulation Expression regulation unreported (UniProt)
Isoform / epitope 2 isoforms; epitope differences unreported (UniProt)
Section 1

Recommended DUSP6 IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol (datasheet A02157-2) with the published DUSP6 tissue protocol (PMC12420332).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human liver cancer tissue; fixative not specified (datasheet A02157-2)
FixationImage fixative and duration unreported (datasheet A02157-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A02157-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A02157-2)
Primary antibodyRabbit anti-DUSP6, 2-5 μg/ml (datasheet A02157-2)
Primary incubationOvernight at 4 °C (datasheet A02157-2)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A02157-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultDUSP6-positive staining in glandular cells of adrenal gland (HPA tissue IHC: Medium). HPA tissue profile: Cytoplasmic expression in most tissues. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet A02157-2); the published protocol used sodium citrate for 20 min (PMC12420332).
Section 2

What Is the Expected DUSP6 Staining Pattern?

DUSP6 is a cytoplasmic protein without a transmembrane segment (UniProt Q16828: location and topology). In paraffin-section IHC, expect cytoplasmic staining in selected glandular and other listed cells; HPA reports medium staining in several tissues and cytoplasmic expression in most tissues (HPA: tissue IHC). The tissue profile is Approved, with medium consistency between staining and RNA data (HPA: reliability).

What am I looking at on my slide?
Medium cytoplasmic staining in colon or breast glandular cells, with cellular boundaries still discernible.This fits the reported positive cell type and level (HPA: colon and breast glandular cells, Medium) and the expected compartment (UniProt Q16828: Cytoplasm). Compare cells within the same section before assigning a whole-tissue score (standard IHC practice).
Predominantly nuclear staining, with little or no cytoplasmic signal, on a chromogenic section.Treat this as a localisation mismatch requiring control review (UniProt Q16828: Cytoplasm; HPA: tissue IHC cytoplasmic profile). Nuclear signal cannot be dismissed categorically: HPA reports uncertain nucleoplasmic localisation in ICC-IF (HPA: subcellular ICC-IF).
Strong staining in adipocytes or ovarian stromal cells while expected positive cells are weak.These cell types were not detected in the supplied tissue profile (HPA: adipocytes and ovarian stroma, Not detected). Suspect nonspecific binding or endogenous detection activity; check control sections before attributing the signal to DUSP6 (standard IHC practice).
Uniform brown haze across cells and extracellular areas, obscuring cytoplasmic boundaries.A noncellular haze does not match the reported cytoplasmic tissue pattern (HPA: tissue IHC). Review the negative control, blocking and chromogen development to distinguish background from cellular signal (standard chromogenic IHC practice).
No signal in colon glandular cells on an otherwise interpretable section.Colon glandular cells provide a listed medium-staining comparison, although expression can vary across specimens (HPA: colon glandular cells, Medium; HPA: Approved, medium consistency). Check the control run and staining workflow before calling this specimen DUSP6-negative (standard IHC practice).
💡Expected DUSP6 appearanceA convincing positive is discernible medium cytoplasmic staining in a listed cell population, such as colon glandular cells (HPA: colon, Medium; UniProt Q16828: Cytoplasm); diffuse haze or staining confined to unexpected cells warrants control review (standard IHC practice).
How each factor affects the staining
Which cells provide comparisons?Listed medium positives include colon and breast glandular cells, bronchial respiratory epithelial cells and cortical glial cells; adipocytes and ovarian stromal cells are listed as not detected (HPA: tissue IHC). Score the named cell type, since a tissue-wide label can hide mixed populations (standard IHC practice).
How strong is the tissue evidence?The tissue profile is Approved, with medium consistency between antibody staining and RNA expression (HPA: reliability). The listed IHC antibody CAB017566 is Approved; the supplied record does not designate its IHC validation as Enhanced (HPA: antibody validation).
Does protein architecture predict a membrane pattern?No transmembrane segment or signal peptide is annotated, and the chain spans residues 1–381 (UniProt Q16828: topology and processing). A crisp membrane-only pattern therefore needs scrutiny against the cytoplasmic reference pattern (UniProt Q16828: Cytoplasm; HPA: tissue IHC).
Do isoforms or processing change interpretation?UniProt lists 2 isoforms and no propeptide, glycosylation sites or annotated modified residues (UniProt Q16828: isoforms, processing and PTMs). The supplied sources do not map the IHC antibody epitope, so they cannot establish isoform-specific staining or retrieval requirements.
Is antigen retrieval prescribed here?No target-specific retrieval or fixation-sensitivity evidence is supplied by UniProt or HPA (UniProt Q16828; HPA: tissue IHC). If signal is weak, evaluate the established paraffin-section retrieval workflow against a listed positive tissue and controls (standard IHC practice).
IF/ICC Q: should the pattern match IHC exactly?HPA reports supported cytosolic and uncertain nucleoplasmic localisation in ICC-IF, with images from CACO-2, PC-3, U2OS and SK-MEL-30 (HPA: subcellular ICC-IF). Use the separate IF/ICC guide for that application; these observations do not establish a chromogenic IHC nuclear-positive criterion.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No cytoplasmic stain in a listed medium-positive tissue.The run may have failed, or the sampled cell population may differ from the reported positive population (HPA: tissue IHC; standard IHC practice).Verify the named cells, check a concurrent positive control, then review retrieval, antibody dilution and detection records (standard IHC practice). Do not infer DUSP6-specific fixation sensitivity from this result.
Only nuclei stain.A nuclear-only IHC pattern conflicts with the tissue cytoplasmic profile, although ICC-IF nucleoplasmic localisation is uncertain (HPA: tissue IHC; HPA: subcellular ICC-IF).Compare the same run with a listed cytoplasmic-positive cell type and a negative control; inspect counterstain and chromogen separately (standard IHC practice).
Adipocytes or ovarian stromal cells stain prominently.Those cells are listed as not detected, making nonspecific signal or endogenous detection activity plausible (HPA: tissue IHC; standard IHC practice).Inspect no-primary and detection controls, then review blocking and detection conditions (standard IHC practice). Interpret any residual signal cautiously against the HPA cell-specific profile.
Brown signal covers empty spaces and multiple unrelated cell types.Diffuse deposition or background can obscure a cellular pattern (standard chromogenic IHC practice); HPA describes cytoplasmic tissue staining (HPA: tissue IHC).Check negative controls and reagent development, reduce excessive chromogen development if documented, and rescore only clearly cellular staining (standard IHC practice).
A low-staining comparison tissue appears negative.Cerebellar granular-layer cells, hippocampal glia and thyroid glandular cells are listed as Low, so a faint signal can be difficult to distinguish from background (HPA: tissue IHC).Use a listed Medium cell population for the run control and document the scored cell type; avoid treating a Low comparison alone as proof of assay failure (HPA: tissue IHC; standard IHC practice).
Two sections give different proportions of positive cells.The HPA profile names specific cell populations and has medium staining-to-RNA consistency; specimen composition can affect a section-level impression (HPA: tissue IHC reliability; standard IHC practice).Compare like cell populations at similar development and counterstain settings, recording intensity and the fraction of positive cells separately (standard IHC scoring practice).

Sample controls for DUSP6 IHC & IF

🧪Run appendix first and score staining in its glandular cells, where DUSP6 is reported at Medium level (HPA: appendix, glandular cells, Medium). Use adipose tissue adipocytes as the negative comparison (HPA: adipose tissue, adipocytes, Not detected); on the appendix slide, use morphologically distinct cells that remain unstained as an internal background reference without assuming they lack DUSP6.
Positive control tissue: Adrenal gland (Glandular cells, HPA Medium)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show DUSP6 in CACO-2, PC-3, U2OS, SK-MEL-30, with annotated localisation: Nucleoplasm (uncertain), Cytosol (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control, a host-matched rabbit IgG control, and, if available, DUSP6 knockout material processed alongside the test section (selected-SKU tissue-IHC caption: rabbit primary; standard IHC control practice). Quench endogenous peroxidase and check endogenous biotin background when using the caption’s biotin-based DAB detection in appendix, particularly around any inflammatory cells (selected-SKU tissue-IHC caption: biotinylated secondary, SABC and DAB; standard IHC practice).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported, and the exact A02157-2 paraffin-section caption does not state a fixative (selected-SKU tissue-IHC caption). That caption uses heat retrieval in EDTA at pH 8.0, but does not establish that retrieval is required for DUSP6 staining (selected-SKU tissue-IHC caption). The supplied evidence does not show that frozen sections or IF are easier than paraffin IHC; in appendix, assess any peroxidase background from inflammatory cells before scoring DAB signal (HPA: appendix glandular cells, Medium; standard IHC practice).

HPA tissue IHC evidence for DUSP6

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells Medium Protein (IHC) HPA →
Appendix Glandular cells Medium Protein (IHC) HPA →
Bone marrow Hematopoietic cells Medium Protein (IHC) HPA →
Breast Glandular cells Medium Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Cervix Squamous epithelial cells Not detected Protein (IHC) HPA →
Esophagus Squamous epithelial cells Not detected Protein (IHC) HPA →
Ovary Ovarian stroma cells Not detected Protein (IHC) HPA →
Vagina Squamous epithelial cells Not detected Protein (IHC) HPA →
Section 3

Advanced DUSP6 IHC Tips

Use the documented paraffin section workflow as the starting point, then judge staining by compartment, cell type, and matched controls.

What retrieval should I use when DUSP6 staining is weak in paraffin sections?
Start with heat mediated retrieval in EDTA at pH 8.0 for paraffin sections (datasheet A02157-2). The selected human liver cancer image used this retrieval before 2 μg/ml primary antibody overnight at 4°C, so reproduce those conditions when benchmarking weak staining (caption A02157-2). If signal remains low, check deparaffinisation and heating uniformity, then compare retrieval times while holding section thickness, detection chemistry, and DAB development constant (standard IHC practice). Try another buffer only as a fallback after the documented condition fails, and process a positive control alongside each test section (standard IHC practice; HPA: medium staining in colon glandular cells).
Can I infer the best fixation conditions for DUSP6 from the tissue image?
The selected image documents a paraffin embedded section, but its fixative and fixation duration are unreported; target specific fixation sensitivity is therefore unknown (caption A02157-2). Record the fixative, duration, tissue thickness, and processing schedule for each specimen, and compare sections prepared consistently before attributing signal differences to DUSP6 (standard IHC practice). For an initial assay check, retain the documented EDTA retrieval at pH 8.0 and 2 μg/ml primary antibody overnight at 4°C (caption A02157-2). Assess preserved morphology and a matched positive control, then investigate fixation experimentally if otherwise comparable sections disagree (standard IHC practice).
Should DUSP6 staining be cytoplasmic or nuclear in tissue sections?
Score cytoplasmic staining as the primary expected pattern: DUSP6 is cytoplasmic in UniProt, and the tissue atlas describes cytoplasmic expression in most tissues (UniProt Q16828: subcellular location; HPA: tissue profile). Cytosol has supported cell imaging evidence, whereas nucleoplasm is marked uncertain, so isolated nuclear DAB should prompt review rather than automatic assignment to DUSP6 (HPA: subcellular location). Check whether staining follows intact cell outlines and agrees with morphology; compare glandular cells in colon, reported at medium staining, with adipocytes, reported as undetected (HPA: tissue IHC). Keep nuclear counterstain and DAB development consistent across sections before comparing compartment patterns (standard IHC practice).
How should unknown epitope coverage affect interpretation of DUSP6 IHC?
DUSP6 has 2 listed isoforms, but the supplied antibody caption does not identify its epitope or establish equal recognition of both (UniProt Q16828: isoforms; caption A02157-2). The protein contains a rhodanese domain at residues 30–148 and a phosphatase domain at 206–349; domain annotation alone cannot locate this antibody’s binding site (UniProt Q16828: domains). It has no transmembrane segment or signal peptide, supporting a cytoplasmic staining expectation without resolving epitope accessibility after processing (UniProt Q16828: topology and processing). If specimens disagree, compare the same retrieval and antibody conditions across matched sections and seek documented epitope information before making isoform claims (standard IHC practice).
How can IF help assess a puzzling DUSP6 IHC pattern?
Use IF as a separate check of cell identity and compartment, multiplexing DUSP6 with a marker for the cell type expected in the specimen, such as a glandular epithelial marker when assessing glandular staining (HPA: glandular cell staining in colon; standard IF practice). Choose a spectrally separated, preferably far red fluorophore where tissue autofluorescence is strong, and inspect single channel controls before judging overlap (standard IF practice). Because DUSP6 is cytoplasmic and lacks a transmembrane segment, test gentle permeabilisation for access to intracellular epitopes rather than assuming surface staining (UniProt Q16828: location and topology; standard IF practice). Interpret any nuclear IF cautiously because supported cytosolic and uncertain nucleoplasmic locations are reported (HPA: subcellular location).
What should I check when DUSP6 DAB staining is diffuse or patchy?
Start by comparing a no primary control with the test section to separate detection system background from antibody dependent staining (standard IHC practice). The documented workflow used 10% goat serum, biotinylated secondary antibody, a streptavidin biotin complex, and DAB; reproduce its blocking and detection sequence before changing several variables together (caption A02157-2). Include an endogenous peroxidase block and consider endogenous biotin where the biotin based system produces signal in controls (standard chromogenic IHC practice). If controls are clean but tissue staining remains diffuse, check deparaffinisation, washing, antibody concentration, and DAB development against a matched positive section (standard IHC practice).
How should I quantify DUSP6 staining across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the region and eligible cell population before scoring, then record the percentage of cells with cytoplasmic DAB and staining intensity in each region (standard IHC practice; UniProt Q16828: cytoplasmic location). An H-score combines the percentages at weak, moderate, and strong intensity using weights 1, 2, and 3, producing a 0–300 range (standard IHC practice). For sparse populations, report positive cells per mm² of viable tissue as well, and normalise comparisons to the same cell type, sampled area, section conditions, and batch controls (standard IHC practice). Exclude necrosis and section edges from the scoring region and report how they were handled (standard IHC practice).
How do I distinguish convincing DUSP6 staining from tissue artefact?
A convincing result should recur in intact cells with predominantly cytoplasmic signal, consistent with the documented tissue profile and supported cytosolic localisation (HPA: tissue profile and subcellular location). Check cell identity against the specimen: glandular colon cells show medium staining, whereas adipocytes are reported as undetected, but the tissue atlas rates staining and RNA agreement as medium consistency (HPA: tissue IHC reliability and cell profiles). Reject apparent enrichment confined to section edges, folds, or necrotic areas, and investigate DAB in a no primary control as possible endogenous enzyme or detection background (standard IHC practice). Treat unexpected nuclear only or cell type discordant staining as provisional until matched controls and morphology support it (HPA: uncertain nucleoplasm; standard IHC practice).
Boster reagents

Best DUSP6 / Dual specificity protein phosphatase 6 IHC Antibodies

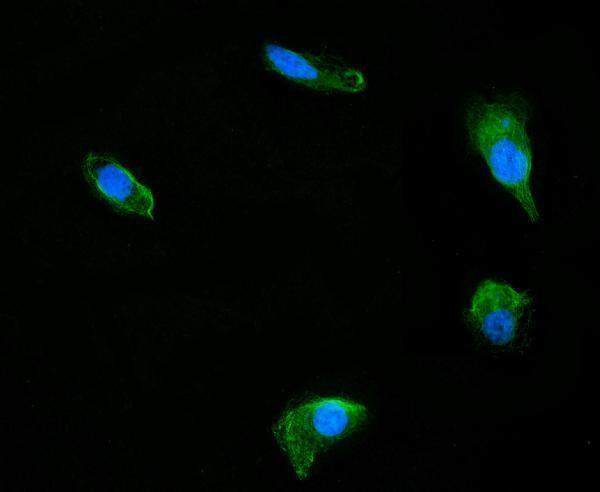
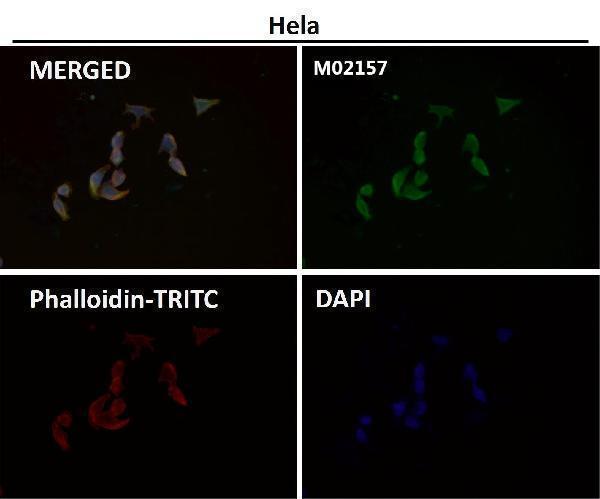
Anti-DUSP6 antibodies have IHC images from human paraffin-embedded tissue and an IF/ICC image from PC-3 cells (catalog image captions); both list human, mouse and rat reactivity (catalog applications and reactivity).

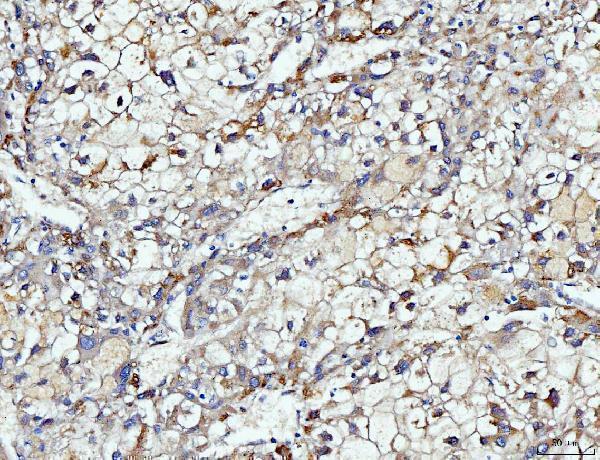
Real IHC data IHC analysis of DUSP6 using anti-DUSP6 antibody (A02157-2). DUSP6 was detected in a paraffin-embedded section of human liver cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-DUSP6 Antibody (A02157-2) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-DUSP6 Antibody ®
Cat # A02157-2
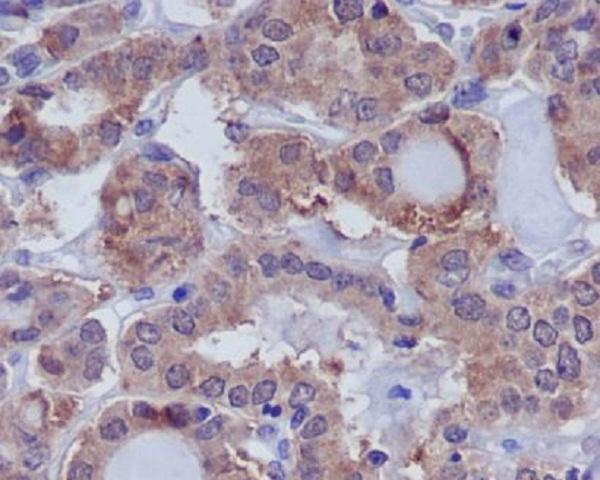
Real IHC data Immunohistochemical analysis of paraffin-embedded human thyroid, using DUSP6 Antibody.
Anti-DUSP6/Mkp 3 Rabbit Monoclonal Antibody
Cat # M02157

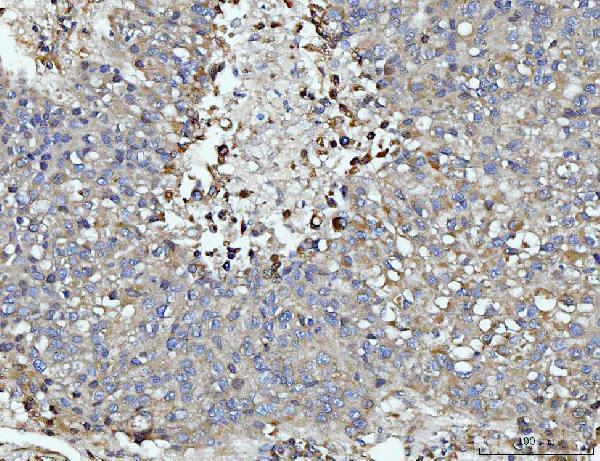
A02157-2 has IHC images from human liver cancer, colonic adenocarcinoma and rectal cancer paraffin sections, plus an IF/ICC image from PC-3 cells (A02157-2 image captions). M02157 lists IHC and IF/ICC applications and has an IHC image from a human thyroid paraffin section (M02157 catalog applications and image caption).

Which to pick: For tissue IHC, choose A02157-2 when its documented EDTA retrieval and 2 μg/ml staining conditions are useful; M02157 offers a rabbit monoclonal, clone DBE-4, with a human thyroid paraffin-section image (A02157-2 IHC image caption; M02157 catalog and IHC image caption). For IF/ICC, A02157-2 has a documented PC-3 cell image at 5 μg/ml, while M02157 lists IF/ICC and has IF images without a reported sample type (A02157-2 IF image caption; M02157 catalog and IF image captions). For work across species, both list human, mouse and rat reactivity; their IHC captions document paraffin sections but do not report the fixative (catalog reactivity; A02157-2 and M02157 IHC image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q16828 (DUS6_HUMAN, Dual specificity protein phosphatase 6).
  2. Human Protein Atlas. DUSP6 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. DUSP6 subcellular location (ICC-IF): Localized to the nucleoplasm and cytosol..
  4. Human Protein Atlas. DUSP6 antibody validation summary (3 antibodies).
  5. Sleeve Gastrectomy Ameliorates Diabetes-Induced Cardiac Hypertrophy Correlates With the MAPK Signaling Pathway. Frontiers in physiology 2021 — PMC8631968.
  6. Inhibition of DUSP6 sensitizes ovarian cancer cells to chemotherapeutic agents via regulation of ERK signaling response genes. Oncotarget 2019 — PMC6534361.
  7. A novel prognostic biomarker DUSP6 promote the malignant progression of bladder cancer through mTOR mediated mitophagy. Frontiers in oncology 2025 — PMC12420332.
  8. Upregulation of cGMP-dependent Protein Kinase (PRKG1) in the Development of Adolescent Idiopathic Scoliosis. Orthopaedic surgery 2020 — PMC7454216.
  9. PubMed PMID:8670865 — UniProt-cited evidence.
  10. PubMed PMID:9858808 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.