EEF2 / Elongation factor 2 · IHC design guide

Design Immunohistochemistry for EEF2

Plan chromogenic EEF2 IHC in paraffin sections using an IHC-validated antibody (datasheet A00830-2). Compare staining with the cytoplasmic and membranous tissue pattern, using high-staining glandular cells as a reference (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for EEF2 (IHC for EEF2): expected localisation Cytoplasmic and membranous staining in most tissues (HPA tissue IHC), antibody A00830-2, validated IHC image, and IHC protocol steps
Printable EEF2 IHC protocol sheet — expected localisation Cytoplasmic and membranous staining in most tissues (HPA tissue IHC), antibody A00830-2, controls and protocol steps. Open the full EEF2 IHC guide →

EEF2 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic and membranous staining in most tissues (HPA tissue IHC)
Staining pattern Glandular cells show cytoplasmic and membranous staining (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A00830-2)
Positive control ⓘ Appendix+4 more · see all
Negative control ⓘ None in HPA (detected in all 45 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep formalin fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Smooth muscle cells, fibroblasts and adipocytes stain weakly (HPA tissue IHC)
Regulation Tissue-specific expression regulation is unreported (UniProt)
Isoform / epitope 0 annotated isoforms; cleavage may affect epitope coverage (UniProt)
Section 1

Recommended EEF2 IHC & IF Protocols

The catalog antibody’s IHC-P protocol is paired with three published paraffin-section protocols for total or phospho-eEF2 staining (PMC4027928; PMC7956131; PMC5613342).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human breast cancer tissue; fixative not specified (datasheet A00830-2)
FixationImage fixative and duration unreported (datasheet A00830-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A00830-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A00830-2)
Primary antibodyRabbit anti-EEF2, 2μg/ml (datasheet A00830-2)
Primary incubationOvernight at 4 °C (datasheet A00830-2)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A00830-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultEEF2-positive staining in glandular cells of appendix (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic and membranous expression in most tissues. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet A00830-2); the published phospho-eEF2 protocol also reports citrate pH 6.0 retrieval (PMC7956131).
Section 2

What Is the Expected EEF2 Staining Pattern?

In paraffin sections, expect EEF2 staining mainly in the cytoplasm of many cell types, with membranous staining also reported (HPA: tissue IHC profile). Strong examples include appendix glandular cells, bone marrow hematopoietic cells, and bronchial respiratory epithelial cells (HPA: High). HPA rates the tissue IHC evidence Enhanced, with medium consistency between staining and RNA data (HPA: reliability). EEF2 has no transmembrane segment (UniProt P13639: topology).

What am I looking at on my slide?
Cytoplasmic staining across several cell types, including strong appendix glands or bone marrow cells.This fits the broad tissue profile (HPA: cytoplasmic and membranous expression in most tissues). Appendix glandular and bone marrow hematopoietic cells are each rated High (HPA: tissue IHC). Compare cell types within the section; uniform intensity is not required by that profile.
Predominantly nuclear staining with little cytoplasmic signal.Recheck staining specificity and nuclear counterstain interpretation because this differs from the reported tissue IHC profile (HPA: cytoplasmic and membranous). Do not call every nuclear signal an artefact: UniProt also lists the nucleus and describes nuclear translocation of a modified C-terminal cleavage product (UniProt P13639: subcellular location).
A strong signal appears chiefly in adipocytes, fibroblasts, or smooth muscle cells.These are listed as Low, so a dominant strong signal deserves a specificity check (HPA: adipocytes, fibroblasts, smooth muscle cells Low). Compare an HPA High cell population and a no-primary control; unexpected color can reflect cross-reactivity or endogenous detection activity (general IHC practice). Low does not mean absent.
Color spreads across cell-free areas or obscures cell boundaries.Treat the diffuse deposit as background until controls establish otherwise (general IHC practice). It cannot be assigned to EEF2 from the tissue profile alone (HPA: cellular cytoplasmic and membranous profile). Inspect the no-primary control and review blocking, washes, and detection conditions (general IHC practice).
No convincing staining in appendix glandular cells or bronchial respiratory epithelium.These are useful expected-positive checks because both are rated High (HPA: tissue IHC). An absent signal calls for review of the antibody's IHC-P instructions, retrieval, antibody dilution, and detection controls (general IHC practice). The supplied sources establish no EEF2-specific retrieval requirement or fixation sensitivity.
💡Expected EEF2 appearanceA credible positive shows cytoplasmic, sometimes membranous, staining in multiple cell types with strong signal possible in appendix glands and bronchial respiratory epithelium (HPA: tissue IHC, High); isolated strong signal in HPA Low cells or diffuse cell-free color warrants investigation (HPA: Low; general IHC practice).
How each factor affects the staining
Subcellular locationThe broad tissue IHC description includes cytoplasmic and membranous expression (HPA: tissue IHC). EEF2 lacks a transmembrane segment, so a membrane-associated appearance does not establish membrane insertion (UniProt P13639: topology). Assess the pattern alongside cytoplasmic staining.
Choice of comparison cellsAppendix and breast glandular cells, bone marrow hematopoietic cells, and cervical squamous cells are rated High (HPA: tissue IHC). Endometrial stromal cells are Medium, while adipocytes, fibroblasts, and smooth muscle cells are Low (HPA: tissue IHC). These levels guide comparison; they are not absolute cutoffs.
Strength of tissue evidenceHPA labels the tissue IHC reliability Enhanced but describes only medium consistency between antibody staining and RNA expression (HPA: reliability). Its antibody entries list two rabbit polyclonals as IHC Enhanced and one as IHC Approved (HPA: antibody validation). Match any cited validation to the antibody actually used.
Modified or cleaved EEF2UniProt records phosphorylation and other modified residues, plus nuclear translocation of a SUMOylated C-terminal cleavage product (UniProt P13639: modifications and subcellular location). The supplied sources do not locate the catalog antibody's epitope, so they cannot predict whether it detects particular modified or cleaved forms.
Antigen retrievalFollow the IHC-validated antibody's own retrieval instructions and assess controls when optimizing a paraffin-section workflow (general IHC practice). No EEF2-specific retrieval condition or fixation effect is established by the supplied HPA tissue observations or UniProt record.
IF/ICC Q: What location should fluorescence show?A: Cytosolic signal is supported; the reported plasma-membrane location is uncertain (HPA: ICC-IF subcellular). UniProt also lists the nucleus under the stated cleavage and translocation condition (UniProt P13639: subcellular location). Use the separate IF/ICC guide for its workflow.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Expected-positive cells are unstained.The run may have insufficient antibody or detection signal (general IHC practice); appendix glandular cells are High (HPA: tissue IHC).Check the run's positive and reagent controls, then review the IHC-validated antibody's stated dilution and retrieval instructions (general IHC practice). No EEF2-specific retrieval condition is supplied.
The section is uniformly dark.Excess antibody or detection signal, inadequate washing, or endogenous detection activity can obscure cell-level localization (general IHC practice).Compare the no-primary control, review blocking and wash steps, and adjust detection or antibody concentration according to the assay instructions (general IHC practice). Reassess whether cytoplasmic cell detail is visible (HPA: tissue IHC profile).
Strong color occurs mainly in an HPA Low cell population.A dominant signal in adipocytes, fibroblasts, or smooth muscle cells conflicts with their Low ratings (HPA: tissue IHC). Cross-reactivity or endogenous detection activity is possible (general IHC practice).Check a no-primary control and compare a High cell population in the same run (general IHC practice; HPA: tissue IHC levels). Do not interpret Low as a required negative result.
Only nuclear staining is visible.This differs from the usual tissue IHC profile (HPA: cytoplasmic and membranous), although UniProt describes conditional nuclear translocation of a cleavage product (UniProt P13639: subcellular location).Verify counterstain and detection controls, and check the antibody's documented target recognition (general IHC practice). Keep the nuclear result provisional because the supplied sources do not establish which EEF2 forms this antibody detects.
Membrane staining dominates without clear cytoplasmic staining.Membranous expression is reported in tissue IHC, but HPA marks plasma-membrane localization uncertain in ICC-IF (HPA: tissue IHC and subcellular).Compare cellular boundaries and cytoplasm against counterstain and controls (general IHC practice). Report the observed distribution without inferring membrane insertion; EEF2 has no transmembrane segment (UniProt P13639: topology).
The catalog antibody's staining differs from an HPA example.HPA validation belongs to its listed antibodies and the tissue profile has medium staining-to-RNA consistency (HPA: antibody validation and reliability).Confirm the catalog antibody's IHC-P validation and follow its instructions, then compare a documented High cell type and assay controls (general IHC practice; HPA: tissue IHC). Do not transfer an HPA antibody's validation status to another antibody.

Sample controls for EEF2 IHC & IF

🧪Start with breast tissue and confirm staining in glandular cells (HPA: High in breast glandular cells). HPA detects EEF2 in all 45 scored tissues, so there is no HPA negative tissue; use no-primary and isotype controls, and treat cells without visible staining on the positive slide as unvalidated internal negatives (HPA: no negative tissue rows).
Positive control tissue: Appendix (Glandular cells, HPA High)
Negative control tissue: None in HPA: EEF2 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show EEF2 in HEK293, U-251MG, U2OS, NIH 3T3, with annotated localisation: Plasma membrane (uncertain), Cytosol (supported) (HPA subcellular).
Technical controls: Run a secondary-only slide, a concentration-matched rabbit IgG isotype control matched to the primary antibody’s clonality where known, and an EEF2 knockout specimen as a biological negative (selected-SKU IHC caption: rabbit primary and biotinylated goat anti-rabbit secondary). With the caption’s biotin-based DAB detection, control endogenous peroxidase and assess endogenous biotin in the positive tissue (selected-SKU IHC caption: SABC with DAB).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported, and the exact selected-SKU tissue-IHC caption does not state a fixative (selected-SKU IHC caption: fixative unreported). The demonstrated paraffin-section workflow uses heat retrieval in EDTA at pH 8.0; the supplied evidence does not establish whether frozen sections or IF are easier (selected-SKU IHC caption: EDTA retrieval; HPA: ICC-IF images available). Assess endogenous biotin in breast sections because the demonstrated detection uses SABC, and interpret any unstained cells cautiously because HPA provides no negative tissue for EEF2 (selected-SKU IHC caption: SABC; HPA: no negative tissue rows).

HPA tissue IHC evidence for EEF2

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Appendix Glandular cells High Protein (IHC) HPA →
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Breast Glandular cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →
Cerebral cortex Glial cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: EEF2 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced EEF2 IHC Tips

Troubleshoot EEF2 staining in paraffin section IHC by checking retrieval, compartment, controls and scoring against the evidence for the selected antibody.

What retrieval should I start with if EEF2 staining is weak?
Start with heat-mediated antigen retrieval in EDTA pH 8.0 (datasheet A00830-2). The selected antibody produced staining in a paraffin-embedded human breast cancer section after that retrieval, followed by 2 µg/mL primary antibody overnight at 4°C (datasheet A00830-2). If staining remains weak, check section adhesion, heating consistency and primary incubation before testing another buffer as a fallback (standard IHC practice). Compare any retrieval change on serial sections with the same detection and counterstain, because stronger overall DAB can also reflect increased background (standard IHC practice). The caption does not state a fixative, so it cannot establish retrieval performance across fixation methods (datasheet A00830-2).
Could fixation explain variable EEF2 staining between paraffin sections?
Target-specific EEF2 sensitivity to fixation is unknown from the supplied evidence; the selected paraffin-section caption does not state a fixative (datasheet A00830-2). Record fixative, fixation duration, tissue thickness and processing history for each specimen before comparing staining intensity (standard IHC practice). If those conditions vary, stain comparable sections in the same run with the same EDTA pH 8.0 retrieval and 2 µg/mL primary concentration used in the selected example (datasheet A00830-2). Include a section with an expected EEF2-positive cell population to detect run failure (HPA: high staining in breast glandular cells; standard IHC practice). Do not assign a fixation mechanism to an intensity difference without matched-condition evidence (standard IHC practice).
How should cytoplasmic, membranous or nuclear EEF2 staining be assessed?
Expect predominantly cytoplasmic staining in tissue sections, while treating a membrane outline cautiously: HPA reports cytoplasmic and membranous tissue expression, but its cytosol localisation is supported and plasma-membrane localisation is uncertain (HPA tissue IHC; HPA subcellular). EEF2 has no transmembrane segment, so a crisp isolated membrane rim deserves comparison with background controls and cytoplasmic signal (UniProt P13639 topology; standard IHC practice). Nuclear staining is biologically possible because CSK-dependent processing can promote nuclear translocation of a C-terminal cleavage product (UniProt P13639 subcellular annotation). Score nuclear and cytoplasmic compartments separately, using identical exposure and DAB development across sections (standard IHC practice). Do not interpret compartment shifts from a single damaged or poorly preserved area (standard IHC practice).
Can epitope choice distinguish full-length EEF2 from a nuclear cleavage product?
The supplied record lists 0 isoforms, so an isoform-specific interpretation is unsupported here (UniProt P13639). It does report phosphorylation at Thr54, Thr57 and Thr59 and a possible C-terminal cleavage product that translocates to the nucleus after CSK-dependent processing (UniProt P13639 modified residues and subcellular annotation). The selected caption identifies the antibody and its 2 µg/mL staining condition but does not map its epitope (datasheet A00830-2). Check documented epitope coverage before claiming that nuclear DAB represents that product, and use an independently validated epitope or orthogonal assay if the distinction matters (standard IHC practice). Keep compartment scores descriptive until that evidence is available (standard IHC practice).
How can IF help check an ambiguous EEF2 IHC pattern?
Use IF as a separate localisation check, while keeping the paraffin-section chromogenic result as this guide’s primary readout (datasheet A00830-2). Multiplex EEF2 with a validated marker for the cell population under study; for example, breast glandular cells are reported as high for EEF2 in tissue IHC (HPA tissue IHC; standard IF practice). Select a fluorophore channel with low measured tissue autofluorescence, and include single-label and no-primary controls to assess bleed-through and background (standard IF practice). Choose permeabilisation according to the antibody’s documented epitope accessibility: cytosolic EEF2 generally requires intracellular access, whereas a claimed surface epitope needs separate validation (HPA subcellular; standard IF practice). The paraffin-section caption supplies no IF fixation or permeabilisation validation (datasheet A00830-2).
What should I check when EEF2 DAB staining is diffuse or patchy?
First compare a no-primary control and an expected-positive section stained in the same run; widespread DAB in the control points to detection background (standard IHC practice). The selected example used 10% goat-serum blocking, a biotinylated secondary and streptavidin–biotin detection with DAB (datasheet A00830-2). Check peroxidase blocking and, for that detection system, endogenous biotin or nonspecific secondary binding when control sections stain (standard IHC practice). EEF2 is broadly expressed in tissue IHC, so diffuse cellular staining alone does not establish artefact (HPA tissue IHC). Review whether signal follows intact cells instead of section edges, folds or necrotic regions before changing primary concentration (standard IHC practice).
How should I quantify EEF2 IHC across heterogeneous tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring; HPA reports high staining in several cell populations and low staining in smooth muscle cells, fibroblasts and adipocytes (HPA tissue IHC). For cellular DAB, record the percentage of positive cells and an H-score using intensity categories 0–3, yielding 0–300 when each category is multiplied by its percentage (standard IHC practice). If counting discrete positive cells, report density per mm² of viable annotated tissue (standard IHC practice). Normalise comparisons to the same cell type, viable area, staining run and scoring thresholds rather than whole-section area alone (standard IHC practice). Report cytoplasmic and nuclear scores separately when both occur (UniProt P13639 subcellular annotation; standard IHC practice).
How can I distinguish genuine EEF2 signal from IHC artefact?
A credible positive follows intact cells in the expected compartment and recurs across comparable areas: cytosolic localisation is supported, and breast glandular cells show high tissue staining (HPA subcellular; HPA tissue IHC). Treat a membrane-only rim cautiously because plasma-membrane localisation is uncertain and EEF2 lacks a transmembrane segment (HPA subcellular; UniProt P13639 topology). Nuclear staining needs separate assessment because a C-terminal cleavage product can translocate there, but the selected antibody’s epitope is unspecified (UniProt P13639 subcellular annotation; datasheet A00830-2). Exclude section edges, folds and necrosis, and inspect a no-primary control for endogenous peroxidase or detection-system signal (standard IHC practice). Interpret an unexpected cell population only after checking morphology, controls and reproducibility across sections (standard IHC practice).
Boster reagents

Best EEF2 / Elongation factor 2 IHC Antibodies

Anti-EEF2 antibodies have paraffin-section IHC images from human cancers and rat ovary, plus IF images from human cells (catalog image captions).

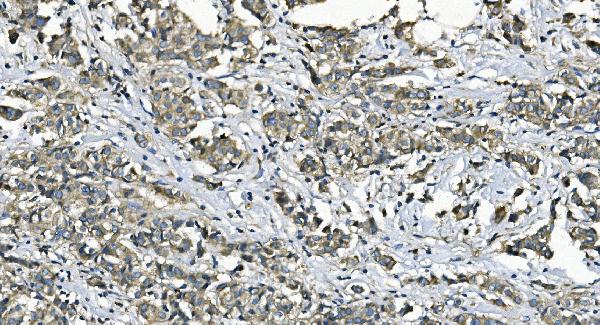
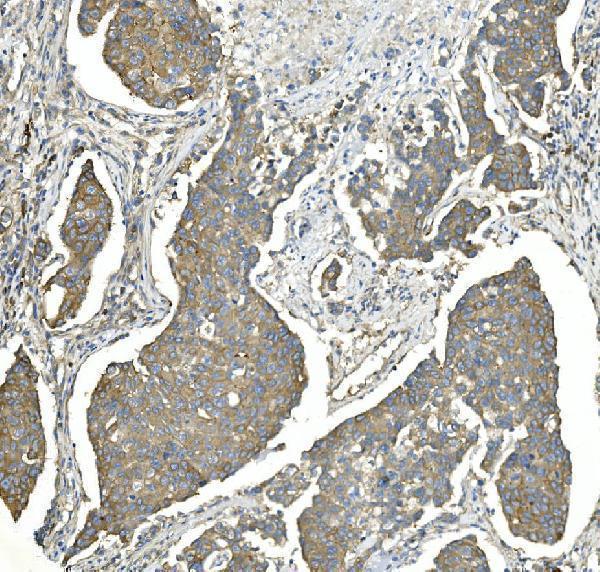
Real IHC data IHC analysis of EEF2/Elongation factor 2 using anti-EEF2/Elongation factor 2 antibody (A00830-2). EEF2/Elongation factor 2 was detected in paraffin-embedded section of human breast cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2μg/ml rabbit anti-EEF2/Elongation factor 2 Antibody (A00830-2) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-EEF2/Elongation factor 2 Antibody ®
Cat # A00830-2
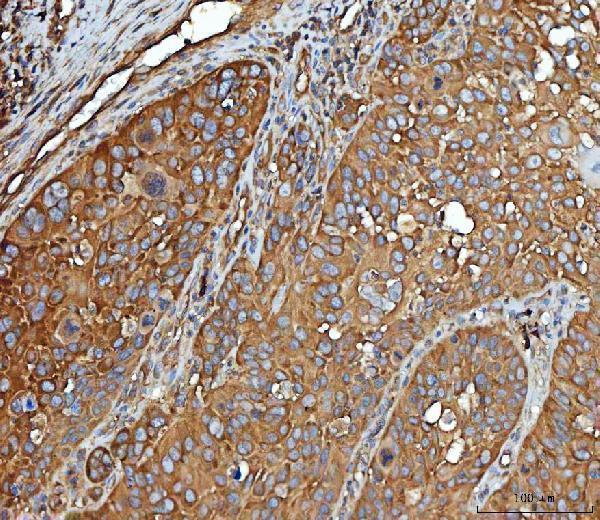
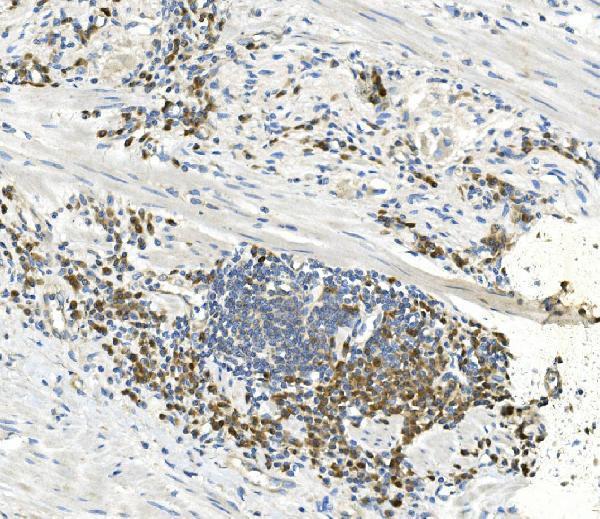
Real IHC data IHC analysis of EEF2 using anti-EEF2 antibody (A00830-1). EEF2 was detected in a paraffin-embedded section of human breast cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-EEF2 Antibody (A00830-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-EEF2 Antibody ®
Cat # A00830-1
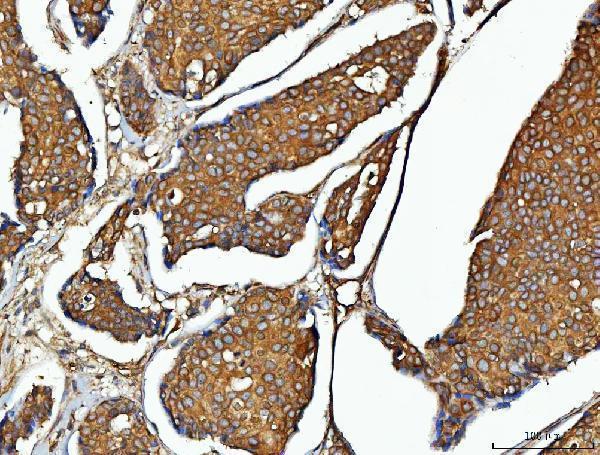
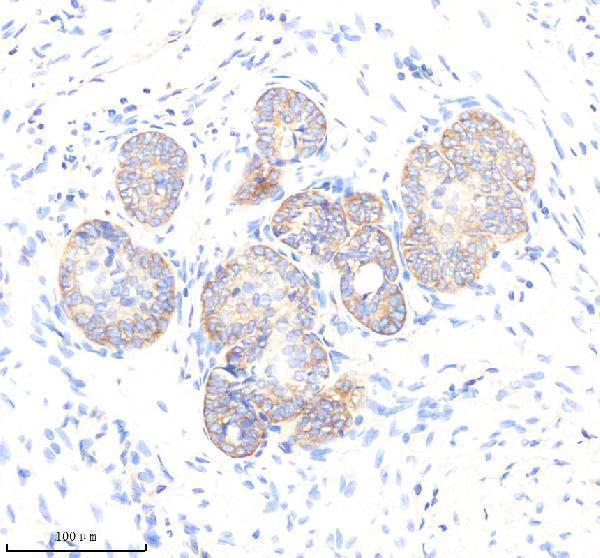
Real IHC data IHC analysis of EEF2 using anti-EEF2 antibody (M00830-2). EEF2 was detected in paraffin-embedded section of human breast cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2μg/ml mouse anti-EEF2 Antibody (M00830-2) overnight at 4°C. Biotinylated goat anti-mouse IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1021) with DAB as the chromogen.
Anti-EEF2 ® Antibody (monoclonal, 5F5)
Cat # M00830-2
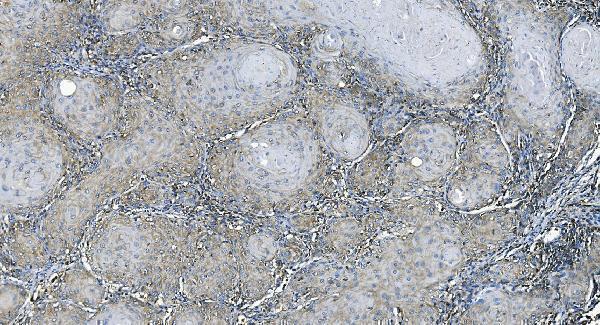
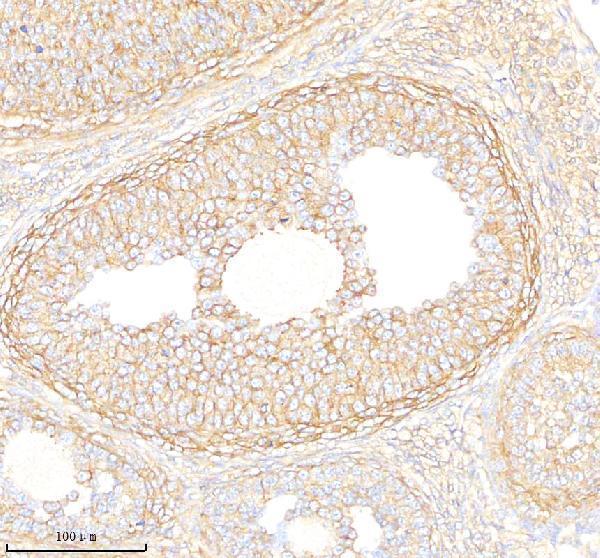
Real IHC data IHC analysis of EEF2 using anti-EEF2 antibody (M00830-1). EEF2 was detected in a paraffin-embedded section of human prostate cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1:50 rabbit anti-EEF2 Antibody (M00830-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-EEF2 Monoclonal Antibody
Cat # M00830-1

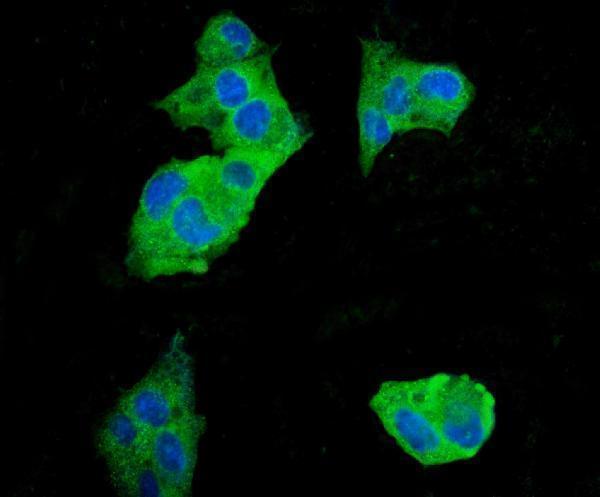
A00830-2 and A00830-1 have IHC images from human breast cancer paraffin sections; A00830-2 also has an IF image from A431 cells (catalog image captions). M00830-2 has a human breast cancer paraffin-section IHC image and a HEPG2 cell IF image, while M00830-1 has human prostate cancer and rat ovary paraffin-section IHC images (catalog image captions).

Which to pick: For tissue IHC, M00830-1 offers a rabbit monoclonal with both human and rat paraffin-section images (catalog host/clone; M00830-1 IHC captions). For IF/ICC, choose A00830-2 or M00830-2: both list IF/ICC and have human-cell IF images; M00830-2 is a mouse monoclonal (catalog applications/host/clone; respective IF captions). For broader species coverage, A00830-1 lists human, monkey, mouse, rat and zebrafish reactivity, though its pictured IHC is in human tissue; the fixative is unreported in each SKU’s paraffin-section IHC caption (catalog reactivity; respective IHC captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P13639 (EF2_HUMAN, Elongation factor 2).
  2. Human Protein Atlas. EEF2 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. EEF2 subcellular location (ICC-IF): Localized to the plasma membrane and cytosol..
  4. Human Protein Atlas. EEF2 antibody validation summary (3 antibodies).
  5. Eukaryotic elongation factor 2 is a prognostic marker and its kinase a potential therapeutic target in HCC. Oncotarget 2017 — PMC5355317.
  6. The translation elongation factor eEF2 is a novel tumor‑associated antigen overexpressed in various types of cancers. International journal of oncology 2014 — PMC4027928.
  7. Rapamycin Extends Life Span in Apc(Min/+) Colon Cancer FAP Model. Clinical colorectal cancer 2021 — PMC7956131.
  8. Coordination of changes in expression and phosphorylation of eukaryotic elongation factor 2 (eEF2) and eEF2 kinase in hypertrophied cardiomyocytes. Biochemistry and biophysics reports 2016 — PMC5613342.
  9. PubMed PMID:2610926 — UniProt-cited evidence.
  10. PubMed PMID:1596361 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.