FTO / Alpha-ketoglutarate-dependent dioxygenase FTO · IHC design guide

Design Immunohistochemistry for FTO

FTO staining is generally nuclear in tissue IHC, with high staining in adrenal glandular cells and cerebellar granular layer cells (HPA tissue IHC). Plan paraffin section staining around the catalog antibody’s 2–5 μg/mL IHC range (datasheet A00219-3).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for FTO (IHC for FTO): expected localisation Predominantly nuclear in tissue; cytoplasm also annotated (HPA tissue IHC; UniProt), antibody A00219-3, validated IHC image, and IHC protocol steps
Printable FTO IHC protocol sheet — expected localisation Predominantly nuclear in tissue; cytoplasm also annotated (HPA tissue IHC; UniProt), antibody A00219-3, controls and protocol steps. Open the full FTO IHC guide →

FTO Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Predominantly nuclear in tissue; cytoplasm also annotated (HPA tissue IHC; UniProt)
Staining pattern General nuclear staining across tissue cell types (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A00219-3)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ None in HPA (detected in all 45 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A00219-3)
Caveat Adipocytes show low staining despite broad tissue expression (HPA tissue IHC; UniProt)
Regulation Elevated in defined AML genotypes (UniProt)
Isoform / epitope 4 isoforms; check epitope coverage for the forms studied (UniProt)
Section 1

Recommended FTO IHC & IF Protocols

The catalog antibody’s IHC-P protocol (datasheet A00219-3) is accompanied by published FTO IHC methods for esophageal, oral, and liver cancer tissues (PMC9107638; PMC9792536; PMC12078176).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human colon cancer tissue; fixative not specified (datasheet A00219-3)
FixationImage fixative and duration unreported (datasheet A00219-3); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A00219-3); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A00219-3)
Primary antibodyRabbit anti-FTO, 2-5μg/ml (datasheet A00219-3)
Primary incubationOvernight at 4 °C (datasheet A00219-3)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A00219-3)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultFTO-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: General nuclear expression. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval (datasheet A00219-3). Tris-EDTA pH 9.0 is a published alternative for oral tissue sections (PMC9792536).
Section 2

What Is the Expected FTO Staining Pattern?

FTO is a soluble protein with no transmembrane segment (UniProt Q9C0B1 topology). Expect predominantly nuclear staining in paraffin tissue sections: HPA describes general nuclear expression, including high staining in adrenal glandular cells and cerebellar granular layer cells (HPA tissue IHC). HPA rates its tissue staining “Enhanced,” while noting medium consistency with RNA expression (HPA tissue IHC). UniProt also reports cytoplasmic localisation, so assess compartment patterns in context (UniProt Q9C0B1).

What am I looking at on my slide?
Nuclear staining in adrenal glandular cells or cerebellar granular layer cells, with limited background.This matches HPA’s general nuclear tissue pattern and high staining in those cells (HPA tissue IHC). Compare intensity within the same staining run; HPA levels do not define a universal scoring cutoff.
Predominantly membranous, extracellular or edge-confined colour instead of a cellular nuclear pattern.These distributions do not match the reported FTO tissue pattern or soluble topology (HPA tissue IHC; UniProt Q9C0B1). Check section edges, detection background and controls before treating them as FTO.
Strong staining in a cell population expected to be low, or in adjacent noncellular material.HPA reports low staining in adipocytes, hepatocytes and bone marrow hematopoietic cells (HPA tissue IHC). Unexpected colour warrants checks for cross-reactivity or endogenous detection activity; a low HPA level does not establish absence.
Diffuse colour across tissue and blank spaces, with little distinction between nuclei and background.This is difficult to score as FTO against HPA’s general nuclear tissue pattern (HPA tissue IHC). In routine chromogenic IHC, inspect the no-primary control, blocking and detection steps for nonspecific signal.
No staining in adequately represented adrenal glandular cells or cerebellar granular layer cells.Both are high-staining HPA examples (HPA tissue IHC). A blank known-positive control makes a negative test section inconclusive; review antibody suitability and the IHC run before assigning a biological negative.
💡Expected FTO appearanceCall a section positive when cellular staining is predominantly nuclear in the sampled cells, with readily visible signal in HPA high examples such as adrenal glandular cells; broad extracellular or edge-confined colour is suspect (HPA tissue IHC; UniProt Q9C0B1 topology).
How each factor affects the staining
Tissue and cell selectionAdrenal glandular cells and cerebellar granular layer cells are HPA high examples; adipocytes and hepatocytes are HPA low examples (HPA tissue IHC). Score the identified cell population rather than averaging colour over a whole section.
Compartment evidenceHPA tissue IHC describes general nuclear expression, whereas UniProt places FTO mainly in the nucleus and also in the cytoplasm (HPA tissue IHC; UniProt Q9C0B1). Some cytoplasmic signal alone is therefore insufficient to call a stain false.
Antibody validationHPA lists HPA041086 and HPA068695 as IHC “Enhanced,” while its tissue profile notes medium consistency with RNA expression (HPA antibodies; HPA tissue IHC). Validation supports interpretation of the reported pattern, not every signal in every specimen.
IF/ICC interpretation?On its separate IF/ICC guide, account for HPA’s supported cytosolic and approved vesicular localisation, which differs from its general nuclear tissue IHC profile (HPA subcellular; HPA tissue IHC). Do not transfer the IF pattern directly to paraffin IHC.
Protein forms and topologyUniProt lists four isoforms, no signal peptide or propeptide, and no transmembrane segment (UniProt Q9C0B1). These annotations support a cellular, nonmembranous expectation; they do not predict which isoforms a given antibody detects.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Known-positive tissue is blank.The run or antibody may have failed; adrenal glandular cells and cerebellar granular layer cells are HPA high examples (HPA tissue IHC).Confirm those cells are present, then review the IHC-validated antibody’s instructions, retrieval, dilution and detection controls. These are general IHC checks, not documented FTO fixation effects.
Test section is weak, but the positive control stains.The sampled cells may have low FTO staining: HPA reports low levels in hepatocytes, adipocytes and bone marrow hematopoietic cells (HPA tissue IHC).Identify the stained cell population and compare it with the HPA tissue profile. Keep a weak result separate from a failed run; do not infer absence from intensity alone.
Colour is strong in blank spaces, stroma or section edges.The distribution conflicts with HPA’s general nuclear pattern and may reflect nonspecific chromogen deposition or detection background (HPA tissue IHC; general IHC practice).Inspect a no-primary control and section morphology; review blocking, washing and detection steps as general IHC checks before scoring the colour as FTO.
Signal appears predominantly membranous.A membrane pattern is not predicted by FTO’s lack of a transmembrane segment or HPA’s general nuclear tissue profile (UniProt Q9C0B1; HPA tissue IHC).Check whether colour follows cell borders rather than nuclei; compare a known-positive section and the no-primary control before accepting a cellular interpretation.
Cytoplasmic staining accompanies nuclear staining.UniProt reports cytoplasmic FTO as well as mainly nuclear FTO; HPA tissue IHC describes a general nuclear pattern (UniProt Q9C0B1; HPA tissue IHC).Record both compartments and judge their distribution in identified cells. Avoid calling cytoplasmic colour an artefact solely because the tissue profile emphasizes nuclei.
An IF/ICC image seems inconsistent with the paraffin IHC slide.HPA reports mainly cytosolic localisation, with additional vesicles, in ICC-IF but general nuclear expression in tissue IHC (HPA subcellular; HPA tissue IHC).Interpret each application against its own HPA evidence and controls. Use the separate IF/ICC guide for that application; do not revise the paraffin IHC call from an ICC-IF image alone.

Sample controls for FTO IHC & IF

🧪Run adrenal gland first: glandular cells should stain strongly (HPA: High in adrenal gland glandular cells). HPA detects FTO in all 45 scored tissues, so there is no supported negative tissue; use no-primary and isotype controls, and expect any unstained neighboring cells to remain at background, although no specific internal-negative cell type is identified (HPA: no negative rows).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: None in HPA: FTO is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show FTO in A-431, U-251MG, U2OS, HeLa, Hep-G2, with annotated localisation: Cytosol (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and a concentration-matched rabbit IgG isotype control matched to the primary antibody’s clonality where known (caption: rabbit anti-FTO antibody). Confirm specificity with FTO knockout material or, if the immunizing peptide is available, peptide blocking; check endogenous peroxidase and biotin background on the adrenal section because the reported detection uses biotin–SABC and DAB (caption: biotinylated secondary, SABC, DAB).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected paraffin-section caption does not state the fixative (caption: fixative not stated). The caption provides EDTA retrieval at pH 8.0 as an IHC starting condition, but does not establish that retrieval is required (caption: heat-mediated EDTA retrieval). The supplied evidence does not show that frozen sections or IF are easier for FTO, or document an adrenal-specific artefact; assess background from the biotin–SABC/DAB detection used in the caption.

HPA tissue IHC evidence for FTO

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Cerebellum Cells in granular layer High Protein (IHC) HPA →
Cervix Glandular cells High Protein (IHC) HPA →
Duodenum Paneth cells High Protein (IHC) HPA →
Epididymis Glandular cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: FTO is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced FTO IHC Tips

Troubleshoot FTO staining in paraffin sections by checking retrieval, cell compartment, background, and scoring before interpreting differences between samples.

Which retrieval conditions should I try first when FTO staining is weak?
Start with heat-mediated retrieval in EDTA at pH 8.0 (datasheet A00219-3). The catalog antibody stained a paraffin section of human colon cancer after that retrieval, followed by 2 μg/ml primary antibody overnight at 4°C (datasheet A00219-3). If staining remains weak, vary heating time on adjacent sections while keeping the buffer and detection steps constant; compare signal in intact cells with tissue damage and background. Include an adrenal glandular-cell control if available, because that cell population has high FTO staining (HPA: High in adrenal glandular cells). Record the retrieval conditions used for each slide before comparing staining intensity.
Could fixation explain variable FTO staining between paraffin blocks?
Target-specific fixation sensitivity is unknown: the selected paraffin-section caption does not report its fixative (datasheet A00219-3: fixative not stated). Compare sections with documented fixation histories using the same EDTA pH 8.0 retrieval, 2 μg/ml primary concentration, and overnight 4°C incubation (datasheet A00219-3). Include a similarly processed reference section in each run, and inspect morphology alongside nuclear and cytoplasmic signal. If one block stains poorly, repeat staining after checking section adhesion, retrieval consistency, and detection controls before assigning the difference to fixation. Neither tissue staining patterns nor FTO structure establish a fixation effect for this antibody.
How should I handle nuclear and cytoplasmic FTO staining in the same section?
Score nuclear and cytoplasmic staining separately: FTO is reported mainly in the nucleus, including nuclear speckles, and also in the cytoplasm (UniProt Q9C0B1: subcellular location). HPA tissue IHC describes general nuclear expression, whereas its cell imaging reports supported cytosolic localisation and additional vesicular localisation (HPA: tissue IHC profile; HPA: subcellular summary). Use the counterstain to define nuclei, then assess cytoplasmic signal within intact cell boundaries at a matched microscope setting. A predominantly cytoplasmic pattern therefore merits validation rather than automatic rejection; confirm it with an independent antibody or orthogonal expression evidence. Document which compartment drives any group difference.
Can this antibody distinguish FTO isoforms or epitope changes?
Do not assign isoform identity from this stain alone: FTO has 4 annotated isoforms, and the supplied caption does not identify the antibody epitope (UniProt Q9C0B1: isoforms; datasheet A00219-3: caption). Map any subsequently supplied immunogen sequence against those isoforms before claiming shared or selective recognition. FTO has annotated phosphothreonine at residue 4 and N6-acetyllysine at residue 216, but their effects on this antibody are unknown (UniProt Q9C0B1: modified residues). If staining changes across samples, compare it with transcript or protein evidence that can resolve isoforms. Report the result as antibody-detected FTO staining unless specificity has been established.
How can IF help resolve FTO staining patterns seen by chromogenic IHC?
Use IF as a separate validation experiment, starting with the cell compartments implicated by IHC rather than assuming that the paraffin-section protocol transfers unchanged. Multiplex FTO with a marker for the expected cell population, such as adrenal glandular cells, which show high tissue staining (HPA: High in adrenal glandular cells). Choose spectrally separated fluorophores and favor a far-red channel when tissue autofluorescence obscures shorter wavelengths; include single-stain and no-primary controls. Because FTO has no annotated transmembrane segment and is reported in nuclear and cytoplasmic compartments, use permeabilisation conditions that allow access to intracellular epitopes (UniProt Q9C0B1: topology and subcellular location). Record nuclear and cytoplasmic fluorescence separately.
What should I check when DAB staining is widespread or patchy?
First inspect a no-primary section to separate detection-system background from primary-antibody staining. The selected protocol uses a biotinylated secondary, streptavidin–biotin complex, and DAB (datasheet A00219-3); endogenous biotin and peroxidase can therefore complicate chromogenic interpretation. Apply an appropriate peroxidase block and, where indicated by the control, an endogenous-biotin block; these are general IHC measures, not demonstrated FTO-specific requirements. The caption used 10% goat serum blocking and 2 μg/ml primary antibody overnight at 4°C (datasheet A00219-3). If background persists, titrate primary antibody and compare wash conditions while preserving a positive reference section.
How should I quantify FTO across sections with different cell mixtures? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, then use the same threshold and imaging settings across samples. For nuclear DAB, record the percentage of positive cells and an H-score based on staining intensity; keep cytoplasmic staining as a separate measure because both compartments are reported for FTO (UniProt Q9C0B1: subcellular location). Normalize counts to the number of evaluable cells in the specified population, or report positive-cell density per mm² of viable tissue. Stratify by cell type when composition differs; adrenal glandular cells, for example, have high staining in the reference atlas (HPA: High in adrenal glandular cells). Exclude folds, damaged edges, and necrotic areas using consistent rules.
How can I distinguish convincing FTO signal from staining artefact?
Look for reproducible staining within intact cells and evaluate nuclear and cytoplasmic patterns separately: UniProt reports both compartments, while HPA tissue IHC describes general nuclear expression (UniProt Q9C0B1: subcellular location; HPA: tissue IHC profile). Check whether the stained population matches an expected cell type, such as highly stained adrenal glandular cells, while allowing for tissue-dependent expression (HPA: High in adrenal glandular cells; HPA: low tissue specificity). Signal confined to section edges, folds, or necrotic areas is suspect on morphological grounds. Run no-primary and detection controls to assess endogenous peroxidase or biotin with the selected DAB and streptavidin–biotin workflow (datasheet A00219-3). Confirm unexpected patterns with orthogonal evidence before drawing biological conclusions.
Boster reagents

Best FTO / Alpha-ketoglutarate-dependent dioxygenase FTO IHC Antibodies

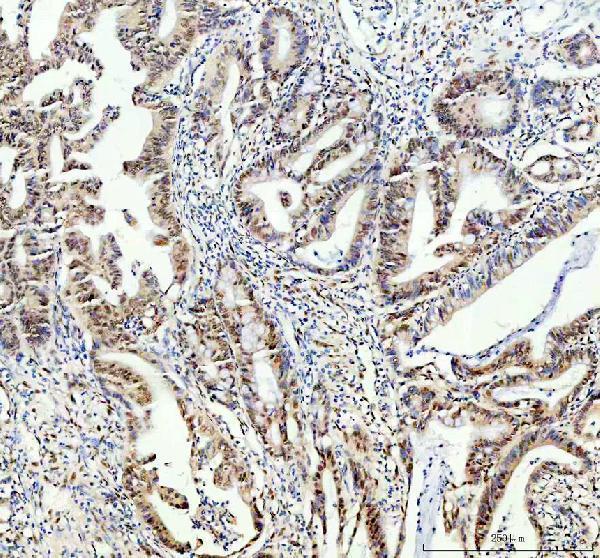
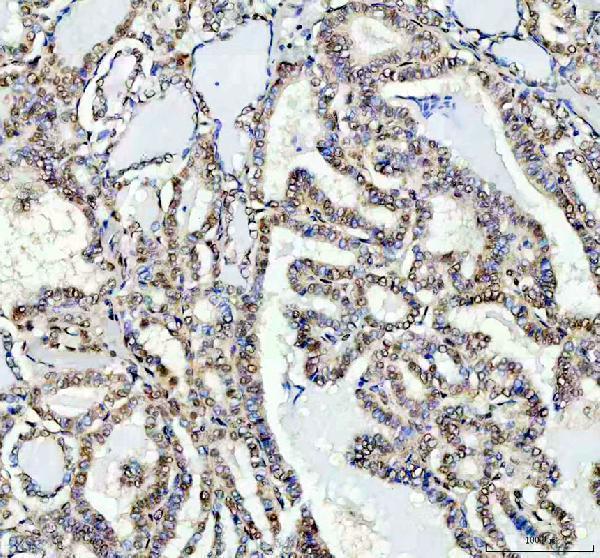
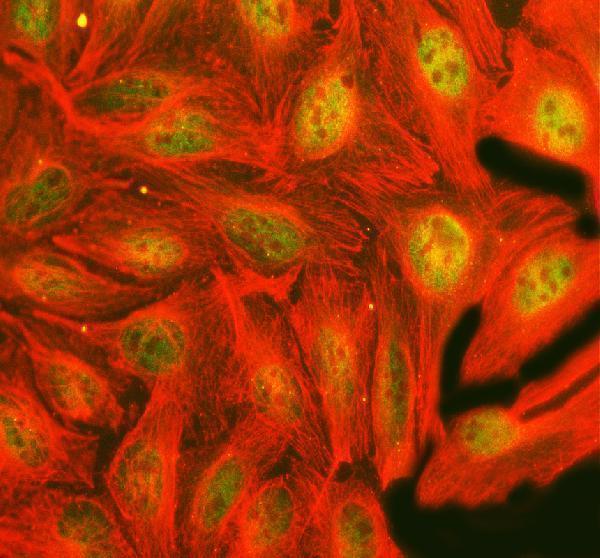
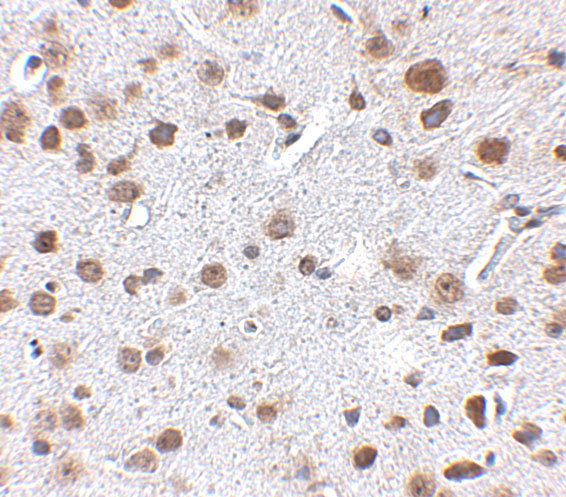
Catalog anti-FTO antibodies have IHC images from human colon cancer, mouse brain and human kidney, plus an IF image with no sample identified (catalog image captions). Listed reactivity spans human, mouse and rat (catalog applications/reactivity).

Real IHC data IHC analysis of FTO using anti-FTO antibody (A00219-3). FTO was detected in a paraffin-embedded section of human colon cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-FTO Antibody (A00219-3) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-FTO Antibody ®
Cat # A00219-3
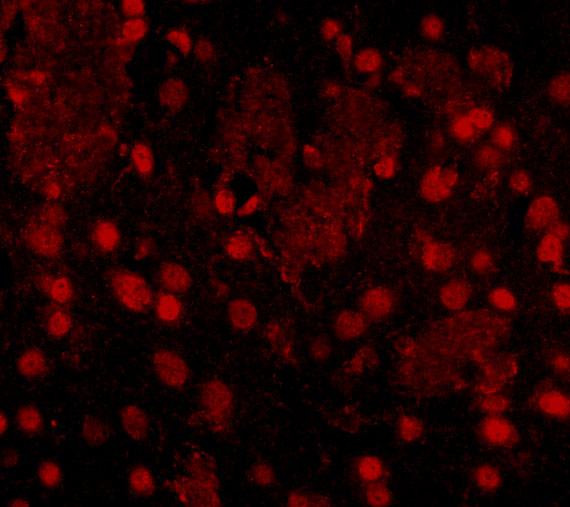
Real IHC data Immunohistochemistry of FTO in mouse brain tissue with FTO antibody at 2.5 μg/mL.
Anti-FTO Antibody
Cat # A00219
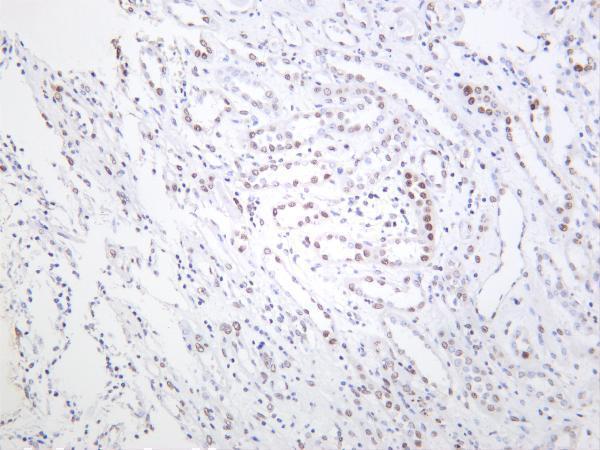
Real IHC data Human kidney was stained with anti-FTO rabbit antibody
Anti-FTO Rabbit Monoclonal Antibody
Cat # M00219-2
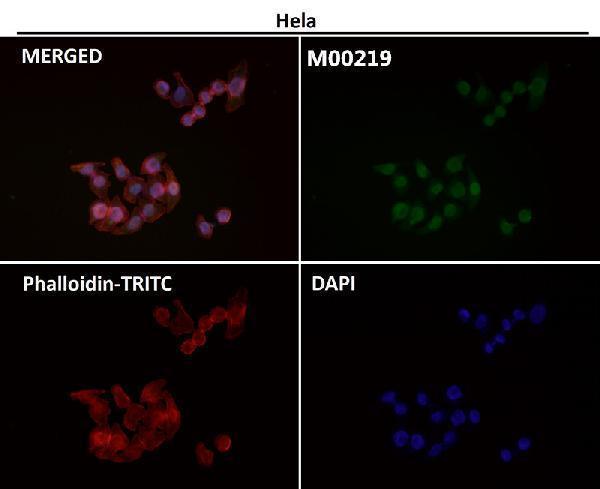
Real IF data Immunofluorescent analysis using the Antibody at 1:50 dilution.
Anti-FTO Monoclonal Antibody
Cat # M00219

A00219-3 shows paraffin-section IHC in human colon cancer (A00219-3 IHC caption); A00219 shows mouse brain IHC at 2.5 μg/mL, although its listed reactivity is human (A00219 IHC caption; catalog reactivity). M00219-2 shows human kidney IHC (M00219-2 IHC caption); M00219 shows IF at 1:50 without an identified sample (M00219 IF caption).

Which to pick: For paraffin-section tissue IHC, choose A00219-3: its human colon cancer caption documents EDTA retrieval at pH 8.0 and antibody at 2 μg/mL; the fixative is unreported (A00219-3 IHC caption). For IF/ICC, A00219-3 lists both applications and has an IF image in U2OS cells; M00219 also lists IF/ICC but its IF caption does not identify the sample (catalog applications; A00219-3 IF caption; M00219 IF caption). For work across human, mouse and rat, A00219-3 and monoclonal M00219-2 list all three species; A00219-3 has paraffin-section IHC captions for each, while M00219-2’s IHC caption identifies human kidney without reporting section processing or fixative (catalog reactivity; A00219-3 IHC captions; M00219-2 IHC caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9C0B1 (FTO_HUMAN, Alpha-ketoglutarate-dependent dioxygenase FTO).
  2. Human Protein Atlas. FTO tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. FTO subcellular location (ICC-IF): Mainly localized to the cytosol. In addition localized to vesicles..
  4. Human Protein Atlas. FTO antibody validation summary (3 antibodies).
  5. m6A demethylase FTO promotes tumor progression via regulation of lipid metabolism in esophageal cancer. Cell & bioscience 2022 — PMC9107638.
  6. A study of RNA m6A demethylases in oral epithelial dysplasia and oral squamous cell carcinoma. Journal of oral biology and craniofacial research 2023 — PMC9792536.
  7. FTO-CHRM3 axis regulates multiple myeloma progression: a machine learning-based identification. Annals of hematology 2026 — PMC13009012.
  8. FTO Promotes Hepatocellular Carcinoma Progression by Mediating m6A Modification of BUB1 and Targeting TGF-βR1 to Activate the TGF-β Signaling Pathway. Journal of clinical and translational hepatology 2025 — PMC12078176.
  9. PubMed PMID:11214970 — UniProt-cited evidence.
  10. PubMed PMID:15616553 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.