IRAK1 / Interleukin-1 receptor-associated kinase 1 · IHC design guide

Design Immunohistochemistry for IRAK1

Plan paraffin-section IRAK1 staining with the catalog antibody at 0.5–1 μg/mL (datasheet A01021-1). Compare cytoplasmic signal across cell types (HPA tissue IHC) and score staining against control sections (standard IHC practice).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
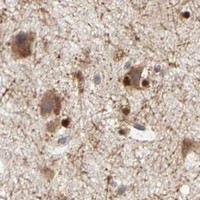
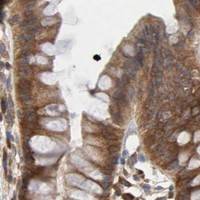
Immunohistochemistry protocol sheet for IRAK1 (IHC for IRAK1): expected localisation Cytoplasmic tissue staining (HPA tissue IHC), antibody A01021-1, validated IHC image, and IHC protocol steps
Printable IRAK1 IHC protocol sheet — expected localisation Cytoplasmic tissue staining (HPA tissue IHC), antibody A01021-1, controls and protocol steps. Open the full IRAK1 IHC guide →

IRAK1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic tissue staining (HPA tissue IHC)
Staining pattern Widespread cytoplasmic staining across cell types (HPA tissue IHC)
Antigen retrieval Citrate pH 6 HIER, heat-mediated (datasheet A01021-1)
Positive control ⓘ Breast+4 more · see all
Negative control ⓘ Adipose tissue+2 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Adipocytes and myocytes may lack staining (HPA tissue IHC)
Regulation Expression induction is unreported (UniProt)
Isoform / epitope 4 isoforms; epitope coverage is unspecified (UniProt)
Section 1

Recommended IRAK1 IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol (datasheet: A01021-1) with three published IRAK1 tissue IHC methods (PMC5367901; PMC12521082; PMC6438138).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human Ovarian cancer tissues; fixative not specified (datasheet A01021-1)
FixationImage fixative and duration unreported (datasheet A01021-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: Citrate pH 6, 20 min (datasheet A01021-1)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A01021-1)
Primary antibodyRabbit anti-IRAK1, 0.5-1μg/ml (datasheet A01021-1)
Primary incubationOvernight at 4 °C (datasheet A01021-1)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A01021-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultIRAK1-positive staining in glandular cells of breast (HPA tissue IHC: High). HPA tissue profile: Ubiquitous cytoplasmic expression. No signal in the no-primary control.
💡Decision noteStart with heat-mediated citrate retrieval at pH 6 (datasheet: A01021-1); a published breast cancer protocol also used sodium citrate, but did not state its pH (PMC6438138).
Section 2

What Is the Expected IRAK1 Staining Pattern?

IRAK1 should show predominantly cytoplasmic staining in many cell types (HPA: ubiquitous cytoplasmic expression; IHC reliability Supported, with medium consistency against RNA data). Strong examples include breast and colon glandular cells, cortical neurons, and placental trophoblastic cells (HPA: High). Nuclear localization can occur under specific conditions (UniProt P51617: nuclear translocation when sumoylated). A membrane rim is not the expected pattern (UniProt P51617: no transmembrane segment).

What am I looking at on my slide?
Cytoplasmic signal in breast or colon glandular cells, cortical neurons, or placental trophoblastic cells.This matches the main compartment and cell populations reported for IRAK1 (HPA: ubiquitous cytoplasmic expression; High in these cells). Compare cells within the same section because widespread expression does not mean equal intensity in every cell (HPA: variable tissue and cell staining levels).
Predominantly sharp cell-surface rims, with little cytoplasmic signal.A membrane-rim pattern conflicts with the reported cytoplasmic pattern and lack of a transmembrane segment (HPA: cytoplasmic expression; UniProt P51617 topology). Review morphology and detection background before assigning it to IRAK1 (general IHC practice).
Strong signal in adipocytes, skeletal myocytes, or smooth muscle cells.These cells are reported as not detected in tissue IHC (HPA: adipocytes, skeletal myocytes, and smooth muscle cells Not detected). Cross-reactivity or endogenous detection activity is possible; inspect negative controls and nearby cell types before interpreting the signal (general IHC practice).
Broad, poorly bounded color over tissue and empty areas.Diffuse deposition cannot establish cellular IRAK1 localization (general IHC practice). Check the no-primary control, blocking, washes, and chromogenic detection steps; excess background can obscure the cytoplasmic pattern reported by HPA (HPA: ubiquitous cytoplasmic expression).
No signal in an adequately preserved breast or colon glandular-cell region.That conflicts with the High staining reported for those cells (HPA: breast and colon glandular cells High). First assess whether the IHC-validated antibody, detection reagents, and retrieval conditions worked on a control section (general IHC practice); one absent stain does not establish absent IRAK1.
💡Expected IRAK1 appearanceCall positive when identifiable breast or colon glandular cells show clear, strong cytoplasmic staining (HPA: High; cytoplasmic expression); a dominant membrane rim or strong staining of reported negative cells warrants investigation (UniProt P51617 topology; HPA: Not detected in adipocytes and muscle cells).
How each factor affects the staining
Compartment and activation stateCytoplasm is the principal tissue-IHC expectation (HPA: ubiquitous cytoplasmic expression). Nuclear staining has biological precedent when IRAK1 is sumoylated (UniProt P51617: nuclear translocation), but nuclear color alone does not demonstrate that modification (general IHC interpretation).
Cell populationTissue context affects the expected intensity: ovarian follicle cells and pancreatic exocrine glandular cells are High, while lung macrophages and kidney glomerular cells are Low (HPA: tissue IHC). Avoid scoring all cell types against one intensity threshold (general IHC practice).
Isoform coverageIsoforms 1 and 2 occur in all tissues examined, with isoform 1 more strongly expressed (UniProt P51617: tissue specificity). Four isoforms are listed (UniProt P51617: isoforms 1–4). The payload does not establish which isoforms the IHC antibodies recognize.
Antibody evidenceHPA marks IHC staining as Supported for HPA054476 and CAB004461 (HPA: antibody validation). Overall tissue reliability is Supported with medium agreement to RNA (HPA: tissue IHC). Treat these classifications as support for interpretation, not proof that every positive cell is specific.
Antigen retrievalRetrieval conditions are a routine IHC optimization variable (general IHC practice). Neither HPA nor UniProt supplies an IRAK1-specific retrieval condition or fixation-sensitivity result here; compare a known-positive section when optimizing, without predicting a target-specific fixation effect.
IF/ICC Q: Where should IRAK1 appear?A: Mainly in the cytosol, with additional nucleoplasmic localization (HPA: ICC-IF, both supported). HPA lists ICC-IF images for MCF-7, U-251MG, U2OS, RPTEC/TERT1, and serum-starved hTERT-RPE1 (HPA: subcellular). This is a localization reference, not an IF protocol.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Known-positive glandular cells remain unstained.An unsuccessful antibody, retrieval, or detection step is possible (general IHC practice); breast and colon glandular cells are reported High (HPA: tissue IHC).Run the IHC-validated antibody with a positive control section; check retrieval, dilution, and detection against its validated IHC-P instructions (general IHC practice). Do not infer tissue absence from a failed control.
Most tissue structures carry diffuse chromogen.Background from insufficient blocking or washing, excessive antibody concentration, or endogenous detection activity is possible (general IHC practice).Review no-primary and detection controls, blocking and washes; adjust dilution using the validated IHC-P instructions (general IHC practice). Reassess whether cytoplasmic signal remains in expected cells (HPA: cytoplasmic expression).
Staining forms a dominant membrane rim.This disagrees with the reported cytoplasmic distribution and lack of a transmembrane segment (HPA: cytoplasmic expression; UniProt P51617 topology).Compare with the no-primary control and tissue morphology; repeat with an IHC-supported antibody if needed (general IHC practice; HPA: HPA054476 and CAB004461 IHC Supported).
Adipocytes or muscle cells stain strongly.Those populations are reported as Not detected, so nonspecific staining or endogenous detection activity is possible (HPA: tissue IHC; general IHC practice).Check negative controls and the chromogenic detection steps, then compare staining in an expected High population on the run (general IHC practice; HPA: breast glandular cells High).
Nuclear staining appears alongside cytoplasmic staining.Nuclear IRAK1 is plausible under specified conditions (UniProt P51617: sumoylation-associated translocation); HPA also reports supported nucleoplasmic localization in ICC-IF (HPA: subcellular).Record nuclear and cytoplasmic scores separately and check controls (general IHC practice). Do not call nuclear IHC staining evidence of sumoylation without independent evidence (UniProt P51617: conditional localization).
A Low population is weaker than a High population.The difference can reflect reported cell-specific staining levels: lung macrophages and kidney glomerular cells are Low, while ovarian follicle cells are High (HPA: tissue IHC).Score each cell population against its reported level and inspect a High control before changing staining conditions (HPA: tissue IHC; general IHC practice).

Sample controls for IRAK1 IHC & IF

🧪Run breast first: glandular cells should stain strongly (HPA: High in breast glandular cells). Use skeletal muscle myocytes as the negative tissue (HPA: Not detected in skeletal muscle myocytes); on the breast slide, compare glandular staining with adjacent nonglandular cells that show background staining, while recognizing that HPA does not identify a validated internal-negative cell type (HPA: breast glandular-cell row).
Positive control tissue: Breast (Glandular cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show IRAK1 in MCF-7, U-251MG, U2OS, RPTEC/TERT1, hTERT-RPE1 (serum starved), with annotated localisation: Cytosol (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control; a matched nonimmune rabbit IgG isotype control; and IRAK1-knockout material as a biological negative (selected-SKU caption: rabbit primary antibody). Quench endogenous peroxidase and check for endogenous biotin staining in breast sections because the documented IHC detection uses a biotinylated secondary, streptavidin–biotin complex, and DAB (selected-SKU caption: SABC/DAB detection).
⚠️Feasibility: A target-specific fixation window and fixation effect are unreported in the supplied evidence; the selected-SKU paraffin-section caption does not state a fixative (selected-SKU caption: fixative unreported). The documented IHC preparation uses heat retrieval in citrate buffer at pH 6 for 20 minutes, but the evidence does not establish whether retrieval is essential (selected-SKU caption: citrate retrieval). Frozen-section versus IF ease is unreported; for breast IHC, assess background from the biotin-based detection system before interpreting glandular staining (selected-SKU caption: SABC/DAB detection; HPA: High in breast glandular cells).

HPA tissue IHC evidence for IRAK1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Breast Glandular cells High Protein (IHC) HPA →
Cerebellum Processes in granular layer High Protein (IHC) HPA →
Cerebral cortex Neuronal cells High Protein (IHC) HPA →
Colon Glandular cells High Protein (IHC) HPA →
Hippocampus Glial cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Skeletal muscle Myocytes Not detected Protein (IHC) HPA →
Smooth muscle Smooth muscle cells Not detected Protein (IHC) HPA →
Section 3

Advanced IRAK1 IHC Tips

Troubleshoot IRAK1 staining in paraffin sections using the catalog antibody’s tissue IHC conditions, with IF/ICC considerations kept to a separate entry.

Which retrieval conditions should I try first for weak IRAK1 staining?
Start with heat mediated retrieval in citrate buffer at pH 6 for 20 minutes (datasheet A01021-1). The selected paraffin section example then used 10% goat serum block and 1 μg/ml primary antibody overnight at 4°C (datasheet A01021-1). If staining remains weak, vary heating time on adjacent sections while holding antibody concentration and detection constant (standard IHC practice). Include a positive reference section with documented IRAK1 staining, such as ovarian follicle cells, so a failed run is distinguishable from a low expressing region (HPA: High in ovarian follicle cells). Compare tissue morphology as well as signal, because excessive heating can damage sections (standard IHC practice).
Could fixation explain weak or uneven IRAK1 staining?
The selected paraffin section caption does not state its fixative, so target specific fixation sensitivity is unknown (datasheet A01021-1: fixative unreported). Record the actual fixative, fixation duration, section thickness, and time from sectioning to staining for each specimen (standard IHC practice). When comparing samples, hold retrieval at citrate pH 6 for 20 minutes and the primary at 1 μg/ml overnight at 4°C initially (datasheet A01021-1). Test differently processed sections side by side with the same positive reference and detection run (standard IHC practice). Do not attribute a fixation effect to IRAK1 without that comparison (standard IHC practice).
Should IRAK1 staining be cytoplasmic, nuclear, or both?
Expect predominantly cytoplasmic staining in tissue sections (HPA: ubiquitous cytoplasmic expression; HPA subcellular: supported cytosol). Nuclear signal can be biologically plausible because IRAK1 translocates to the nucleus when sumoylated (UniProt P51617: subcellular location). Lipid droplet association is also described through RSAD2 recruitment by similarity, so avoid treating puncta alone as proof of this location (UniProt P51617: lipid droplet, by similarity). Score cytoplasmic and nuclear staining separately in viable cells, with the same counterstain and exposure conditions across sections (standard IHC practice). Compare doubtful compartments against a no primary control and tissue morphology before assigning them to IRAK1 (standard IHC practice).
Can this antibody distinguish IRAK1 isoforms or modified epitopes in sections?
IRAK1 has 4 listed isoforms, while isoforms 1 and 2 are reported across examined tissues, with isoform 1 more abundant (UniProt P51617: isoforms and tissue specificity). The supplied tissue IHC caption does not identify the antibody epitope or establish isoform selectivity (datasheet A01021-1: selected caption). Check the immunogen and its alignment to each isoform before interpreting a staining difference as isoform specific (standard antibody validation practice). Phosphorylation sites include residues 66 and 209, but the caption supplies no modification selective staining evidence (UniProt P51617: modified residues; datasheet A01021-1: selected caption). Report the observed staining as IRAK1 immunoreactivity unless independent epitope or isoform validation supports a narrower claim (standard IHC practice).
How should I assess IRAK1 localisation by multiplex IF/ICC?
Use a marker for the expected cell population, such as an epithelial marker when examining glandular cells, and assess IRAK1 within marker positive cells (HPA: High in breast and colon glandular cells; standard IF practice). Place the weaker channel on a bright, spectrally separated fluorophore and compare it with an unstained specimen to assess tissue autofluorescence; a far red channel may help (standard IF practice). IRAK1 is mainly cytosolic with additional nucleoplasmic localisation and has no transmembrane segment, so optimise permeabilisation for intracellular epitope access (HPA subcellular: supported locations; UniProt P51617: topology; standard IF practice). Include single stain and no primary controls when setting multiplex acquisition (standard IF practice). Do not transfer the paraffin IHC retrieval conditions to IF/ICC without separate validation (datasheet A01021-1: tissue IHC caption; standard IF practice).
How can I reduce diffuse DAB background without losing IRAK1 signal?
The selected tissue IHC example used 10% goat serum block, biotinylated secondary antibody, a streptavidin biotin complex, and DAB (datasheet A01021-1). First compare a no primary section to identify detection related signal, then check the peroxidase block and wash steps (standard chromogenic IHC practice). Endogenous biotin can contribute to background with this detection system, so assess a biotin blocking step or an alternative detection method if the control stains (standard IHC practice). Keep the 1 μg/ml primary concentration fixed during that comparison, then titrate only if background remains (datasheet A01021-1; standard IHC practice). Evaluate background away from tissue folds, cut edges, and necrotic regions (standard IHC practice).
What is a defensible way to quantify IRAK1 IHC across samples? ⚠ ANSWER MARKED FOR VERIFICATION
Define the viable cell population and cytoplasmic compartment before scoring, since tissue staining is described as ubiquitously cytoplasmic (HPA: tissue IHC profile; standard IHC practice). For a cellular readout, record the percentage of positive cells and intensity on a 0–3 scale; an H-score spans 0–300 when each intensity percentage is weighted by its score (standard IHC practice). For sparse positive populations, report positive cells per mm² of viable tissue alongside the cell denominator (standard IHC practice). Normalise comparisons to the same cell type, viable area, staining batch, and image acquisition settings (standard IHC practice). Keep nuclear staining as a separate outcome rather than folding it into the cytoplasmic score (HPA subcellular: additional nucleoplasm; standard IHC practice).
How do I distinguish true IRAK1 staining from an IHC artefact?
Plausible IRAK1 signal is chiefly cytoplasmic, while nuclear localisation is possible under the reported sumoylation condition (HPA: tissue IHC profile; UniProt P51617: subcellular location). Compare cell identity with a documented reference: ovarian follicle cells are reported High, whereas adipocytes are reported Not detected (HPA: ovary and adipose tissue). Diffuse extracellular colour, isolated cut edge staining, and signal confined to necrosis warrant review against morphology and a no primary control (standard IHC practice). Persistent colour in that control can reflect endogenous enzyme activity or the detection system rather than primary antibody binding (standard IHC practice). Do not infer pathway activation solely from total IRAK1 staining, because activation involves phosphorylation and complex assembly (UniProt P51617: function).
Boster reagents

Best IRAK1 / Interleukin-1 receptor-associated kinase 1 IHC Antibodies

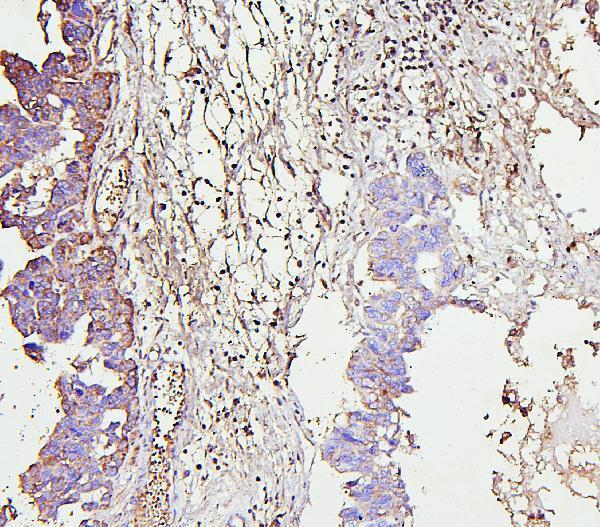
The catalog shows IRAK1 IHC images from human ovarian cancer paraffin sections and rat liver, and IF images from A549 and HeLa cells (catalog figure captions).

Real IHC data IHC analysis of IRAK1 using anti-IRAK1 antibody (A01021-1). IRAK1 was detected in paraffin-embedded section of human Ovarian cancer tissues. Heat mediated antigen retrieval was performed in citrate buffer (pH6, epitope retrieval solution) for 20 mins. The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml rabbit anti-IRAK1 Antibody (A01021-1) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC)(Catalog # SA1022) with DAB as the chromogen.
Anti-IRAK-1/IRAK1 Antibody ®
Cat # A01021-1
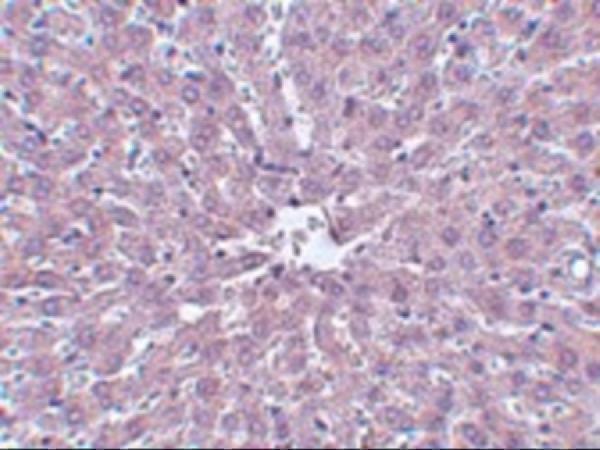
Real IHC data Immunohistochemistry of IRAK in rat liver tissue with IRAK antibody at 5 μg/mL.
Anti-IRAK IRAK1 Monoclonal Antibody [8F1A7]
Cat # M01021-1
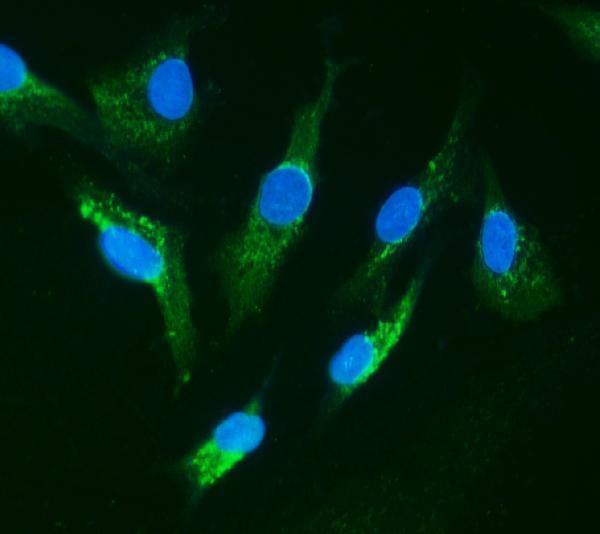
Real IF data IF analysis of IRAK1 using anti-IRAK1 antibody (A01021). IRAK1 was detected in immunocytochemical section of A549 cells. Enzyme antigen retrieval was performed using IHC enzyme antigen retrieval reagent (AR0022) for 15 mins. The cells were blocked with 10% goat serum. And then incubated with 2μg/mL rabbit anti-IRAK1 Antibody (A01021) overnight at 4°C. DyLight®488 Conjugated Goat Anti-Rabbit IgG (BA1127) was used as secondary antibody at 1:100 dilution and incubated for 30 minutes at 37°C. The section was counterstained with DAPI. Visualize using a fluorescence microscope and filter sets appropriate for the label used.
Anti-IRAK/IRAK1 Antibody ®
Cat # A01021
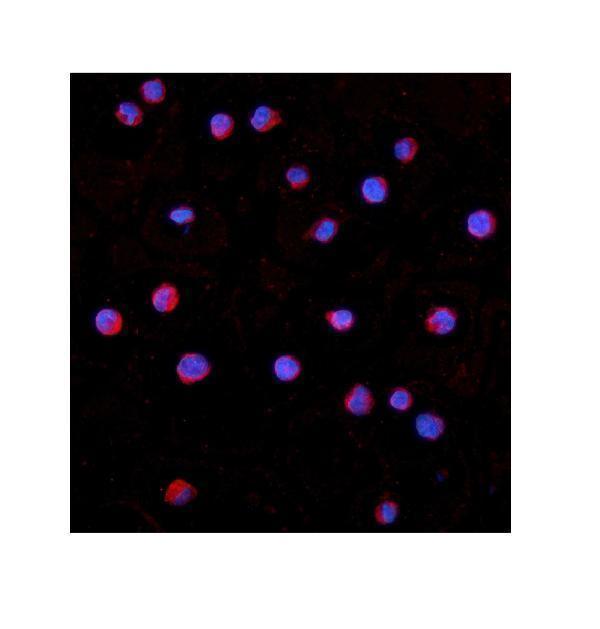
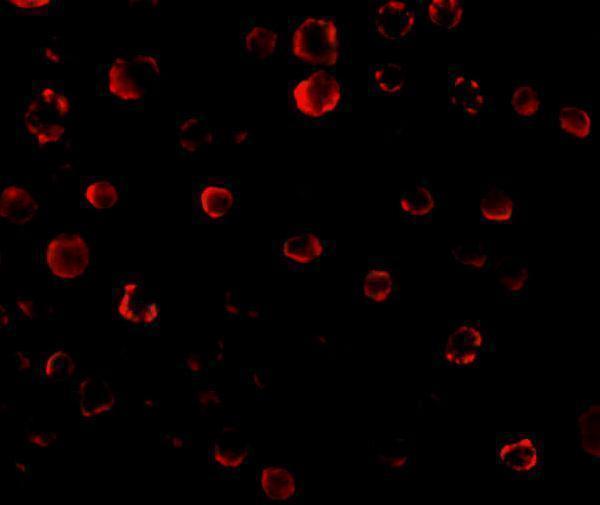
Real IF data Immunofluorescence Validation of IRAK in Human HeLa Cells Immunofluorescent analysis of 4% paraformaldehyde-fixed HeLa Cells labeling IRAK with A01021-2 at 20 μg/mL, followed by goat anti-rabbit IgG secondary antibody at 1/500 dilution (red).
Anti-IRAK IRAK1 Antibody
Cat # A01021-2

A01021-1 has an IHC image of human ovarian cancer paraffin sections, while M01021-1 has an IHC image of rat liver (respective IHC captions). A01021 has an IF image of A549 cells, and A01021-2 has an IF image of paraformaldehyde-fixed HeLa cells (respective IF captions).

Which to pick: For human tissue IHC, choose polyclonal A01021-1: its paraffin-section image uses citrate retrieval at pH 6, but the fixative is unreported (A01021-1 catalog and IHC caption); monoclonal M01021-1 is another IHC-P option with a rat-liver image, although its listed reactivity is Human and Mouse (M01021-1 catalog and IHC caption). For IF/ICC, A01021 has an A549 IF image and A01021-2 has a paraformaldehyde-fixed HeLa IF image (respective catalogs and IF captions). For cross-species planning, A01021-1 lists Human, Mouse and Rat and both IHC and IF applications, but its stated IHC dilution and pictured tissue IHC are specific to human samples (A01021-1 catalog and IHC caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P51617 (IRAK1_HUMAN, Interleukin-1 receptor-associated kinase 1).
  2. Human Protein Atlas. IRAK1 tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. IRAK1 subcellular location (ICC-IF): Mainly localized to the cytosol. In addition localized to the nucleoplasm..
  4. Human Protein Atlas. IRAK1 antibody validation summary (2 antibodies).
  5. RNA-Sequencing Based microRNA Expression Signature of Colorectal Cancer: The Impact of Oncogenic Targets Regulated by miR-490-3p. International journal of molecular sciences 2021 — PMC8469425.
  6. Diagnostic and prognostic roles of IRAK1 in hepatocellular carcinoma tissues: an analysis of immunohistochemistry and RNA-sequencing data from the cancer genome atlas. OncoTargets and therapy 2017 — PMC5367901.
  7. Interleukin-1 receptor-associated kinase-1 is a therapeutic target for gastric cancer. Discover oncology 2025 — PMC12521082.
  8. The role of IRAK1 in breast cancer patients treated with neoadjuvant chemotherapy. OncoTargets and therapy 2019 — PMC6438138.
  9. PubMed PMID:8599092 — UniProt-cited evidence.
  10. PubMed PMID:10723722 — UniProt-cited evidence.
  11. PubMed PMID:11397809 — UniProt-cited evidence.