PCBP2 / Poly(rC)-binding protein 2 · IHC design guide

Design Immunohistochemistry for PCBP2

Plan paraffin-section PCBP2 staining around the reported cytoplasmic tissue pattern (HPA tissue IHC). Score nuclear signal separately in light of UniProt's nuclear localisation and HPA's warning about presumed off-target staining (UniProt; HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for PCBP2 (IHC for PCBP2): expected localisation Cytoplasmic tissue staining (HPA tissue IHC); nuclear localisation also annotated (UniProt), antibody A02425-2, validated IHC image, and IHC protocol steps
Printable PCBP2 IHC protocol sheet — expected localisation Cytoplasmic tissue staining (HPA tissue IHC); nuclear localisation also annotated (UniProt), antibody A02425-2, controls and protocol steps. Open the full PCBP2 IHC guide →

PCBP2 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic tissue staining (HPA tissue IHC); nuclear localisation also annotated (UniProt)
Staining pattern High cytoplasmic staining in hepatocytes (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A02425-2)
Positive control ⓘ Bronchus+4 more · see all
Negative control ⓘ Adipose tissue
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Presumed off-target staining can confound scoring (HPA tissue IHC)
Regulation Stimulus-dependent regulation unreported (UniProt)
Isoform / epitope 8 isoforms; epitope coverage is unspecified (UniProt)
Section 1

Recommended PCBP2 IHC & IF Protocols

The catalog antibody’s IHC-P protocol (datasheet A02425-2) is followed by published PCBP2 IHC methods for melanoma tissue, placental explants, and mouse tissues (PMC10474410; PMC8172583; PMC12914862).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded mouse brain tissue; fixative not specified (datasheet A02425-2)
FixationImage fixative and duration unreported (datasheet A02425-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A02425-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A02425-2)
Primary antibodyRabbit anti-PCBP2, 2-5μg/ml (datasheet A02425-2)
Primary incubationOvernight at 4 °C (datasheet A02425-2)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A02425-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultPCBP2-positive staining in respiratory epithelial cells of bronchus (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic expression. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet A02425-2). The melanoma study used sodium citrate pH 6.0 (PMC10474410).
Section 2

What Is the Expected PCBP2 Staining Pattern?

PCBP2 staining in paraffin sections is expected mainly in the cytoplasm, including respiratory epithelial cells, hepatocytes and kidney tubular cells with high HPA staining (HPA tissue IHC). Nuclear staining can also be plausible because PCBP2 localizes to the nucleus and cytoplasm and may shuttle between them (UniProt Q15366). Interpret this pattern cautiously: HPA rates tissue IHC reliability Approved, reports medium RNA–staining consistency and notes presumed off-target binding (HPA tissue IHC).

What am I looking at on my slide?
Cytoplasmic staining in hepatocytes, kidney tubular cells or respiratory epithelial cells.This matches HPA's general cytoplasmic profile and its High ratings for these cells (HPA tissue IHC). Compare the signal with neighboring cells and the negative control; the HPA rating is an observed pattern, not proof that every stained cell contains PCBP2 (HPA tissue IHC: reliability description).
Cytoplasmic staining with some nuclear staining in the same section.A nuclear component is plausible because PCBP2 is found in both compartments and may shuttle (UniProt Q15366); ICC-IF supports nucleoplasm and cytosol localization (HPA subcellular). Predominantly membrane-bound or extracellular staining lacks support from these localization records (UniProt Q15366; HPA subcellular).
Strong staining in adipocytes or another cell population expected to be negative in the comparison section.HPA reports adipocytes as Not detected, making strong adipocyte staining a specificity warning rather than an expected positive pattern (HPA tissue IHC). Check the negative control and detection reagents; cross-reactivity or endogenous detection activity are possible explanations (standard IHC practice).
Diffuse color across cells, extracellular areas and the section background.A widespread haze does not resemble the reported cellular cytoplasmic pattern (HPA tissue IHC). It can obscure genuine signal; assess blocking, primary antibody concentration, washes and detection background with controls (standard IHC practice). Do not assign a PCBP2 compartment from diffuse color alone.
No detectable staining in a section containing an HPA High cell population.Absence of signal in a selected positive control, such as hepatocytes or kidney tubular cells, makes the run difficult to interpret (HPA tissue IHC: High). Check section quality, retrieval, antibody and detection controls before treating a test section as PCBP2-negative (standard IHC practice).
💡Expected PCBP2 appearanceCall a result consistent when HPA High cell populations show clear, predominantly cytoplasmic staining, with possible nuclear signal (HPA tissue IHC; UniProt Q15366); strong adipocyte or membrane-only staining warrants investigation (HPA tissue IHC: adipocytes Not detected; UniProt Q15366 topology).
How each factor affects the staining
Which tissue provides an interpretable positive comparison?HPA rates hepatocytes, kidney tubular cells, Purkinje cells and several epithelial populations High; choose a section containing an identified High population (HPA tissue IHC). Adipocytes are reported Not detected and offer a tissue-level contrast (HPA tissue IHC).
How certain is the tissue pattern?HPA labels tissue IHC Approved but reports medium consistency with RNA data, possible recognition of protein from more than one gene and presumed off-target binding (HPA tissue IHC). Treat an unexpected cell pattern as a finding to verify, not as established PCBP2 distribution.
Does PCBP2 require a membrane or secreted-protein pattern?PCBP2 has no transmembrane segment or signal peptide and is recorded as one chain spanning residues 1–365 (UniProt Q15366 topology and processing). A membrane-only rim or extracellular deposit therefore has no support as the expected localization.
Could isoforms affect antibody interpretation?UniProt lists 8 PCBP2 isoforms (UniProt Q15366). The supplied record gives no antibody epitope or isoform coverage, so a difference between specimens cannot be assigned to a particular isoform from staining alone.
What should IF/ICC show?HPA supports signal in the nucleoplasm and cytosol and lists images from A-431, U-251MG and U2OS cells (HPA subcellular). This supports a compartment comparison; the IF/ICC workflow belongs to its own guide.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
A known-positive section has no chromogenic signal.The run may have failed at section preparation, retrieval, primary antibody incubation or detection (standard IHC practice); HPA reports High staining in hepatocytes and kidney tubular cells (HPA tissue IHC).Confirm that the expected cells are present, then inspect the positive control and each workflow step (standard IHC practice). Do not score other sections as negative until the control yields interpretable staining.
Signal is confined to membranes or extracellular material.That distribution conflicts with the reported cellular compartments and absence of a transmembrane segment (HPA tissue IHC; UniProt Q15366 topology). Nonspecific staining or detection background is possible (standard IHC practice).Compare a known-positive section and negative control, then reassess blocking, washes and detection background (standard IHC practice). Retain a PCBP2 call only where a supported cellular pattern is visible.
Adipocytes stain strongly.HPA records adipocytes as Not detected, while warning of presumed off-target binding in tissue IHC (HPA tissue IHC). Cross-reactivity or endogenous detection activity may also produce misleading color (standard IHC practice).Check a no-primary control and the cellular distribution in the same section (standard IHC practice). If the signal persists without primary antibody, investigate the detection system before interpreting adipocyte staining.
The whole section has diffuse brown haze.Widespread background can arise from incomplete blocking, excessive primary antibody or insufficient washing (standard IHC practice); it does not match HPA's general cytoplasmic profile (HPA tissue IHC).Review the no-primary control, blocking and wash steps, and titrate the primary antibody as needed (standard IHC practice). Reassess the cell-specific pattern only after the background is controlled.
Nuclei stain along with cytoplasm.Nuclear signal is biologically plausible: UniProt places PCBP2 in the nucleus and cytoplasm, and HPA supports nucleoplasm and cytosol by ICC-IF (UniProt Q15366; HPA subcellular).Check that staining remains cellular and that controls are clean (standard IHC practice). Record nuclear and cytoplasmic components separately; do not discard a section solely because nuclei stain.
An unexpected cell population stains in one specimen.HPA's tissue observations do not establish every cell type's status, and its Approved rating includes a warning about presumed off-target binding (HPA tissue IHC). A single unusual pattern is therefore uncertain.Compare with HPA's reported positive and Not detected populations, inspect controls and repeat with an independently validated antibody if available (HPA tissue IHC; standard IHC practice). Report the unusual pattern as unverified until specificity is supported.

Sample controls for PCBP2 IHC & IF

🧪Run kidney first: tubular cells must stain because HPA rates them High (HPA: kidney, cells in tubules). Run adipose tissue as the negative tissue; adipocytes are Not detected (HPA: adipose tissue). Any unstained cells within the kidney section should show background only, but the supplied HPA row does not identify a specific internal negative cell type (HPA: kidney, cells in tubules).
Positive control tissue: Bronchus (Respiratory epithelial cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show PCBP2 in A-431, U-251MG, U2OS, with annotated localisation: Nucleoplasm (supported), Cytosol (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control, a rabbit IgG isotype control matched to the primary antibody’s format, and knockout tissue if available (selected caption: rabbit primary; standard IHC practice). For the biotin-based DAB method, quench endogenous peroxidase and check for endogenous biotin in kidney tubules, which can produce background (selected caption: biotinylated secondary and SABC–DAB; standard IHC practice).
⚠️Feasibility: The selected-SKU caption reports heat retrieval in EDTA at pH 8.0 for a paraffin-embedded mouse brain section, but its fixative is unreported; no target-specific fixation window or fixation effect is reported (selected caption: A02425-2). That retrieval condition is a starting point for kidney IHC, not an established kidney requirement (selected caption: mouse brain; HPA: kidney). The supplied evidence does not establish that frozen sections or IF are easier; endogenous biotin in kidney tubules warrants particular attention with the caption’s biotin-based detection method (selected caption: SABC–DAB; standard IHC practice).

HPA tissue IHC evidence for PCBP2

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data. Caution, targets protein from more than one gene. Presumed off target binding observed and disregarded.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →
Cerebellum Purkinje cells High Protein (IHC) HPA →
Kidney Cells in tubules High Protein (IHC) HPA →
Liver Hepatocytes High Protein (IHC) HPA →
Nasopharynx Respiratory epithelial cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Section 3

Advanced PCBP2 IHC Tips

Troubleshoot PCBP2 staining by checking retrieval, specimen handling, compartment, and controls before comparing signal across sections.

Which retrieval condition should I start with for paraffin section PCBP2 IHC?
Start with heat mediated retrieval in EDTA at pH 8.0 for paraffin sections (datasheet A02425-2). The catalog antibody produced a mouse brain IHC image after that retrieval, followed by 10% goat serum blocking and overnight primary incubation at 4°C (datasheet A02425-2). If staining is weak, first check heating consistency, section attachment, and reagent exposure before testing another retrieval condition on adjacent sections (standard IHC practice). Keep retrieval duration and detection settings identical across comparison sections, and include a no primary control to distinguish recovered signal from background (standard IHC practice).
How should I assess whether fixation is limiting PCBP2 staining?
Target specific fixation sensitivity is unknown: the catalog mouse brain caption identifies paraffin sections but does not report a fixative (datasheet A02425-2). Record the fixative and fixation duration for each specimen, then compare similarly processed sections using the same EDTA pH 8.0 retrieval (datasheet A02425-2; standard IHC practice). If signal differs, assess tissue morphology and run a no primary control before attributing the difference to PCBP2 epitope loss (standard IHC practice). Compare matched fixation conditions experimentally; neither tissue staining patterns nor protein features establish how this antibody responds to fixation (standard IHC practice).
Should a convincing PCBP2 stain be nuclear or cytoplasmic?
Assess both nuclear and cytoplasmic staining: PCBP2 is reported in the nucleus and cytoplasm and may shuttle between them (UniProt Q15366). Nucleoplasm and cytosol are supported locations in cell imaging, while tissue IHC has a general cytoplasmic profile (HPA subcellular; HPA tissue IHC). Score the compartments separately in intact cells, using the counterstain to define nuclei and consistent DAB exposure to compare sections (standard IHC practice). Treat a compartment shift as a finding to verify with controls and matched processing, rather than assigning a biological cause from location alone (standard IHC practice).
How can isoforms or epitope accessibility affect the IHC result?
PCBP2 has 8 reported isoforms and 3 KH domains, so epitope coverage depends on which sequence the antibody recognizes (UniProt Q15366). Do not assume that this IHC signal represents every isoform unless the immunogen sequence and isoform sequences establish shared recognition (UniProt Q15366; standard IHC practice). Compare the stated epitope, if available, with the isoforms before interpreting differences between specimens, and keep EDTA pH 8.0 retrieval consistent (datasheet A02425-2; standard IHC practice). PCBP2 also has reported phosphoserines, but their presence alone does not establish a fixation or retrieval effect for this antibody (UniProt Q15366; standard IHC practice).
How should I use IF to check the cell source of an IHC signal?
On the separate IF/ICC workflow, multiplex PCBP2 with an independently validated Purkinje cell marker when examining cerebellum, where Purkinje cells show high tissue staining (HPA tissue IHC). Choose a fluorophore whose signal can be separated from specimen autofluorescence, and inspect single color and no primary controls before interpreting overlap (standard IF practice). PCBP2 has no transmembrane segment and is reported in nucleoplasm and cytosol, so use controlled permeabilisation to access intracellular epitopes (UniProt Q15366; HPA subcellular; standard IF practice). Compare cell identity and compartment with chromogenic IHC, while treating the two detection methods as separate validation contexts (standard IHC/IF practice).
What controls help separate PCBP2 staining from chromogenic background?
Run a no primary section through secondary antibody and DAB development to reveal detection background, and inspect tissue edges and damaged areas separately (standard IHC practice). The catalog image used 10% goat serum blocking, a biotinylated secondary, streptavidin biotin detection, and DAB, making matched reagent controls useful (datasheet A02425-2). Include an endogenous peroxidase block and assess whether endogenous biotin contributes signal when using this detection chemistry (standard IHC practice). Reduce excessive primary or detection exposure only after controls identify the background source; keep changes consistent across comparison sections (standard IHC practice).
How should I quantify PCBP2 staining across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, because PCBP2 can occur in nucleus and cytoplasm (UniProt Q15366). Use percent positive cells with a fixed positivity threshold, or an H-score based on the fraction of cells at each intensity; report nuclear and cytoplasmic results separately (standard IHC practice). Normalise counts to evaluable cells in the same annotated region, or report positive cell density per mm² of viable tissue when cell counts are impractical (standard IHC practice). Keep retrieval, DAB development, imaging, and threshold settings matched, and exclude folds and necrosis consistently (standard IHC practice).
How can I distinguish credible PCBP2 signal from an artefact?
Look for reproducible staining in intact cells with plausible nuclear or cytoplasmic location, since both compartments are reported for PCBP2 (UniProt Q15366; HPA subcellular). Respiratory epithelial cells in bronchus and Purkinje cells in cerebellum have high reported tissue staining, while adipocytes were not detected in the cited tissue survey (HPA tissue IHC). Check whether apparent positivity tracks section edges, necrosis, or the no primary control, which can reveal preparation or detection artefacts (standard IHC practice). Interpret cell patterns cautiously because the tissue reference notes presumed off target binding and only medium agreement with RNA expression (HPA tissue IHC).
Boster reagents

Best PCBP2 / Poly(rC)-binding protein 2 IHC Antibodies

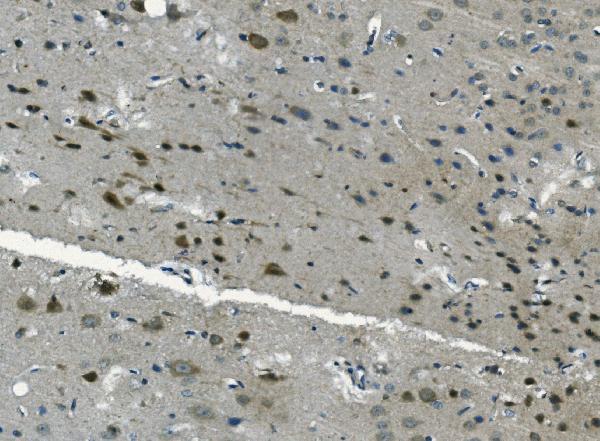
Anti-PCBP2 antibodies have IHC images from paraffin sections of mouse and rat brain and human ovarian and pancreatic cancer tissue (A02425-2 IHC captions), plus IF/ICC images from PC-3 and Caco-2 cells (A02425-3 and M02425 IF captions).

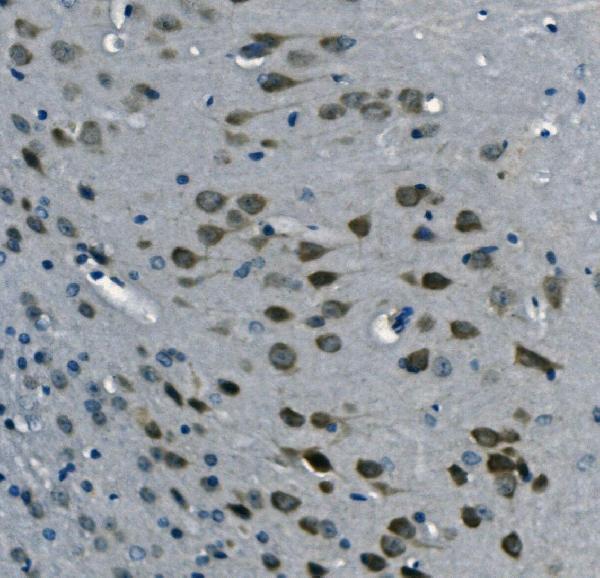
Real IHC data IHC analysis of PCBP2/hnRNP E2 using anti-PCBP2/hnRNP E2 antibody (A02425-2). PCBP2/hnRNP E2 was detected in paraffin-embedded section of mouse brain tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2μg/ml rabbit anti-PCBP2/hnRNP E2 Antibody (A02425-2) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-PCBP2/hnRNP E2 Antibody ®
Cat # A02425-2
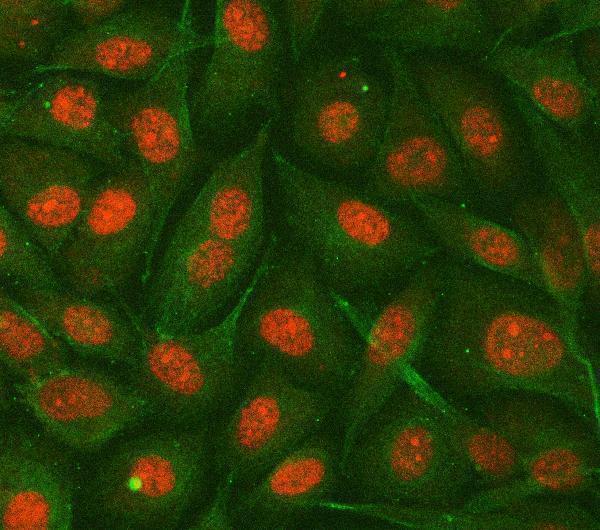
Real IF data IF analysis of hnRNP E2/PCBP2 using anti-hnRNP E2/PCBP2 antibody (A02425-3) and anti-Tubulin Alpha antibody (M03989-3). hnRNP E2/PCBP2 was detected in immunocytochemical section of PC-3 cell. Enzyme antigen retrieval was performed using IHC enzyme antigen retrieval reagent (AR0022) for 15 mins. The cells were blocked with 10% goat serum. And then incubated with 5 μg/mL rabbit anti-hnRNP E2/PCBP2 Antibody (A02425-3) and mouse anti-Tubulin Alpha antibody (M03989-3) overnight at 4°C. Cy3 Conjugated Goat Anti-Rabbit IgG (BA1032) and DyLight®488 Conjugated Goat Anti-Mouse IgG (BA1126) were used as secondary antibody at 1:500 dilution and incubated for 30 minutes at 37°C. Visualize using a fluorescence microscope and filter sets appropriate for the label used.
Anti-hnRNP E2/PCBP2 Antibody ®
Cat # A02425-3
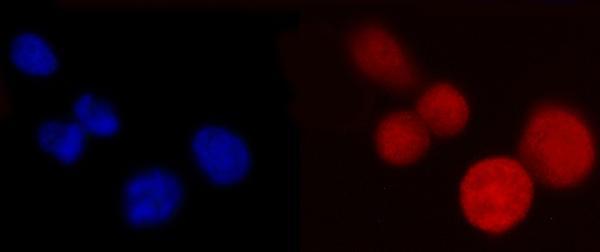
Real IF data IF analysis of PCBP2/hnRNP E2 using anti-PCBP2/hnRNP E2 antibody (M02425). PCBP2/hnRNP E2 was detected in an immunocytochemical section of Caco-2 cells. Enzyme antigen retrieval was performed using IHC enzyme antigen retrieval reagent (AR0022) for 15 mins. The cells were blocked with 10% goat serum. And then incubated with 5 μg/mL mouse anti-PCBP2/hnRNP E2 Antibody (M02425) overnight at 4°C. DyLight®594 Conjugated Goat Anti-Mouse IgG (BA1141) was used as secondary antibody at 1:100 dilution and incubated for 30 minutes at 37°C. The section was counterstained with DAPI. Visualize using a fluorescence microscope and filter sets appropriate for the label used.
Anti-PCBP2/hnRNP E2 Antibody ® (monoclonal, 4B9C7)
Cat # M02425

A02425-2 is listed for IHC and shown on paraffin sections of mouse and rat brain and human ovarian and pancreatic cancer tissue (catalog applications; A02425-2 IHC captions). A02425-3 is listed for IF/ICC and shown in PC-3 cells; M02425 is listed for IF/ICC and shown in Caco-2 cells (catalog applications; respective IF captions).

Which to pick: Choose A02425-2 for chromogenic tissue IHC: it is a rabbit antibody listed for IHC in human, mouse and rat, with paraffin-section images from all three species; the fixative is unreported (catalog host, applications and reactivity; A02425-2 IHC captions). For IF/ICC, choose rabbit A02425-3 for the documented PC-3 cell example or mouse monoclonal M02425, clone 4B9C7, for the documented Caco-2 cell example (catalog host, clone and applications; respective IF captions). For cross-species paraffin-section IHC, A02425-2 has image evidence in human, mouse and rat tissue, whereas the supplied IF/ICC images for A02425-3 and M02425 each show one cell model (respective image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q15366 (PCBP2_HUMAN, Poly(rC)-binding protein 2).
  2. Human Protein Atlas. PCBP2 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. PCBP2 subcellular location (ICC-IF): Localized to the nucleoplasm and cytosol..
  4. Human Protein Atlas. PCBP2 antibody validation summary (2 antibodies).
  5. Specific enrichment of the RNA-binding proteins PCBP1 and PCBP2 in chief cells of the murine gastric mucosa. Gene expression patterns : GEP 2014 — PMC4008318.
  6. MiR-5195-3p targets the PCBP2/PI3K/AKT pathway to inhibit melanoma cell proliferation and migration. Heliyon 2023 — PMC10474410.
  7. Knockdown of Splicing Complex Protein PCBP2 Reduces Extravillous Trophoblast Differentiation Through Transcript Switching. Frontiers in cell and developmental biology 2021 — PMC8172583.
  8. PCBP2 inhibits antiviral innate immune responses via the MAVS-mediated signaling pathway in severe fever with thrombocytopenia syndrome. Virus research 2026 — PMC12914862.
  9. PubMed PMID:7607214 — UniProt-cited evidence.
  10. PubMed PMID:14702039 — UniProt-cited evidence.
  11. PubMed PMID:16541075 — UniProt-cited evidence.