This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan PPM1K staining in paraffin sections using the general cytoplasmic tissue pattern as a reference (HPA tissue IHC). Breast glandular cells and ovarian follicle cells show high staining, while liver cholangiocytes are undetected (HPA tissue IHC); start the catalog antibody at 1:100–1:300 (datasheet: IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasm observed (HPA tissue IHC); mitochondrial matrix expected (UniProt) | |
| Staining pattern | Cytoplasmic staining across tissue cell types (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Breast+4 more · see all | |
| Negative control | Liver |
| Fixation | Keep fixation consistent across sections. (standard IHC practice; not target-specific) | |
| Caveat | Moderate staining–RNA agreement; verify specificity (HPA tissue IHC) | |
| Regulation | Refeeding raises the BCKDK:PPM1K ratio (UniProt) | |
| Isoform / epitope | 3 isoforms; verify antibody epitope coverage (UniProt) |
The catalog antibody’s IHC-P protocol is accompanied by three published chromogenic PPM1K IHC protocols (PMC12254316; PMC10495377; PMC13066379).
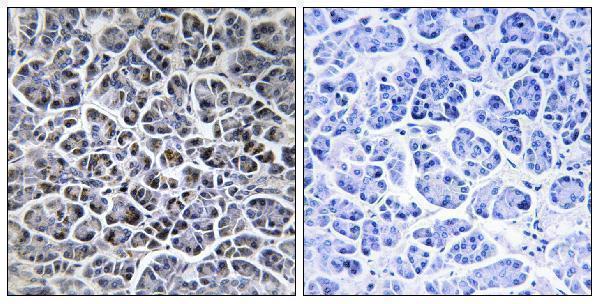
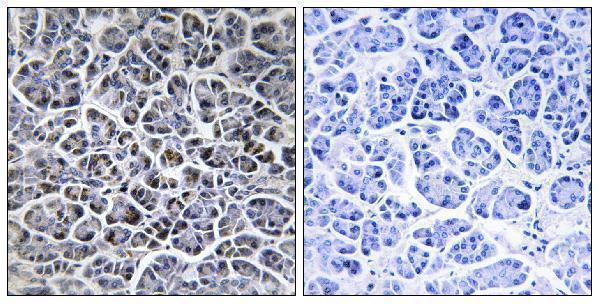
| Sample | Paraffin-embedded human pancreas tissue; fixative not specified (datasheet A04319) |
| Fixation | Image fixative and duration unreported (datasheet A04319); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-PPM1K, 1:100-1:300 (datasheet A04319) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | PPM1K-positive staining in glandular cells of breast (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic expression in all tissues. No signal in the no-primary control. |
PPM1K is assigned to the mitochondrial matrix, with cytosolic detection also reported in liver cells (UniProt Q8N3J5: subcellular location). In paraffin tissue sections, expect cytoplasmic staining, including strong staining in breast glandular cells and ovarian follicle cells (HPA: tissue IHC). The protein has no transmembrane segment (UniProt Q8N3J5: topology). HPA rates the tissue staining Approved, with medium agreement with RNA data and external verification pending (HPA: tissue IHC reliability).
| Distinct cytoplasmic chromogen in breast glandular cells or ovarian follicle cells. | This fits the reported High staining in those cells (HPA: tissue IHC). At light microscope resolution, a cytoplasmic pattern is compatible with mitochondrial matrix localisation; the tissue stain alone does not prove mitochondrial identity (UniProt Q8N3J5: subcellular location; HPA: tissue IHC profile). |
| Predominantly nuclear or sharply plasma membrane restricted staining. | Treat this as a compartment mismatch requiring investigation: PPM1K is assigned to the mitochondrial matrix and has no transmembrane segment (UniProt Q8N3J5: subcellular location and topology). Compare with a known positive section and detection controls before calling the pattern specific (general IHC practice). |
| Strong staining of liver cholangiocytes. | HPA reports PPM1K as Not detected in cholangiocytes (HPA: liver tissue IHC). Unexpected signal raises concern for cross-reactivity or endogenous detection activity; it does not establish either cause by itself (general IHC interpretation). Do not treat the whole liver as a negative control. |
| Diffuse chromogen across cells and surrounding tissue, with little cellular distinction. | This does not match the reported general cytoplasmic expression pattern (HPA: tissue IHC profile). Review the no-primary control and staining conditions for background from detection chemistry or excessive antibody signal before scoring individual cells (general IHC practice). |
| No staining in breast glandular cells or ovarian follicle cells. | Both are reported High by HPA, so an entirely blank expected-positive compartment makes this run difficult to interpret (HPA: tissue IHC). Check that the positive control stained and review reagent, retrieval and detection steps (general IHC practice). HPA's Approved rating still has external verification pending (HPA: reliability). |
| Tissue and cell selection | Use breast glandular cells and ovarian follicle cells as expected High staining examples; adrenal glandular cells and bronchial respiratory epithelial cells are reported Medium (HPA: tissue IHC). Score the named cell population, since a tissue-wide average can hide a cell-specific mismatch (general IHC practice). |
| Negative comparison | Liver cholangiocytes are reported Not detected, while HPA describes general cytoplasmic expression across tissues (HPA: tissue IHC). They offer a cell-specific comparison, not evidence that every liver cell should be blank. UniProt also reports cytosolic detection in liver cells (UniProt Q8N3J5: subcellular location). |
| Antibody validation | HPA lists IHC as Approved for HPA020862 and HPA023891; its tissue profile has medium agreement with RNA data and awaits external verification (HPA: antibody validation and tissue reliability). Interpret a matching pattern as support for the result, while using controls to assess the particular IHC-validated antibody and run (general IHC practice). |
| Processing and epitope coverage | UniProt lists a processed chain spanning residues 30–372 and three isoforms (UniProt Q8N3J5: processing and isoforms). No antibody epitope is supplied, so coverage of the processed protein or each isoform cannot be inferred. Do not explain a staining difference by epitope loss without antibody-specific evidence. |
| IF/ICC Q: What localisation should an IF image show? | A: HPA reports supported mitochondrial localisation in ICC-IF images from A-431, U-251MG and U2OS (HPA: subcellular ICC-IF). This supports a mitochondrial expectation for IF interpretation, but the ICC-supported antibody HPA020066 has no IHC status listed; its validation does not transfer to an IHC run (HPA: antibody validation). |
| Situation | Likely cause | Next action |
|---|---|---|
| Expected-positive glandular or follicle cells are blank. | The run may have failed to reveal a signal expected to be High in those cells (HPA: tissue IHC); the staining pattern alone does not identify which workflow step failed. | Confirm staining on the positive control, then review the IHC-validated antibody's specified conditions, retrieval and detection reagents in the run record (general IHC practice). |
| Nuclei dominate the stain. | A nuclear dominant pattern conflicts with mitochondrial matrix localisation (UniProt Q8N3J5: subcellular location); nonspecific signal is a possibility, not a diagnosis. | Compare the pattern with breast glandular or ovarian follicle cells and a no-primary control; reassess specificity before scoring nuclei as PPM1K (HPA: tissue IHC; general IHC practice). |
| Liver cholangiocytes stain strongly. | This conflicts with their Not detected HPA result; cross-reactivity or endogenous detection activity could contribute (HPA: liver tissue IHC; general IHC practice). | Compare adjacent liver cell populations, inspect no-primary and detection controls, and record the discrepancy as cell-specific rather than declaring the liver positive or negative as a whole (general IHC practice). |
| Most of the section has diffuse colour. | Broad background obscures the cellular cytoplasmic pattern reported by HPA (HPA: tissue IHC profile). Detection background or overly strong staining can produce this appearance (general IHC practice). | Review the no-primary control, blocking, washing, antibody dilution and chromogen development for this run before assigning cell scores (general IHC practice). |
| A mitochondrial pattern is clear by IF but IHC looks broadly cytoplasmic. | HPA reports supported mitochondrial ICC-IF localisation and a general cytoplasmic tissue IHC profile (HPA: subcellular ICC-IF and tissue IHC). The two image types report localisation at different visual detail. | Judge the paraffin section against the reported cytoplasmic cell pattern; use the IF observation as supporting context, while checking each antibody's application-specific validation (HPA: antibody validation; general IHC practice). |
| Heart muscle is chosen as the sole expected strong protein control. | HPA calls PPM1K RNA tissue enhanced in heart muscle, but that RNA label does not specify a High heart muscle IHC staining level (HPA: RNA specificity and tissue IHC). | Include a reported High IHC cell population, such as breast glandular or ovarian follicle cells, when assessing whether the stain worked (HPA: tissue IHC). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Breast | Glandular cells | High | Protein (IHC) | HPA → |
| Ovary | Follicle cells | High | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | Medium | Protein (IHC) | HPA → |
| Appendix | Glandular cells | Medium | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Liver | Cholangiocytes | Not detected | Protein (IHC) | HPA → |
Troubleshoot PPM1K staining in paraffin sections by checking retrieval, controls and the expected cellular pattern before comparing signal across samples.
Both anti-PPM1K antibodies have human pancreas paraffin-section IHC images (catalog image captions) and list IF plus Human, Mouse and Rat reactivity (catalog applications and reactivity); no IF image is supplied (catalog image fields).
A04319 lists IHC and IF for Human, Mouse and Rat (catalog applications and reactivity), with an IHC image of paraffin-embedded human pancreas tissue and peptide blocking (A04319 image caption). A04319-1 also lists ICC (catalog applications) and has its own IHC image of paraffin-embedded human pancreas tissue with peptide blocking (A04319-1 image caption).
Which to pick: For tissue IHC, either SKU has its own paraffin-section human pancreas example (A04319 image caption; A04319-1 image caption); the fixative is unreported in both captions. For ICC, choose A04319-1 because ICC is listed for that SKU (A04319-1 applications); for IF, both list IF, with no IF image supplied for either (catalog applications and image fields). For Human, Mouse or Rat samples, both list reactivity in those species (catalog reactivity), while the supplied IHC images document human pancreas only (A04319 image caption; A04319-1 image caption).