PTRH2 / Peptidyl-tRNA hydrolase 2, mitochondrial · IHC design guide

Design Immunohistochemistry for PTRH2

Plan chromogenic PTRH2 IHC-P around granular cytoplasmic tissue staining (HPA tissue IHC) and its expected outer mitochondrial membrane location (UniProt). Start the IHC-validated antibody at 10 μg/mL (datasheet: A02459-1), using adrenal glandular cells as a positive reference and adipocytes as a low-signal comparison (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for PTRH2 (IHC for PTRH2): expected localisation Granular cytoplasm (HPA tissue IHC); outer mitochondrial membrane expected (UniProt), antibody A02459-1, validated IHC image, and IHC protocol steps
Printable PTRH2 IHC protocol sheet — expected localisation Granular cytoplasm (HPA tissue IHC); outer mitochondrial membrane expected (UniProt), antibody A02459-1, controls and protocol steps. Open the full PTRH2 IHC guide →

PTRH2 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Granular cytoplasm (HPA tissue IHC); outer mitochondrial membrane expected (UniProt)
Staining pattern Many cell types show granular cytoplasmic staining (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Adipose tissue
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A02459-1)
Caveat Adipocytes are undetected despite broad tissue staining (HPA tissue IHC)
Regulation No expression regulator annotated (UniProt)
Isoform / epitope No annotated isoforms; chain spans residues 1–179 (UniProt)
Section 1

Recommended PTRH2 IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol with a published PTRH2 protocol for FFPE human heart sections (PMC12852877).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleTissue sections; selected-image fixative not specified (standard IHC workflow)
FixationImage fixative and duration unreported (datasheet A02459-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-PTRH2, 10 μg/mL (datasheet A02459-1)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultPTRH2-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Ubiquitous cytoplasmic expression with a granular pattern. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 HIER at 95–98 °C for 20 min (page antigen retrieval); the heart protocol also uses citrate pH 6.0 (PMC12852877).
Section 2

What Is the Expected PTRH2 Staining Pattern?

PTRH2 is an outer mitochondrial membrane protein with a transmembrane segment at residues 15–37 (UniProt Q9Y3E5 topology). In paraffin-section IHC, expect granular cytoplasmic staining across many cell types (HPA tissue IHC: ubiquitous granular cytoplasmic profile). HPA rates the tissue pattern Supported, with medium consistency between staining and RNA expression (HPA tissue IHC: reliability). Interpret individual cells in their tissue context.

What am I looking at on my slide?
Granular cytoplasmic staining in adrenal glandular cells, bronchial respiratory epithelium, or marrow hematopoietic cells.This fits the reported pattern: each listed population stains High (HPA tissue IHC). Cytoplasmic granules are consistent with mitochondrial localization (HPA ICC-IF: mitochondria; UniProt Q9Y3E5: outer mitochondrial membrane). Chromogenic IHC alone cannot resolve the outer membrane (standard IHC practice).
Predominantly nuclear, surface-rim, or uniformly diffuse staining replaces the granular cytoplasmic pattern.Treat this as a localization mismatch, especially when the expected granules are absent (HPA tissue IHC: granular cytoplasmic profile; UniProt Q9Y3E5: outer mitochondrial membrane). Review staining specificity and detection conditions before scoring it as PTRH2 (standard IHC practice).
Strong staining appears chiefly in adipocytes or soft-tissue fibroblasts while expected positive cells are weak.Adipocytes are Not detected and fibroblasts are reported at low staining (HPA tissue IHC). Consider cross-reactivity or endogenous chromogen-generating activity (standard IHC practice). These findings warrant investigation rather than an automatic negative call for the whole section.
Broad, smooth color covers cells and extracellular areas, obscuring cell boundaries or granules.This is difficult to reconcile with the reported granular cytoplasmic profile (HPA tissue IHC). Compare with a reagent-omission control and inspect blocking, washes, and detection background (standard IHC practice); do not score the haze as cellular PTRH2.
No cellular signal appears in a section containing a reported high-staining population.An absent signal in bronchial respiratory epithelium, for example, conflicts with its High HPA observation (HPA tissue IHC). Check section quality, reagent performance, retrieval, and detection controls (standard IHC practice). HPA's Supported rating is not a guarantee for every specimen.
💡Expected PTRH2 appearanceCall a convincing positive when discrete cytoplasmic granules appear in reported high-staining cells, such as adrenal glandular cells or bronchial respiratory epithelial cells (HPA tissue IHC), consistent with mitochondrial localization (HPA ICC-IF; UniProt Q9Y3E5); dominant nuclear color or diffuse haze instead calls for review (standard IHC practice).
How each factor affects the staining
Compartment and optical resolutionPTRH2 has one annotated transmembrane segment at 15–37 and localizes to the outer mitochondrial membrane (UniProt Q9Y3E5). Expect cytoplasmic granularity in chromogenic sections (HPA tissue IHC); do not infer membrane sidedness from it (standard IHC practice).
Tissue and cell contextHPA reports low tissue specificity by RNA and a ubiquitous granular cytoplasmic IHC profile (HPA tissue IHC). Its examples still differ: marrow hematopoietic cells stain High, soft-tissue fibroblasts low, and adipocytes are Not detected (HPA tissue IHC).
Antibody evidenceThe listed antibody HPA012897 has Supported IHC and ICC status (HPA antibodies). The tissue profile has medium staining-to-RNA consistency (HPA tissue IHC: reliability). Use both observations when judging an unexpected pattern; neither establishes specificity in every specimen.
IF/ICC Q&A: Where should the signal appear?In IF/ICC, expect mitochondrial localization (HPA subcellular: supported mitochondria). HPA lists images from U2OS and sperm (HPA subcellular). This corroborates compartment interpretation; it does not prescribe an IF protocol or establish IHC intensity in those samples.
Processing and fixation evidenceUniProt annotates a 1–179 chain, with no signal peptide, propeptide, glycosylation sites, or isoforms in this record (UniProt Q9Y3E5). These annotations do not predict retrieval needs or fixation sensitivity; no target-specific fixation effect is supplied.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
High-staining reference cells show no signal.The IHC run may have failed, or the chosen section may lack an intact reference population (standard IHC practice).Confirm the cell population is present; inspect a run control, antibody dilution, retrieval record, and detection steps (standard IHC practice). Use a reported high-staining population as a reference (HPA tissue IHC).
Nuclear color dominates while cytoplasmic granules are absent.The compartment conflicts with mitochondrial localization (HPA ICC-IF; UniProt Q9Y3E5) and may reflect nonspecific staining (standard IHC practice).Compare with a reagent-omission control and reassess antibody concentration and detection background (standard IHC practice). Score PTRH2 only where cellular staining fits the reported granular profile (HPA tissue IHC).
Adipocytes stain strongly.This differs from Not detected adipocytes (HPA tissue IHC); cross-reactivity or endogenous detection activity is possible (standard IHC practice).Check the relevant detection control and chromogen background, then compare adjacent reported positive cells in the same run (standard IHC practice; HPA tissue IHC).
A uniform brown haze prevents cell-level scoring.Diffuse background can obscure the granular cytoplasmic pattern (standard IHC practice; HPA tissue IHC).Inspect reagent-omission controls, blocking, washes, and detection development; repeat only after the background source is identified (standard IHC practice).
Only faint staining appears in soft-tissue fibroblasts.Low staining is reported for this population (HPA tissue IHC), so weak signal alone does not show that the run failed.Judge the run against a reported high-staining population and its controls, then score fibroblasts separately (HPA tissue IHC; standard IHC practice).
Granules are visible, but their exact mitochondrial membrane position is uncertain.Chromogenic section resolution limits membrane-level localization (standard IHC practice), although mitochondrial localization is supported (HPA ICC-IF; UniProt Q9Y3E5).Report granular cytoplasmic IHC staining (HPA tissue IHC). Consult the separate IF/ICC guide for compartment-level assessment (HPA subcellular: supported mitochondria).

Sample controls for PTRH2 IHC & IF

🧪Run adrenal gland first and score glandular cells, where PTRH2 staining is High (HPA: adrenal gland, glandular cells High). Run adipose tissue as the negative tissue, focusing on adipocytes (HPA: adipose tissue, adipocytes Not detected); on the adrenal slide, treat morphologically distinct cells without specific signal as internal negatives only after checking their staining, since the supplied HPA row does not establish their PTRH2 status.
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show PTRH2 in U2OS, Sperm, with annotated localisation: Mitochondria (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control; an isotype control matched to the primary antibody’s host species, immunoglobulin class and concentration; and a PTRH2 knockout or immunizing-peptide block as a biological specificity control (standard IHC practice). For chromogenic adrenal sections, quench endogenous peroxidase and check for endogenous biotin if using avidin–biotin detection (standard IHC practice).
⚠️Feasibility: No target-specific fixation window or antigen-retrieval dependency is reported in the supplied evidence; the selected A02459-1 tissue-IHC caption does not state a fixative (A02459-1 caption). The evidence does not establish whether frozen sections or IF are easier, although ICC-IF images support mitochondrial localization (HPA: subcellular, mitochondria supported). No adrenal-specific staining artifact is reported in the supplied evidence (HPA: adrenal gland row; A02459-1 caption).

HPA tissue IHC evidence for PTRH2

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Glandular cells High Protein (IHC) HPA →
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Breast Glandular cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Section 3

Advanced PTRH2 IHC Tips

Troubleshoot PTRH2 staining by checking retrieval, compartment, cell type and controls before comparing chromogenic IHC scores across sections.

How should I retrieve PTRH2 in paraffin sections when staining is weak?
Start with citrate buffer at pH 6.0, heated to 95–98 °C for 20 minutes for PTRH2 IHC (page retrieval rule). Let sections cool consistently, then compare the same antibody dilution and detection conditions across runs so retrieval remains the variable being tested (standard IHC practice). If staining remains weak, test an alternative retrieval buffer on matched sections as a fallback, recording its pH and heating time rather than assuming it is superior (standard IHC practice). Evaluate whether staining becomes granular and cytoplasmic, as expected from tissue staining, while checking for tissue damage or stronger diffuse background (HPA tissue IHC; standard IHC practice).
Can fixation explain inconsistent PTRH2 staining between paraffin blocks?
PTRH2-specific sensitivity to fixation is unknown from the supplied evidence; the selected small-intestine IHC caption reports 10 µg/mL antibody but does not state its fixative (A02459-1 tissue-IHC caption). Record each block’s fixative, fixation duration and processing history before attributing a difference in staining to antigen loss (standard IHC practice). Run matched sections from the blocks together with identical retrieval, antibody incubation and chromogenic detection, then inspect morphology and staining side by side (standard IHC practice). Treat staining differences as provisional until repeat sections and an appropriate positive control show the same pattern, because fixation effects cannot be assigned specifically to PTRH2 here (standard IHC practice; A02459-1 tissue-IHC caption).
What staining pattern should count as plausible PTRH2 localisation?
Expect predominantly granular cytoplasmic staining in tissue sections, consistent with the reported PTRH2 tissue pattern and mitochondrial localisation (HPA tissue IHC; HPA subcellular). PTRH2 is annotated on the mitochondrial outer membrane with a transmembrane segment at residues 15–37, but chromogenic light microscopy cannot establish membrane sidedness from a brown signal alone (UniProt Q9Y3E5 topology; standard IHC practice). Compare staining within intact cells against a matched negative control, and assess whether apparent nuclear or extracellular signal persists after background controls (standard IHC practice). Where compartment assignment matters, use a mitochondrial marker in a separate, validated imaging experiment to test spatial agreement (HPA subcellular; standard IHC practice).
How do I investigate a discordant PTRH2 antibody epitope?
First obtain the antibody’s stated immunogen or epitope and check whether it overlaps the 15–37 transmembrane segment or a region likely to be exposed after section processing (UniProt Q9Y3E5 topology; standard IHC practice). The supplied record annotates 0 isoforms, 0 glycosylation sites and 0 modified residues, so those annotations do not explain discordant staining by themselves (UniProt Q9Y3E5 record). Compare matched sections under the page’s citrate pH 6.0 retrieval condition while keeping detection constant (page retrieval rule; standard IHC practice). If antibodies to distinct documented epitopes disagree, use independent specificity controls before interpreting either compartment pattern as PTRH2 (standard IHC practice).
How can IF help resolve ambiguous PTRH2 staining in tissue?
For this secondary IF application, multiplex PTRH2 with a marker identifying the expected cell type and, if compartment assignment matters, a mitochondrial marker (HPA tissue IHC; HPA subcellular; standard IF practice). Choose fluorophores whose emission is separable from the tissue’s measured autofluorescence, and include single-channel controls when comparing overlap (standard IF practice). PTRH2 has an outer-membrane transmembrane segment at residues 15–37; because the antibody epitope’s membrane-facing side is unspecified, select and validate permeabilisation against that side instead of assuming access (UniProt Q9Y3E5 topology; standard IF practice). Compare any punctate signal with marker overlap and negative controls before carrying an IF conclusion back to chromogenic IHC interpretation (standard IF/IHC practice).
What should I adjust when PTRH2 chromogenic staining looks diffuse?
First compare the section with a no-primary control and inspect whether brown signal follows tissue edges, damaged regions or areas lacking intact cellular morphology (standard IHC practice). Use a peroxidase block before HRP-based DAB detection, because endogenous peroxidase can produce chromogen independently of PTRH2 binding (standard IHC practice). Optimise blocking, antibody concentration and wash stringency one variable at a time; the selected small-intestine image used 10 µg/mL, which is evidence for that image rather than a universal dilution (A02459-1 tissue-IHC caption; standard IHC practice). Retain a granular cytoplasmic pattern as the reference when judging whether background reduction also removes plausible PTRH2 signal (HPA tissue IHC).
How should I score PTRH2 IHC across samples with mixed cell populations? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, since PTRH2 tissue staining is described as granular and cytoplasmic across many tissues (HPA tissue IHC; standard IHC practice). For intact target cells, record either the percentage positive or an H-score using prespecified intensity bins; apply the same threshold and imaging settings to every section (standard IHC practice). If the question concerns infiltrating cells, count positive cells per mm² of evaluable tissue and report the relevant cell-type fraction separately (standard IHC practice). Normalise scores to the number or area of eligible cells, exclude necrotic and damaged regions, and retain matched controls for each staining run (standard IHC practice).
How can I distinguish true PTRH2 positivity from IHC artefact?
A plausible positive signal is granular and cytoplasmic within intact cells, consistent with tissue staining and mitochondrial localisation (HPA tissue IHC; HPA subcellular). Check cell identity against the section’s morphology: high staining is reported in appendix glandular cells, whereas adipocytes are reported as not detected, so these are useful context-specific comparisons (HPA tissue IHC). Reject apparent positivity confined to cut edges or necrotic tissue, and investigate staining in the no-primary control or after inadequate peroxidase blocking before calling it target-specific (standard IHC practice). Because the HPA tissue assessment is only Supported with medium RNA–staining consistency, corroborate consequential findings with an independent specificity control (HPA tissue IHC; standard IHC practice).
Boster reagents

Best PTRH2 / Peptidyl-tRNA hydrolase 2, mitochondrial IHC Antibodies

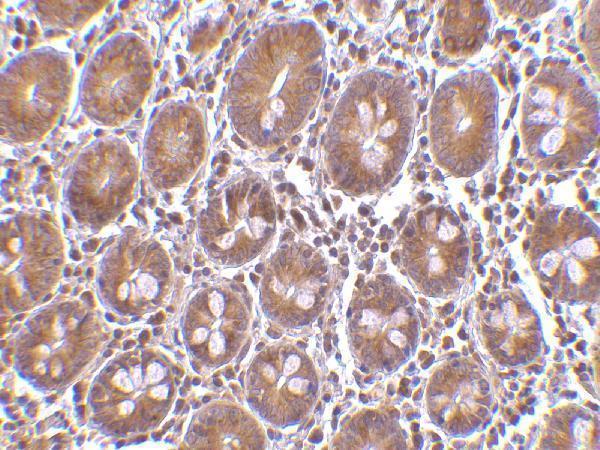
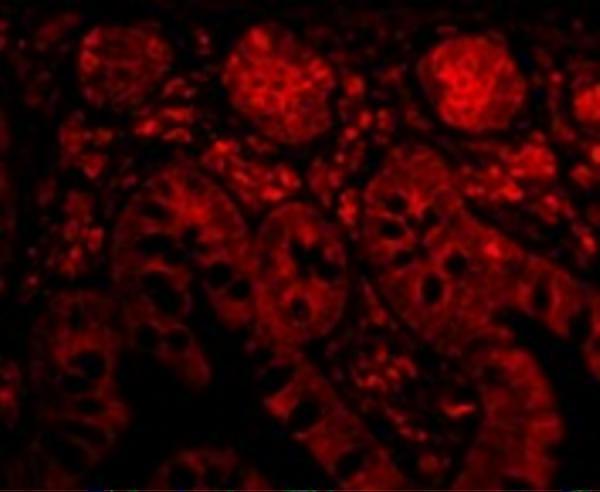
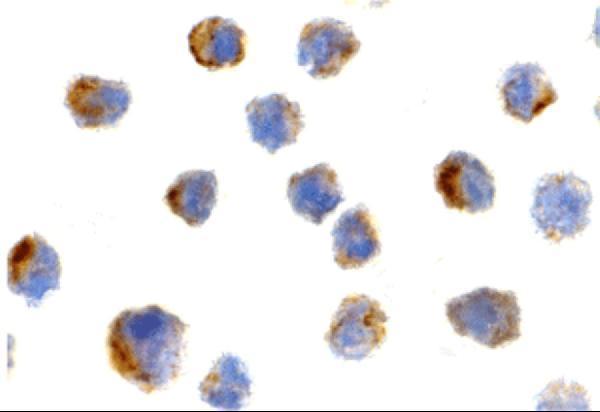
The catalog includes paraffin-section IHC for human small intestine (A02459-1 applications and image caption) and IF/ICC images of 3T3 cells (A02459 image captions); listed reactivity spans human, mouse and rat (catalog).

Real IHC data Immunohistochemistry of Bit1 in human small intestine tissue with Bit1 antibody at 10 μg/mL.
Anti-Bit1 PTRH2 Antibody
Cat # A02459-1
Real IF data Immunocytochemistry of Bit1 in 3T3 cells with Bit1 antibody at 2 μg/mL.
Anti-Bit1 PTRH2 Antibody
Cat # A02459

A02459-1 will render with its human small intestine IHC image at 10 μg/mL (image caption; applications: IHC-P). A02459 will render with its 3T3 cell ICC image at 2 μg/mL (image caption; applications: ICC, IF).

Which to pick: Choose A02459-1 for paraffin-section tissue IHC (applications: IHC-P; image caption: human small intestine); the caption does not report a fixative (image caption). Choose A02459 for IF/ICC (applications: IF, ICC; image caption: 3T3 cells), with no IHC application listed (catalog). For rat samples, A02459-2 lists IHC and IF, includes rat reactivity, and is polyclonal, although no IHC or IF image caption is supplied (catalog).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9Y3E5 (PTH2_HUMAN, Peptidyl-tRNA hydrolase 2, mitochondrial).
  2. Human Protein Atlas. PTRH2 tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. PTRH2 subcellular location (ICC-IF): Localized to the mitochondria..
  4. Human Protein Atlas. PTRH2 antibody validation summary (1 antibodies).
  5. PTRH2 is Necessary for Purkinje Cell Differentiation and Survival and its Loss Recapitulates Progressive Cerebellar Atrophy and Ataxia Seen in IMNEPD Patients. Cerebellum (London, England) 2023 — PMC10657312.
  6. Peptidyl-tRNA hydrolase 2 is a negative regulator of peripartum cardiomyopathy with heart failure in female mice. Nature communications 2025 — PMC12852877.
  7. PubMed PMID:10810093 — UniProt-cited evidence.
  8. PubMed PMID:14702039 — UniProt-cited evidence.
  9. PubMed PMID:15489334 — UniProt-cited evidence.