SOD2 / Superoxide dismutase [Mn], mitochondrial · IHC design guide

Design Immunohistochemistry for SOD2

Plan chromogenic SOD2 IHC on paraffin sections using 0.5–1 μg/mL as the PB9442 antibody starting range (datasheet: PB9442). Assess staining by cell type and intensity against the reported cytoplasmic, mitochondrial tissue pattern (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for SOD2 (IHC for SOD2): expected localisation Cytoplasmic, mitochondrial pattern in tissue (HPA tissue IHC), antibody PB9442, validated IHC image, and IHC protocol steps
Printable SOD2 IHC protocol sheet — expected localisation Cytoplasmic, mitochondrial pattern in tissue (HPA tissue IHC), antibody PB9442, controls and protocol steps. Open the full SOD2 IHC guide →

SOD2 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic, mitochondrial pattern in tissue (HPA tissue IHC)
Staining pattern General cytoplasmic staining with a mitochondrial pattern (HPA tissue IHC)
Antigen retrieval Citrate pH 6 HIER, heat-mediated (datasheet PB9442)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ None in HPA (detected in all 44 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Staining–RNA consistency is medium; restaining is pending (HPA tissue IHC)
Regulation Bone marrow–enhanced RNA expression (HPA tissue RNA)
Isoform / epitope 4 isoforms; mature chain spans residues 25–222; verify epitope coverage (UniProt)
Section 1

Recommended SOD2 IHC & IF Protocols

The catalog antibody’s IHC-P protocol (datasheet PB9442) is followed by three published SOD2 paraffin-section protocols (PMC11481372; PMC5955150; PMC8147985).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human mammary cancer tissue; fixative not specified (datasheet PB9442)
FixationImage fixative and duration unreported (datasheet PB9442); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: Citrate pH 6, 20 min (datasheet PB9442)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet PB9442)
Primary antibodyRabbit anti-SOD2, 0.5-1μg/ml (datasheet PB9442)
Primary incubationOvernight at 4 °C (datasheet PB9442)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet PB9442)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultSOD2-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic expression with a mitochondrial pattern. No signal in the no-primary control.
💡Decision noteStart with heat-mediated citrate retrieval at pH 6 (datasheet PB9442). If staining is weak, compare published tris retrieval at pH 8 (PMC11481372; PMC8147985).
Section 2

What Is the Expected SOD2 Staining Pattern?

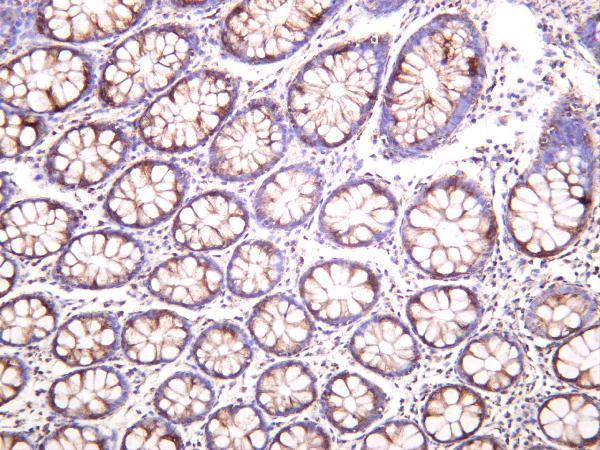
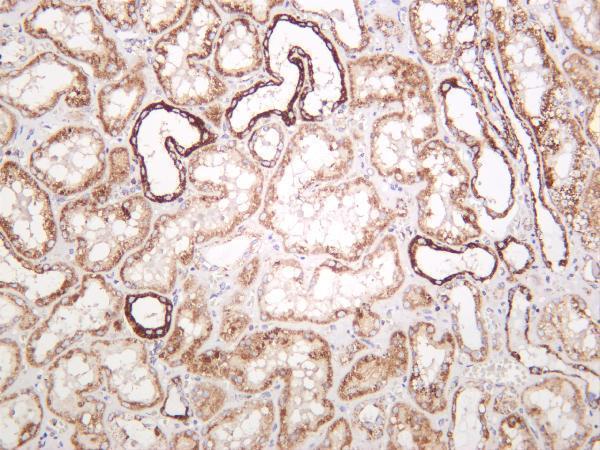
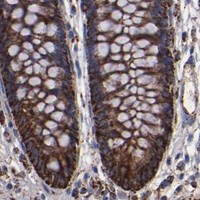
SOD2 is a mitochondrial matrix protein with no transmembrane segment (UniProt P04179 topology). In paraffin section IHC, expect cytoplasmic staining with a mitochondrial pattern (HPA: tissue IHC profile), including strong staining in colon glandular cells and bronchial respiratory epithelial cells (HPA: High in each). HPA rates its tissue IHC evidence Supported, with medium agreement between staining and RNA data; restaining is pending (HPA: tissue IHC reliability).

What am I looking at on my slide?
Strong, granular cytoplasmic staining in colon glands or bronchial respiratory epithelium.This fits SOD2's mitochondrial matrix location (UniProt P04179 subcellular location) and the reported high staining in those cell types (HPA: colon and bronchus tissue IHC). Score staining in the identified cells and note its cytoplasmic distribution; chromogenic IHC alone does not prove that every stained structure is a mitochondrion (general IHC practice).
Predominantly nuclear, cell-surface, or extracellular staining.Those compartments conflict with the expected mitochondrial matrix location (UniProt P04179 subcellular location). Treat the pattern as suspect, then inspect the negative reagent control and compare it with a known-positive tissue on the same run (general IHC practice). A wrong compartment alone does not identify the cause.
Strong staining mainly in cells outside the expected positive population.For example, high staining limited to cells other than colon glandular cells would not match the reported colon pattern (HPA: High in glandular cells). Consider antibody cross-reactivity or endogenous detection activity, then compare cell morphology, controls, and the distribution in a known-positive section (general IHC practice). Do not label an unlisted cell type definitively negative.
Diffuse color covers tissue structures without a discernible cellular pattern.Broad background prevents a confident call of mitochondrial-pattern cytoplasmic staining (HPA: tissue IHC profile). Check the negative reagent control, blocking and detection steps, and whether excessive primary or detection reagent increases background (general IHC practice). Avoid scoring diffuse color as positive SOD2.
No signal in colon glandular cells or bronchial respiratory epithelial cells.Both are reported as high-staining populations (HPA: colon and bronchus tissue IHC), so an absent signal warrants a run-level check. Verify tissue identity, control performance, antibody dilution, retrieval, and detection according to the validated IHC procedure (general IHC practice). A failed run cannot establish biological absence.
💡Expected SOD2 appearanceCall a result positive when the expected cells show distinct cytoplasmic, mitochondrial-pattern staining—often strong in colon glands or bronchial respiratory epithelium (HPA: tissue IHC profile; High in each); dominant nuclear or extracellular color is suspect (UniProt P04179 subcellular location).
How each factor affects the staining
Subcellular location and topologySOD2 resides in the mitochondrial matrix and has no transmembrane segment (UniProt P04179 subcellular location and topology). Interpret signal as an intracellular cytoplasmic pattern; a membrane-outline pattern needs control review (general IHC practice).
Tissue and cell selectionColon glandular cells and bronchial respiratory epithelial cells are reported High, while splenic red-pulp cells are reported Low (HPA: tissue IHC). The spleen entry is a low-staining observation, not proof that every red-pulp cell should be blank.
Strength of tissue evidenceHPA calls the tissue IHC pattern Supported, describes medium agreement with RNA, and notes pending restaining (HPA: tissue IHC reliability). Use its cell-level pattern to guide interpretation while checking each staining run with controls (general IHC practice).
Antigen retrieval and antibody setupFollow the selected IHC-validated antibody's established paraffin-section procedure for retrieval and dilution (general IHC practice). Neither UniProt nor the supplied HPA record establishes a SOD2-specific retrieval requirement or fixation sensitivity.
IF/ICC Q: Where should SOD2 appear?A: In mitochondria; HPA reports supported mitochondrial ICC-IF localisation and images in U2OS (HPA: subcellular record). This corroborates compartment choice but does not supply an IF protocol or override tissue-specific IHC observations.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Known-positive cells show no chromogenic signal.The run may have failed at retrieval, primary incubation, or detection (general IHC practice); colon glands are reported High (HPA: colon tissue IHC).Check the positive control and reagent sequence, then repeat with the IHC-validated antibody's established retrieval and dilution conditions (general IHC practice).
Signal is weak but restricted to the expected cells.Weak staining may reflect assay conditions, while intensity also differs by tissue: splenic red-pulp cells are Low (HPA: tissue IHC; general IHC practice).Compare a High control such as colon glandular cells before changing conditions; record cell type and intensity separately (HPA: colon tissue IHC; general IHC practice).
Nuclei dominate the staining pattern.Nuclear staining conflicts with mitochondrial matrix localisation (UniProt P04179 subcellular location); its cause is unresolved from appearance alone.Review the negative reagent control, tissue morphology, and staining in a known-positive section before accepting the result (general IHC practice).
Color is diffuse across tissue or appears in the negative reagent control.Nonspecific reagent binding or endogenous detection activity can contribute to background (general IHC practice).Check blocking, washes, detection controls, and reagent concentration using the validated IHC workflow; score only interpretable cellular staining (general IHC practice).
Unexpected cells stain more strongly than the reported positive cells.Cross-reactivity or endogenous detection activity is possible (general IHC practice); HPA's reported pattern identifies specific High cell populations (HPA: tissue IHC).Compare cell identity and compartment with the HPA pattern, then review negative controls and a High positive tissue before assigning SOD2 specificity (general IHC practice).
Results differ across sections or tissue types.HPA reports tissue-dependent staining and only medium agreement between antibody staining and RNA, with restaining pending (HPA: tissue IHC reliability and levels).Score each cell population and control separately, document the observed compartment and intensity, and avoid treating a Low tissue as an absolute negative control (HPA: tissue IHC; general IHC practice).

Sample controls for SOD2 IHC & IF

🧪Run bronchus first: respiratory epithelial cells should stain strongly (HPA: High in bronchus respiratory epithelial cells). HPA detects SOD2 in all 44 scored tissues, so no negative tissue is available; use no-primary and isotype controls, and judge cells without visible signal on the positive slide by the absence of specific granular cytoplasmic staining, without treating them as validated biological negatives (HPA: no negative tissue rows; UniProt P04179: mitochondrial matrix).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: None in HPA: SOD2 is detected in all 44 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show SOD2 in U2OS, with annotated localisation: Mitochondria (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only slide, a rabbit IgG control matched to the primary antibody’s clonality and concentration, and a similarly processed SOD2 knockout specimen as a biological negative (selected PB9442 caption: rabbit primary; standard IHC control practice). Quench endogenous peroxidase and check endogenous biotin when using the caption’s streptavidin–biotin/DAB detection, particularly where blood or inflammatory cells are present (selected PB9442 caption: SABC/DAB; standard IHC practice).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported, and the selected paraffin-section caption leaves the fixative unreported (selected PB9442 caption). The caption uses heat retrieval in citrate buffer at pH 6 for 20 minutes, but does not establish that retrieval is required under other conditions (selected PB9442 caption). IF/ICC can help assess mitochondrial localization, which HPA supports, while the supplied evidence does not establish that frozen sections are easier; blood and inflammatory cells in bronchus warrant attention to peroxidase background with chromogenic detection (HPA: mitochondria supported; HPA: High in bronchus respiratory epithelial cells; standard IHC practice).

HPA tissue IHC evidence for SOD2

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data. Pending restaining.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Glandular cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →
Caudate Neuronal cells High Protein (IHC) HPA →
Cerebellum Cells in granular layer High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: SOD2 is detected in all 44 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced SOD2 IHC Tips

Troubleshoot SOD2 staining in paraffin sections by checking retrieval, cellular pattern, controls and scoring before interpreting differences in signal.

How should I optimize retrieval when SOD2 staining is weak in paraffin sections?
Start with heat-mediated citrate retrieval at pH 6 for 20 minutes, matching the PB9442 tissue-IHC caption (datasheet PB9442). Keep section thickness, heating and cooling consistent across the comparison, then check whether the expected cytoplasmic, mitochondrial pattern becomes clearer (HPA tissue IHC; standard IHC practice). If staining remains weak, assess section retention and compare a modest change in heating time on adjacent sections before considering another retrieval buffer as a fallback (standard IHC practice). Run a section without primary antibody alongside each condition so stronger color is not mistaken for improved SOD2 detection (standard IHC practice).
Could fixation explain weak or uneven SOD2 staining?
Target-specific fixation sensitivity is unknown: the PB9442 caption describes paraffin-embedded tissue but does not state its fixative (datasheet PB9442). Record the fixative, fixation duration and tissue thickness for each specimen, then compare like with like because fixation can alter antigen accessibility in paraffin-section IHC (standard IHC practice). If one batch stains weakly, repeat the documented citrate pH 6 retrieval for 20 minutes before assigning the difference to fixation (datasheet PB9442). Examine adjacent morphology and staining controls for processing differences; neither the reported mitochondrial location nor the annotated modifications establish how this target responds to fixation (UniProt P04179; standard IHC practice).
What staining pattern should I expect for SOD2 in tissue sections?
Expect predominantly cytoplasmic staining with a mitochondrial pattern rather than a nuclear or cell-surface outline (HPA tissue IHC; UniProt P04179 mitochondrial matrix). At light-microscope resolution, inspect whether granular cytoplasmic signal follows intact cells and whether comparable cells show a reproducible pattern across the section (standard IHC practice). SOD2 has no annotated transmembrane segment, so a crisp membrane rim alone needs investigation before it is called specific (UniProt P04179 topology). Compare the pattern with a section without primary antibody and with tissue containing reported high glandular-cell staining, such as colon, while checking morphology and detection background (HPA tissue IHC; standard IHC practice).
How could isoforms or epitope changes affect SOD2 IHC?
Four SOD2 isoforms are annotated, but the supplied PB9442 caption does not map the antibody epitope or establish isoform recognition (UniProt P04179; datasheet PB9442). The annotated mature chain spans residues 25–222, and modifications include nitration at residue 58 and alternative lysine modifications at 68 and 75 (UniProt P04179). If staining differs across specimens, check available antibody documentation for epitope placement before proposing isoform or modification-dependent detection (standard IHC practice). Compare adjacent sections under identical retrieval and detection conditions, because staining intensity alone cannot identify an isoform or modification state (standard IHC practice).
How can IF help check an ambiguous chromogenic SOD2 pattern?
Use IF as a separate localisation check: SOD2 is reported in the mitochondrial matrix, and tissue IHC shows a cytoplasmic mitochondrial pattern (UniProt P04179; HPA tissue IHC). For a glandular region, multiplex SOD2 with an epithelial marker to identify the expected cells, and choose spectrally separated fluorophores after checking tissue autofluorescence (HPA tissue IHC; standard IF practice). After fixation, optimize permeabilisation so antibody can reach a matrix epitope across mitochondrial membranes without disrupting cell morphology (UniProt P04179 topology; standard IF practice). Include single-label and no-primary controls to distinguish channel bleed-through and background from punctate SOD2 signal; report IF results separately from chromogenic IHC scores (standard IF practice).
How do I reduce diffuse color or nonspecific granular staining?
First compare the stained section with a no-primary control and inspect section edges, damaged areas and endogenous pigment for matching color (standard IHC practice). The PB9442 tissue-IHC example used 10% goat serum blocking, 1 µg/ml primary antibody overnight at 4°C, and a biotin-based DAB detection sequence (datasheet PB9442). For DAB work, check the peroxidase block and reagent-only controls; these are general detection safeguards, not evidence of SOD2-specific interference (standard IHC practice). If background persists, titrate primary antibody and detection exposure on adjacent sections while retaining the citrate pH 6 retrieval reference condition (datasheet PB9442; standard IHC practice).
How should I score SOD2 staining across specimens? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and tissue region before scoring, because reported SOD2 staining varies among cell types and tissues (HPA tissue IHC; standard IHC practice). For cellular intensity, record the percentage of cells at scores 0–3 and calculate an H-score of 0–300, or report percentage positive when intensity is unreliable (standard IHC practice). For spatial comparisons, measure positive-cell density per mm² of viable analyzed tissue and exclude necrotic or folded areas (standard IHC practice). Normalize comparisons to the same cell type, viable area, retrieval and detection settings; record background separately rather than subtracting an assumed universal SOD2 baseline (standard IHC practice).
When is apparent SOD2 positivity likely to be an artefact?
Treat reproducible cytoplasmic staining with a mitochondrial pattern in intact cells as more credible than an isolated nuclear or membrane rim (HPA tissue IHC; UniProt P04179 mitochondrial matrix). Check whether the stained cell type fits the tissue context: high staining is reported in colon glandular cells, whereas spleen red-pulp cells are reported low (HPA tissue IHC). Intense signal confined to cut edges, necrosis or damaged regions should prompt review of section quality and no-primary controls (standard IHC practice). With DAB detection, inspect endogenous pigment and residual peroxidase activity before interpreting brown deposits as SOD2; HPA labels its tissue-IHC evidence Supported with medium staining–RNA consistency and pending restaining (standard IHC practice; HPA tissue IHC).
Boster reagents

Best SOD2 / Superoxide dismutase [Mn], mitochondrial IHC Antibodies

These anti-SOD2 antibodies have catalog IHC images from human and rat paraffin sections (catalog image captions); one also has an IF image from U2OS cells (PA1776 image caption).

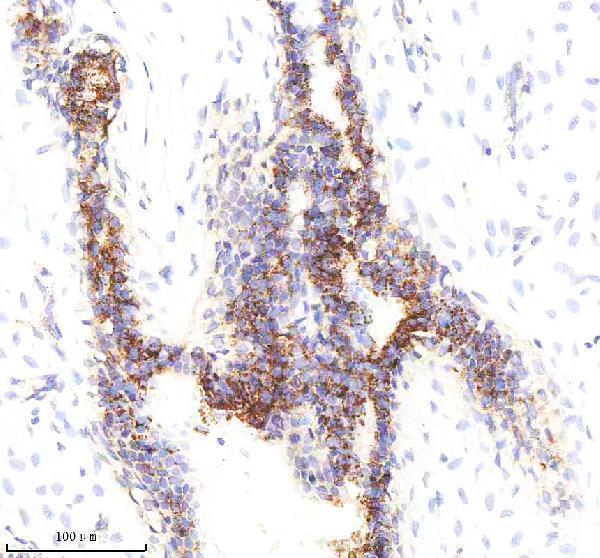
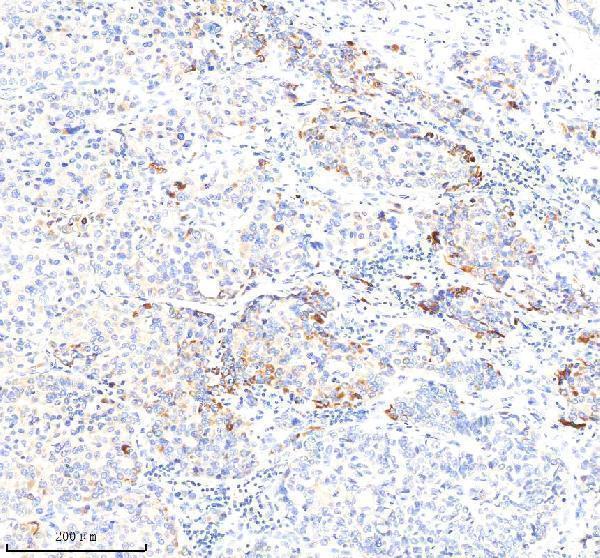
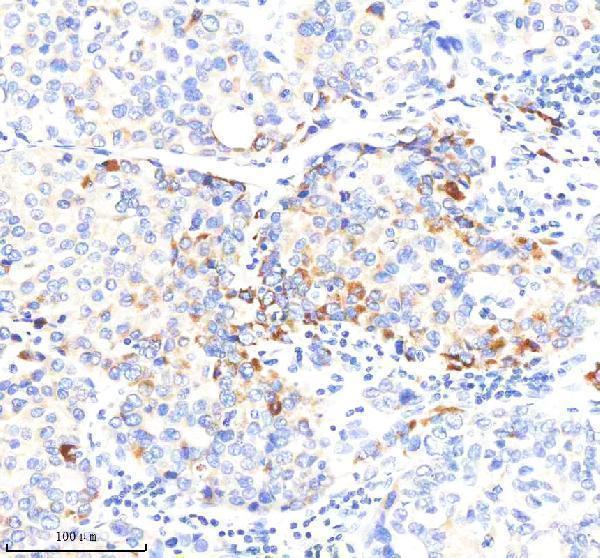
Real IHC data IHC analysis of SOD2 using anti-SOD2 antibody (PB9442). SOD2 was detected in paraffin-embedded section of human mammary cancer tissue. Heat mediated antigen retrieval was performed in citrate buffer (pH6, epitope retrieval solution) for 20 mins. The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml rabbit anti-SOD2 Antibody (PB9442) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC)(Catalog # SA1022) with DAB as the chromogen.
Anti-SOD2 Antibody ®
Cat # PB9442
Real IHC data IHC analysis of SOD2 (acetyl K68) using anti-SOD2 (acetyl K68) antibody (M00349-2). SOD2 (acetyl K68) was detected in a paraffin-embedded section of human breast cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1:50 rabbit SOD2 (acetyl K68) Antibody (M00349-2) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-SOD2 (acetyl K68) Rabbit Monoclonal Antibody
Cat # M00349-2
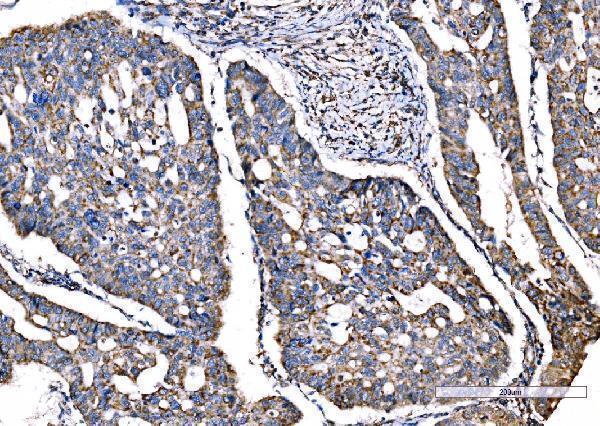
Real IHC data IHC analysis of SOD2 using anti-SOD2 antibody (M00349-3). SOD2 was detected in a paraffin-embedded section of human adenocarcinoma of the right colon tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml mouse anti-SOD2 Antibody (M00349-3) overnight at 4°C. Peroxidase Conjugated Goat Anti-mouse IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Mouse IgG Super Vision Assay Kit (Catalog # SV0001) with DAB as the chromogen.
Anti-SOD2 Antibody ® (monoclonal, 2B12B1)
Cat # M00349-3
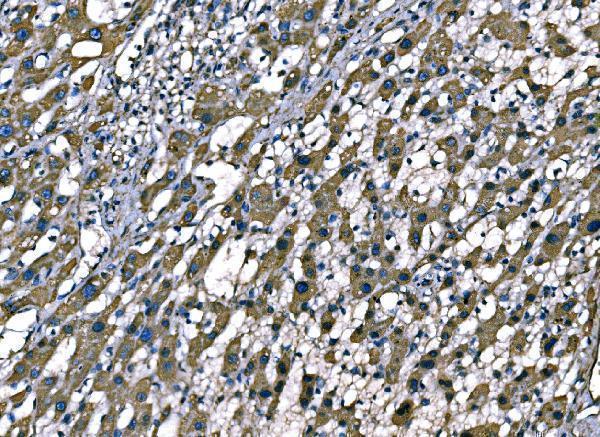
Real IHC data IHC analysis of SOD2 using anti-SOD2 antibody (M00349). SOD2 was detected in a paraffin-embedded section of human liver cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1:50 rabbit anti-SOD2 Antibody (M00349) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-SOD2/Mnsod Rabbit Monoclonal Antibody
Cat # M00349
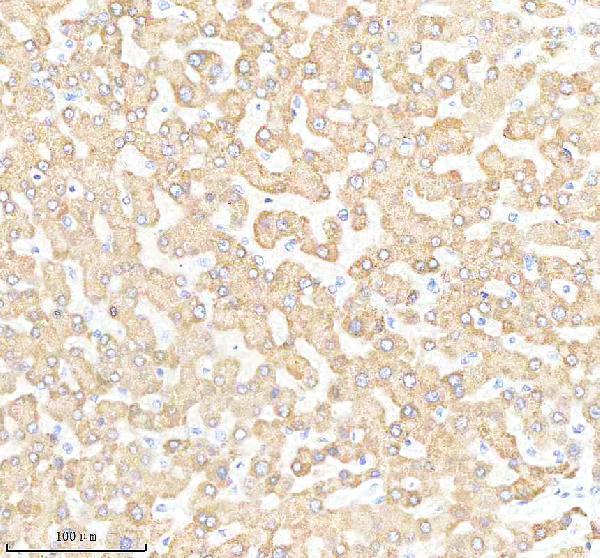
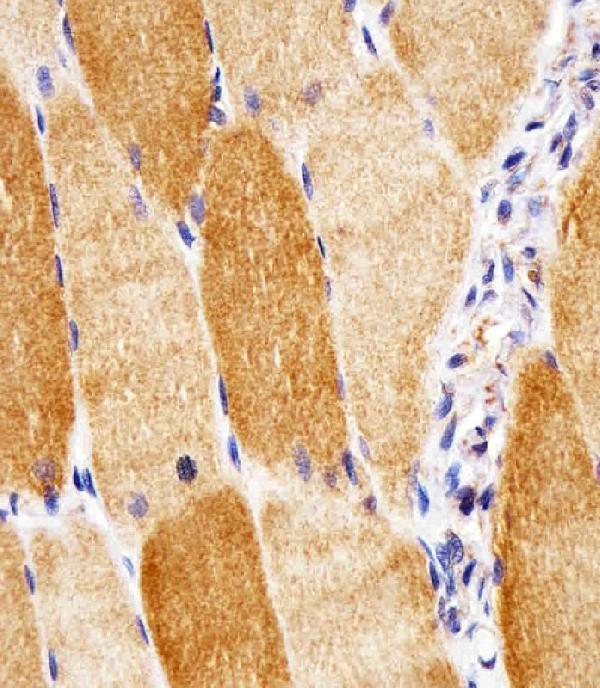
Real IHC data M33970-1 staining SODM in human skeletal muscle sections by Immunohistochemistry (IHC-P -paraformaldehyde-fixed, paraffin-embedded sections). Tissue was fixed with formaldehyde and blocked with 3% BSA for 0. 5 hour at room temperature; antigen retrieval was by heat mediation with a citrate buffer (pH6). Samples were incubated with primary antibody (1/25) for 1 hours at 37°C. A undiluted biotinylated goat polyvalent antibody was used as the secondary antibody.
Anti-SODM Antibody
Cat # M33970-1
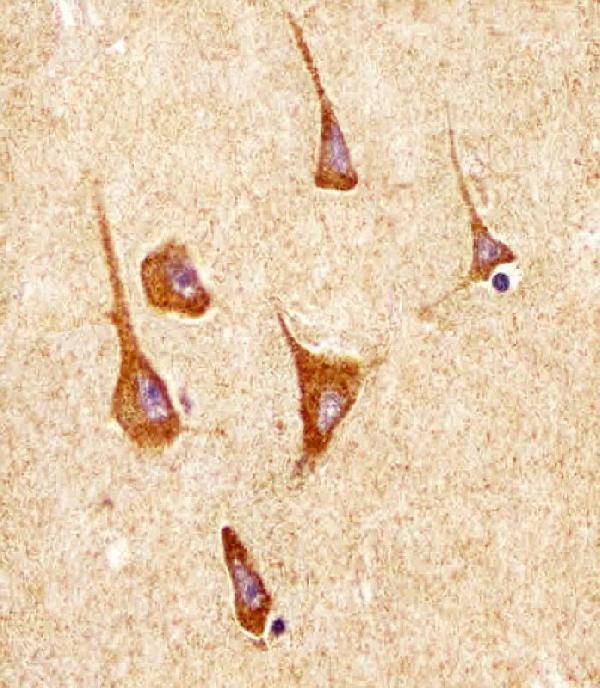
Real IHC data IHC analysis of SOD2/Mnsod using anti-SOD2/Mnsod antibody (PA1776). SOD2/Mnsod was detected in paraffin-embedded section of rat brain tissues. Heat mediated antigen retrieval was performed in citrate buffer (pH6, epitope retrieval solution) for 20 mins. The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml rabbit anti-SOD2/Mnsod Antibody (PA1776) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC)(Catalog # SA1022) with DAB as the chromogen.
Anti-SOD2 Antibody ®
Cat # PA1776

PB9442 was shown on human mammary cancer, M00349-2 on human breast cancer for acetyl-K68 SOD2, and M00349-3 on human right-colon adenocarcinoma (respective IHC image captions). M00349 was shown on human liver cancer, M33970-1 on human skeletal muscle, and PA1776 on rat brain (respective IHC image captions).

Which to pick: For tissue IHC, choose rabbit monoclonal M00349 when its human liver cancer example and EDTA retrieval at pH 8.0 suit the experiment; its paraffin-section caption does not report the fixative (M00349 catalog entry and IHC image caption). For IF/ICC, choose PA1776: ICC is listed and its IF image shows U2OS cells, while its own IHC caption shows rat brain after citrate retrieval at pH 6; that paraffin-section caption does not report the fixative (PA1776 catalog entry and image captions). For work across human, mouse and rat, PB9442 and PA1776 list all three species and IHC plus ICC; PB9442’s own IHC example uses human mammary cancer paraffin sections with citrate retrieval at pH 6, with fixative unreported (PB9442 and PA1776 catalog entries; PB9442 IHC image caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P04179 (SODM_HUMAN, Superoxide dismutase [Mn], mitochondrial).
  2. Human Protein Atlas. SOD2 tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. SOD2 subcellular location (ICC-IF): Localized to the mitochondria..
  4. Human Protein Atlas. SOD2 antibody validation summary (1 antibodies).
  5. Post-mortem Findings of Inflammatory Cells and the Association of 4-Hydroxynonenal with Systemic Vascular and Oxidative Stress in Lethal COVID-19. Cells 2022 — PMC8834180.
  6. Melatonin increases superoxide dismutase 2 (SOD2) levels and improves rat ovarian graft function after transplantation. Journal of ovarian research 2024 — PMC11481372.
  7. Strong SOD2 expression and HPV-16/18 positivity are independent events in cervical cancer. Oncotarget 2018 — PMC5955150.
  8. High Expression of SOD2 Protein Is a Strong Prognostic Factor for Stage IIIB Squamous Cell Cervical Carcinoma. Antioxidants (Basel, Switzerland) 2021 — PMC8147985.
  9. PubMed PMID:2462451 — UniProt-cited evidence.
  10. PubMed PMID:3684581 — UniProt-cited evidence.
  11. PubMed PMID:3399391 — UniProt-cited evidence.