TLR8 / Toll-like receptor 8 · IHC design guide

Design Immunohistochemistry for TLR8

Plan chromogenic TLR8 IHC on paraffin sections using the 2–5 μg/mL catalog antibody range (datasheet A01541-3). Evaluate cytoplasmic staining in immune-cell subsets, using bone marrow hematopoietic cells and splenic red-pulp cells as high-expression references (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for TLR8 (IHC for TLR8): expected localisation Cytoplasmic staining in immune-cell subsets; endosomal membrane expected (HPA tissue IHC; UniProt), antibody A01541-3, validated IHC image, and IHC protocol steps
Printable TLR8 IHC protocol sheet — expected localisation Cytoplasmic staining in immune-cell subsets; endosomal membrane expected (HPA tissue IHC; UniProt), antibody A01541-3, controls and protocol steps. Open the full TLR8 IHC guide →

TLR8 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic staining in immune-cell subsets; endosomal membrane expected (HPA tissue IHC; UniProt)
Staining pattern Cytoplasmic staining in subsets of immune cells (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A01541-3)
Positive control ⓘ Bone marrow+3 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Subset staining can complicate whole-tissue scoring (HPA tissue IHC)
Regulation Expression regulation not specified (UniProt)
Isoform / epitope 2 isoforms; verify extracellular vs cytoplasmic epitope (UniProt)
Section 1

Recommended TLR8 IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol (datasheet A01541-3) with published chromogenic IHC on human adipose tissue (PMC5146894).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human gastric cancer tissue; fixative not specified (datasheet A01541-3)
FixationImage fixative and duration unreported (datasheet A01541-3); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A01541-3); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A01541-3)
Primary antibodyRabbit anti-TLR8, 2 μg/ml (datasheet A01541-3)
Primary incubationOvernight at 4 °C (datasheet A01541-3)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A01541-3)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultTLR8-positive staining in hematopoietic cells of bone marrow (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in subsets of immune cells. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 (datasheet A01541-3); consider the published pH 6.0 retrieval for adipose sections (PMC5146894).
Section 2

What Is the Expected TLR8 Staining Pattern?

TLR8 is an endosomal membrane receptor with one transmembrane segment (UniProt Q9NR97: endosome membrane; residues 828–848). In paraffin-section IHC, expect cytoplasmic staining in subsets of immune cells (HPA: Enhanced tissue IHC; medium consistency with RNA). Reported positive populations include bone marrow hematopoietic cells and spleen red-pulp cells at High levels, and lung macrophages and tonsil non-germinal-center cells at Medium levels (HPA: tissue IHC).

What am I looking at on my slide?
Cytoplasmic signal in a subset of immune cells, with other cells unstained.This fits the reported tissue pattern (HPA: cytoplasmic expression in subsets of immune cells). Assess the relevant cell population, since HPA reports staining in selected cells within each positive tissue (HPA: tissue IHC).
Signal is predominantly nuclear or confined to the cell surface.That compartment pattern conflicts with the expected cytoplasmic IHC profile and endosomal membrane assignment (HPA: tissue IHC; UniProt Q9NR97: endosome membrane). Treat it as suspect and review morphology and controls before scoring it as TLR8.
Strong staining appears in a population reported as undetected, such as bronchial respiratory epithelial cells.HPA reports TLR8 as Not detected in that population (HPA: bronchus IHC). Check for antibody cross-reactivity or endogenous chromogen activity using appropriate controls (general IHC practice); the HPA result is a reference pattern, not proof that every specimen must be negative.
A uniform haze covers multiple cell types or extends beyond cell boundaries.Diffuse haze obscures the cell-restricted pattern reported for TLR8 (HPA: tissue IHC). Review blocking, washes, antibody concentration and detection controls as general IHC troubleshooting steps (general IHC practice); haze alone does not identify its cause.
No signal is visible in the expected positive cell population of a control section.Bone marrow hematopoietic cells and spleen red-pulp cells are reported at High levels (HPA: tissue IHC). Check that those cells are present, then assess retrieval, antibody incubation and detection controls before interpreting an experimental negative (general IHC practice).
💡Expected TLR8 appearanceCall a result consistent with TLR8 when cytoplasmic staining is concentrated in the reported immune-cell subsets, with High signal in bone marrow hematopoietic or spleen red-pulp cells where present (HPA: tissue IHC); isolated nuclear signal or broad epithelial staining is suspect against the reported pattern (HPA: tissue IHC; UniProt Q9NR97: endosome membrane).
How each factor affects the staining
Compartment and membrane topologyTLR8 resides at the endosome membrane and spans residues 828–848 (UniProt Q9NR97: location and topology). HPA describes cytoplasmic tissue staining (HPA: tissue IHC). Routine chromogenic IHC may show cytoplasmic signal without resolving individual endosomes (general IHC practice).
Cell population and tissue choiceHPA reports High staining in bone marrow hematopoietic cells and spleen red-pulp cells, Medium in lung macrophages and tonsil non-germinal-center cells, and Low in lymph-node non-germinal-center cells (HPA: tissue IHC). Score the named population rather than an entire section.
Antibody evidenceThe listed rabbit polyclonal antibody, HPA001608, has Enhanced IHC validation (HPA: antibody validation). The overall tissue profile is also labeled Enhanced, with medium consistency between staining and RNA expression (HPA: tissue IHC). These labels support interpretation but do not establish specificity in every specimen.
Processing and epitope uncertaintyUniProt notes distinctive proteolytic processing linked to endosomal localization and lists 2 isoforms (UniProt Q9NR97). The supplied record does not locate the catalog antibody epitope or establish equal isoform recognition; do not assign a staining difference to either mechanism without further evidence.
Chromogenic detection backgroundEndogenous enzyme activity or nonspecific detection can imitate staining in IHC (general IHC practice). Use a detection control and examine whether color remains restricted to the expected cells (HPA: tissue IHC). No TLR8-specific detection artifact is documented in the supplied sources.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Expected positive tissue stains weakly or not at all.The relevant positive cells may be absent from the section, or a general IHC step may have failed; HPA reports High signal in specified bone marrow and spleen cell populations (HPA: tissue IHC).Confirm the named cells by morphology, then review retrieval and detection controls and the antibody working conditions (general IHC practice). No TLR8-specific retrieval condition or fixation sensitivity is supplied.
The entire section has diffuse chromogen color.Nonspecific antibody binding, incomplete washing or endogenous detection activity are possible general IHC causes (general IHC practice). Diffuse color differs from the subset pattern (HPA: tissue IHC).Compare a primary-antibody omission control, review blocking and washes, and reassess the working antibody concentration (general IHC practice). Interpret only cell-associated signal above the control.
Nuclei are the dominant stained compartment.Predominant nuclear staining does not fit HPA's cytoplasmic profile or UniProt's endosomal membrane assignment (HPA: tissue IHC; UniProt Q9NR97: location). Its specific cause cannot be inferred from appearance alone.Check the counterstain and detection controls, then compare staining in a reported positive cell population (general IHC practice; HPA: tissue IHC). Do not score nuclear color alone as confirmed TLR8.
Strong signal appears across respiratory epithelium in bronchus.HPA reports bronchial respiratory epithelial cells as Not detected (HPA: bronchus IHC). Cross-reactivity or detection background is possible, but staining alone cannot distinguish them (general IHC practice).Check cell identity and compare an omission control with a positive immune-cell control (general IHC practice; HPA: tissue IHC). Record any unresolved epithelial signal separately from the expected pattern.
A reported positive section contains both stained and unstained cells.Subset staining is expected: HPA describes cytoplasmic expression in subsets of immune cells (HPA: tissue IHC). UniProt reports expression in myeloid dendritic cells, monocytes and monocyte-derived dendritic cells (UniProt Q9NR97: tissue specificity).Score identified cell populations and their staining intensity separately, using morphology and suitable cell markers if identity is uncertain (general IHC practice). Avoid treating unstained neighboring cells as assay failure.
Can the IHC pattern be used as an IF/ICC protocol or localization validation?The supplied HPA subcellular summary says Membrane, but gives no main location or ICC-IF image-bearing cell line (HPA: subcellular summary). UniProt assigns TLR8 to the endosome membrane (UniProt Q9NR97).Use this section to set an IHC expectation only; consult the separate IF/ICC guide for assay design. Do not infer an IF/ICC protocol or image-validated punctate pattern from these records (HPA: subcellular summary).

Sample controls for TLR8 IHC & IF

🧪Run spleen first: cells in the red pulp should stain (HPA: High in spleen red-pulp cells). Use adipose tissue adipocytes as the negative tissue (HPA: Not detected in adipocytes); on the spleen slide, morphologically identified non-target cells should show background-level staining, but their TLR8-negative status needs independent confirmation (HPA: positive population specified as red-pulp cells).
Positive control tissue: Bone marrow (Hematopoietic cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA carries no ICC-IF cell line for TLR8; derive a cell-line control from the positive tissue's cell type (Hematopoietic cells) and confirm it by RNA or western blot first.
Technical controls: Include a no-primary, secondary-only control and a concentration-matched rabbit isotype control; confirm specificity with TLR8 knockout tissue or a validated immunizing-peptide block (standard IHC practice; selected-SKU IHC caption: rabbit primary). For chromogenic staining of spleen, block endogenous peroxidase and check for endogenous biotin when using the caption’s streptavidin–biotin detection system (standard IHC practice; selected-SKU IHC caption: SABC/DAB).
⚠️Feasibility: The selected-SKU caption documents paraffin-section IHC with heat retrieval in EDTA at pH 8.0, but reports no fixative; a TLR8-specific fixation window or effect and a requirement for that retrieval condition are unreported (selected-SKU IHC caption). Whether frozen sections or IF are easier is unreported in the supplied evidence (selected-SKU IHC caption: paraffin IHC only; HPA subcellular: no ICC-IF image cell lines). In spleen red pulp, endogenous peroxidase and pigment can complicate chromogenic interpretation (HPA: red-pulp target cells; standard IHC practice).

HPA tissue IHC evidence for TLR8

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Spleen Cells in red pulp High Protein (IHC) HPA →
Lung Macrophages Medium Protein (IHC) HPA →
Tonsil Non-germinal center cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Appendix Endocrine cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Not detected Protein (IHC) HPA →
Section 3

Advanced TLR8 IHC Tips

Troubleshoot TLR8 staining in paraffin sections by checking retrieval, cell identity and the expected intracellular pattern before comparing signal intensity.

What should I adjust if TLR8 staining is weak after antigen retrieval?
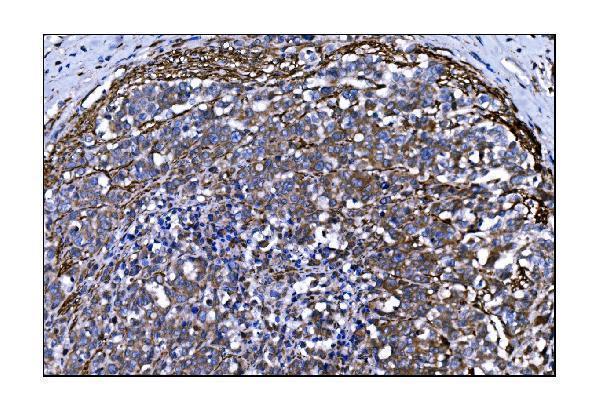
Start with heat-mediated retrieval in EDTA at pH 8.0 (datasheet A01541-3). The selected paraffin-section example used that retrieval before incubation with 2 μg/ml antibody overnight at 4°C, so reproduce those conditions when assessing weak staining (datasheet A01541-3). Include a section with expected immune-cell staining: bone-marrow hematopoietic cells stain strongly, while lung macrophages show medium staining (HPA tissue IHC). If signal remains weak, vary heating duration on matched sections while keeping antibody concentration and detection constant, then compare tissue preservation and background (general IHC practice). Record retrieval conditions for each run because altered heating can change both epitope exposure and tissue integrity (general IHC practice).
Can I attribute weak TLR8 staining to the tissue fixative?
The selected image documents a paraffin-embedded gastric cancer section but does not report its fixative, so target-specific fixation sensitivity is unknown (datasheet A01541-3). Do not infer a preferred fixative from the antibody image or from TLR8 topology and glycosylation; neither supplies a fixation comparison (datasheet A01541-3; UniProt Q9NR97). For troubleshooting, compare sections with documented processing histories under the same EDTA pH 8.0 retrieval and antibody conditions (datasheet A01541-3; general IHC practice). Check whether weak signal tracks processing batches while morphology and a separate control stain remain intact (general IHC practice). Report the actual fixation and processing conditions alongside staining results rather than assigning a TLR8-specific fixation effect (general IHC practice).
Where should convincing TLR8 staining appear in a paraffin section?
Expect intracellular staining in appropriate immune cells: TLR8 is an endosome-membrane receptor, and HPA describes cytoplasmic staining in immune-cell subsets (UniProt Q9NR97 subcellular location; HPA tissue IHC). The membrane segment spans residues 828–848, with residues 27–827 on the luminal side and 849–1041 cytoplasmic (UniProt Q9NR97 topology). On chromogenic sections, assess a cellular cytoplasmic pattern with preserved morphology rather than requiring individual endosomes to be resolved (general IHC practice). Compare staining with expected populations, including lung macrophages and splenic red-pulp cells (HPA tissue IHC). Diffuse staining across unrelated cells or prominent nuclear signal needs further specificity checks before it is scored as TLR8 (UniProt Q9NR97 subcellular location; general IHC practice).
How do isoforms and epitope position affect interpretation of TLR8 IHC?
TLR8 has 2 annotated isoforms, but the supplied antibody caption does not identify its epitope or establish which isoforms it detects (UniProt Q9NR97 isoforms; datasheet A01541-3). The receptor has an endosomal luminal region at residues 27–827 and a cytoplasmic region at 849–1041, separated by one transmembrane segment (UniProt Q9NR97 topology). Its luminal region includes 21 annotated glycosylation sites, and endosomal localization is associated with distinctive proteolytic processing (UniProt Q9NR97 glycosylation and subcellular location). These features make epitope location relevant when comparing antibodies or processing conditions, but they do not establish this antibody’s binding site (UniProt Q9NR97; datasheet A01541-3). Confirm the epitope and isoform coverage from antibody-specific documentation before interpreting a negative stain as absence of every TLR8 form (general IHC practice).
How should I investigate TLR8 by multiplex immunofluorescence?
Treat IF as a separate assay: the supplied antibody example demonstrates paraffin-section chromogenic IHC, with no IF validation stated (datasheet A01541-3). Pair TLR8 with a marker identifying the expected immune-cell population, such as a macrophage marker when examining lung macrophages, and evaluate cell-level overlap (HPA tissue IHC; general IF practice). Choose fluorophores and exposure settings against measured tissue autofluorescence, using single-label and unstained controls to distinguish bleed-through and background (general IF practice). TLR8 spans the endosome membrane, so select and validate permeabilisation for the antibody’s epitope side, luminal or cytoplasmic; that side is unspecified here (UniProt Q9NR97 topology; datasheet A01541-3). Assess the intracellular pattern independently of marker overlap, since shared cells alone do not establish endosomal localization (UniProt Q9NR97 subcellular location; general IF practice).
How can I reduce diffuse or misleading brown signal?
The selected chromogenic example used 10% goat serum blocking, a biotinylated secondary, streptavidin-biotin detection and DAB (datasheet A01541-3). Reproduce its 2 μg/ml primary concentration and overnight incubation at 4°C before changing one condition at a time (datasheet A01541-3; general IHC practice). Include a no-primary control to assess secondary and detection background, and apply a peroxidase block appropriate for DAB detection (general IHC practice). If widespread staining persists, assess endogenous biotin where relevant to this detection system and compare a lower primary concentration with the reference condition (datasheet A01541-3; general IHC practice). Score only signal associated with intact cells after checking necrotic areas, tissue edges and pigment for misleading color (general IHC practice).
What is a defensible way to quantify TLR8-positive cells? ⚠ ANSWER MARKED FOR VERIFICATION
Define the immune-cell compartment before scoring, because HPA reports TLR8 staining in subsets of immune cells rather than uniform staining across tissue (HPA tissue IHC). For identified cells, report the percentage positive and an H-score using prespecified intensity categories; for spatial comparisons, report positive-cell density per mm² of evaluable tissue (general IHC practice). Normalize counts to the number of eligible cells or measured evaluable area, and keep thresholds, imaging and section selection consistent across groups (general IHC practice). Record excluded necrotic, folded and edge regions before measuring so their DAB signal cannot inflate the estimate (general IHC practice). Interpret group differences alongside cell composition, since a changed macrophage fraction can change tissue-level TLR8 staining (HPA tissue IHC; general IHC practice).
Which staining patterns support a true TLR8 result?
Favor intracellular staining in plausible immune cells: HPA reports high staining in bone-marrow hematopoietic cells and splenic red-pulp cells, and medium staining in lung macrophages (HPA tissue IHC). TLR8 is an endosome-membrane receptor, so predominantly nuclear staining or broad staining of unrelated cells requires further scrutiny (UniProt Q9NR97 subcellular location; general IHC practice). HPA reports no detectable staining in adipocytes from adipose tissue, providing a useful cell-type comparison where those cells are present (HPA tissue IHC). Exclude edge effects and necrotic deposits, and use a no-primary control plus peroxidase blocking to investigate DAB signal from the detection workflow (general IHC practice). HPA rates tissue staining as Enhanced but reports medium agreement with RNA expression, so treat concordance as supporting evidence rather than definitive validation (HPA tissue IHC).
Boster reagents

Best TLR8 / Toll-like receptor 8 IHC Antibodies

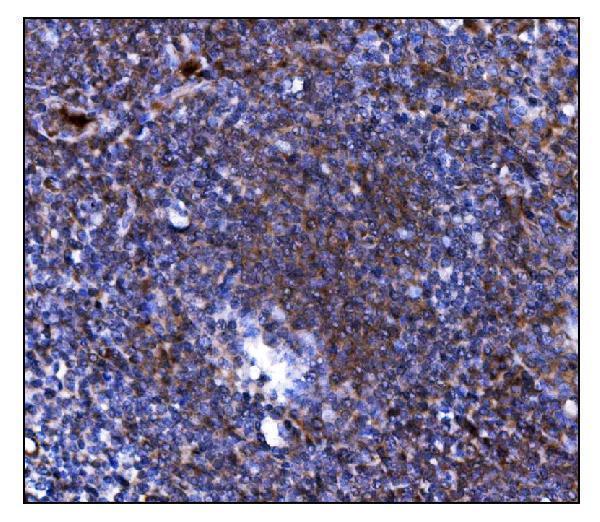
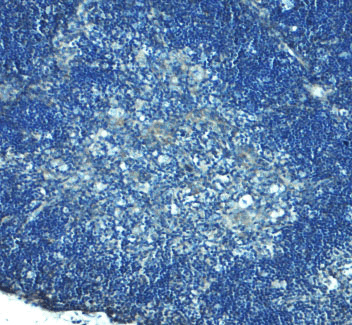
Anti-TLR8 antibodies have IHC images from human paraffin sections and human and mouse thymus, plus IF/ICC images from Daudi cells (catalog image captions).

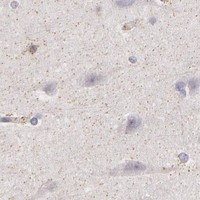
Real IHC data IHC analysis of TLR8 using anti-TLR8 antibody (A01541-3). TLR8 was detected in a paraffin-embedded section of human gastric cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-TLR8 Antibody (A01541-3) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-TLR8 Antibody
Cat # A01541-3
Real IHC data Immunohistochemistry of TLR8 in human thymus tissue with TLR8 antibody at 5 μg/mL.
Anti-Toll-like receptor 8 TLR8 Antibody
Cat # A01541
Real IF data Immunocytochemistry of TLR8 in Daudi cells with TLR8 antibody at 2 μg/mL.
Anti-Toll-like receptor 8 TLR8 Antibody
Cat # A01541-1

A01541-3 has IHC images from human gastric cancer and tonsil paraffin sections (A01541-3 image captions); A01541 has IHC images from human and mouse thymus (A01541 image captions). A01541-1 has ICC and IF images from Daudi cells (A01541-1 image captions).

Which to pick: For human paraffin-section IHC, choose A01541-3: its caption documents EDTA retrieval and 2 μg/mL primary antibody, but does not report the fixative (A01541-3 image caption). For IF/ICC, choose A01541-1, which lists both applications and shows Daudi-cell images (A01541-1 catalog applications and image captions). For IHC across human and mouse samples, choose A01541; both species have thymus IHC images, and its listed application is IHC-P (A01541 catalog applications and image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9NR97 (TLR8_HUMAN, Toll-like receptor 8).
  2. Human Protein Atlas. TLR8 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. TLR8 subcellular location (ICC-IF): Membrane.
  4. Human Protein Atlas. TLR8 antibody validation summary (1 antibodies).
  5. Expression of toll like receptor 8 (TLR8) in specific groups of mouse hippocampal interneurons. PloS one 2022 — PMC9067651.
  6. Increased adipose tissue expression of TLR8 in obese individuals with or without type-2 diabetes: significance in metabolic inflammation. Journal of inflammation (London, England) 2016 — PMC5146894.
  7. Antibody preparation and age-dependent distribution of TLR8 in Bactrian camel spleens. BMC veterinary research 2023 — PMC10725000.
  8. Toll-like receptor 8 functions as a negative regulator of neurite outgrowth and inducer of neuronal apoptosis. The Journal of cell biology 2006 — PMC2064562.
  9. PubMed PMID:11022119 — UniProt-cited evidence.
  10. PubMed PMID:11022120 — UniProt-cited evidence.
  11. PubMed PMID:18810425 — UniProt-cited evidence.