ALDH1A1 / Aldehyde dehydrogenase 1A1 · IHC design guide

Design Immunohistochemistry for ALDH1A1

Plan chromogenic ALDH1A1 IHC in paraffin sections using the catalog antibody’s documented staining conditions. Compare cytoplasmic staining across tissues with HPA tissue IHC patterns and appropriate controls.

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for ALDH1A1 (IHC for ALDH1A1): expected localisation Cytoplasmic staining in selected tissues (HPA tissue IHC), antibody A01392, validated IHC image, and IHC protocol steps
Printable ALDH1A1 IHC protocol sheet — expected localisation Cytoplasmic staining in selected tissues (HPA tissue IHC), antibody A01392, controls and protocol steps. Open the full ALDH1A1 IHC guide →

ALDH1A1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic staining in selected tissues (HPA tissue IHC)
Staining pattern Cytoplasmic staining; high in epididymal and stomach glandular cells (HPA tissue IHC)
Antigen retrieval Citrate pH 6 HIER, heat-mediated (datasheet A01392)
Positive control ⓘ Epididymis+4 more · see all
Negative control ⓘ Adrenal gland+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific); Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A01392)
Caveat Glandular staining varies by tissue (HPA tissue IHC)
Regulation Tissue-dependent expression (HPA tissue IHC)
Isoform / epitope No annotated isoforms; one chain spans residues 2–501 (UniProt)
Section 1

Recommended ALDH1A1 IHC & IF Protocols

The catalog antibody’s IHC-P protocol is accompanied by published ALDH1A1 staining protocols for pancreatic cancer and colorectal cancer sections (PMC3135572; PMC6181398).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human renal cancer tissues; fixative not specified (datasheet A01392)
FixationImage fixative and duration unreported (datasheet A01392); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: Citrate pH 6, 20 min (datasheet A01392)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A01392)
Primary antibodyRabbit anti-ALDH1A1, 0.5-1μg/ml (datasheet A01392)
Primary incubationOvernight at 4 °C (datasheet A01392)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A01392)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
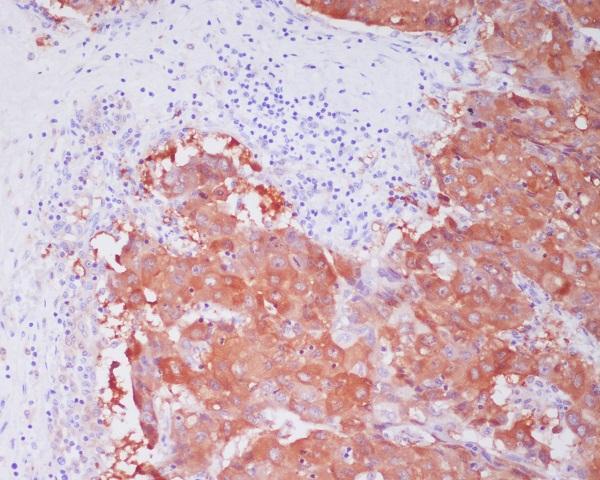
Expected resultALDH1A1-positive staining in glandular cells of epididymis (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in selected tissues. No signal in the no-primary control.
💡Decision noteStart with heat-mediated citrate retrieval at pH 6, as specified for the catalog antibody and used in both published protocols (datasheet A01392; PMC3135572; PMC6181398).
Section 2

What Is the Expected ALDH1A1 Staining Pattern?

ALDH1A1 should appear mainly in the cytoplasm, consistent with its cytosolic location and lack of a transmembrane segment (UniProt P00352). In paraffin tissue sections, expect staining in selected cells, including epididymal and stomach glandular cells and liver hepatocytes (HPA tissue IHC). HPA rates tissue staining reliability as Enhanced, while reporting medium consistency between antibody staining and RNA expression (HPA tissue IHC).

What am I looking at on my slide?
Cytoplasmic staining is strong in epididymal or stomach glandular cells (HPA tissue IHC: High).This matches the strongest listed tissue patterns and the expected compartment (HPA tissue IHC; UniProt P00352). Judge the relevant cells, rather than treating every cell in the section as equally positive (HPA tissue IHC: expression in selected tissues).
Hepatocytes stain at moderate intensity, while nearby cells differ (HPA tissue IHC: Medium in hepatocytes).A medium hepatocyte signal is compatible with the reference pattern (HPA tissue IHC). Liver-enhanced RNA expression does not require the strongest protein staining on a given slide (HPA tissue IHC: RNA tissue enhanced in liver; hepatocyte staining Medium).
The dominant signal is nuclear or confined to cell borders.Question the localization and check controls and image interpretation: ALDH1A1 is cytosolic and lacks a transmembrane segment (UniProt P00352; HPA subcellular: cytosol). The supplied records do not establish a nuclear or membrane staining pattern.
An HPA-listed undetected cell population stains strongly, or staining covers many unrelated cell types.Consider cross-reactivity or chromogenic detection background (general IHC practice). Compare the named cell type with its HPA entry: for example, adrenal glandular cells are listed as Not detected (HPA tissue IHC). An undetected entry is not a guarantee about every cell in that organ.
The entire section has a light haze, or a listed high-staining glandular population has no signal.Uniform haze obscures cell-level interpretation; absent signal in epididymal or stomach glandular cells makes the run inconclusive (HPA tissue IHC: High in those cells). Review controls and staining conditions before assigning a biological negative (general IHC practice).
💡Expected ALDH1A1 appearanceCall a result positive when staining is predominantly cytoplasmic in the listed cell type, especially strong in epididymal or stomach glandular cells; dominant nuclear, border-only or uniform tissue-wide color warrants review (HPA tissue IHC: High in those glandular cells; HPA subcellular: cytosol; UniProt P00352; general IHC practice).
How each factor affects the staining
Cell-specific reference intensityHPA reports High staining in epididymal and stomach glandular cells, Medium in hepatocytes and several other named populations, and Low in selected neuronal, respiratory and glandular populations (HPA tissue IHC). Match intensity to the cell type when choosing a comparator.
Undetected reference populationsHPA lists Not detected for specified cells, including adrenal glandular cells, esophageal squamous epithelial cells and heart cardiomyocytes (HPA tissue IHC). These are cell-specific observations, so whole-organ positive or negative labels would overstate the evidence.
Antibody validationHPA lists IHC as Enhanced for HPA002123 and CAB020690; its tissue profile reports Enhanced reliability but medium agreement with RNA data (HPA antibodies; HPA tissue IHC). Use the protein staining pattern as a reference, with that agreement limit in mind.
Protein form and compartmentUniProt lists no signal peptide, transmembrane segment or isoforms and annotates a 2–501 chain (UniProt P00352). These entries support a cytosolic interpretation; they do not identify an antibody epitope or establish an antigen retrieval condition.
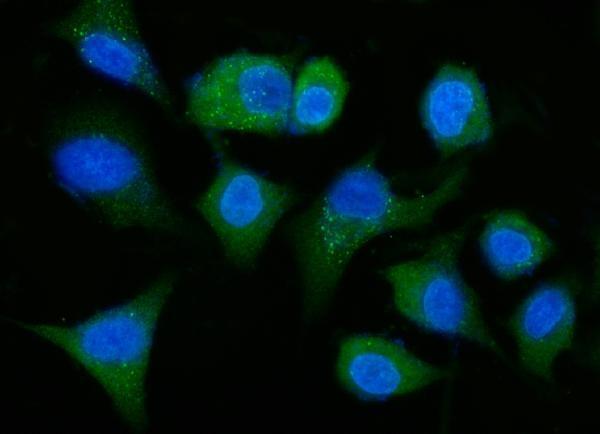
IF/ICC: what should the signal look like?Expect cytosolic fluorescence: HPA calls cytosol the enhanced main location and lists no additional location (HPA subcellular). This localization answers the IF/ICC pattern question; staining conditions belong in the separate IF/ICC guide.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
High-reference glandular cells show no chromogenic signal.The run may have inadequate detection or an unsuitable staining condition; the supplied sources do not identify a target-specific fixation or retrieval failure (general IHC practice; HPA tissue IHC: High in epididymal and stomach glandular cells).Confirm the control section, primary antibody and detection steps; review the antibody's validated IHC-P instructions before changing conditions (general IHC practice). Do not score the specimen negative until the control works.
Signal is mainly nuclear or outlines cell membranes.That distribution conflicts with the reported cytosolic location and lack of a transmembrane segment (HPA subcellular; UniProt P00352).Check the compartment against morphology and the counterstain, then compare positive and negative controls (general IHC practice). Treat the discordant pattern as unconfirmed rather than scoring it as ALDH1A1.
An HPA-listed undetected population appears strongly positive.Cross-reactivity or detection background is possible (general IHC practice); HPA reports Not detected only for the specified cell type in each listed tissue (HPA tissue IHC).Verify cell identity and compare a no-primary control with a listed positive population (general IHC practice; HPA tissue IHC). Investigate persistent cell-specific staining before interpreting it as expression.
Color or haze extends evenly across cells and extracellular spaces.A non-cell-specific pattern can reflect background from blocking, washes or chromogenic detection (general IHC practice). It does not resemble HPA's cytoplasmic expression in selected tissues (HPA tissue IHC).Inspect the no-primary control, review blocking and washes, and check chromogen development (general IHC practice). Reassess localization only after the background is low enough to resolve individual cells.
A section seems negative because only a low-reference population was examined.HPA lists Low staining in cells such as lung alveolar cells and duodenal glandular cells; weaker signal there is expected relative to its High glandular references (HPA tissue IHC).Compare the same cell type and compartment across sections, and include a listed High population as a run control when available (HPA tissue IHC; general IHC practice).
Staining of erythrocytes complicates interpretation.UniProt reports ALDH1A1 protein expression in erythrocytes (UniProt P00352); chromogenic background can also complicate interpretation (general IHC practice). Color in erythrocytes alone cannot establish its cause.Assess erythrocyte staining alongside a no-primary control and the expected glandular or hepatocyte pattern (general IHC practice; HPA tissue IHC). Avoid using erythrocyte color alone to validate the run.

Sample controls for ALDH1A1 IHC & IF

🧪Run epididymis first: its glandular cells should show ALDH1A1 staining (HPA: High in epididymis glandular cells). Use adrenal gland as the negative tissue (HPA: Not detected in adrenal gland glandular cells); on the epididymis slide, cells without specific cytosolic signal should remain at background, without assuming every nonglandular cell is negative (HPA subcellular: cytosol).
Positive control tissue: Epididymis (Glandular cells, HPA High)
Negative control tissue: Adrenal gland (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show ALDH1A1 in A-549, Hep-G2, BJ hTERT+ SV40 Large T+, BJ hTERT+ SV40 Large T+ RasG12V, BJ [Human fibroblast], BJ1-hTERT, with annotated localisation: Cytosol (enhanced) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control; a concentration-matched rabbit IgG isotype control (A01392 IHC caption: rabbit primary antibody); and an independently verified ALDH1A1 knockout specimen as a biological negative. For the epididymis slide, check endogenous peroxidase and biotin background because the reported detection uses a streptavidin–biotin complex with DAB (A01392 IHC caption).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A01392 tissue-IHC caption does not state its fixative (A01392 IHC caption). Heat retrieval in citrate buffer at pH 6 for 20 minutes is reported, but retrieval dependence and whether frozen sections or IF/ICC are easier are unreported (A01392 IHC caption). For IF/ICC, expect cytosolic localisation and check autofluorescence in the specimen being used (HPA subcellular: cytosol).

HPA tissue IHC evidence for ALDH1A1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Epididymis Glandular cells High Protein (IHC) HPA →
Stomach Glandular cells High Protein (IHC) HPA →
Adipose tissue Adipocytes Medium Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Medium Protein (IHC) HPA →
Gallbladder Glandular cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Cerebral cortex Endothelial cells Not detected Protein (IHC) HPA →
Cervix Glandular cells Not detected Protein (IHC) HPA →
Colon Endothelial cells Not detected Protein (IHC) HPA →
Section 3

Advanced ALDH1A1 IHC Tips

Troubleshoot ALDH1A1 staining in paraffin sections by checking retrieval, cytosolic localisation, cell identity and detection controls before comparing scores.

How should I adjust retrieval when ALDH1A1 staining is weak in paraffin sections?
Start with heat-mediated citrate retrieval at pH 6 for 20 minutes (datasheet A01392). Keep section thickness, heating, cooling and primary incubation consistent while comparing test sections, because changes in several steps obscure the cause of weak staining (standard IHC practice). The pictured paraffin-section workflow used 1 μg/mL primary antibody overnight at 4°C, so it provides a practical starting condition for this antibody (datasheet A01392). If staining remains weak after checking controls, compare a carefully titrated alternative retrieval buffer as a fallback, assessing tissue damage and background alongside signal (standard IHC practice).
Could fixation explain weak or patchy ALDH1A1 staining?
The selected paraffin-section caption does not state a fixative, so ALDH1A1 sensitivity to fixation is unknown for this antibody (datasheet A01392). Record fixative, fixation duration, processing schedule and section age for each case before attributing variable staining to the antigen (standard IHC practice). Compare sections processed under matched conditions and include a known positive control on each run; differences confined to one processing batch warrant a workflow review (standard IHC practice). Avoid assigning a target-specific fixation effect from tissue expression patterns or protein modifications, because neither measures how this antibody's epitope survives fixation (HPA tissue IHC; UniProt P00352).
What staining compartment should count as ALDH1A1 positive?
Score convincing cytoplasmic staining in intact cells, consistent with ALDH1A1's cytosolic localisation (UniProt P00352; HPA subcellular). Its sequence has no annotated transmembrane segment, so isolated crisp membrane outlining deserves scrutiny before it is counted as specific staining (UniProt P00352 topology). Check the stained cell against morphology and the counterstain, then compare the same compartment in positive and low-expression control material (standard IHC practice; HPA tissue IHC). UniProt also records an axonal location, but that annotation should not turn diffuse extracellular staining or nuclear-only signal into an accepted paraffin-section pattern (UniProt P00352; standard IHC practice).
How can I assess an unexpected staining pattern without assuming an ALDH1A1 isoform?
The supplied record lists 0 isoforms and no annotated transmembrane segment, so an unexpected compartment does not establish an alternative ALDH1A1 isoform (UniProt P00352). First verify the antibody's stated immunogen and epitope information, if available, and check whether the observed pattern follows that epitope's expected accessibility after retrieval (standard IHC practice). ALDH1A1 has annotated acetylated and phosphorylated residues, but this record does not show that any modification alters recognition by A01392 (UniProt P00352; datasheet A01392). Compare staining across retrieval and primary-antibody titrations with appropriate controls, and treat persistent discordance as a specificity question requiring independent validation (standard IHC practice).
How should I investigate ALDH1A1 localisation by IF alongside tissue IHC?
Use IF as a separate localisation check, with an expected cell-type marker chosen for the specimen, and assess overlap at the single-cell level (standard IF practice; HPA tissue IHC). HPA reports ALDH1A1 in the cytosol, so permeabilisation should allow antibody access to an intracellular epitope; optimise it against cell preservation and background (HPA subcellular; standard IF practice). Choose a fluorophore channel away from strong tissue autofluorescence and inspect an unstained specimen before interpreting weak signal (standard IF practice). Compare the IF compartment with cytoplasmic chromogenic staining, while treating the A01392 paraffin-section caption as IHC evidence only (datasheet A01392; HPA subcellular).
How can I separate ALDH1A1 signal from chromogenic background?
Inspect a no-primary control and a known positive section beside the test section to identify staining attributable to the detection workflow (standard IHC practice). The pictured workflow used 10% goat-serum blocking, a biotinylated secondary, a streptavidin-biotin complex and DAB, so assess nonspecific secondary binding and endogenous biotin where relevant (datasheet A01392; standard IHC practice). Include a peroxidase block for DAB detection and examine deposits in vessels, damaged edges and necrotic areas before calling cells positive (standard IHC practice). Titrate the primary and detection conditions if background persists, while requiring cytoplasmic signal in morphologically intact cells (standard IHC practice; HPA subcellular).
What is a defensible way to score ALDH1A1 IHC across specimens? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and viable analysis area before scoring, then record the percentage of cells with convincing cytoplasmic staining (standard IHC practice; HPA subcellular). An H-score can combine intensity categories with their cell percentages, provided the intensity scale and thresholds are fixed before comparisons (standard IHC practice). For spatial analyses, report positive cells per mm² of viable tissue and normalise to the measured area, rather than the whole image or a field containing empty space (standard IHC practice). Keep exposure, counterstain, detection batch and positive-control performance consistent, and report separate scores for distinct compartments or cell populations (standard IHC practice).
When is ALDH1A1 staining likely genuine rather than an artefact?
A credible result shows reproducible cytoplasmic staining in intact cells, with control sections behaving as expected (HPA subcellular; standard IHC practice). HPA reports high staining in epididymal and stomach glandular cells and medium staining in hepatocytes, providing cell-specific reference patterns rather than a rule that every cell must stain (HPA tissue IHC). Question nuclear-only or isolated membrane staining, staining confined to cut edges or necrosis, and brown deposits also present without primary antibody (UniProt P00352 topology; standard IHC practice). Check endogenous peroxidase with an appropriate detection control, and resolve unexpected positive cells by morphology and an independent cell marker where needed (standard IHC practice).
Boster reagents

Best ALDH1A1 / Aldehyde dehydrogenase 1A1 IHC Antibodies

The catalog covers human, mouse and rat reactivity, with IHC images from human and mouse tissues and IF/ICC images from A431 and A549 cells (catalog reactivity and image captions).

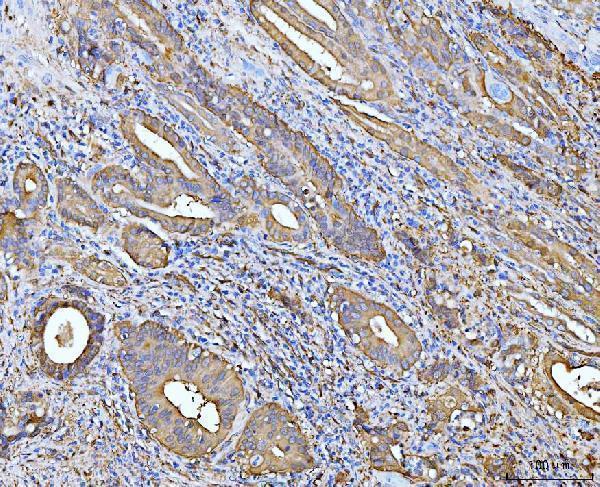
Real IHC data IHC analysis of ALDH1A1 using anti-ALDH1A1 antibody (A01392). ALDH1A1 was detected in paraffin-embedded section of human renal cancer tissues. Heat mediated antigen retrieval was performed in citrate buffer (pH6, epitope retrieval solution) for 20 mins. The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml rabbit anti-ALDH1A1 Antibody (A01392) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC)(Catalog # SA1022) with DAB as the chromogen.
Anti-Retinal dehydrogenase 1 ALDH1A1 Antibody ®
Cat # A01392
Real IHC data IHC analysis of ALDH1A1 using anti-ALDH1A1 antibody (M01392-2). ALDH1A1 was detected in a paraffin-embedded section of human gall bladder adenosquamous carcinoma tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml mouse anti-ALDH1A1 Antibody (M01392-2) overnight at 4°C. Biotinylated goat anti-mouse IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1021) with DAB as the chromogen.
Anti-ALDH1A1 Antibody ® (monoclonal, 4C3)
Cat # M01392-2
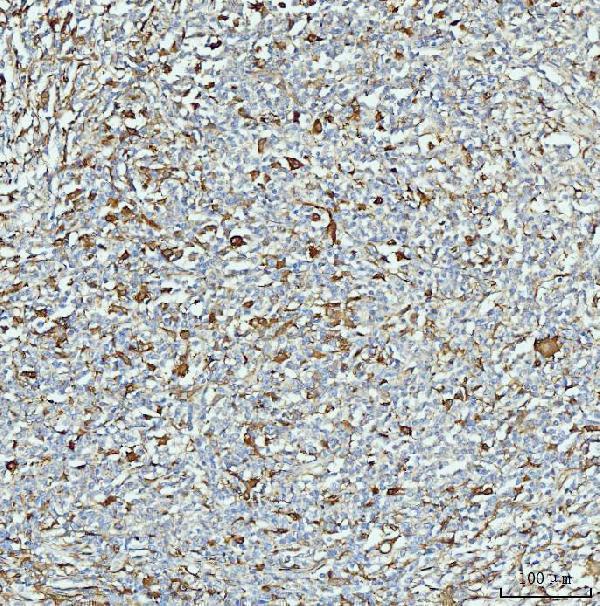
Real IHC data IHC analysis of ALDH1A1 using anti-ALDH1A1 antibody (PA1671). ALDH1A1 was detected in a paraffin-embedded section of human lung cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-ALDH1A1 Antibody (PA1671) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-Retinal dehydrogenase 1 ALDH1A1 Antibody ®
Cat # PA1671
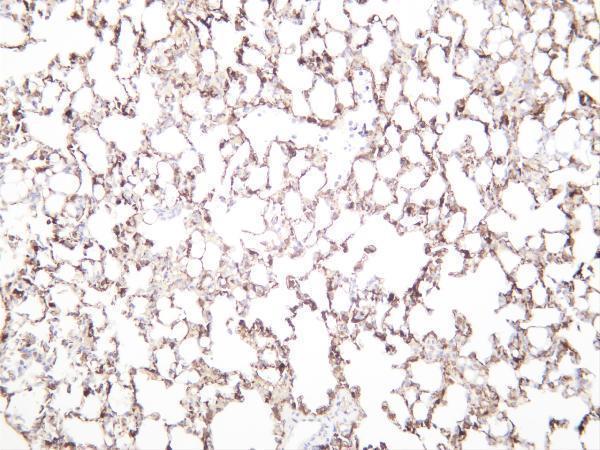
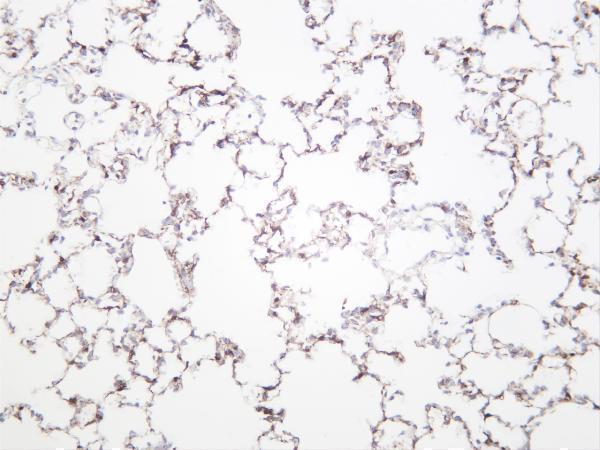
Real IHC data Mouselung was stained with anti-ALDH1A1 rabbit antibody
Anti-ALDH1A1 Rabbit Monoclonal Antibody
Cat # M01392-3
Real IHC data Immunohistochemical analysis of paraffin-embedded human liver cancer, using ALDH1A1 Antibody.
Anti-ALDH1A1 Rabbit Monoclonal Antibody
Cat # M01392-1

A01392 has paraffin-section IHC images from human renal cancer, M01392-2 from human gall bladder adenosquamous carcinoma, and PA1671 from human lung cancer (respective IHC captions). M01392-3 has mouse, rat and human lung IHC captions; M01392-1 has a paraffin-section human liver cancer IHC caption (respective IHC captions).

Which to pick: For paraffin-section IHC, start with A01392 at 0.5–1 μg/ml; its renal cancer caption reports citrate retrieval at pH 6 for 20 minutes and DAB detection, but does not report the fixative (catalog A01392 dilution; A01392 IHC caption). For IF/ICC, choose A01392 for its A431 and A549 images at 2 μg/ml (A01392 IF captions). For cross-species IHC, choose rabbit monoclonal M01392-3: it lists human, mouse and rat reactivity, has lung IHC captions for all three, and specifies 1:500–1:2000; its captions do not report fixation or retrieval (catalog M01392-3; M01392-3 IHC captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P00352 (AL1A1_HUMAN, Aldehyde dehydrogenase 1A1).
  2. Human Protein Atlas. ALDH1A1 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. ALDH1A1 subcellular location (ICC-IF): Localized to the cytosol..
  4. Human Protein Atlas. ALDH1A1 antibody validation summary (2 antibodies).
  5. A neutrophil-biomimic platform for eradicating metastatic breast cancer stem-like cells by redox microenvironment modulation and hypoxia-triggered differentiation therapy. Acta pharmaceutica Sinica. B 2023 — PMC9939302.
  6. Low expression of aldehyde dehydrogenase 1A1 (ALDH1A1) is a prognostic marker for poor survival in pancreatic cancer. BMC cancer 2011 — PMC3135572.
  7. ALDH1A1 expression is associated with poor differentiation, 'right-sidedness' and poor survival in human colorectal cancer. PloS one 2018 — PMC6181398.
  8. Colorectal adenoma stem-like cell populations: associations with adenoma characteristics and metachronous colorectal neoplasia. Cancer prevention research (Philadelphia, Pa.) 2013 — PMC4079278.
  9. PubMed PMID:2591967 — UniProt-cited evidence.
  10. PubMed PMID:8214422 — UniProt-cited evidence.
  11. PubMed PMID:19296407 — UniProt-cited evidence.