MCM2 / DNA replication licensing factor MCM2 · IHC design guide

Design Immunohistochemistry for MCM2

Plan paraffin-section MCM2 IHC around distinct nuclear staining in proliferative cells (HPA tissue IHC). Use the catalog antibody’s IHC-P conditions as a starting point and compare nuclear staining across tissue regions with different proliferative-cell content (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
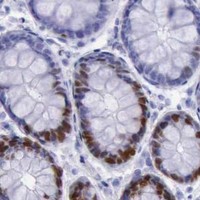
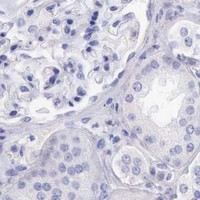
Immunohistochemistry protocol sheet for MCM2 (IHC for MCM2): expected localisation Nuclear staining in proliferative cells (HPA tissue IHC), antibody M00374, validated IHC image, and IHC protocol steps
Printable MCM2 IHC protocol sheet — expected localisation Nuclear staining in proliferative cells (HPA tissue IHC), antibody M00374, controls and protocol steps. Open the full MCM2 IHC guide →

MCM2 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nuclear staining in proliferative cells (HPA tissue IHC)
Staining pattern Distinct nuclear staining in proliferative cells (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet M00374)
Positive control ⓘ Appendix+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Staining varies with proliferative-cell content (HPA tissue IHC)
Regulation Enriched in proliferative cells (HPA tissue IHC)
Isoform / epitope No isoforms annotated; chain spans residues 2–904 (UniProt)
Section 1

Recommended MCM2 IHC & IF Protocols

The catalog antibody’s IHC-P protocol (datasheet: M00374) appears alongside four published MCM2 IHC protocols (PMC1343577; PMC3715081; PMC3140260; PMC6982666).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human bladder cancer tissue; fixative not specified (datasheet M00374)
FixationImage fixative and duration unreported (datasheet M00374); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet M00374); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet M00374)
Primary antibodyRabbit monoclonal (clone BCA-13) anti-MCM2, 1:50 (datasheet M00374)
Primary incubationOvernight at 4 °C (datasheet M00374)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet M00374)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
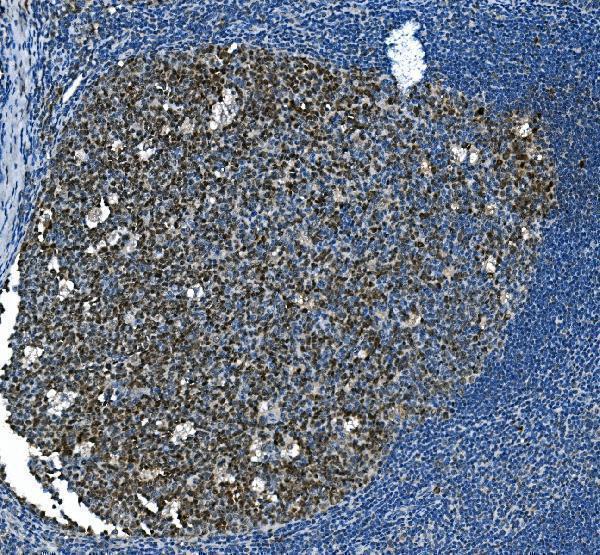
Expected resultMCM2-positive staining in germinal center cells of appendix (HPA tissue IHC: High). HPA tissue profile: Distinct nuclear expression in proliferative cells. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet: M00374); use each article’s stated retrieval when reproducing its protocol (cited PMC).
Section 2

What Is the Expected MCM2 Staining Pattern?

MCM2 should stain nuclei in proliferative cells: UniProt places it in the nucleus and on chromosomes, while HPA reports distinct nuclear expression in proliferative cells (UniProt P49736; HPA: tissue IHC, Enhanced reliability). Its lack of a transmembrane segment supports a nuclear rather than membrane pattern (UniProt P49736 topology).

What am I looking at on my slide?
Distinct nuclear staining in germinal center cells or hematopoietic cells.This matches HPA's high staining in appendix and lymph node germinal centers and bone marrow hematopoietic cells (HPA: tissue IHC). Judge the pattern by the stained cells and their nuclear compartment; HPA's tissue-level reliability is Enhanced, meaning staining is highly consistent with RNA expression (HPA: tissue IHC).
Predominantly cytoplasmic or membrane staining, with little nuclear signal.Treat this as discordant with the expected IHC pattern (UniProt P49736: nucleus and chromosome; HPA: distinct nuclear expression). Check the antibody's IHC validation, detection controls and slide morphology before assigning it to MCM2. HPA reports additional cytosol and vesicle locations as uncertain in ICC-IF; that does not establish a cytoplasmic IHC pattern (HPA: subcellular).
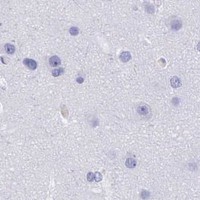
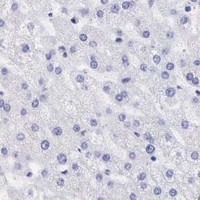
Strong staining in adipocytes or cardiomyocytes.These cell types are listed as not detected (HPA: adipose tissue adipocytes; heart muscle cardiomyocytes). Recheck cell identification and compare a no-primary control. Persistent staining could reflect cross-reactivity or endogenous chromogenic detection activity (general IHC practice); the tissue result alone cannot distinguish those causes.
Diffuse color across nuclei, cytoplasm and tissue spaces.A widespread, poorly localized deposit is difficult to reconcile with distinct nuclear expression (HPA: tissue IHC). Inspect a no-primary control and the counterstain, then review blocking, washes and development time (general IHC practice). Background in that control points toward the detection workflow rather than a defensible MCM2-positive cell assignment (general IHC practice).
No nuclear signal in a known-positive tissue section.High staining is reported in lymph node germinal center cells, bone marrow hematopoietic cells and placental cytotrophoblasts (HPA: tissue IHC). Confirm that the relevant cells are present, then check the IHC antibody, retrieval, detection reagents and controls (general IHC practice). A blank section alone does not establish absent MCM2 expression.
💡Expected MCM2 appearanceCall a section positive when the relevant proliferative cells show distinct nuclear chromogenic staining, including high staining in HPA-listed germinal center cells; prominent membrane or diffuse cytoplasmic color is discordant (HPA: tissue IHC; UniProt P49736 topology).
How each factor affects the staining
Cell population and tissueHPA reports high staining in germinal center cells, bone marrow hematopoietic cells, placental cytotrophoblasts and preleptotene spermatocytes; skin spinous-layer cells and colon enterocytes are medium, while adipocytes and cardiomyocytes are not detected (HPA: tissue IHC). Choose a control by its named cell population, not its tissue label alone.
Nuclear and chromatin associationMCM2 is nuclear and chromosomal; UniProt describes chromatin association before nuclei form and detachment as DNA replication progresses (UniProt P49736). This supports assessing nuclear localization while allowing for cell-cycle-dependent appearance. It does not provide an IHC scoring threshold or justify calling widespread cytoplasmic staining positive.
IHC antibody validationHPA lists IHC as Enhanced for HPA031495, HPA031496 and CAB000303, while HPA031450 has no IHC status in the supplied antibody record (HPA: antibodies). Match any comparison to the antibody actually used. HPA's Enhanced tissue-profile reliability describes consistency with RNA data; it is a separate assessment (HPA: tissue IHC).
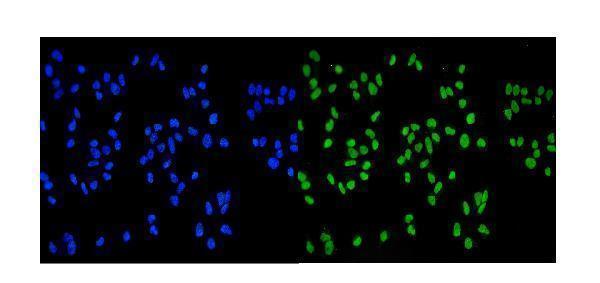
IF/ICC: should the same compartment be expected?Yes: the supported main ICC-IF location is nucleoplasm (HPA: subcellular). HPA also lists vesicles, primary cilium and cytosol as uncertain additional locations, so those signals should not override a nuclear interpretation (HPA: subcellular). IF/ICC assay details belong in its separate guide.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Positive-control section is blank.The selected section may lack the named positive cells, or the IHC workflow may have failed (HPA: tissue IHC; general IHC practice).Verify germinal center cells in a lymph node section or hematopoietic cells in bone marrow, both high by HPA; then review antibody identity, retrieval and detection controls (HPA: tissue IHC; general IHC practice).
Only cytoplasm or cell borders are colored.This conflicts with MCM2's nuclear and chromosomal location; the additional cytosol location is uncertain in ICC-IF (UniProt P49736; HPA: subcellular).Compare nuclear morphology and a no-primary control, then review antibody validation and detection conditions (general IHC practice; HPA: antibodies). Do not score the nonnuclear deposit as the expected IHC result.
Adipocytes or cardiomyocytes appear strongly positive.Both are reported as not detected (HPA: tissue IHC); nonspecific binding or endogenous detection activity are possible IHC causes (general IHC practice).Confirm cell identity, run a no-primary control and check the relevant blocking and detection steps (general IHC practice). Interpret any remaining signal against the HPA cell-specific result.
The whole section has diffuse brown background.Broad deposit obscures the distinct nuclear pattern reported by HPA (HPA: tissue IHC); incomplete blocking, washing or excessive development can contribute (general IHC practice).Inspect a no-primary control; review blocking, washes and chromogen development using the assay's established procedure (general IHC practice). Reassess only clearly resolved nuclei.
A low-staining tissue gives few positive nuclei.HPA lists salivary gland and stomach glandular cells, duodenal enterocytes and several other cell populations as low (HPA: tissue IHC).Use an HPA high-staining cell population as a positive control before treating sparse staining as an assay failure (HPA: tissue IHC). Score the observed cells and compartment separately from overall tissue intensity.
Two sections show different fractions of stained nuclei.HPA describes expression in proliferative cells, and UniProt links MCM2 to DNA replication and cell division (HPA: tissue IHC; UniProt P49736 function). Different sampled cell populations may therefore produce different fractions.Compare matching tissue regions and named cell populations under the same scoring rule (general IHC practice). Check that nuclear staining remains distinct before interpreting a difference as biological.

Sample controls for MCM2 IHC & IF

🧪Run lymph node first: germinal center cells should show nuclear staining (HPA: High in lymph node germinal center cells; UniProt P49736: nucleus). Use adipose tissue as the negative tissue, where adipocytes are not detected; within the lymph node slide, morphologically quiescent cells outside germinal centers should lack comparable nuclear staining, although scattered proliferating cells may stain (HPA: Not detected in adipocytes; HPA: High in germinal center cells; UniProt P49736: cell cycle).
Positive control tissue: Appendix (Germinal center cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show MCM2 in HEL, SiHa, U2OS, A-431, MCF-7, ASC52telo, RPTEC/TERT1, hTERT-RPE1 (serum starved), NIH 3T3, with annotated localisation: Nucleoplasm (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control; an isotype control matched to the primary antibody’s host species and clonality; and a biological negative using MCM2 knockout material or a peptide block if the antibody’s immunizing peptide is available (standard IHC controls; selected M00374 caption: rabbit primary antibody). In lymph node, block endogenous peroxidase and assess background from endogenous biotin if using biotin-based detection, or check autofluorescence for IF (standard IHC/IF practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected M00374 paraffin-section caption does not state a fixative (selected M00374 caption). The reported IHC example uses heat retrieval in EDTA at pH 8.0, so start there and verify staining against the tissue controls; the payload does not establish whether frozen sections or IF are easier (selected M00374 caption; HPA: High in lymph node germinal center cells). Lymph node immune cells can produce peroxidase-related background in chromogenic IHC, making the no-primary slide useful when interpreting weak signal (standard IHC practice).

HPA tissue IHC evidence for MCM2

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — High consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Appendix Germinal center cells High Protein (IHC) HPA →
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Lymph node Germinal center cells High Protein (IHC) HPA →
Placenta Cytotrophoblasts High Protein (IHC) HPA →
Skin Cells in spinous layer Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Bronchus Basal cells Not detected Protein (IHC) HPA →
Caudate Glial cells Not detected Protein (IHC) HPA →
Cerebellum Cells in granular layer Not detected Protein (IHC) HPA →
Section 3

Advanced MCM2 IHC Tips

Troubleshoot MCM2 staining in paraffin sections by checking retrieval, nuclear localisation, cell context and assay controls (datasheet M00374; UniProt P49736; HPA tissue IHC).

How should I retrieve MCM2 when nuclear staining is weak in paraffin sections?
Start with heat-mediated antigen retrieval in EDTA at pH 8.0 for paraffin sections (datasheet M00374). The documented image used a 1:50 primary antibody dilution overnight at 4°C, so keep those conditions consistent while assessing retrieval (datasheet M00374). Compare a known positive compartment, such as lymph node germinal center cells, across sections processed together (HPA tissue IHC: High in germinal center cells; standard IHC practice). If signal remains weak, adjust heating duration in a controlled series and check section adhesion and tissue morphology before accepting stronger staining as specific (standard IHC practice). Score nuclear signal separately from diffuse background because MCM2 is principally nuclear (UniProt P49736 localisation; HPA subcellular).
Can fixation explain weak or uneven MCM2 staining?
The M00374 tissue caption identifies a paraffin section but does not report its fixative; target-specific fixation sensitivity is therefore unknown (datasheet M00374). Record the fixative, fixation duration and processing history for each specimen before comparing staining intensity across cases (standard IHC practice). Process a positive control alongside test sections, then compare nuclear signal after the same EDTA pH 8.0 retrieval and 1:50 primary incubation (datasheet M00374; standard IHC practice). Uneven staining should prompt inspection of section thickness, folds and tissue preservation, with any fixation explanation treated as a hypothesis requiring matched specimens (standard IHC practice). Do not infer fixation tolerance from the reported HPA staining distribution (HPA tissue IHC; standard IHC practice).
What staining pattern should I accept as MCM2 in tissue sections?
Prioritise staining in nuclei of proliferative cells; MCM2 is reported in the nucleus and on chromosomes, and HPA describes distinct nuclear expression (UniProt P49736 localisation; HPA tissue IHC). In paraffin sections, use the hematoxylin counterstain to confirm that DAB overlaps nuclei rather than cytoplasm or luminal material (standard chromogenic IHC practice). Germinal center cells in lymph node or appendix provide documented high-staining cell populations for pattern comparison (HPA tissue IHC: High in germinal center cells). MCM2 associates with chromatin before nuclei form and detaches as replication progresses, so variation in nuclear intensity can reflect cell-cycle state (UniProt P49736 localisation). Treat dominant cytoplasmic staining as a specificity concern pending controls (HPA subcellular: nucleoplasm supported; standard IHC practice).
Could an epitope or MCM2 modification explain discordant staining?
The supplied UniProt record lists 0 isoforms, but the M00374 caption does not map the antibody epitope (UniProt P49736 isoforms; datasheet M00374). MCM2 has annotated phosphorylation sites near its N terminus and an MCM C-terminal AAA(+) ATPase domain spanning residues 456–808 (UniProt P49736 modified residues and domains). Without an epitope map, do not attribute a staining difference to phosphorylation, domain masking or a particular sequence region (UniProt P49736; standard antibody validation practice). Compare the IHC-validated antibody with an independently validated epitope reagent or an appropriate biological control if those materials are available (standard IHC practice). Keep EDTA pH 8.0 retrieval constant during that comparison so processing does not confound interpretation (datasheet M00374; standard IHC practice).
How can IF help resolve ambiguous MCM2 staining in paraffin sections?
Use IF as a separate, validated assay to check whether the signal aligns with nuclei and an expected cell population, such as germinal center cells (HPA tissue IHC: High in germinal center cells; standard IF practice). Multiplex a nuclear counterstain with a validated marker for that population, and choose fluorophores after checking the specimen’s autofluorescence in each channel (standard IF practice). MCM2 has no transmembrane segment and is mainly nucleoplasmic, so an intracellular epitope generally requires permeabilisation; optimise detergent exposure against nuclear preservation (UniProt P49736 topology; HPA subcellular: nucleoplasm supported; standard IF practice). Include single-colour and secondary-only controls to assess bleed-through and nonspecific fluorescence before comparing IF with DAB staining (standard IF practice). The paraffin IHC caption supplies no IF-specific fixation or permeabilisation settings (datasheet M00374).
How do I distinguish MCM2 signal from chromogenic background?
Inspect no-primary and secondary-only controls alongside the tissue section to locate nonspecific DAB deposition (standard chromogenic IHC practice). The documented workflow used 10% goat serum blocking, a 1:50 primary overnight at 4°C, and a peroxidase-linked secondary for 30 minutes at 37°C (datasheet M00374). Include a peroxidase block as a general DAB workflow step, then check whether colour persists without primary antibody (standard chromogenic IHC practice). If background is widespread, review blocking, washing, primary concentration and DAB development while changing one condition at a time (standard IHC practice). Count nuclear staining in expected cells separately from extracellular pigment or diffuse cytoplasmic colour (HPA tissue IHC: distinct nuclear expression; standard IHC practice).
What is a defensible way to quantify MCM2 IHC? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and tissue region before scoring, then report the percentage of cells with nuclear staining (standard IHC quantification practice; HPA tissue IHC: distinct nuclear expression). If intensity matters, use an H-score from 0–300 by weighting the percentages at each intensity grade, with thresholds set before reviewing groups (standard IHC quantification practice). For spatial comparisons, report positive nuclei per mm² of viable tissue and retain the total nuclei counted as the denominator (standard IHC quantification practice). Normalise within the same cell population and comparable processing batch, using a shared positive control to monitor run variation (standard IHC practice). Exclude folds and necrotic areas, and report sampling regions and scoring rules so another reader can reproduce the measurement (standard IHC practice).
When should apparent MCM2 positivity be treated as an artefact?
A credible result shows nuclear staining in a plausible proliferative population, consistent with MCM2’s replication role and the HPA nuclear tissue pattern (UniProt P49736 function; HPA tissue IHC). Compare suspect signal with documented high-staining germinal center cells and with negative controls processed in the same run (HPA tissue IHC: High in germinal center cells; standard IHC practice). Predominantly cytoplasmic colour, staining confined to section edges or necrotic tissue, and colour persisting without primary antibody warrant investigation before scoring (HPA subcellular: nucleoplasm supported; standard IHC practice). Check endogenous peroxidase activity when DAB appears in the no-primary control (standard chromogenic IHC practice). Interpret differences as changes in the fraction of stained nuclei within comparable cell populations, rather than as proof of replication rate (UniProt P49736 function; standard IHC interpretation practice).
Boster reagents

Best MCM2 / DNA replication licensing factor MCM2 IHC Antibodies

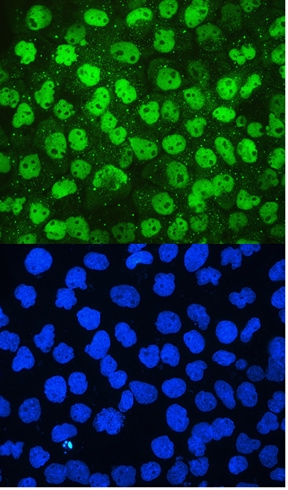
Anti-MCM2 antibodies have IHC images from human cancer paraffin sections (catalog IHC captions) and IF/ICC images from A431, HeLa and U20S cells (catalog IF captions).

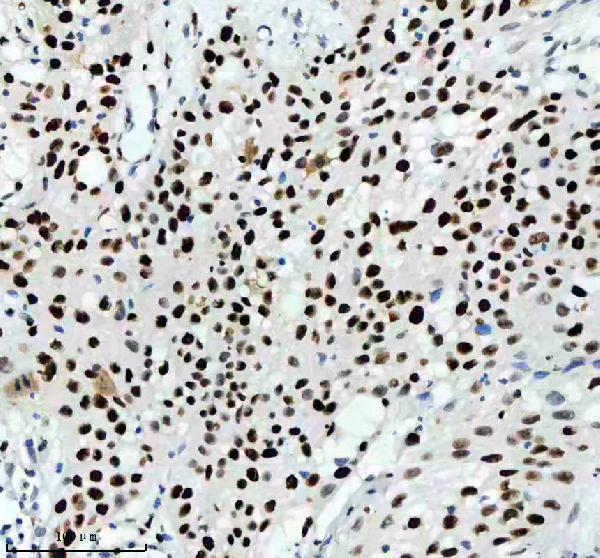
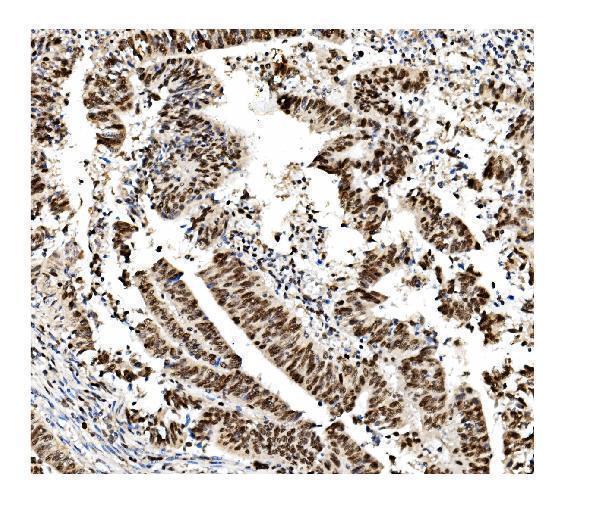
Real IHC data IHC analysis of MCM2 using anti-MCM2 antibody (M00374). MCM2 was detected in a paraffin-embedded section of human bladder cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1:50 rabbit anti-MCM2 Antibody (M00374) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-MCM2 Rabbit Monoclonal Antibody
Cat # M00374
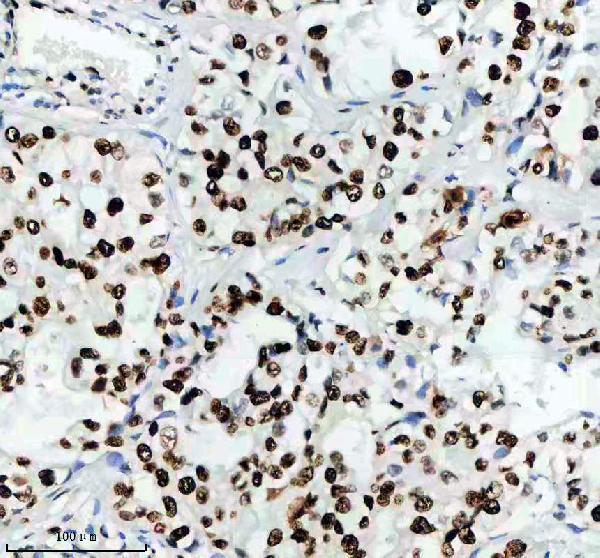
Real IHC data IHC analysis of MCM2 using anti-MCM2 antibody (A00374-1). MCM2 was detected in paraffin-embedded section of human intestinal cancer tissues. Heat mediated antigen retrieval was performed in citrate buffer (pH6, epitope retrieval solution) for 20 mins. The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml rabbit anti-MCM2 Antibody (A00374-1) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC)(Catalog # SA1022) with DAB as the chromogen.
Anti-MCM2 Antibody ®
Cat # A00374-1
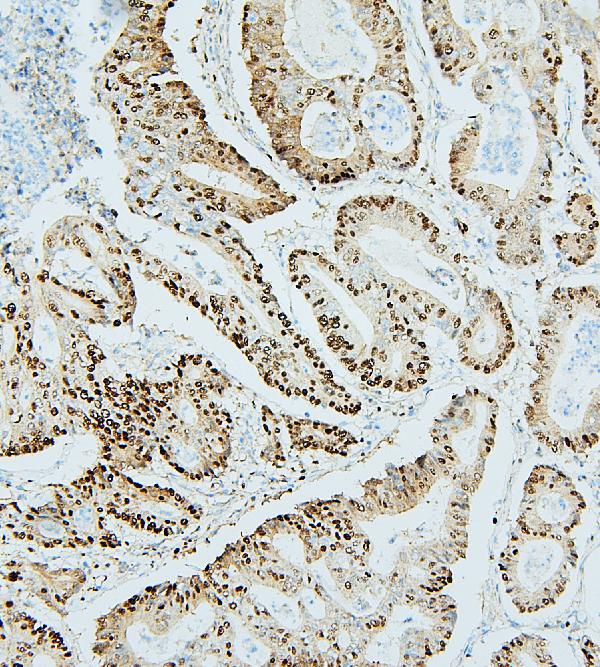
Real IHC data IHC analysis of MCM2 using anti-MCM2 antibody (M00374-1). MCM2 was detected in paraffin-embedded section of human rectal cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml mouse anti-MCM2 Antibody (M00374-1) overnight at 4°C. Biotinylated goat anti-mouse IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1021) with DAB as the chromogen.
Anti-MCM2 Antibody ® (monoclonal, 11C4)
Cat # M00374-1
Real IHC data Anti-MCM2 antibody, PA1650, IHC(P) IHC(P): Human Lung Cancer Tissue
Anti-MCM2 Antibody ®
Cat # PA1650

M00374 has IHC data from human bladder cancer paraffin sections (M00374 IHC caption); A00374-1 has IHC data from human intestinal cancer paraffin sections and IF data from A431 cells (A00374-1 IHC and IF captions). M00374-1 has IHC data from human rectal cancer paraffin sections and IF data from HeLa cells (M00374-1 IHC and IF captions); PA1650 has IHC data from human lung cancer tissue and IF data from U20S cells (PA1650 IHC and IF captions).

Which to pick: For tissue IHC, choose rabbit monoclonal M00374 for a human paraffin section workflow using EDTA retrieval at pH 8.0 (M00374 catalog and IHC caption); its caption does not report the fixative (M00374 IHC caption). For IF/ICC, choose M00374-1 when a mouse monoclonal is useful: its application list includes IF and ICC, and its IF caption shows HeLa cells at 4 μg/ml (M00374-1 catalog and IF caption). For work across species, A00374-1 lists human, mouse and rat reactivity and has rat paraffin section IHC images; its human intestinal cancer IHC caption uses citrate retrieval at pH 6 and does not report the fixative (A00374-1 catalog and IHC captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P49736 (MCM2_HUMAN, DNA replication licensing factor MCM2).
  2. Human Protein Atlas. MCM2 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. MCM2 subcellular location (ICC-IF): Mainly localized to the nucleoplasm. In addition localized to vesicles, cytosol and primary cilium..
  4. Human Protein Atlas. MCM2 antibody validation summary (4 antibodies).
  5. Expression of minichromosome maintenance protein 2 as a marker for proliferation and prognosis in diffuse large B-cell lymphoma: a tissue microarray and clinico-pathological analysis. BMC cancer 2005 — PMC1343577.
  6. Immunohistochemical expression of minichromosome maintenance complex protein 2 predicts biochemical recurrence in prostate cancer: a tissue microarray and digital imaging analysis-based study of 428 cases. Human pathology 2012 — PMC3715081.
  7. Novel molecular markers of malignancy in histologically normal and benign breast. Pathology research international 2011 — PMC3140260.
  8. Minichromosome Maintenance Complex (MCM) Genes Profiling and MCM2 Protein Expression in Cervical Cancer Development. Asian Pacific journal of cancer prevention : APJCP 2019 — PMC6982666.
  9. PubMed PMID:8175912 — UniProt-cited evidence.
  10. PubMed PMID:7584026 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.