PINK1 / Serine/threonine-protein kinase PINK1, mitochondrial · IHC design guide

Design Immunohistochemistry for PINK1

Plan paraffin-section PINK1 staining around a generally cytoplasmic tissue profile with uncertain reliability (HPA tissue IHC). Start with the IHC-validated antibody M00201 at 1:25 and compare staining with matched controls (datasheet: IHC-P 1:25; standard IHC practice).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for PINK1 (IHC for PINK1): expected localisation Cytoplasmic tissue staining (HPA tissue IHC); mitochondrial PINK1 (UniProt), antibody M00201, validated IHC image, and IHC protocol steps
Printable PINK1 IHC protocol sheet — expected localisation Cytoplasmic tissue staining (HPA tissue IHC); mitochondrial PINK1 (UniProt), antibody M00201, controls and protocol steps. Open the full PINK1 IHC guide →

PINK1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic tissue staining (HPA tissue IHC); mitochondrial PINK1 (UniProt)
Staining pattern Cytoplasmic staining in glandular and trophoblastic cells (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Bone marrow+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Tissue staining reliability is uncertain (HPA tissue IHC)
Regulation Damage stabilizes outer-membrane PINK1 (UniProt)
Isoform / epitope 2 isoforms; processing warrants epitope mapping (UniProt)
Section 1

Recommended PINK1 IHC & IF Protocols

The catalog antibody’s IHC-P protocol is followed by three published PINK1 IHC protocols from paraffin sections (PMC13069790; PMC11551102; PMC10335790).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded H. stomach tissue; fixative not specified (datasheet M00201)
FixationImage fixative and duration unreported (datasheet M00201); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyMouse monoclonal (clone 38CT20.8.5) anti-PINK1, 1:25 (datasheet M00201)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultPINK1-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic expression. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 retrieval at 95–98 °C for 20 min (page antigen-retrieval rule); compare staining with tissue controls before changing conditions.
Section 2

What Is the Expected PINK1 Staining Pattern?

PINK1 localizes mainly to mitochondria, while smaller processed fragments localize mainly to cytosol; its UniProt record lists outer and inner mitochondrial membranes but no transmembrane segment (UniProt Q9BXM7 localization and topology). In paraffin tissue, expect predominantly cytoplasmic staining in HPA positive cell populations, especially placental trophoblasts and adrenal glandular cells (HPA tissue IHC). HPA rates the tissue pattern Uncertain, so interpret intensity cautiously (HPA tissue IHC).

What am I looking at on my slide?
Cytoplasmic chromogen in placental trophoblasts or adrenal glandular cells, with little signal in adjacent unstained structures (HPA tissue IHC).This fits HPA's general cytoplasmic profile and its High ratings for those cell types (HPA tissue IHC). Compare cells within the same section; the High rating does not guarantee uniform staining in every specimen (HPA tissue IHC; standard IHC practice).
Predominantly nuclear staining, without a convincing cytoplasmic component (HPA tissue IHC; UniProt Q9BXM7 localization).Nuclear localization is absent from the supplied PINK1 record and HPA describes general cytoplasmic expression (UniProt Q9BXM7 localization; HPA tissue IHC). Treat a nuclear-only pattern as suspect and check the no-primary control and antibody staining conditions (standard IHC practice).
Strong staining in cells HPA lists as Not detected, such as bone marrow hematopoietic cells or esophageal squamous epithelium (HPA tissue IHC).Consider cross-reactivity or endogenous detection activity, especially if expected positive cells are weak (standard IHC practice; HPA tissue IHC). A Not detected HPA result is an assay observation, not proof that every specimen must be blank (HPA tissue IHC).
Broad, diffuse color across cells and surrounding tissue, with little distinction between cellular compartments (standard IHC practice).This is difficult to score as PINK1's reported cytoplasmic pattern (HPA tissue IHC). Check the no-primary control, blocking, washing and chromogen development before assigning biological meaning (standard IHC practice).
No chromogen in an HPA High cell population, including placental trophoblasts or rectal glandular cells (HPA tissue IHC).First assess section integrity, retrieval, antibody dilution and detection controls (standard IHC practice). Because both listed HPA antibodies have Uncertain IHC validation, an absent result alone cannot establish absent PINK1 protein (HPA antibody validation).
💡Expected PINK1 appearanceCall a result consistent with the reference when cytoplasmic staining is strongest in an HPA High cell population, such as placental trophoblasts, while isolated nuclear-only or widespread cell-independent color is suspect (HPA tissue IHC; UniProt Q9BXM7 localization; standard IHC practice).
How each factor affects the staining
Localization and processing (UniProt Q9BXM7 localization).PINK1 is mainly mitochondrial, while two smaller proteolytic fragments localize mainly to cytosol (UniProt Q9BXM7 localization). A cytoplasmic IHC signal need not resolve individual mitochondria; compare its cellular distribution with the HPA tissue profile (HPA tissue IHC; standard IHC practice).
Tissue evidence differs by measurement (UniProt Q9BXM7 tissue specificity; HPA tissue IHC).UniProt reports high expression in skeletal muscle, yet HPA records skeletal myocytes as Not detected by tissue IHC and RNA specificity as enhanced in skeletal muscle and tongue (UniProt Q9BXM7 tissue specificity; HPA tissue IHC). Do not use skeletal muscle as an assured IHC positive control (HPA tissue IHC).
Strength of IHC evidence (HPA tissue IHC; HPA antibody validation).HPA rates the overall tissue pattern Uncertain because antibody staining and RNA data have medium consistency; both listed antibodies also have Uncertain IHC status (HPA tissue IHC; HPA antibody validation). Use morphology and appropriate controls before interpreting weak or unexpected staining (standard IHC practice).
IF/ICC Q&A: Is a specific fluorescent PINK1 pattern established here? (HPA subcellular ICC-IF).HPA provides no main subcellular location or ICC-IF image cell lines in this payload, so it does not establish an observed IF pattern (HPA subcellular ICC-IF). UniProt supports mitochondrial and cytosolic localization as biological context, not an IF validation result (UniProt Q9BXM7 localization).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
An HPA High population is blank (HPA tissue IHC).Insufficient detection, unsuitable retrieval or antibody dilution, or a section problem may suppress visible chromogen (standard IHC practice).Check tissue preservation and a functioning detection control; review the antibody's documented IHC-P conditions before adjusting retrieval or dilution (standard IHC practice). Interpret a persistently blank result in light of HPA's Uncertain rating (HPA tissue IHC).
The no-primary control develops color (standard IHC practice).Endogenous enzyme activity or detection reagent background can produce chromogen independently of primary antibody (standard IHC practice).Address endogenous activity for the chosen chromogenic system, reassess blocking and washes, then repeat the no-primary control alongside the specimen (standard IHC practice).
The entire section has hazy cytoplasmic color (standard IHC practice).Nonspecific binding or excessive chromogen development can obscure cell-level differences (standard IHC practice).Compare with the no-primary control and review blocking, antibody dilution, wash stringency and development time; score only a reproducible cellular pattern (standard IHC practice).
Staining is mainly nuclear (HPA tissue IHC; UniProt Q9BXM7 localization).The observed compartment conflicts with HPA's general cytoplasmic profile and the supplied UniProt localization (HPA tissue IHC; UniProt Q9BXM7 localization).Recheck morphology and counterstain, compare a known HPA High cell population, and inspect controls before assigning the nuclear signal to PINK1 (HPA tissue IHC; standard IHC practice).
A listed Not detected population stains strongly (HPA tissue IHC).Cross-reactivity or endogenous chromogenic activity is possible; HPA's Uncertain reliability also limits the reference pattern (standard IHC practice; HPA tissue IHC).Compare the no-primary control and a High reference population on the same run, then report the discrepancy without treating either result as definitive (standard IHC practice; HPA tissue IHC).
Skeletal myocytes show no signal despite expected expression from UniProt (UniProt Q9BXM7 tissue specificity).HPA tissue IHC lists skeletal myocytes as Not detected, despite UniProt's high tissue expression description (HPA tissue IHC; UniProt Q9BXM7 tissue specificity).Use an HPA High IHC population, such as placental trophoblasts, to assess the staining run; document the skeletal muscle discrepancy rather than changing the scoring threshold to force positivity (HPA tissue IHC; standard IHC practice).

Sample controls for PINK1 IHC & IF

🧪Run placenta first: trophoblastic cells should stain (HPA: High in placental trophoblastic cells). Use esophageal squamous epithelial cells as the negative tissue (HPA: Not detected); on the placenta slide, non-trophoblastic cells without brown signal can serve as background comparators, although their PINK1-negative status is unreported in the supplied HPA rows.
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Bone marrow (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA carries no ICC-IF cell line for PINK1; derive a cell-line control from the positive tissue's cell type (Glandular cells) and confirm it by RNA or western blot first.
Technical controls: Include a no-primary, secondary-only control and nonimmune IgG matched to the primary antibody’s host species and, for a monoclonal antibody, its isotype (standard IHC practice). Use PINK1-knockout material or a validated peptide-block control as a biological negative; quench endogenous peroxidase and, if using the caption’s biotinylated secondary, assess endogenous biotin before interpreting placental DAB staining (standard IHC practice; M00201 caption: biotinylated secondary and DAB).
⚠️Feasibility: A PINK1-specific fixation window and retrieval dependency are unreported in the supplied evidence; the M00201 paraffin-section caption gives a 1:25 dilution but does not report a fixative (M00201 caption). Frozen sections or IF may avoid paraffin retrieval, but the supplied evidence does not establish that either is easier for PINK1; no HPA ICC-IF image-bearing cell lines are listed (HPA subcellular payload). For placental DAB staining, check peroxidase and biotin background because the caption uses a biotinylated secondary (standard IHC practice; M00201 caption).

HPA tissue IHC evidence for PINK1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Uncertain — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Breast Myoepithelial cells High Protein (IHC) HPA →
Parathyroid gland Glandular cells High Protein (IHC) HPA →
Placenta Trophoblastic cells High Protein (IHC) HPA →
Rectum Glandular cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Esophagus Squamous epithelial cells Not detected Protein (IHC) HPA →
Oral mucosa Squamous epithelial cells Not detected Protein (IHC) HPA →
Skeletal muscle Myocytes Not detected Protein (IHC) HPA →
Soft tissue Fibroblasts Not detected Protein (IHC) HPA →
Section 3

Advanced PINK1 IHC Tips

Troubleshoot PINK1 chromogenic IHC in paraffin sections using the catalog antibody’s tissue image, reported localisation, and appropriate staining controls.

What retrieval should I try first when PINK1 staining is weak in paraffin sections?
Start with citrate buffer at pH 6.0, heated to 95–98 °C for 20 min (page retrieval setting). Let sections cool in buffer, then compare a serial section processed without retrieval to distinguish poor epitope exposure from background introduced by heating (standard IHC practice). The M00201 image establishes staining in a paraffin-embedded stomach section at 1:25, but its caption gives no retrieval condition (M00201 tissue-IHC caption). If staining remains weak, test a more alkaline retrieval buffer on matched sections while holding antibody dilution and detection constant; judge improvement against tissue morphology and a no-primary control (standard IHC practice).
How should I troubleshoot fixation-related loss of PINK1 staining?
The M00201 stomach image identifies a paraffin-embedded section but does not report its fixative, so target-specific fixation sensitivity is unknown (M00201 tissue-IHC caption). Record the fixative, fixation duration, processing schedule, and section age for each specimen before comparing staining intensity (standard IHC practice). When tissue is available, stain matched sections processed under different fixation conditions in the same run, using citrate pH 6.0 retrieval at 95–98 °C for 20 min (page retrieval setting; standard IHC practice). Check preserved morphology and a no-primary control before attributing an intensity difference to fixation rather than section quality or detection variability (standard IHC practice).
Should PINK1 appear mitochondrial or diffusely cytoplasmic by chromogenic IHC?
PINK1 is reported at the mitochondrial outer and inner membranes, while smaller processed fragments localize mainly in the cytosol (UniProt Q9BXM7 localisation). Healthy mitochondria import PINK1 for processing; membrane depolarization stalls import and promotes accumulation at the outer membrane (UniProt Q9BXM7 function). Thus, cytoplasmic staining alone cannot establish which molecular form is present, and chromogenic resolution cannot reliably assign fine staining to a particular mitochondrial membrane (UniProt Q9BXM7 localisation; standard IHC practice). Compare the distribution in intact cells with matched controls and morphology; HPA describes general cytoplasmic tissue staining but rates its tissue-IHC reliability as uncertain (HPA tissue IHC; standard IHC practice).
Can this antibody distinguish PINK1 isoforms or processed protein in sections?
PINK1 has 2 annotated isoforms, and the precursor is processed to a chain beginning at residue 78 (UniProt Q9BXM7 isoforms and processing). The catalog image calls the reagent “Pink1(115-213),” but the caption does not establish which isoforms or processed forms its tissue staining detects (M00201 tissue-IHC caption). Request documented immunogen and epitope mapping before making a form-specific claim; include an orthogonal control such as genetic depletion when feasible (standard IHC practice). Because the kinase domain spans residues 156–511 and autophosphorylation is annotated at 228 and 402, neither localisation nor staining intensity alone identifies a phosphorylation state (UniProt Q9BXM7 domains and modified residues; standard IHC practice).
How can I compare PINK1 immunofluorescence with the chromogenic IHC result?
Treat IF/ICC as a separate validation task: the M00201 caption documents chromogenic staining of a paraffin-embedded stomach section, with an unreported fixative, and supplies no IF condition (M00201 tissue-IHC caption). Multiplex PINK1 with a marker for the cell population being assessed and, if testing subcellular distribution, a mitochondrial marker; verify each channel separately (standard IF practice; UniProt Q9BXM7 localisation). Choose fluorophores after checking tissue autofluorescence and include single-stain and no-primary controls (standard IF practice). Match permeabilisation to the mapped epitope’s accessibility: PINK1 associates with mitochondrial membranes and also has cytosolic processed fragments, while its topology lists no transmembrane segment (UniProt Q9BXM7 localisation and topology; standard IF practice).
How do I separate PINK1 signal from chromogenic background?
The M00201 example used a biotinylated secondary followed by DAB, so assess endogenous biotin and detection-reagent background with appropriate control sections (M00201 tissue-IHC caption; standard IHC practice). Include a no-primary control, block endogenous peroxidase before chromogen development, and check whether deposits track section edges or damaged tissue (standard IHC practice). Titrate the primary around the caption’s 1:25 condition on matched sections rather than assuming that image dilution is optimal for every specimen (M00201 tissue-IHC caption; standard IHC practice). If background persists, review blocking, wash stringency, secondary compatibility, and DAB development time while keeping retrieval fixed at citrate pH 6.0 initially (standard IHC practice; page retrieval setting).
What should I score when PINK1 staining varies across cells? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and tissue area before scoring, then report the percentage of positive intact cells and an intensity-weighted H-score from 0–300 when ordinal staining levels are reproducible (standard IHC practice). For spatially restricted populations, positive-cell density per mm² can supplement the H-score; normalize counts to the corresponding evaluable tissue area, not the whole image field (standard IHC practice). Keep retrieval, detection, exposure, and scoring thresholds consistent across comparison groups (standard IHC practice). Score cytoplasmic staining separately from artefacts, and identify the cell type explicitly because HPA reports variable staining across tissue cell populations and rates its tissue-IHC reliability as uncertain (HPA tissue IHC; standard IHC practice).
What evidence makes a PINK1-positive area credible rather than an artefact?
Prioritize staining in intact, identifiable cells with a plausible cytoplasmic distribution; UniProt reports mitochondrial and cytosolic PINK1, while HPA describes general cytoplasmic tissue staining (UniProt Q9BXM7 localisation; HPA tissue IHC). Compare cell identity with the expected population rather than treating every dark deposit as positive: HPA reports high staining in placental trophoblastic cells but no detection in skeletal-muscle myocytes, with uncertain tissue-IHC reliability (HPA tissue IHC). Discount staining confined to section edges, necrotic regions, or the no-primary control, and investigate residual endogenous peroxidase before scoring DAB deposits (standard IHC practice). A credible staining pattern still does not prove PINK1 activation or mitophagy without independent functional evidence (UniProt Q9BXM7 function; standard IHC practice).
Boster reagents

Best PINK1 / Serine/threonine-protein kinase PINK1, mitochondrial IHC Antibodies

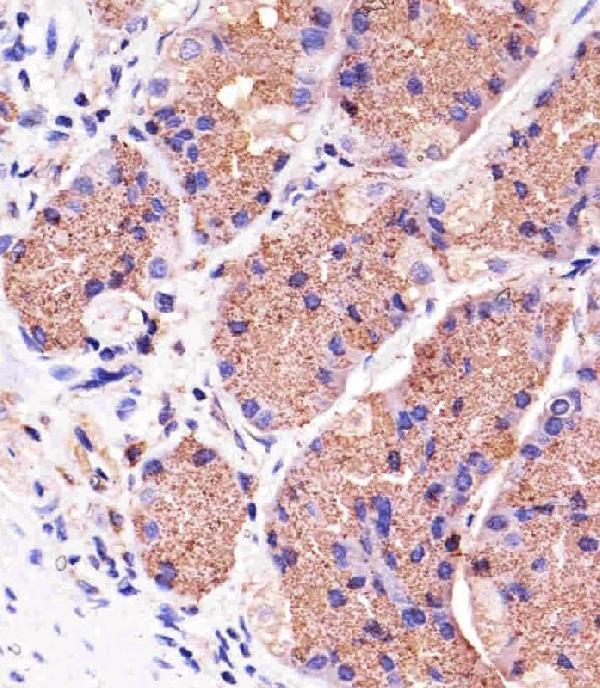
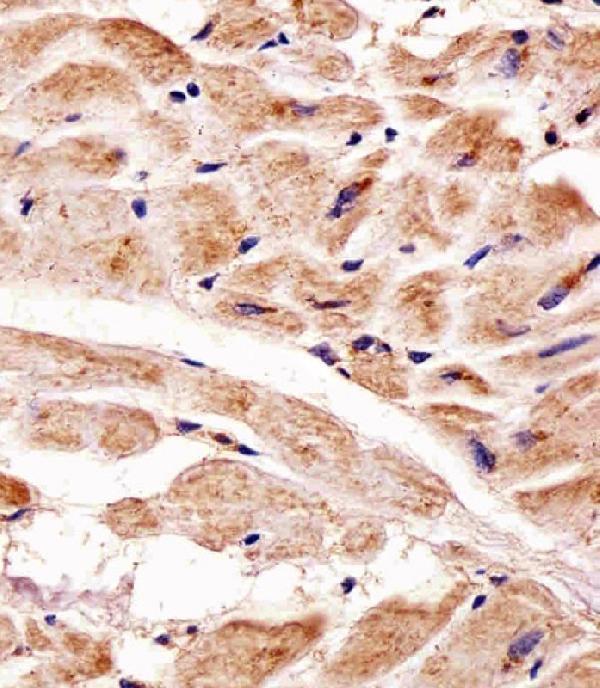
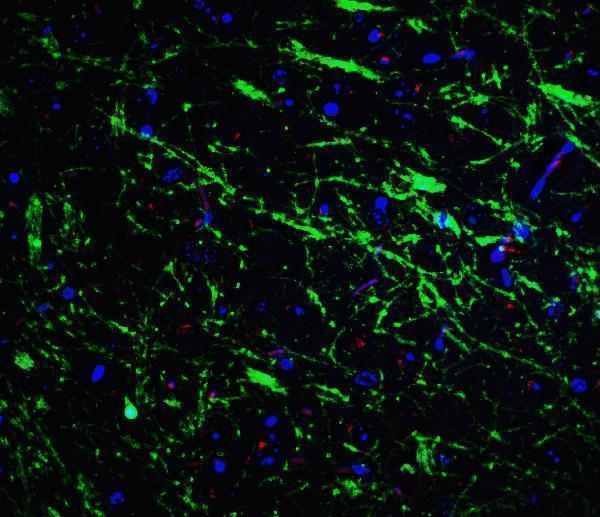
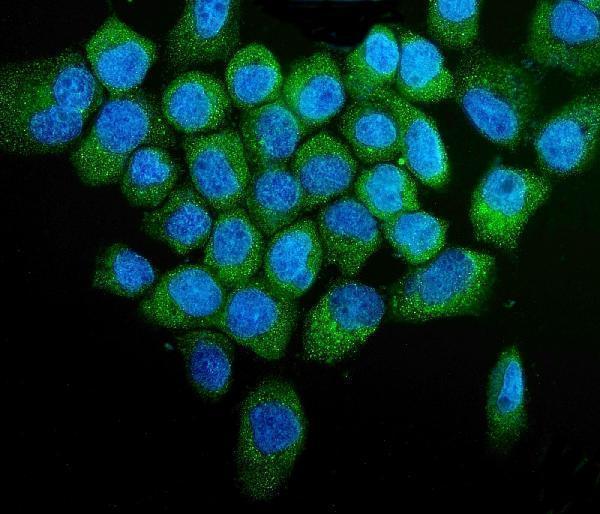
Anti-PINK1 antibodies have IHC images from human paraffin stomach and heart sections and mouse brain, plus an IF/ICC image from A431 cells (catalog image captions).

Real IHC data Immunohistochemical analysis of paraffin-embedded H. stomach section using Pink1(115-213). M00201 was diluted at 1:25 dilution. A undiluted biotinylated goat polyvalent antibody was used as the secondary, followed by DAB staining.
Anti-PINK1 Antibody
Cat # M00201
Real IHC data Immunohistochemistry of PINK1 in mouse brain tissue with PINK1 Antibody at 5 μg/mL.
Anti-PINK1 Antibody
Cat # A00201
Real IF data IF analysis of PINK1 using anti-PINK1 antibody (A00201-2). PINK1 was detected in immunocytochemical section of A431 cells. Enzyme antigen retrieval was performed using IHC enzyme antigen retrieval reagent (AR0022) for 15 mins. The cells were blocked with 10% goat serum. And then incubated with 5μg/mL rabbit anti-PINK1 Antibody (A00201-2) overnight at 4°C. DyLight®488 Conjugated Goat Anti-Rabbit IgG (BA1127) was used as secondary antibody at 1:100 dilution and incubated for 30 minutes at 37°C. The section was counterstained with DAPI. Visualize using a fluorescence microscope and filter sets appropriate for the label used.
Anti-PINK1 Antibody ®
Cat # A00201-2

M00201 has human paraffin stomach and heart IHC images; A00201 has mouse brain IHC and IF images (catalog image captions). A00201-2 lists human IF/ICC and has an A431 cell IF image (catalog applications/reactivity; A00201-2 IF caption).

Which to pick: For human tissue IHC-P, choose M00201, a mouse monoclonal: its own captions show paraffin stomach and heart sections stained with DAB; the fixative is unreported (catalog clone/applications; M00201 IHC captions). For human-cell IF/ICC, choose A00201-2, which lists both applications and has an A431 cell IF image (catalog applications/reactivity; A00201-2 IF caption). For cross-species planning, A00201 lists human, mouse and rat reactivity and IHC-P/IF applications, with mouse brain images for both; its IHC caption does not report processing or fixative (catalog applications/reactivity; A00201 image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9BXM7 (PINK1_HUMAN, Serine/threonine-protein kinase PINK1, mitochondrial).
  2. Human Protein Atlas. PINK1 tissue IHC expression (reliability: Uncertain).
  3. Human Protein Atlas. PINK1 subcellular location (ICC-IF): Highest expression in SiHa: 82.2 nTPM.
  4. Human Protein Atlas. PINK1 antibody validation summary (2 antibodies).
  5. Complement protein C1q induces endothelial apoptosis through C1qBP regulation of mitochondrial function in lung endothelial cells in systemic sclerosis. Molecular medicine (Cambridge, Mass.) 2026 — PMC13069790.
  6. PINK1 Immunoexpression Predicts Survival in Patients Undergoing Hepatic Resection for Colorectal Liver Metastases. International journal of molecular sciences 2023 — PMC10095114.
  7. TRPC6-Calpain-1 Axis Promotes Tubulointerstitial Inflammation by Inhibiting Mitophagy in Diabetic Kidney Disease. Kidney international reports 2024 — PMC11551102.
  8. Activation of aldehyde dehydrogenase-2 improves ischemic random skin flap survival in rats. Frontiers in immunology 2023 — PMC10335790.
  9. PubMed PMID:11494141 — UniProt-cited evidence.
  10. PubMed PMID:14607334 — UniProt-cited evidence.
  11. PubMed PMID:14702039 — UniProt-cited evidence.