This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
A positive ELISA result can look convincing for all the usual reasons: the standard curve is smooth, duplicates agree, the blank is low, and the sample produces a clear signal.
Yet the measured concentration may still be wrong.
One reason is heterophilic antibody interference in ELISA. Endogenous antibodies present in a biological sample can sometimes interact with the antibodies used by the assay itself. In a sandwich ELISA, these interactions may retain the detection antibody even when the intended analyte is absent or present at a much lower concentration than the result suggests.
What makes this type of interference difficult to recognize is that the assay does not necessarily look as though it has failed. Often, the first clue is simply that the result does not behave the way a true analyte measurement should.
This article focuses on those clues: what heterophilic antibody interference looks like in sandwich ELISA, how to distinguish it from more common assay problems, and what experiments can help determine whether an unexpected signal is real.
A sandwich ELISA depends on two antibodies recognizing the same analyte.
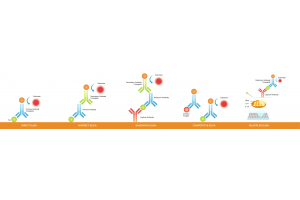
The plate-bound capture antibody binds the target first. A detection antibody then recognizes another epitope on that target, completing the antibody-analyte-antibody complex that ultimately generates the measurable signal.
The problem arises when an endogenous antibody in the sample can interact with both assay antibodies. Instead of the target forming the bridge, the interfering antibody does:
Because the detection antibody remains associated with the well after washing, substrate development proceeds normally. The plate reader cannot distinguish whether the detection antibody was retained by the intended analyte or by an interfering antibody.
The result can therefore be interpreted as a positive signal even when it does not accurately reflect analyte concentration.
This bridging mechanism is one reason sandwich assays are particularly susceptible to this form of interference.
For readers who want a broader comparison of sandwich, direct, indirect, and competitive formats, Boster's ELISA Principle resource explains how the different assay formats generate signal.
Heterophilic antibodies are discussed most often in the context of falsely elevated measurements, but interference does not always increase signal. An endogenous antibody can also obstruct normal antigen binding or interfere with one of the assay antibodies, producing a falsely low result. The exact effect depends on where and how the interfering antibody binds.
Heterophilic interference rarely announces itself through a failed standard curve or an obvious plate-wide background problem.
A run may look technically sound while one sample behaves strangely.
Imagine that most samples in an experimental group fall between 30 and 90 pg/mL, but one sample repeatedly measures 700 pg/mL. That result could represent genuine biology. It could also reflect a sample-specific interference, contamination, a concentration outside the useful assay range, or another matrix-related effect.
The important question is therefore not simply whether the value is high. It is whether the signal continues to behave like the analyte when you challenge it experimentally.
That distinction is important because a clean blank and a smooth standard curve mainly tell you that the assay system itself is functioning. They do not demonstrate that every biological sample is free of interfering components.
Boster's guide to ELISA Controls That Actually Matter: Blank vs Negative vs Spike explores this distinction in more detail, particularly the difference between a process blank, a genuine matrix negative, spike-and-recovery, and dilution linearity.
One of the most useful checks for a suspicious result is serial dilution.
Suppose a sample initially gives an unusually high measurement. If the signal is primarily driven by true analyte, diluting the sample should generally produce a predictable response within the validated range of the assay. After correcting for the dilution factor, the calculated concentration should remain reasonably stable.
| Dilution | Measured concentration | Back-calculated concentration |
|---|---|---|
| 1:2 | 210 pg/mL | 420 pg/mL |
| 1:4 | 103 pg/mL | 412 pg/mL |
| 1:8 | 51 pg/mL | 408 pg/mL |
The raw concentration decreases with dilution, as expected, but after correction the estimated concentration remains close to 400 pg/mL.
Now consider a different result:
| Dilution | Measured concentration | Back-calculated concentration |
|---|---|---|
| 1:2 | 310 pg/mL | 620 pg/mL |
| 1:4 | 82 pg/mL | 328 pg/mL |
| 1:8 | 16 pg/mL | 128 pg/mL |
Here, the apparent concentration changes dramatically as the sample is diluted.
That behavior should raise suspicion that the signal is being affected by something other than a simple analyte-antibody interaction.
It does not, however, prove heterophilic antibody interference. Matrix effects, concentrations outside the quantitative range, or other nonspecific interactions can also cause poor dilution linearity. The value of serial dilution is that it tells you the original number should not yet be accepted at face value.
For experimental guidance on choosing and testing working dilutions, see Boster's How to Decide ELISA Dilution Ratio guide.
A second useful clue comes from assay dependence.
Consider a sample tested by two independently validated assays for the same target:
A discrepancy this large deserves investigation.
If the two assays use different antibody pairs, different epitopes, or antibodies from different host species, an interfering antibody may interact strongly with one system but not the other.
This is why changing the antibody pair can be more informative than simply repeating the original assay several times.
Repeated measurements with the same reagents may reproduce the same interference very precisely. Good precision therefore does not necessarily mean good accuracy.
At the same time, disagreement between assays is not automatic proof that one is affected by heterophilic antibodies. Assays may differ in calibration, epitope recognition, standards, detection ranges, and the molecular forms of an analyte they recognize.
The discrepancy tells you that the result needs explanation.
This is where troubleshooting becomes more important than labeling.
If almost every well has high background, heterophilic antibodies are unlikely to be the first problem to investigate. Washing, blocking, contaminated reagents, incubation conditions, and detection chemistry are more plausible starting points.
If the problem consistently follows the outer wells of the plate, consider an edge effect rather than sample-specific antibody interference.
If replicate wells are highly variable, first review pipetting and mixing.
Cross-reactivity is another possibility. A detection system that recognizes a structurally related protein can produce an apparently positive result, but the mechanism differs from a heterophilic antibody physically interacting with the assay antibodies.
The pattern of the failure therefore matters.
| What you observe | What to consider first |
|---|---|
| One or a few samples are unexpectedly high | Sample-specific interference, true biology, matrix effect |
| Most wells have high background | Washing, blocking, reagent or incubation problem |
| Back-calculated concentration changes with dilution | Matrix interference, heterophilic antibodies, assay-range issue |
| Signal follows related proteins | Cross-reactivity |
| Signal follows plate position | Edge effect |
| Replicates disagree randomly | Pipetting or handling |
| Standard curve is normal but one sample remains unusually high | Sample-specific interference deserves investigation |
Boster's PicoKine ELISA Troubleshooting Guide covers broader assay failures such as weak signal, excessive signal, high background, and other common technical problems. It is useful when the abnormal pattern is not clearly sample-specific.
Several endogenous antibodies can interfere with immunoassays, which is why the terminology is sometimes confusing.
| Interferent | Typical origin | Main reactivity | Potential ELISA effect |
|---|---|---|---|
| Heterophile antibodies | Naturally occurring, broadly reactive antibodies | Can react with immunoglobulins from multiple species | May bridge capture and detection antibodies |
| HAMA | Human anti-mouse antibody response associated with exposure to mouse immunoglobulins | Mouse immunoglobulin | Particularly relevant to assays using murine antibodies |
| HAAA | Human anti-animal antibodies | Immunoglobulins from a particular non-human species | Can interfere with assays using antibodies from that species |
| Rheumatoid factor | Autoantibodies that commonly recognize IgG Fc regions | Fc portion of IgG | Can create nonspecific interactions with assay antibodies |
Analytically, these different antibody populations may produce similar problems. If one of them bridges or otherwise interferes with the assay antibody pair, the reported signal can become disconnected from the true analyte concentration.
For routine research troubleshooting, the practical question is often less about assigning the perfect name to the interfering antibody and more about establishing whether the measured signal depends on the intended target or on an interaction with the assay reagents.
There is no single experiment that identifies every case of heterophilic antibody interference. A convincing investigation usually comes from several pieces of evidence pointing in the same direction.
Serial dilution is often a reasonable place to start because it requires little additional material. If the back-calculated concentration is unstable across dilutions, the sample deserves further investigation.
Spike-and-recovery can answer a related question. Adding a known amount of analyte to the sample tests whether the matrix allows the assay to recover that analyte as expected. Poor recovery suggests that the matrix is affecting the assay, although it cannot tell you by itself whether heterophilic antibodies are responsible.
These two tests address slightly different problems, which is why they are often more informative together.
Boster's ELISA Sample Compatibility Guide discusses dilution linearity, spike recovery, and matrix interference across serum, plasma, tissue homogenates, cell lysates, CSF, saliva, urine, and other sample types.
When antibody-mediated interference remains a concern, the sample can also be retested after treatment with a heterophile-blocking reagent or an appropriate nonimmune immunoglobulin preparation.
A major decrease in signal after blocking supports the possibility that endogenous antibodies contributed to the original measurement.
The wording here matters: it supports interference. It does not prove it.
Blocking reagents vary in what they neutralize, and interfering antibodies vary in concentration, affinity, and reactivity. An unchanged result after blocking therefore does not automatically rule the problem out.
Testing the sample with another antibody pair can provide stronger evidence. If one assay repeatedly reports a very high concentration while another system using different antibodies produces a much lower result, the original antibody pair becomes part of the investigation.
Finally, when the biological conclusion depends heavily on a single unexpected ELISA result, an independent method is valuable. Depending on the target, this may be another immunoassay, Western blot, a functional readout, mass spectrometry, or another biological measurement that does not rely on the same antibody pair.
Consider a serum sample that initially measures 760 pg/mL, while the other samples from the same experiment fall between 30 and 90 pg/mL.
The assay is repeated. The result is still approximately 740 pg/mL.
This tells us the high signal is reproducible, but not yet that it is correct.
The sample is then serially diluted. After correcting for dilution, the calculated concentrations are:
The concentration is no longer stable across dilution.
That changes the interpretation. The original 760 pg/mL measurement may not represent a straightforward analyte concentration.
After heterophile-blocking treatment, the same sample measures 82 pg/mL.
A second assay using another antibody pair reports 76 pg/mL.
No one of these observations is definitive on its own. Together, however, they tell a coherent story: the original signal was reproducible, but it did not dilute normally; it decreased markedly after blocking; and it was not reproduced by another antibody system.
That is much stronger evidence for assay interference than simply observing an unusually high OD.
Heterophilic antibody interference is primarily discussed in serum and plasma because these samples contain endogenous immunoglobulins, but it sits within the broader problem of sample matrix effects.
Different matrices introduce different potential sources of interference.
Serum and plasma are not interchangeable. Anticoagulants can influence assay behavior, and endogenous proteins may affect recovery or background.
Tissue homogenates and cell lysates introduce extraction buffers, detergents, salts, cellular proteins, and sometimes substantial differences in total protein concentration.
Other matrices such as CSF, urine, saliva, and culture supernatants have their own composition and concentration ranges.
This is why validation of a sample type should involve more than checking whether the assay produces a measurable OD. Dilution linearity, recovery, background, and expected concentration range all help determine whether the assay is actually providing quantitative information in that matrix.
If sample preparation itself may be contributing to the problem, Boster's ELISA Sample Preparation Guide covers common sample types and practical preparation factors that can influence ELISA performance.
An unexpectedly high result can also arise because a sample is being measured outside the assay's useful quantitative range. A saturated or poorly positioned sample may produce a number that looks precise but is not quantitatively reliable.
Before attributing a high result to heterophilic interference, confirm that the sample falls within the validated standard-curve range. Boster's How to Perfect Your ELISA Standards provides practical guidance on standard preparation, serial dilution, and curve setup.
It can be reduced, but not universally eliminated.
For assay developers, antibody-pair selection is part of that prevention. The species, subclass, epitope, molecular format, and Fc structure of the assay antibodies can influence susceptibility to endogenous antibody interactions.
Appropriate blocking components may also be incorporated into assay buffers. Nonimmune immunoglobulins, heterophile-blocking reagents, and related additives can compete with unwanted antibody interactions.
The effectiveness of these approaches has to be demonstrated experimentally.
A blocker that works well against one interfering sample may be less effective against another. High concentrations or unusual affinities can exceed the blocking capacity of a reagent, and different types of endogenous antibody interference do not necessarily respond identically.
From the user's perspective, prevention also means working within the conditions for which an assay has actually been validated. Specificity, recovery, dilution linearity, precision, and sample compatibility provide much more useful information than sensitivity alone.
An unusual result should not immediately be labeled as heterophilic antibody interference.
Suspicion becomes more reasonable when several observations occur together.
The result may be difficult to reconcile with the biology. Its back-calculated concentration may change substantially with dilution. A true matrix negative may behave differently from the blank. Blocking treatment may lower the result. Another antibody pair may fail to reproduce the same concentration.
The more these pieces of evidence converge, the harder it becomes to explain the result as a straightforward analyte measurement.
Conversely, if an unusual result dilutes normally, reproduces across independent assays, fits the biological context, and behaves as expected in recovery testing, interference becomes a less compelling explanation.
That is why heterophilic antibody interference is best approached as a troubleshooting question rather than a diagnosis based on one observation.
The most difficult false-positive ELISA results are not the ones that obviously fail.
They are the ones that look technically clean.
A smooth standard curve, low blank, and tight duplicates demonstrate that an assay ran reproducibly. They do not guarantee that every signal in every biological sample was generated by the intended analyte.
When a result is unexpectedly high or inconsistent with the experiment, the next step should be to challenge the signal rather than simply repeat the same measurement.
Serial dilution asks whether the concentration behaves predictably. Spike-and-recovery asks whether the matrix supports accurate measurement. Blocking experiments test whether endogenous antibody interactions contribute to the signal. An alternative antibody pair asks whether the result depends on one particular assay architecture.
Together, these experiments help answer the question that matters most:
Is the ELISA measuring the target — or is something in the sample making it look as though it is?
For broader guidance on ELISA principles, sample preparation, optimization, troubleshooting, and technical blogs, visit Boster's ELISA Technical Resource Center.