This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic TFF3 IHC on paraffin sections using intestinal goblet cells as a positive reference (HPA tissue IHC). Assess cellular and secreted staining with appropriate controls, since TFF3 is secreted (UniProt).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Secreted/extracellular; cytoplasm also annotated (UniProt) | |
| Staining pattern | GI goblet, cervical glandular and airway epithelial cells; secreted thyroid staining (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Appendix+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep formalin fixation consistent across paraffin sections (standard IHC practice; not target-specific) | |
| Caveat | Secreted TFF3 may stain away from producing cells (UniProt; HPA tissue IHC) | |
| Regulation | Regulation unreported in the supplied record (UniProt) | |
| Isoform / epitope | No isoforms listed; signal peptide 1–21 cleaved, leaving chain 22–80 (UniProt) |
Compare the catalog antibody’s IHC-P protocol with three published TFF3 staining protocols for paraffin sections (PMC2528153; PMC7709562; PMC6174951).
| Sample | Tissue sections; selected-image fixative not specified (standard IHC workflow) |
| Fixation | Image fixative and duration unreported (datasheet A01738); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-TFF3, 2 μg/mL (datasheet A01738) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
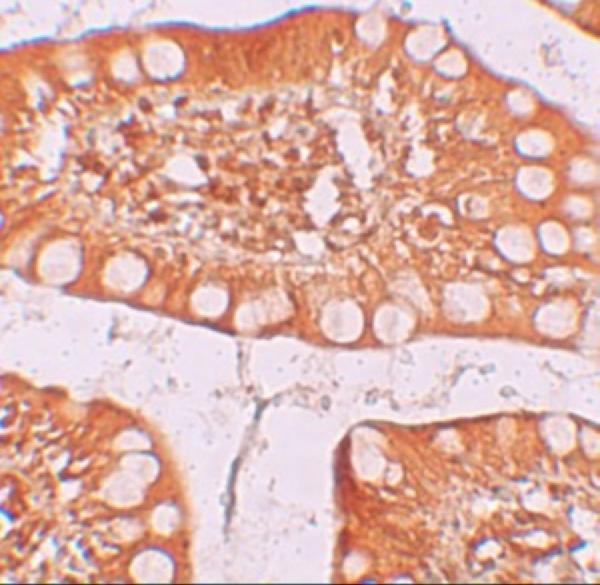
| Expected result | TFF3-positive staining in goblet cells of appendix (HPA tissue IHC: High). HPA tissue profile: Distinct expression in mucus secreting cells in gastrointestinal tract, cervix uteri and respiratory epithelia, with secreted positivity in thyroid gland. No signal in the no-primary control. |
TFF3 is a secreted protein with no transmembrane segment; UniProt also lists cytoplasmic localization (UniProt Q07654). In paraffin-section IHC, expect staining in gastrointestinal goblet cells and other mucus-secreting epithelia, including cervical glandular and respiratory epithelial cells (HPA tissue IHC). HPA rates its tissue pattern Enhanced, while noting that secretion can complicate agreement between RNA and protein locations (HPA tissue IHC).
| Strong staining in intestinal or colonic goblet cells, with neighboring cells less prominent (HPA: High in goblet cells). | This matches the reported tissue IHC pattern. Assess staining in identified cells rather than requiring every epithelial cell to stain; HPA reports High goblet-cell staining in the appendix, colon, duodenum, rectum and small intestine (HPA tissue IHC). |
| Predominantly nuclear staining in a gastrointestinal IHC section, without the expected goblet-cell pattern (HPA tissue IHC). | Treat this as discordant tissue IHC staining and investigate an artefact or unintended detection (HPA tissue IHC; general IHC practice). Nuclear fluorescence is reported separately by HPA for ICC-IF, so nuclear location alone does not settle antibody specificity across applications (HPA subcellular ICC-IF). |
| Strong staining in an unexpected cell type while goblet cells remain unstained (HPA: High in intestinal goblet cells). | Consider antibody cross-reactivity or endogenous chromogenic detection activity; inspect the negative-reagent control and compare cell identity with the HPA tissue pattern (general IHC practice; HPA tissue IHC). |
| Diffuse color over cells and surrounding tissue, with little cell-specific contrast (general IHC practice). | Interpret cautiously: background can obscure a secreted target's distribution (UniProt Q07654 secretion; general IHC practice). Compare a negative-reagent control and check blocking, washes and detection before scoring cells (general IHC practice). |
| No signal in a section expected to contain intestinal goblet cells (HPA tissue IHC). | First verify that goblet cells are present, then check the antibody's IHC validation and the staining run (general IHC practice). HPA reports High staining in several intestinal goblet-cell populations; a blank slide alone cannot establish TFF3 absence (HPA tissue IHC). |
| Secreted protein and topology (UniProt Q07654) | TFF3 has a signal peptide and no transmembrane segment; extracellular signal can reflect secretion, so require cell-type context when interpreting chromogenic deposits (UniProt Q07654; general IHC practice). |
| Processing and epitope information (UniProt Q07654) | The signal peptide spans residues 1–21 and the listed mature chain spans 22–80 (UniProt Q07654). Epitope location is not supplied, so these boundaries cannot predict this antibody's staining or retrieval needs. |
| Tissue and antibody evidence (HPA tissue IHC; HPA antibodies) | The tissue profile is Enhanced, and HPA lists Enhanced IHC validation for HPA035464 and CAB020681 (HPA tissue IHC; HPA antibodies). Use that support for pattern comparison, without assuming it validates a different antibody. |
| Negative comparator choice (HPA tissue IHC) | HPA reports Not detected in adipocytes of adipose tissue and in adrenal glandular cells (HPA tissue IHC). These are cell-specific comparisons, not proof that every cell in either tissue must be negative. |
| IF/ICC Q: Is nuclear fluorescence expected? (HPA subcellular ICC-IF) | HPA reports approved nucleoplasm localization, with additional nucleoli localization, in ICC-IF (HPA subcellular ICC-IF). That observation answers the IF question but does not replace the tissue IHC pattern. |
| Situation | Likely cause | Next action |
|---|---|---|
| A known-positive intestinal section is blank (HPA: High in goblet cells). | Goblet cells may be absent from the sampled area, or the IHC detection run may have failed (general IHC practice). | Confirm goblet cells on the section and review staining and detection controls (general IHC practice). HPA's tissue result alone does not specify a retrieval condition or dilution. |
| The entire section has diffuse chromogenic color (general IHC practice). | Nonspecific reagent binding or endogenous detection activity can raise background (general IHC practice). | Compare negative-reagent controls; review blocking, washes and any detection-system block before judging TFF3 distribution (general IHC practice). |
| Only nuclei stain in gastrointestinal tissue IHC (HPA tissue IHC). | The result is discordant with HPA's goblet-cell tissue pattern, although HPA separately reports nuclear ICC-IF localization (HPA tissue IHC; HPA subcellular ICC-IF). | Review cell identity, controls and antibody IHC validation; do not transfer the ICC-IF localization call directly to paraffin-section IHC (HPA antibodies; general IHC practice). |
| Unexpected cells stain more strongly than goblet cells (HPA: High in goblet cells). | Cross-reactivity or endogenous detection activity is possible; secreted TFF3 can also complicate a simple cell-of-origin reading (general IHC practice; UniProt Q07654). | Compare negative-reagent controls and the HPA cell-level tissue pattern before assigning the stain to TFF3-producing cells (general IHC practice; HPA tissue IHC). |
| Extracellular color is present without convincing goblet-cell staining (UniProt Q07654 secretion). | Secretion permits protein and source-cell locations to differ, but diffuse background can produce a similar impression (UniProt Q07654; HPA tissue IHC; general IHC practice). | Check whether deposits follow tissue structures, compare controls and seek the expected goblet-cell pattern in the same run (general IHC practice; HPA tissue IHC). |
| A proposed negative comparator contains isolated stained cells (HPA tissue IHC). | HPA's Not detected entries name specific cell populations; they do not establish a whole-section negative rule (HPA tissue IHC). | Identify the stained cell type and compare it with the exact HPA entry; avoid scoring an entire tissue from a cell-specific label (HPA tissue IHC; general IHC practice). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — High consistency between antibody staining and RNA expression data. At least one protein variant secreted, tissue location of RNA and protein might differ and correlation is complex.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Appendix | Goblet cells | High | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | High | Protein (IHC) | HPA → |
| Cervix | Glandular cells | High | Protein (IHC) | HPA → |
| Colon | Goblet cells | High | Protein (IHC) | HPA → |
| Duodenum | Goblet cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Not detected | Protein (IHC) | HPA → |
| Breast | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Caudate | Glial cells | Not detected | Protein (IHC) | HPA → |
TFF3 IHC troubleshooting centers on retrieval, secreted staining, and cell specific interpretation (UniProt Q07654; HPA tissue IHC).
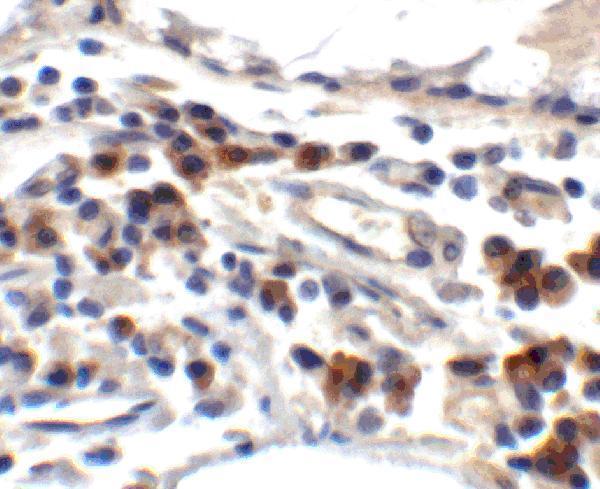
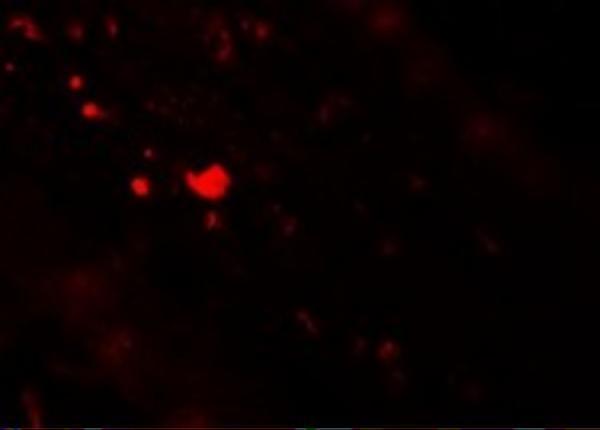
A01738 has human small-intestine IHC and IF images and a HeLa ICC image (A01738 image captions); its listed reactivity covers human, mouse and rat (catalog: A01738 reactivity).
A01738 is listed for IHC-P, IF and ICC in human, mouse and rat (catalog: A01738 applications/reactivity). Its captions show human small-intestine IHC and IF and HeLa ICC (A01738 image captions).
Which to pick: For tissue IHC, choose A01738 (catalog: IHC-P application); its own human small-intestine IHC captions show 2–2.5 μg/mL, but do not report the fixative (A01738 IHC image captions). For IF/ICC, A01738 has human small-intestine IF and HeLa ICC images (A01738 IF/ICC image captions). For mouse or rat samples, A01738 lists both species as reactive (catalog: A01738 reactivity); the supplied IHC/IF tissue images are from human small intestine (A01738 image captions).