ADRM1 / Proteasomal ubiquitin receptor ADRM1 · IHC design guide

Design Immunohistochemistry for ADRM1

Plan chromogenic ADRM1 IHC-P around cytoplasmic and nuclear tissue staining (HPA tissue IHC). Start the catalog antibody A04010-2 at 2–5 μg/mL (datasheet A04010-2), and assess staining against high-staining glandular cells and cardiomyocytes reported as not detected (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for ADRM1 (IHC for ADRM1): expected localisation Cytoplasmic and nuclear tissue staining (HPA tissue IHC), antibody A04010-2, validated IHC image, and IHC protocol steps
Printable ADRM1 IHC protocol sheet — expected localisation Cytoplasmic and nuclear tissue staining (HPA tissue IHC), antibody A04010-2, controls and protocol steps. Open the full ADRM1 IHC guide →

ADRM1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic and nuclear tissue staining (HPA tissue IHC)
Staining pattern Glandular and neural cells show cytoplasmic/nuclear staining (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A04010-2)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Heart muscle
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep formalin fixation consistent across paraffin sections. (standard IHC practice; not target-specific)
Caveat Antibody staining and RNA show medium consistency (HPA tissue IHC)
Regulation Expression regulation not annotated (UniProt)
Isoform / epitope No isoforms; mature chain spans residues 2–407, with no transmembrane segment (UniProt)
Section 1

Recommended ADRM1 IHC & IF Protocols

The catalog antibody’s IHC-P protocol (datasheet A04010-2) is accompanied by published bladder and ovarian tissue protocols (PMC10491834; PMC5547474).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human lung cancer tissue; fixative not specified (datasheet A04010-2)
FixationImage fixative and duration unreported (datasheet A04010-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A04010-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A04010-2)
Primary antibodyRabbit anti-ADRM1, 2-5 μg/ml (datasheet A04010-2)
Primary incubationOvernight at 4 °C (datasheet A04010-2)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A04010-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultADRM1-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic and nuclear expression. No signal in the no-primary control.
💡Decision noteStart with EDTA pH 8.0 heat retrieval for the catalog antibody (datasheet A04010-2); the published protocols used citrate heating (PMC10491834) or steaming in retrieval solution (PMC5547474).
Section 2

What Is the Expected ADRM1 Staining Pattern?

ADRM1 is expected mainly in the cytoplasm and nucleus (UniProt Q16186 subcellular location; HPA tissue IHC: general cytoplasmic and nuclear expression). HPA reports high staining in several glandular, epithelial, neuronal and glial cell populations (HPA tissue IHC). Its tissue IHC profile has Supported reliability, with medium consistency between antibody staining and RNA expression (HPA tissue IHC). ADRM1 has no transmembrane segment, so membrane-only staining needs caution (UniProt Q16186 topology).

What am I looking at on my slide?
Cytoplasmic and nuclear staining in glandular cells of colon, duodenum, appendix or adrenal gland (HPA tissue IHC: High).This matches the reported tissue pattern (HPA tissue IHC: general cytoplasmic and nuclear expression). Judge signal within identifiable cells; compare it with the section background (general IHC practice).
Nuclear and cytoplasmic staining in cerebellar Purkinje cells, cortical neurons or caudate glial cells (HPA tissue IHC: High).These are additional reported positive populations (HPA tissue IHC). Their appearance can support interpretation, though the HPA profile has Supported reliability and medium RNA agreement (HPA tissue IHC).
A sharp membrane rim dominates, with little cytoplasmic or nuclear signal.Treat a membrane-only IHC result as inconclusive: UniProt lists cytoplasm and nucleus and no transmembrane segment (UniProt Q16186). HPA ICC-IF reports plasma membrane localisation as uncertain, while nucleoplasm and cytosol are supported (HPA subcellular).
Staining appears in an unexpected cell population, or chromogen covers extracellular spaces.Check morphology and controls before calling cross-reactivity or endogenous detection activity (general IHC practice). HPA reports broad tissue expression, so absence from its supplied examples does not establish that a cell type is negative (HPA tissue IHC).
The known-positive control has no detectable cellular staining.An absent signal in a reported High population suggests an assay failure or an unsuitable section before it establishes ADRM1 absence (HPA tissue IHC; general IHC practice). Review the control section, retrieval, antibody application and detection steps (general IHC practice).
💡Expected ADRM1 appearanceCall a positive result when identifiable cells show cytoplasmic and nuclear chromogen, especially in HPA High populations; diffuse extracellular deposit is background, and membrane-only signal is inconclusive (HPA tissue IHC; UniProt Q16186 topology; general IHC practice).
How each factor affects the staining
Tissue and cell choiceHPA reports High staining in the listed glandular, epithelial, neuronal and glial populations, but cardiomyocytes in heart muscle are Not detected (HPA tissue IHC). Use a reported High population to check assay performance; do not assume that every cell in a positive tissue stains (general IHC practice).
Strength of tissue evidenceThe tissue IHC profile is Supported, with medium consistency between antibody staining and RNA expression; HPA042266 is IHC Supported (HPA tissue IHC; HPA antibody validation). RNA is tissue enhanced in skeletal muscle, which does not by itself predict the chromogenic pattern of an individual cell (HPA tissue IHC).
Topology and processingADRM1 has no transmembrane segment, signal peptide, propeptide or annotated glycosylation sites (UniProt Q16186). These annotations support caution with membrane-only staining; they do not establish an IHC epitope, retrieval requirement or fixation sensitivity (UniProt Q16186; general IHC practice).
IF/ICC: where should ADRM1 appear?Expect supported nucleoplasmic and cytosolic localisation in ICC-IF; HPA also lists plasma membrane localisation as uncertain (HPA subcellular). This IF observation is context for compartment interpretation, not a separate IHC-P protocol or proof of a membrane-only tissue pattern.
Chromogenic detectionEndogenous enzyme activity or nonspecific reagent deposition can resemble staining; assess reagent controls and whether colour follows cell boundaries and compartments (general IHC practice). The supplied HPA data do not identify a tissue-specific source of such background.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No signal in a reported High population (HPA tissue IHC).A section or IHC workflow problem is possible; a blank slide alone does not establish target absence (general IHC practice).Check tissue identity, cellular preservation, retrieval, primary antibody application and detection with a known-positive section (general IHC practice).
Both specimen and reagent control show diffuse colour.Background may arise from detection chemistry, endogenous activity or insufficient blocking or washing (general IHC practice).Compare controls, check blocking and washing, and interpret only signal that follows identifiable cells (general IHC practice).
Chromogen is widespread but obscures nuclei and cell borders.Excess background or overly strong detection can prevent compartment scoring (general IHC practice).Review primary antibody dilution and detection development using the assay instructions; rescore only when morphology is readable (general IHC practice).
A membrane rim is the sole convincing signal.Membrane localisation is uncertain in HPA ICC-IF, whereas nucleoplasm and cytosol are supported (HPA subcellular).Treat membrane-only IHC as inconclusive; compare a reported High control for cytoplasmic and nuclear staining and check reagent controls (HPA tissue IHC; general IHC practice).
Unexpected cells stain while the expected cells do not.Cross-reactivity, endogenous detection activity or misidentified cells are possibilities; HPA examples are not an exhaustive negative-cell list (HPA tissue IHC; general IHC practice).Recheck morphology and control staining, then compare with the named HPA populations before assigning biological specificity (HPA tissue IHC; general IHC practice).
Cardiomyocytes stain strongly despite the supplied HPA negative observation.HPA lists heart muscle cardiomyocytes as Not detected; a conflicting result warrants review but is not proof of an artefact (HPA tissue IHC).Check tissue identity, cellular localisation and reagent controls; compare the same run with a reported High population (HPA tissue IHC; general IHC practice).

Sample controls for ADRM1 IHC & IF

🧪Run adrenal gland first: glandular cells should stain strongly (HPA: High in adrenal gland glandular cells). Run heart muscle as the negative tissue (HPA: Not detected in cardiomyocytes); on the adrenal slide, use adjacent cells that remain unstained as an internal background reference, without assuming they are ADRM1-negative.
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Heart muscle (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show ADRM1 in A-431, U-251MG, U2OS, with annotated localisation: Nucleoplasm (supported), Plasma membrane (uncertain), Cytosol (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and a concentration-matched rabbit IgG isotype control (caption: rabbit primary antibody); use ADRM1 knockout tissue or cells, if available, as a biological specificity control. With SABC/DAB detection (caption: SABC/DAB), check the adrenal section for endogenous peroxidase and biotin background alongside the controls.
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A04010-2 paraffin-section caption does not state the fixative (caption: fixative not stated). That caption uses heat retrieval in EDTA at pH 8.0, so start there while comparing retrieval conditions if staining is weak (caption: EDTA pH 8.0 heat retrieval). Frozen-section feasibility and any advantage of IF are unreported; assess adrenal background from endogenous peroxidase or biotin before scoring (caption: SABC/DAB).

HPA tissue IHC evidence for ADRM1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Glandular cells High Protein (IHC) HPA →
Caudate Glial cells High Protein (IHC) HPA →
Cerebellum Purkinje cells High Protein (IHC) HPA →
Cerebral cortex Neuronal cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Heart muscle Cardiomyocytes Not detected Protein (IHC) HPA →
Section 3

Advanced ADRM1 IHC Tips

Troubleshoot ADRM1 staining in paraffin sections by checking retrieval, compartment patterns, background and scoring against the available tissue evidence.

Which retrieval condition should I try first for ADRM1 in paraffin sections?
Start with heat-mediated retrieval in EDTA at pH 8.0 (datasheet A04010-2). The selected paraffin-section example used that condition before staining human lung cancer tissue with 2 μg/ml primary antibody overnight at 4°C (datasheet A04010-2). If staining is weak, compare retrieval duration on adjacent sections while holding antibody concentration and chromogen development constant (standard IHC practice). Record tissue morphology alongside signal, because excessive heating can damage sections and make a stronger stain difficult to interpret (standard IHC practice). The caption does not specify a retrieval duration, so establish one with your equipment (datasheet A04010-2; standard IHC practice).
How should I troubleshoot weak ADRM1 staining when fixation history is uncertain?
The selected paraffin-section caption does not state a fixative, and target-specific fixation sensitivity is unknown (datasheet A04010-2). Record the available fixation history and compare sections processed together, using the same EDTA pH 8.0 retrieval and 2 μg/ml primary antibody conditions as starting points (datasheet A04010-2; standard IHC practice). Include a tissue control that stains reliably in your run, then assess staining and morphology together before changing retrieval or detection (standard IHC practice). Differences between specimens cannot establish an ADRM1-specific fixation effect without matched processing and controls (standard IHC practice).
What compartment pattern is plausible for ADRM1, and when should I question staining?
Assess cytoplasmic and nuclear staining first: UniProt lists both compartments, and tissue IHC reports general expression in both (UniProt Q16186 subcellular; HPA tissue IHC). Cell imaging supports nucleoplasm and cytosol, while its plasma-membrane assignment is uncertain (HPA subcellular). ADRM1 has no annotated transmembrane segment, so strong membrane-only chromogenic staining needs particular scrutiny rather than automatic acceptance (UniProt Q16186 topology; standard IHC practice). Compare compartment patterns in intact cells with a counterstain, a no-primary control and a consistently stained tissue control before assigning signal to ADRM1 (standard IHC practice).
Can isoforms or epitope accessibility explain discordant ADRM1 staining?
The supplied record lists 0 isoforms and identifies Pru residues 18–131 and DEUBAD residues 277–391 (UniProt Q16186 isoforms and domains). It also lists modifications, including phosphorylation at residues 15, 127, 140 and 211, but supplies no antibody epitope (UniProt Q16186 modified residues; datasheet A04010-2). Therefore, do not assign a staining difference to an isoform or a particular modified residue from these data alone (UniProt Q16186 isoforms; standard IHC practice). If paired sections disagree, compare retrieval and detection conditions first, then seek antibody epitope information before proposing an epitope mechanism (standard IHC practice).
How should I adapt the ADRM1 question to multiplex IF?
For multiplex IF, pair ADRM1 with a marker identifying the cell population being assessed, such as a validated marker for glandular cells when examining glandular tissue (HPA tissue IHC; standard IF practice). Expect nucleoplasmic and cytosolic signal; treat membrane staining cautiously because that location is uncertain and ADRM1 has no annotated transmembrane segment (HPA subcellular; UniProt Q16186 topology). Choose fluorophores after checking tissue autofluorescence in each channel, and place the weaker signal in the cleaner detection channel (standard IF practice). For intracellular ADRM1 epitopes, test permeabilisation and include single-stain controls; the supplied IHC caption does not establish an IF permeabilisation condition (UniProt Q16186 subcellular; datasheet A04010-2; standard IF practice).
What should I check when ADRM1 DAB staining is diffuse or patchy?
First compare a no-primary section with the test section to identify signal from detection reagents or endogenous enzyme activity (standard IHC practice). The selected workflow used 10% goat serum, biotinylated goat anti-rabbit secondary, streptavidin–biotin detection and DAB, making blocking and detection controls relevant to this setup (datasheet A04010-2). Use a peroxidase block for chromogenic detection and assess whether a biotin-based system contributes background in the tissue being tested (standard IHC practice). Examine tissue edges, folds and damaged areas separately from intact cells before changing the 2 μg/ml primary antibody concentration (datasheet A04010-2; standard IHC practice).
How can I quantify ADRM1 IHC without confusing cell composition with expression? ⚠ ANSWER MARKED FOR VERIFICATION
Define nuclear and cytoplasmic compartments before scoring because both are reported for ADRM1 (UniProt Q16186 subcellular; HPA tissue IHC). Within a specified cell population, report the percentage of positive cells and staining intensity, or use an H-score from 0–300 with documented intensity categories (standard IHC practice). Normalise counts to the number of evaluable cells in that population, and report positive-cell density per mm² only when the analysed tissue area is defined (standard IHC practice). Apply identical imaging, threshold and exclusion rules across sections, excluding folds and necrotic regions before comparing conditions (standard IHC practice).
How do I distinguish credible ADRM1 positivity from staining artefact?
Credible staining should localise to intact cells and show a reproducible cytoplasmic or nuclear pattern, both consistent with reported ADRM1 localisation (UniProt Q16186 subcellular; HPA tissue IHC; standard IHC practice). HPA reports high staining in several glandular cell populations and no detected staining in heart cardiomyocytes, although its tissue-IHC reliability is described as supported with medium consistency against RNA data (HPA tissue IHC). Treat isolated membrane-only signal, stained tissue edges or necrotic deposits cautiously, and check a no-primary section for endogenous-enzyme or detection background (HPA subcellular; standard IHC practice). Interpret differences only among comparable cells and processing conditions; tissue composition and technical background can otherwise change the apparent result (standard IHC practice).
Boster reagents

Best ADRM1 / Proteasomal ubiquitin receptor ADRM1 IHC Antibodies

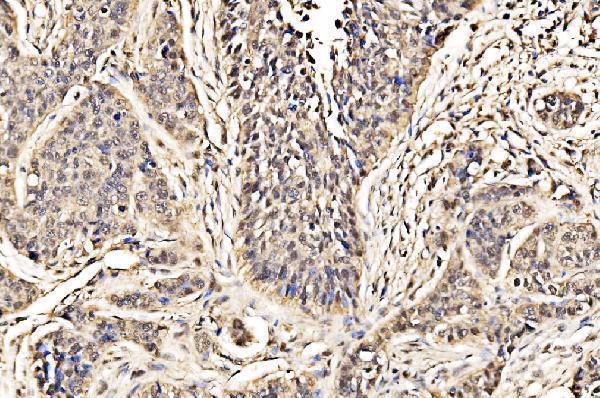
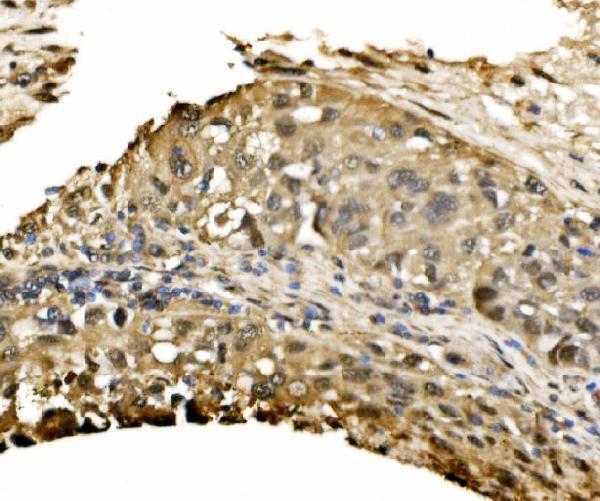
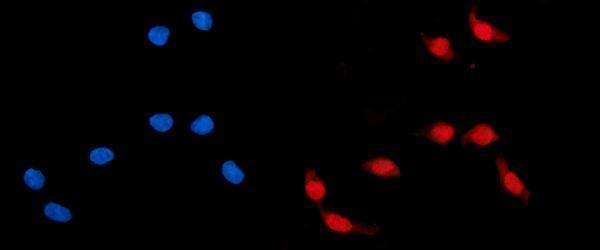
Anti-ADRM1 antibodies have IHC images from human spleen, lung cancer, liver and stomach cancer, and mouse brain; an IF image shows CACO-2 cells (catalog image captions).

Real IHC data IHC analysis of ADRM1/ARM-1 using anti-ADRM1/ARM-1 antibody (A04010-2). ADRM1/ARM-1 was detected in a paraffin-embedded section of human lung cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-ADRM1/ARM-1 Antibody (A04010-2) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-ADRM1/ARM-1 Antibody ®
Cat # A04010-2
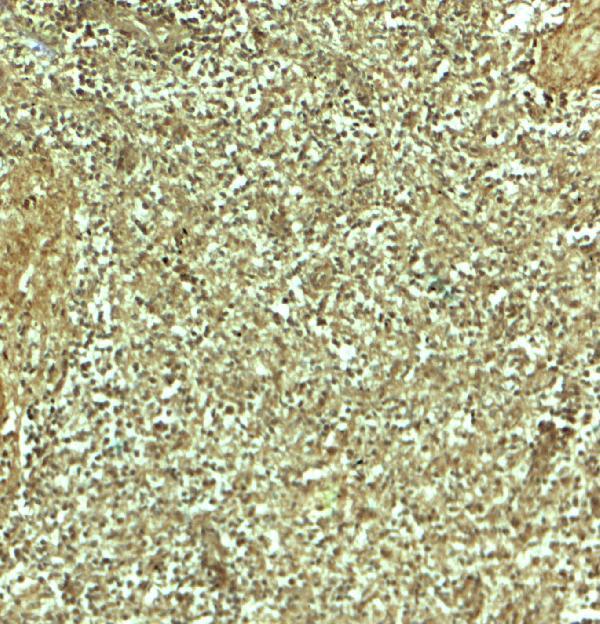
Real IHC data Immunohistochemistry of ADRM1 in human spleen tissue with ADRM1 antibody at 5 μg/mL.
Anti-ADRM1 Antibody
Cat # A04010

A04010 has a human spleen IHC image at 5 μg/mL (A04010 image caption). A04010-2 has paraffin-section IHC images from human lung cancer, liver and stomach cancer and mouse brain, plus an IF/ICC image from CACO-2 cells (A04010-2 image captions).

Which to pick: For tissue IHC, choose A04010 for the documented human spleen example or A04010-2 for its documented human and mouse paraffin-section examples (catalog IHC image captions). For IF/ICC, choose A04010-2 at the listed 5 μg/mL; A04010 lists IHC-P but no IF/ICC application (catalog applications and dilutions). Both list human, mouse and rat reactivity, but the supplied IHC images show human tissue for both and mouse tissue only for A04010-2; the fixative is unreported in those captions (catalog reactivity; catalog IHC image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q16186 (ADRM1_HUMAN, Proteasomal ubiquitin receptor ADRM1).
  2. Human Protein Atlas. ADRM1 tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. ADRM1 subcellular location (ICC-IF): Localized to the nucleoplasm, plasma membrane and cytosol..
  4. Human Protein Atlas. ADRM1 antibody validation summary (1 antibodies).
  5. ADRM1 as a therapeutic target in hepatocellular carcinoma. The Kaohsiung journal of medical sciences 2021 — PMC11896441.
  6. Adhesion-regulating molecule 1 (ADRM1) can be a potential biomarker and target for bladder cancer. Scientific reports 2023 — PMC10491834.
  7. Early and consistent overexpression of ADRM1 in ovarian high-grade serous carcinoma. Journal of ovarian research 2017 — PMC5547474.
  8. Downregulation of pro-surfactant protein B contributes to the recurrence of early-stage non-small cell lung cancer by activating PGK1-mediated Akt signaling. Experimental hematology & oncology 2023 — PMC10633994.
  9. PubMed PMID:8033103 — UniProt-cited evidence.
  10. PubMed PMID:16990800 — UniProt-cited evidence.
  11. PubMed PMID:11780052 — UniProt-cited evidence.