This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic ARMCX1 IHC in paraffin sections using cytoplasmic staining in adrenal glandular cells as a reference (HPA tissue IHC). The guide pairs that tissue pattern with the mitochondrial outer-membrane annotation (UniProt) and the catalog antibody’s 1:100–1:300 IHC dilution range (datasheet A09670).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic staining (HPA tissue IHC); mitochondrial outer membrane (UniProt) | |
| Staining pattern | Cytoplasmic in most cells, except lymphoid and CNS cells (HPA tissue IHC) | |
| Antigen retrieval | Tris-EDTA pH 9.0 HIER, heat-mediated (datasheet A09670) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | Appendix+4 more · see all |
| Fixation | Keep paraffin-section fixation consistent (standard IHC practice; not target-specific); Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A09670) | |
| Caveat | Brain expression may not predict CNS tissue staining (UniProt; HPA tissue IHC) | |
| Regulation | Reduced in several carcinomas (UniProt) | |
| Isoform / epitope | No annotated isoforms or cleavage; residues 30–453 face cytoplasm (UniProt) |
Compare the catalog antibody’s IHC-P protocol with published ARMCX1 IHC on retinal cross sections (PMC5189716), attempted retinal staining (PMC11364276), and NPC tissue microarrays (PMC12804310).
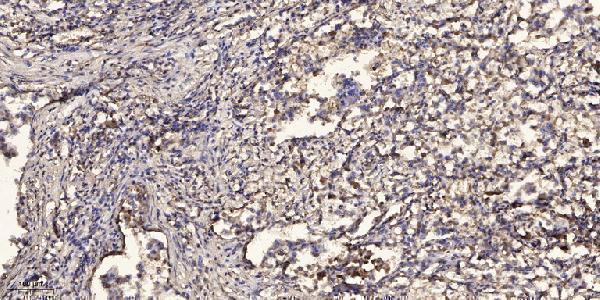
| Sample | Paraffin-embedded human Squamous cell carcinoma of lung tissue; fixative not specified (datasheet A09670) |
| Fixation | Image fixative and duration unreported (datasheet A09670); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: Tris-EDTA pH 9.0 (datasheet A09670); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-ARMCX1, 1:100-1:300 (datasheet A09670) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | ARMCX1-positive staining in glandular cells of adrenal gland (HPA tissue IHC: Medium). HPA tissue profile: Cytoplasmic expression in most cells except lymphoid cells and cells in CNS. No signal in the no-primary control. |
ARMCX1 should appear mainly in the cytoplasm of many non-lymphoid cells on tissue IHC (HPA: supported IHC; medium agreement with RNA; pending external verification). Its mitochondrial outer-membrane anchor and cytoplasm-facing region support a mitochondrial-associated pattern (UniProt Q9P291 topology). HPA reports medium staining in several epithelial and glandular cell populations and colon endothelial cells, while individual tissues and cell types vary (HPA tissue IHC).
| Cytoplasmic granular staining in breast or duodenal glandular cells, with little nuclear staining. | Consistent with ARMCX1 localization (UniProt Q9P291 topology) and medium staining in these cell populations (HPA tissue IHC). Chromogenic IHC alone cannot establish that each granule is mitochondrial. |
| Predominantly nuclear or sharply cell-surface staining, without the expected cytoplasmic pattern. | Reassess antibody specificity, detection, and slide quality before interpreting it as ARMCX1 (UniProt Q9P291 topology; HPA tissue IHC). HPA also reports additional nucleoplasmic localization by ICC-IF, so nuclear staining alone is not conclusive evidence of an artifact (HPA subcellular ICC-IF). |
| Strong staining of lymph-node germinal-center cells or bone-marrow hematopoietic cells. | These populations were not detected in HPA tissue IHC; cross-reactivity or endogenous chromogenic activity is possible, especially if controls show the same signal (HPA tissue IHC). Check the pattern against the positive control before scoring it. |
| Uniform color across cells, stroma, and blank areas, obscuring cell boundaries. | This favors nonspecific background over a cell-associated ARMCX1 pattern (HPA tissue IHC). Review blocking, wash steps, detection reagent, and a no-primary control using standard IHC practice. |
| No stain in breast glandular cells or bronchial respiratory epithelium. | Both are medium-staining HPA examples, so a blank result warrants a run-level check (HPA tissue IHC). Absence in one specimen is not definitive: HPA rates tissue IHC as supported, with medium RNA agreement and external verification pending. |
| Outer-membrane topology (UniProt Q9P291 topology) | Residues 7–29 form the membrane segment; residues 30–453 face the cytoplasm (UniProt Q9P291 topology). The antibody epitope is unspecified, so topology does not establish an antigen-retrieval requirement. |
| Cell population and tissue context (HPA tissue IHC) | HPA reports medium staining in breast and duodenal glandular cells, but no detection in appendix glandular cells (HPA tissue IHC). Judge the named cell population, not merely the organ label. |
| Evidence strength (HPA tissue IHC; HPA antibodies) | The tissue profile is supported, with medium staining-to-RNA consistency and external verification pending (HPA tissue IHC). Two listed antibodies have supported IHC status; that status alone does not make every unexpected stain target-specific (HPA antibodies). |
| Protein annotations (UniProt Q9P291 record) | No glycosylation sites, modified residues, or alternative isoforms are annotated, and the chain spans residues 1–453 (UniProt Q9P291 record). These annotations do not justify predicting a processing-dependent IHC pattern. |
| IF localization evidence (HPA subcellular ICC-IF) | Mitochondria are the supported main ICC-IF location; nucleoplasm and cytosol are approved additional locations (HPA subcellular ICC-IF). This helps interpret compartment differences, but does not set a paraffin-IHC scoring threshold. |
| Situation | Likely cause | Next action |
|---|---|---|
| Expected positive cells are blank. | The run may have weak detection, or this specimen may differ from HPA's example; tissue IHC has medium RNA agreement (HPA tissue IHC). | Check a listed medium-staining positive population in the same run, then review the IHC-validated antibody, detection reagents, and routine antigen-retrieval controls. Do not infer ARMCX1-specific retrieval sensitivity from these sources. |
| Nuclear staining dominates the section. | UniProt places ARMCX1 at the mitochondrial outer membrane, while HPA approves nucleoplasm as an additional ICC-IF location (UniProt Q9P291; HPA subcellular ICC-IF). | Compare cytoplasmic staining in a listed positive population and inspect no-primary controls. Treat isolated nuclear IHC signal cautiously; the ICC-IF observation does not validate a nuclear-only chromogenic pattern. |
| Lymphoid or hematopoietic cells stain strongly. | HPA reports no detection in lymph-node germinal-center and bone-marrow hematopoietic cells; cross-reactivity or endogenous detection activity could contribute (HPA tissue IHC). | Inspect no-primary and detection-only controls, then compare the same run with a listed medium-positive cell population before assigning an ARMCX1 score. |
| Diffuse color obscures cell boundaries. | Nonspecific background or endogenous chromogenic activity may overwhelm the cytoplasmic pattern described by HPA (HPA tissue IHC). | Use standard IHC controls to check blocking, washes, and detection activity; score only discernible cell-associated staining in the relevant population. |
| Brain, ovary, prostate, or spleen appears inconsistent with a high-expression listing. | UniProt's tissue-expression summary and HPA's cell-resolved IHC can differ: HPA reports low staining in ovarian follicle and prostate glandular cells and no detection in splenic red-pulp cells (UniProt Q9P291 tissue specificity; HPA tissue IHC). | Record the sampled cell type and its HPA level. Avoid treating a whole-tissue expression statement as a predicted staining intensity for every cell. |
| What should an IF/ICC image show? | HPA supports mitochondria as the main ICC-IF location and approves additional nucleoplasm and cytosol localization (HPA subcellular ICC-IF). | Expect a mainly mitochondrial pattern, with the reported additional compartments possible (HPA subcellular ICC-IF); assess IF/ICC methods in its own guide rather than applying an IHC staining score. |

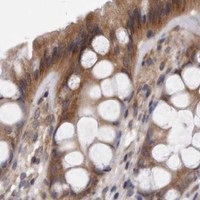


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | Medium | Protein (IHC) | HPA → |
| Breast | Glandular cells | Medium | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | Medium | Protein (IHC) | HPA → |
| Cervix | Squamous epithelial cells | Medium | Protein (IHC) | HPA → |
| Colon | Endothelial cells | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Appendix | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Not detected | Protein (IHC) | HPA → |
| Cerebellum | Cells in granular layer | Not detected | Protein (IHC) | HPA → |
| Hippocampus | Glial cells | Not detected | Protein (IHC) | HPA → |
| Liver | Cholangiocytes | Not detected | Protein (IHC) | HPA → |
Use the catalog antibody’s paraffin section protocol as the IHC starting point, then judge staining against ARMCX1’s expected compartment and cell distribution.
A09670 lists human, mouse and rat reactivity (catalog: reactivity). Its real IHC figure shows paraffin-embedded human lung squamous cell carcinoma (A09670 IHC caption); IF is listed without a supplied figure (catalog: applications, IF image alts).
A09670 is listed for IHC and IF, with human, mouse and rat reactivity (catalog: applications, reactivity). Its supplied IHC figure shows paraffin-embedded human squamous cell carcinoma of lung using a 1:200 primary dilution and Tris-EDTA retrieval at pH 9.0 (A09670 IHC caption).
Which to pick: For tissue IHC, choose A09670: its own caption documents paraffin sections, a 1:200 primary dilution overnight at 4 °C, and Tris-EDTA retrieval at pH 9.0; the fixative is unreported (A09670 IHC caption). For IF/ICC, A09670 lists IF at 1:200–1:1000, but has no supplied IF figure or explicit ICC validation (catalog: applications, IF dilution, IF image alts). For mouse or rat work, A09670 is a rabbit polyclonal with listed reactivity in both species, while its pictured IHC evidence is from human tissue (catalog: host, dilution_raw, reactivity; A09670 IHC caption).