CAV3 / Caveolin-3 · IHC design guide

Design Immunohistochemistry for CAV3

Plan CAV3 IHC in paraffin sections using skeletal or heart muscle as positive controls; expect membranous staining in myocytes (HPA tissue IHC). Keep fixation consistent, block endogenous peroxidase, and score membrane staining against a negative control (standard IHC practice).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
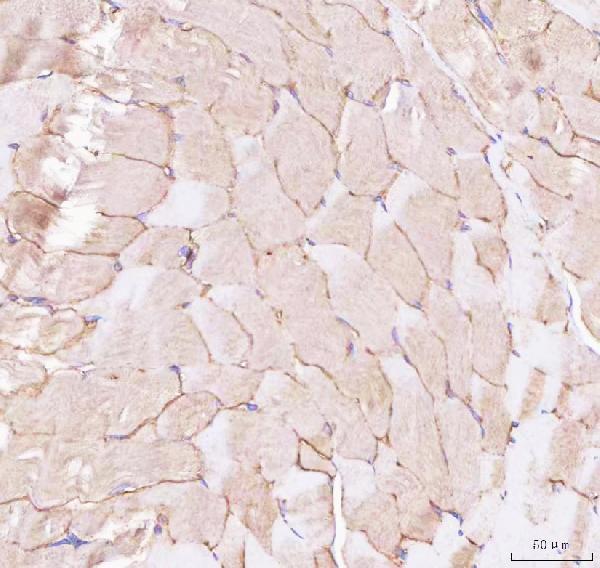
Immunohistochemistry protocol sheet for CAV3 (IHC for CAV3): expected localisation Membranous staining observed in muscle; sarcolemma expected (HPA tissue IHC; UniProt), antibody A00990-2, validated IHC image, and IHC protocol steps
Printable CAV3 IHC protocol sheet — expected localisation Membranous staining observed in muscle; sarcolemma expected (HPA tissue IHC; UniProt), antibody A00990-2, controls and protocol steps. Open the full CAV3 IHC guide →

CAV3 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Membranous staining observed in muscle; sarcolemma expected (HPA tissue IHC; UniProt)
Staining pattern Cardiomyocytes and skeletal myocytes: membranous staining (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A00990-2)
Positive control ⓘ Heart muscle+1 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A00990-2)
Caveat Endogenous peroxidase may add muscle background (standard IHC practice)
Regulation No expression regulation specified (UniProt)
Isoform / epitope No isoforms; one 1–151 chain with cytoplasmic termini (UniProt)
Section 1

Recommended CAV3 IHC & IF Protocols

The catalog antibody’s IHC-P protocol is paired with one published CAV3 staining protocol from mouse heart sections (PMC8052133).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human skeletal muscle tissue; fixative not specified (datasheet A00990-2)
FixationImage fixative and duration unreported (datasheet A00990-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A00990-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A00990-2)
Primary antibodyRabbit anti-CAV3, 0.5-1μg/ml recommended; image 2 μg/ml (datasheet A00990-2)
Primary incubationOvernight at 4 °C (datasheet A00990-2)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A00990-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultCAV3-positive staining in cardiomyocytes of heart muscle (HPA tissue IHC: High). HPA tissue profile: Membranous expression in skeletal muscle and heart muscle. No signal in the no-primary control.
💡Decision noteStart with EDTA pH 8.0 heat retrieval for the catalog antibody (datasheet A00990-2); the published mouse heart protocol used citrate pH 6.0 (PMC8052133).
Section 2

What Is the Expected CAV3 Staining Pattern?

CAV3 should stain predominantly along the membranes of skeletal myocytes and cardiomyocytes in IHC sections (HPA: Enhanced tissue IHC; High in both cell types). UniProt places CAV3 at the sarcolemma and caveolae, with both annotated terminal regions facing the cytoplasm and a potential hairpin-like membrane structure (UniProt P56539 topology). HPA reports high consistency between antibody staining and RNA expression (HPA: Enhanced reliability).

What am I looking at on my slide?
Strong, crisp outlines of skeletal myocytes or cardiomyocytes.This fits the expected membranous pattern in the two High-staining cell types (HPA: tissue IHC) and sarcolemmal localization (UniProt P56539). Judge the pattern within identifiable muscle cells, alongside the tissue control.
Predominantly nuclear, uniformly cytoplasmic, or extracellular staining replaces membrane outlines.Treat a dominant pattern in these compartments as suspect because HPA describes muscle staining as membranous (HPA: tissue IHC). UniProt also lists Golgi membrane localization, so a limited internal signal alone does not prove an artefact (UniProt P56539).
Prominent staining in adipocytes or bronchial respiratory epithelium.These cells are reported Not detected (HPA: tissue IHC). Check antibody specificity and, with chromogenic detection, endogenous enzyme activity before interpreting the signal as CAV3 (general IHC practice).
Diffuse colour extends across cells and surrounding tissue.A diffuse field does not reproduce the membranous muscle pattern (HPA: tissue IHC). Uneven blocking, excessive primary antibody, or incomplete washes can raise background; distinguish these possibilities with appropriate controls (general IHC practice).
No discernible membrane signal in an intact skeletal muscle or heart muscle control.Both are High-staining controls (HPA: tissue IHC), so a blank result warrants a technical check before calling the specimen negative. Review the antibody's IHC-P instructions, detection reagents, and the control section (general IHC practice).
💡Expected CAV3 appearanceCall a result positive when strong membranous staining outlines skeletal myocytes or cardiomyocytes (HPA: High; membranous); broad nuclear, extracellular, or adipocyte staining is suspect (HPA: tissue IHC).
How each factor affects the staining
Tissue and cell identitySkeletal myocytes and cardiomyocytes are High, while adipocytes in adipose tissue are Not detected (HPA: tissue IHC). Compare the stained cells with the section's morphology before scoring. Salivary glandular cells are Low, so faint staining there is a weaker specificity test (HPA: tissue IHC).
Membrane topologyCAV3 has no annotated transmembrane segment; residues 1–83 and 105–151 are cytoplasmic, with a potential membrane hairpin (UniProt P56539 topology). Its sarcolemmal and caveolar locations support a membrane-outline readout (UniProt P56539); topology alone does not predict retrieval conditions.
Antibody validationHPA lists HPA072988, CAB017518, and CAB018557 as IHC Enhanced (HPA: antibody validation). That supports the tissue pattern, but validation for those antibodies does not establish the specificity of a different catalog antibody. Confirm its IHC-P suitability and use tissue controls (general IHC practice).
Antigen retrievalNo CAV3-specific retrieval condition or fixation sensitivity is supplied (UniProt P56539; HPA: supplied records). Follow the IHC-validated antibody's documented IHC-P conditions; if optimisation is needed, compare retrieval conditions using the same positive control (general IHC practice).
Chromogenic detectionEndogenous enzyme activity and nonspecific detection can resemble a positive reaction in chromogenic IHC (general IHC practice). A no-primary control helps identify detection background; require the expected muscle-cell membrane pattern before assigning CAV3 positivity (HPA: tissue IHC).
Q: Does ICC-IF define the IHC pattern?A: HPA reports plasma membrane with additional vesicles in ICC-IF images from Rh30, and rates HPA054488 ICC Supported (HPA: subcellular; antibody validation). This provides localization context; score paraffin IHC against HPA's membranous muscle-tissue pattern (HPA: tissue IHC).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Skeletal muscle control has no membrane staining.The expected High signal is absent (HPA: skeletal myocytes). A failed detection step or unsuitable IHC-P conditions are possible (general IHC practice).Check the IHC-validated antibody's IHC-P instructions, reagent activity, and control section; then repeat with a documented positive muscle control (general IHC practice; HPA: skeletal muscle High).
Heart muscle is weak while skeletal muscle is convincing.Both cell types are reported High (HPA: tissue IHC). Differences in section quality or staining conditions may affect the comparison (general IHC practice).Review cardiomyocyte morphology and staining controls, then compare sections processed together before treating the difference as biological (general IHC practice; HPA: heart muscle High).
Strong staining appears in adipocytes.Adipocytes are Not detected in adipose tissue (HPA: tissue IHC); cross-reactivity or detection background is possible (general IHC practice).Run a no-primary control and review antibody specificity and detection blocking. Require the expected muscle membrane pattern in a positive control (general IHC practice; HPA: tissue IHC).
The whole section has diffuse chromogenic colour.Diffuse colour obscures the expected membranous pattern (HPA: tissue IHC). Excess primary antibody, inadequate blocking, or incomplete washing may contribute (general IHC practice).Inspect the no-primary control, then optimise antibody dilution, blocking, and washes within the documented IHC-P workflow (general IHC practice).
The main signal is nuclear or extracellular.Neither is the reported muscle-tissue pattern (HPA: membranous expression). Appearance alone cannot identify the source of the signal.Check morphology, compare a positive muscle section, and review no-primary and antibody-specific controls before assigning CAV3 staining (general IHC practice; HPA: tissue IHC).
Weak glandular staining is treated as a definitive positive control.Salivary glandular cells are Low, whereas skeletal myocytes and cardiomyocytes are High (HPA: tissue IHC). A weak control cannot reliably distinguish assay failure from low expression.Use skeletal muscle or heart muscle as the positive tissue control and assess membrane outlines in the relevant muscle cells (HPA: tissue IHC).

Sample controls for CAV3 IHC & IF

🧪Run skeletal muscle first: myocytes should show CAV3 staining at the sarcolemma (HPA: High in skeletal-muscle myocytes; UniProt P56539: sarcolemmal localization). Run adipose tissue as the negative: adipocytes are not detected (HPA: Not detected in adipocytes); nonmyocyte cells on the skeletal-muscle slide should provide a background reference without the myocyte sarcolemmal pattern (HPA: High in myocytes; UniProt P56539: sarcolemmal localization).
Positive control tissue: Heart muscle (Cardiomyocytes, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show CAV3 in Rh30, with annotated localisation: Plasma membrane (approved) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and a concentration-matched rabbit isotype control for the rabbit primary (selected-SKU caption: rabbit anti-CAV3); CAV3 knockout tissue, if available, provides a biological negative. Quench endogenous peroxidase in the skeletal-muscle section before HRP/DAB detection (selected-SKU caption: skeletal muscle and HRP/DAB).
⚠️Feasibility: A target-specific fixation window and fixation effect are unreported, and the exact selected-SKU paraffin-section caption does not state the fixative (selected-SKU caption: fixative unreported). The matched example used heat-mediated EDTA retrieval at pH 8.0, but does not establish whether retrieval is required (selected-SKU caption: EDTA retrieval); the supplied evidence does not establish whether frozen sections or IF would be easier. Assess staining at the sarcolemma while watching for skeletal-muscle section artefacts that obscure cell borders (UniProt P56539: sarcolemmal localization; standard IHC practice).

HPA tissue IHC evidence for CAV3

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — High consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Heart muscle Cardiomyocytes High Protein (IHC) HPA →
Skeletal muscle Myocytes High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Appendix Glandular cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Section 3

Advanced CAV3 IHC Tips

Troubleshoot CAV3 staining in paraffin sections by checking retrieval, membrane localisation, controls and scoring before interpreting changes in signal.

How should I retrieve CAV3 in paraffin sections?
Start with heat-mediated retrieval in EDTA at pH 8.0 for paraffin sections (datasheet A00990-2). The selected skeletal-muscle image used that retrieval before incubation with 2 μg/ml antibody overnight at 4°C (datasheet A00990-2). If staining is weak, keep the antibody concentration and detection conditions fixed while checking heating, cooling and buffer preparation across a positive-control section (standard IHC practice). Compare membrane definition as well as signal intensity: skeletal myocytes and cardiomyocytes provide expected positive compartments, whereas diffuse staining alone is insufficient evidence of successful retrieval (HPA tissue IHC; standard IHC practice).
Does fixation change CAV3 staining in paraffin sections?
CAV3-specific sensitivity to fixation is unknown from the supplied evidence, and the selected paraffin-section caption does not state a fixative (datasheet A00990-2). Record the specimen’s actual fixative and fixation duration, then compare sections processed under matched conditions when investigating variable staining (standard IHC practice). For a starting IHC workflow, the documented section used EDTA at pH 8.0, 10% goat-serum block and 2 μg/ml primary antibody overnight at 4°C (datasheet A00990-2). Do not assign a fixation effect to CAV3 solely because staining differs between specimens; first assess retrieval, section quality and controls alongside fixation history (standard IHC practice).
Where should convincing CAV3 staining appear?
Look for membranous staining along skeletal myocytes or cardiomyocytes in chromogenic sections (HPA tissue IHC: High in skeletal myocytes and cardiomyocytes). CAV3 is associated with the sarcolemma, caveolar membrane and Golgi membrane; its membrane topology has cytoplasmic regions at residues 1–83 and 105–151 (UniProt P56539 localisation and topology). A predominantly diffuse nuclear or widespread extracellular DAB signal does not fit that expected distribution and warrants a control review (UniProt P56539 localisation; standard IHC practice). Compare intact fibres or cells away from damaged edges, and assess the staining pattern together with morphology and a matched negative control (standard IHC practice).
How can I troubleshoot an unexpected CAV3 epitope pattern?
Check the antibody’s stated immunogen or epitope against the 151-residue CAV3 sequence before attributing discordant staining to an isoform (UniProt P56539; standard IHC practice). The supplied record annotates 0 isoforms, no transmembrane segment and cytoplasmic regions at residues 1–83 and 105–151 (UniProt P56539 topology and isoforms). It also lists 0 glycosylation sites and 0 modified residues, so these annotations do not explain a changed chromogenic pattern (UniProt P56539 processing). If the epitope remains unspecified, vary retrieval cautiously and judge results against the expected myocyte membrane distribution and negative controls (HPA tissue IHC; standard IHC practice).
How should I adapt the CAV3 localisation check for multiplex IF?
For the separate IF/ICC workflow, pair CAV3 with a marker that identifies the expected muscle cell type, and inspect each channel before interpreting overlap (HPA tissue IHC; standard IF practice). Select a fluorophore whose signal can be distinguished from tissue autofluorescence, using an unstained specimen and single-colour controls to check bleed-through (standard IF practice). Match permeabilisation to the antibody’s mapped epitope: CAV3 has cytoplasmic regions at residues 1–83 and 105–151, but the supplied evidence does not identify this antibody’s epitope (UniProt P56539 topology; standard IF practice). Evaluate membrane-enriched signal separately from vesicular signal, both of which are reported CAV3 locations (HPA subcellular).
What should I check when CAV3 DAB staining is diffuse?
First compare the stained section with a no-primary control and inspect whether DAB follows intact myocyte membranes rather than damaged tissue or section edges (HPA tissue IHC; standard IHC practice). The selected paraffin-section image used 10% goat serum, 2 μg/ml primary antibody overnight at 4°C, and a peroxidase-conjugated secondary incubated for 30 minutes at 37°C (datasheet A00990-2). Check blocking and washes, and include an endogenous-peroxidase block as part of the chromogenic workflow when appropriate (standard IHC practice). If background persists, titrate the primary antibody against a positive-control section while keeping retrieval and development consistent (standard IHC practice).
How should I score CAV3 staining across sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the scoring compartment as the membrane of morphologically intact myocytes or cardiomyocytes before reviewing experimental groups (HPA tissue IHC; standard IHC practice). For cell-based scoring, record the percentage of positive cells and staining intensity, or calculate an H-score using the same thresholds for every section (standard IHC practice). If measuring stained membrane length or area, normalise to evaluable muscle area or the number of eligible cells, and report excluded damaged regions (standard IHC practice). Keep section thickness, retrieval, antibody incubation and DAB development matched; the selected caption documents 2 μg/ml primary antibody overnight at 4°C (datasheet A00990-2; standard IHC practice).
How do I distinguish genuine CAV3 signal from artefact?
A credible positive pattern is membranous staining in skeletal myocytes or cardiomyocytes, the cell types reported as High by tissue IHC (HPA tissue IHC). CAV3 is associated with the sarcolemma and caveolar membrane, so isolated nuclear deposits or uniform extracellular colour need scrutiny (UniProt P56539 localisation; standard IHC practice). Compare suspicious signal with adjacent intact tissue, section edges, necrotic areas and a no-primary control; endogenous enzyme activity can also contribute to chromogenic staining (standard IHC practice). Treat a negative section cautiously if its positive control fails, and interpret between-specimen differences only after checking processing and morphology (standard IHC practice).
Boster reagents

Best CAV3 / Caveolin-3 IHC Antibodies

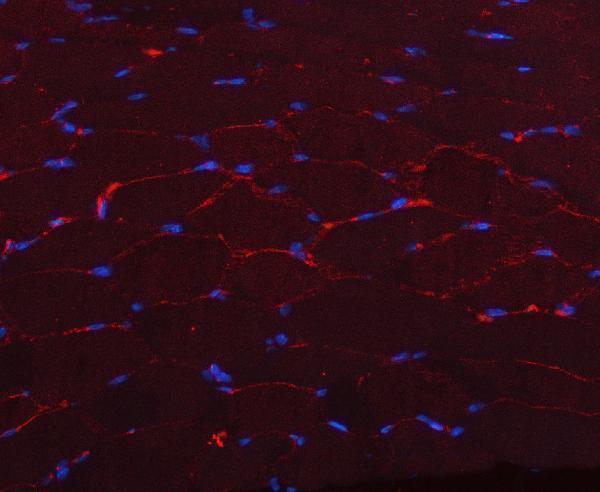
A00990-2 has IHC data from paraffin-embedded human skeletal muscle and IF data from paraffin-embedded human, mouse and rat cardiac muscle (A00990-2 image captions).

Real IHC data IHC analysis of CAV3 using anti-CAV3 antibody (A00990-2). CAV3 was detected in a paraffin-embedded section of human skeletal muscle tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-CAV3 Antibody (A00990-2) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-Caveolin-3/CAV3 Antibody ®
Cat # A00990-2

A00990-2 is the sole SKU with a rendered card; its IHC figure shows chromogenic staining of paraffin-embedded human skeletal muscle (cards payload; A00990-2 IHC image caption). Its IF images show paraffin-embedded cardiac muscle from human, mouse and rat (A00990-2 IF image captions).

Which to pick: Choose A00990-2 for tissue IHC: its own figure documents a paraffin-embedded human skeletal-muscle section with EDTA pH 8 retrieval and chromogenic detection; the fixative is unreported (A00990-2 IHC image caption). Choose A00990-2 for section IF or cross-species work based on its human, mouse and rat IF images and listed reactivity; ICC validation is unreported (A00990-2 IF image captions; catalog: applications and reactivity). M00990-2 is a human-reactive rabbit monoclonal listed for IHC, but has no IHC image caption (catalog: clone, reactivity, applications and image alts).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P56539 (CAV3_HUMAN, Caveolin-3).
  2. Human Protein Atlas. CAV3 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. CAV3 subcellular location (ICC-IF): Mainly localized to the plasma membrane. In addition localized to vesicles..
  4. Human Protein Atlas. CAV3 antibody validation summary (4 antibodies).
  5. Loss of Immunohistochemical Reactivity in Association With Handling-Induced Dark Neurons in Mouse Brains. Toxicologic pathology 2020 — PMC7113115.
  6. Vascular restenosis in coronary artery bypass grafting might be associated with VEGF-C/VEGFR-3 signaling pathway. Heart and vessels 2018 — PMC6096743.
  7. Effect of Verapamil, an L-Type Calcium Channel Inhibitor, on Caveolin-3 Expression in Septic Mouse Hearts. Oxidative medicine and cellular longevity 2021 — PMC8052133.
  8. CAV3.1 knockdown suppresses cell proliferation, migration and invasion of prostate cancer cells by inhibiting AKT. Cancer management and research 2018 — PMC6197829.
  9. PubMed PMID:9537420 — UniProt-cited evidence.
  10. PubMed PMID:9545514 — UniProt-cited evidence.
  11. PubMed PMID:9536092 — UniProt-cited evidence.