CBL / E3 ubiquitin-protein ligase CBL · IHC design guide

Design Immunohistochemistry for CBL

Plan CBL staining in paraffin sections around cytoplasmic signal in spermatogonia and subsets of immune cells (HPA tissue IHC). Use the catalog antibody's IHC-P evidence and score each cell population separately (datasheet: PB9077 IHC-P; HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for CBL (IHC for CBL): expected localisation Cytoplasmic in tissue (HPA tissue IHC), antibody PB9077, validated IHC image, and IHC protocol steps
Printable CBL IHC protocol sheet — expected localisation Cytoplasmic in tissue (HPA tissue IHC), antibody PB9077, controls and protocol steps. Open the full CBL IHC guide →

CBL Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic in tissue (HPA tissue IHC)
Staining pattern Cytoplasmic in spermatogonia and subsets of immune cells (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet PB9077)
Positive control ⓘ Testis+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific)
Caveat Immune-cell staining may complicate tissue-wide scoring (HPA tissue IHC)
Regulation Intensity varies among cell populations (HPA tissue IHC)
Isoform / epitope No annotated isoforms; no extracellular segment (UniProt)
Section 1

Recommended CBL IHC & IF Protocols

The catalog antibody’s IHC-P protocol (datasheet PB9077) is paired with a published marmoset c-CBL IHC protocol (PMC7041541).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human intestinal cancer tissues; fixative not specified (datasheet PB9077)
FixationImage fixative and duration unreported (datasheet PB9077); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet PB9077); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet PB9077)
Primary antibodyRabbit anti-CBL, 0.5-1μg/ml (datasheet PB9077)
Primary incubationOvernight at 4 °C (datasheet PB9077)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet PB9077)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultCBL-positive staining in spermatogonia cells of testis (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in spermatogonia, subsets of immune cells and lymphoid tissues. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA retrieval at pH 8.0 (datasheet PB9077); the published marmoset protocol used citrate at pH 6.0 (PMC7041541).
Section 2

What Is the Expected CBL Staining Pattern?

CBL should show predominantly cytoplasmic staining in spermatogonia, selected immune cells, and lymphoid tissue on paraffin IHC sections (HPA: tissue IHC profile). The tissue profile has Enhanced reliability, supported by agreement between antibody staining and RNA expression and by similar results from paired antibodies (HPA: tissue IHC reliability). CBL has no transmembrane segment, although UniProt also places it at the cell membrane, cilium, and Golgi apparatus (UniProt P22681: topology and subcellular location).

What am I looking at on my slide?
Strong cytoplasmic staining in spermatogonia, with less intense staining in selected lymphoid cells.This matches the reported High level in spermatogonia and Medium levels in appendix lymphoid tissue and lymph-node or tonsil germinal-center cells (HPA: tissue IHC). Compare the named cells rather than assigning one intensity to every cell in the section.
Predominantly nuclear staining, without a convincing cytoplasmic component, in the expected positive cells.Treat a nuclear-only pattern as suspect: HPA describes cytoplasmic tissue staining, and UniProt lists cytoplasm, membrane, cilium, and Golgi locations (HPA: tissue IHC profile; UniProt P22681: subcellular location). Check morphology and controls before calling it CBL signal; those sources do not establish nuclear staining as the expected IHC pattern.
Strong staining in an HPA-listed negative cell population, such as adipocytes or colon glandular cells.HPA reports CBL as Not detected in those specific cell populations (HPA: adipose tissue and colon IHC). If the expected positive control stains appropriately, consider antibody cross-reactivity or endogenous detection activity; the finding alone cannot distinguish them (general IHC practice).
Diffuse brown deposit across cells and tissue spaces, with little distinction between positive and negative cell populations.This obscures the cell-specific cytoplasmic pattern reported by HPA (HPA: tissue IHC profile). Uneven blocking, excess antibody or detection reagent, and inadequate washes are possible workflow causes; assess controls before interpreting the deposit as CBL (general IHC practice).
No staining in spermatogonia or another HPA-listed positive cell population.Absence of signal in an expected positive population makes the run difficult to interpret (HPA: High in spermatogonia; Medium in listed immune and lymphoid populations). First confirm that the relevant cells are present, then review antibody and detection controls (general IHC practice).
💡Expected CBL appearanceCall the result positive when the appropriate cells show predominantly cytoplasmic staining—strongest in spermatogonia and moderate in the listed lymphoid or immune populations—while widespread nuclear-only or cell-independent brown deposit is suspect (HPA: tissue IHC levels and profile; general IHC interpretation).
How each factor affects the staining
Cell population chosen for comparisonCBL staining varies within tissues: HPA reports High in testis spermatogonia, Medium in lung macrophages, and Not detected in bronchial respiratory epithelium (HPA: tissue IHC). Record the cell type when judging a positive or negative result.
Subcellular location and topologyCBL has no transmembrane segment and is annotated in the cytoplasm, at the membrane, in cilia, and at the Golgi (UniProt P22681: topology and subcellular location). The observed paraffin-section profile is cytoplasmic; a membrane-only requirement would overstate the tissue IHC evidence (HPA: tissue IHC profile).
Antibody validationTwo listed antibodies have Enhanced IHC validation, while the overall tissue profile also has Enhanced reliability (HPA: antibody validation and tissue IHC reliability). This supports the reported pattern, but does not verify an unlisted antibody or establish the cause of staining in an individual run.
Fixation and antigen retrievalTarget-specific fixation sensitivity and a CBL retrieval condition are unreported in the supplied HPA and UniProt evidence. Retrieval choice should therefore follow the IHC-validated antibody's instructions and be checked with appropriate controls; any adjustment is a general IHC workflow decision, not a documented CBL effect.
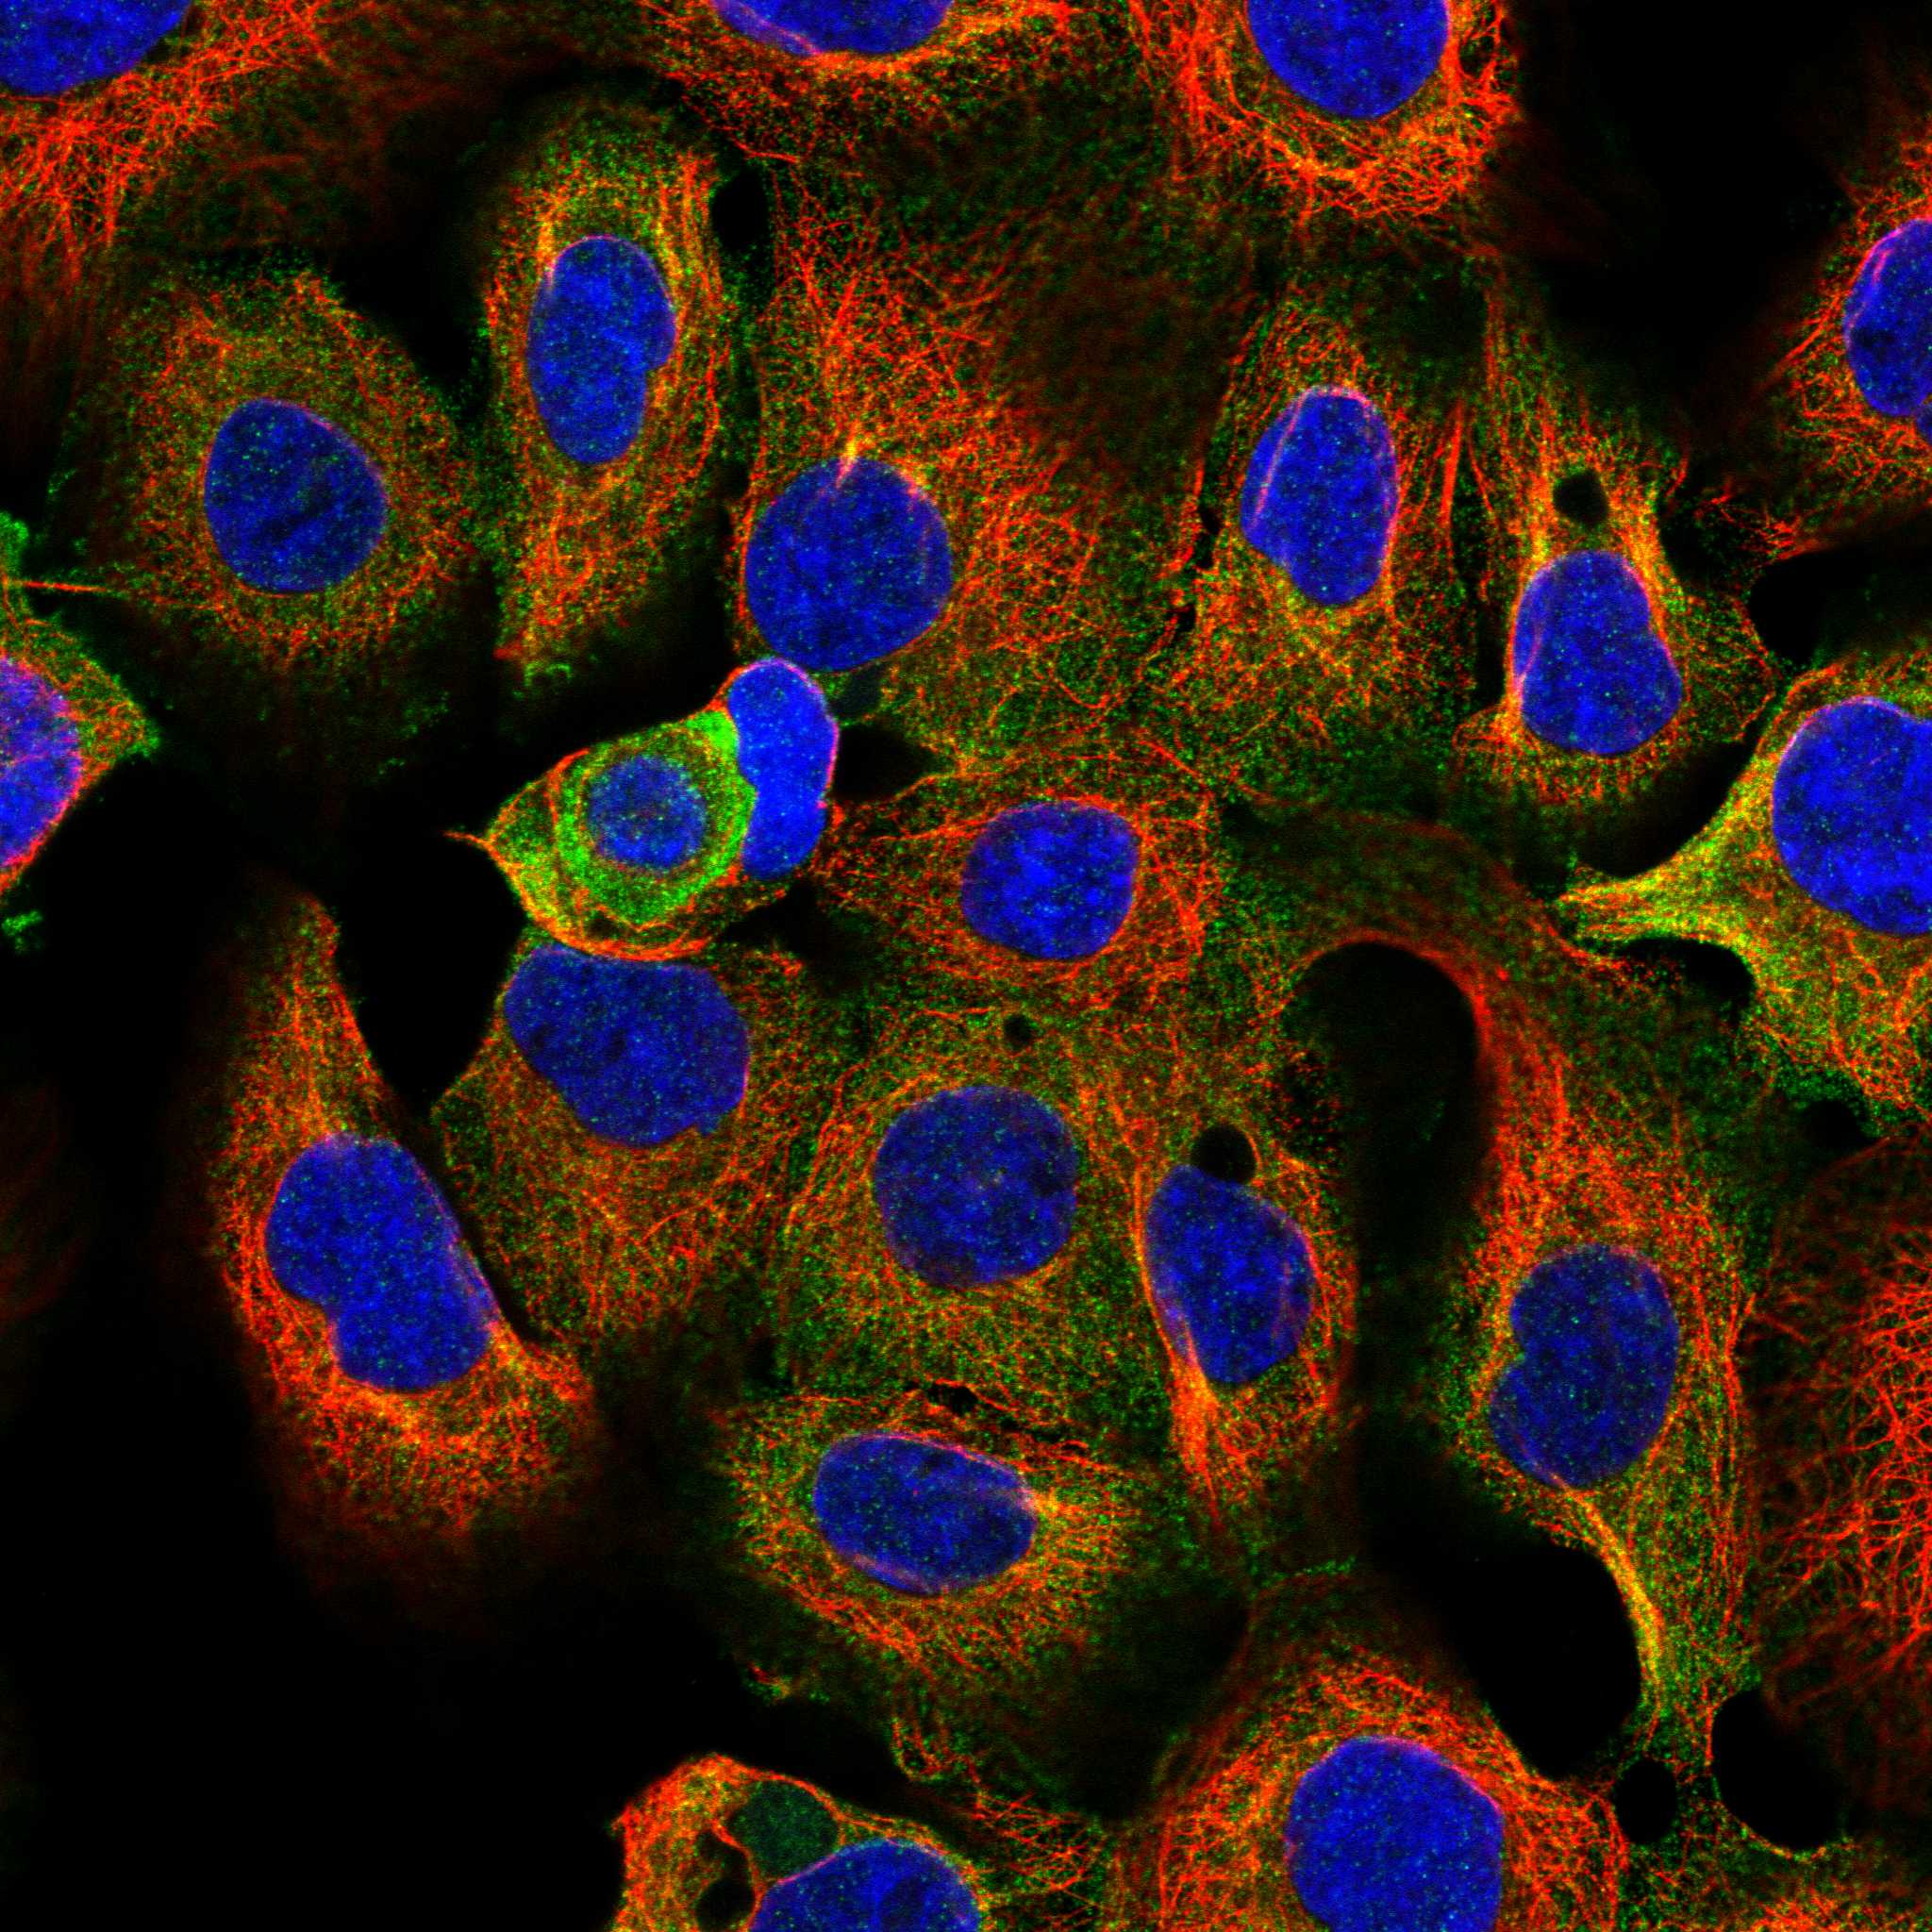
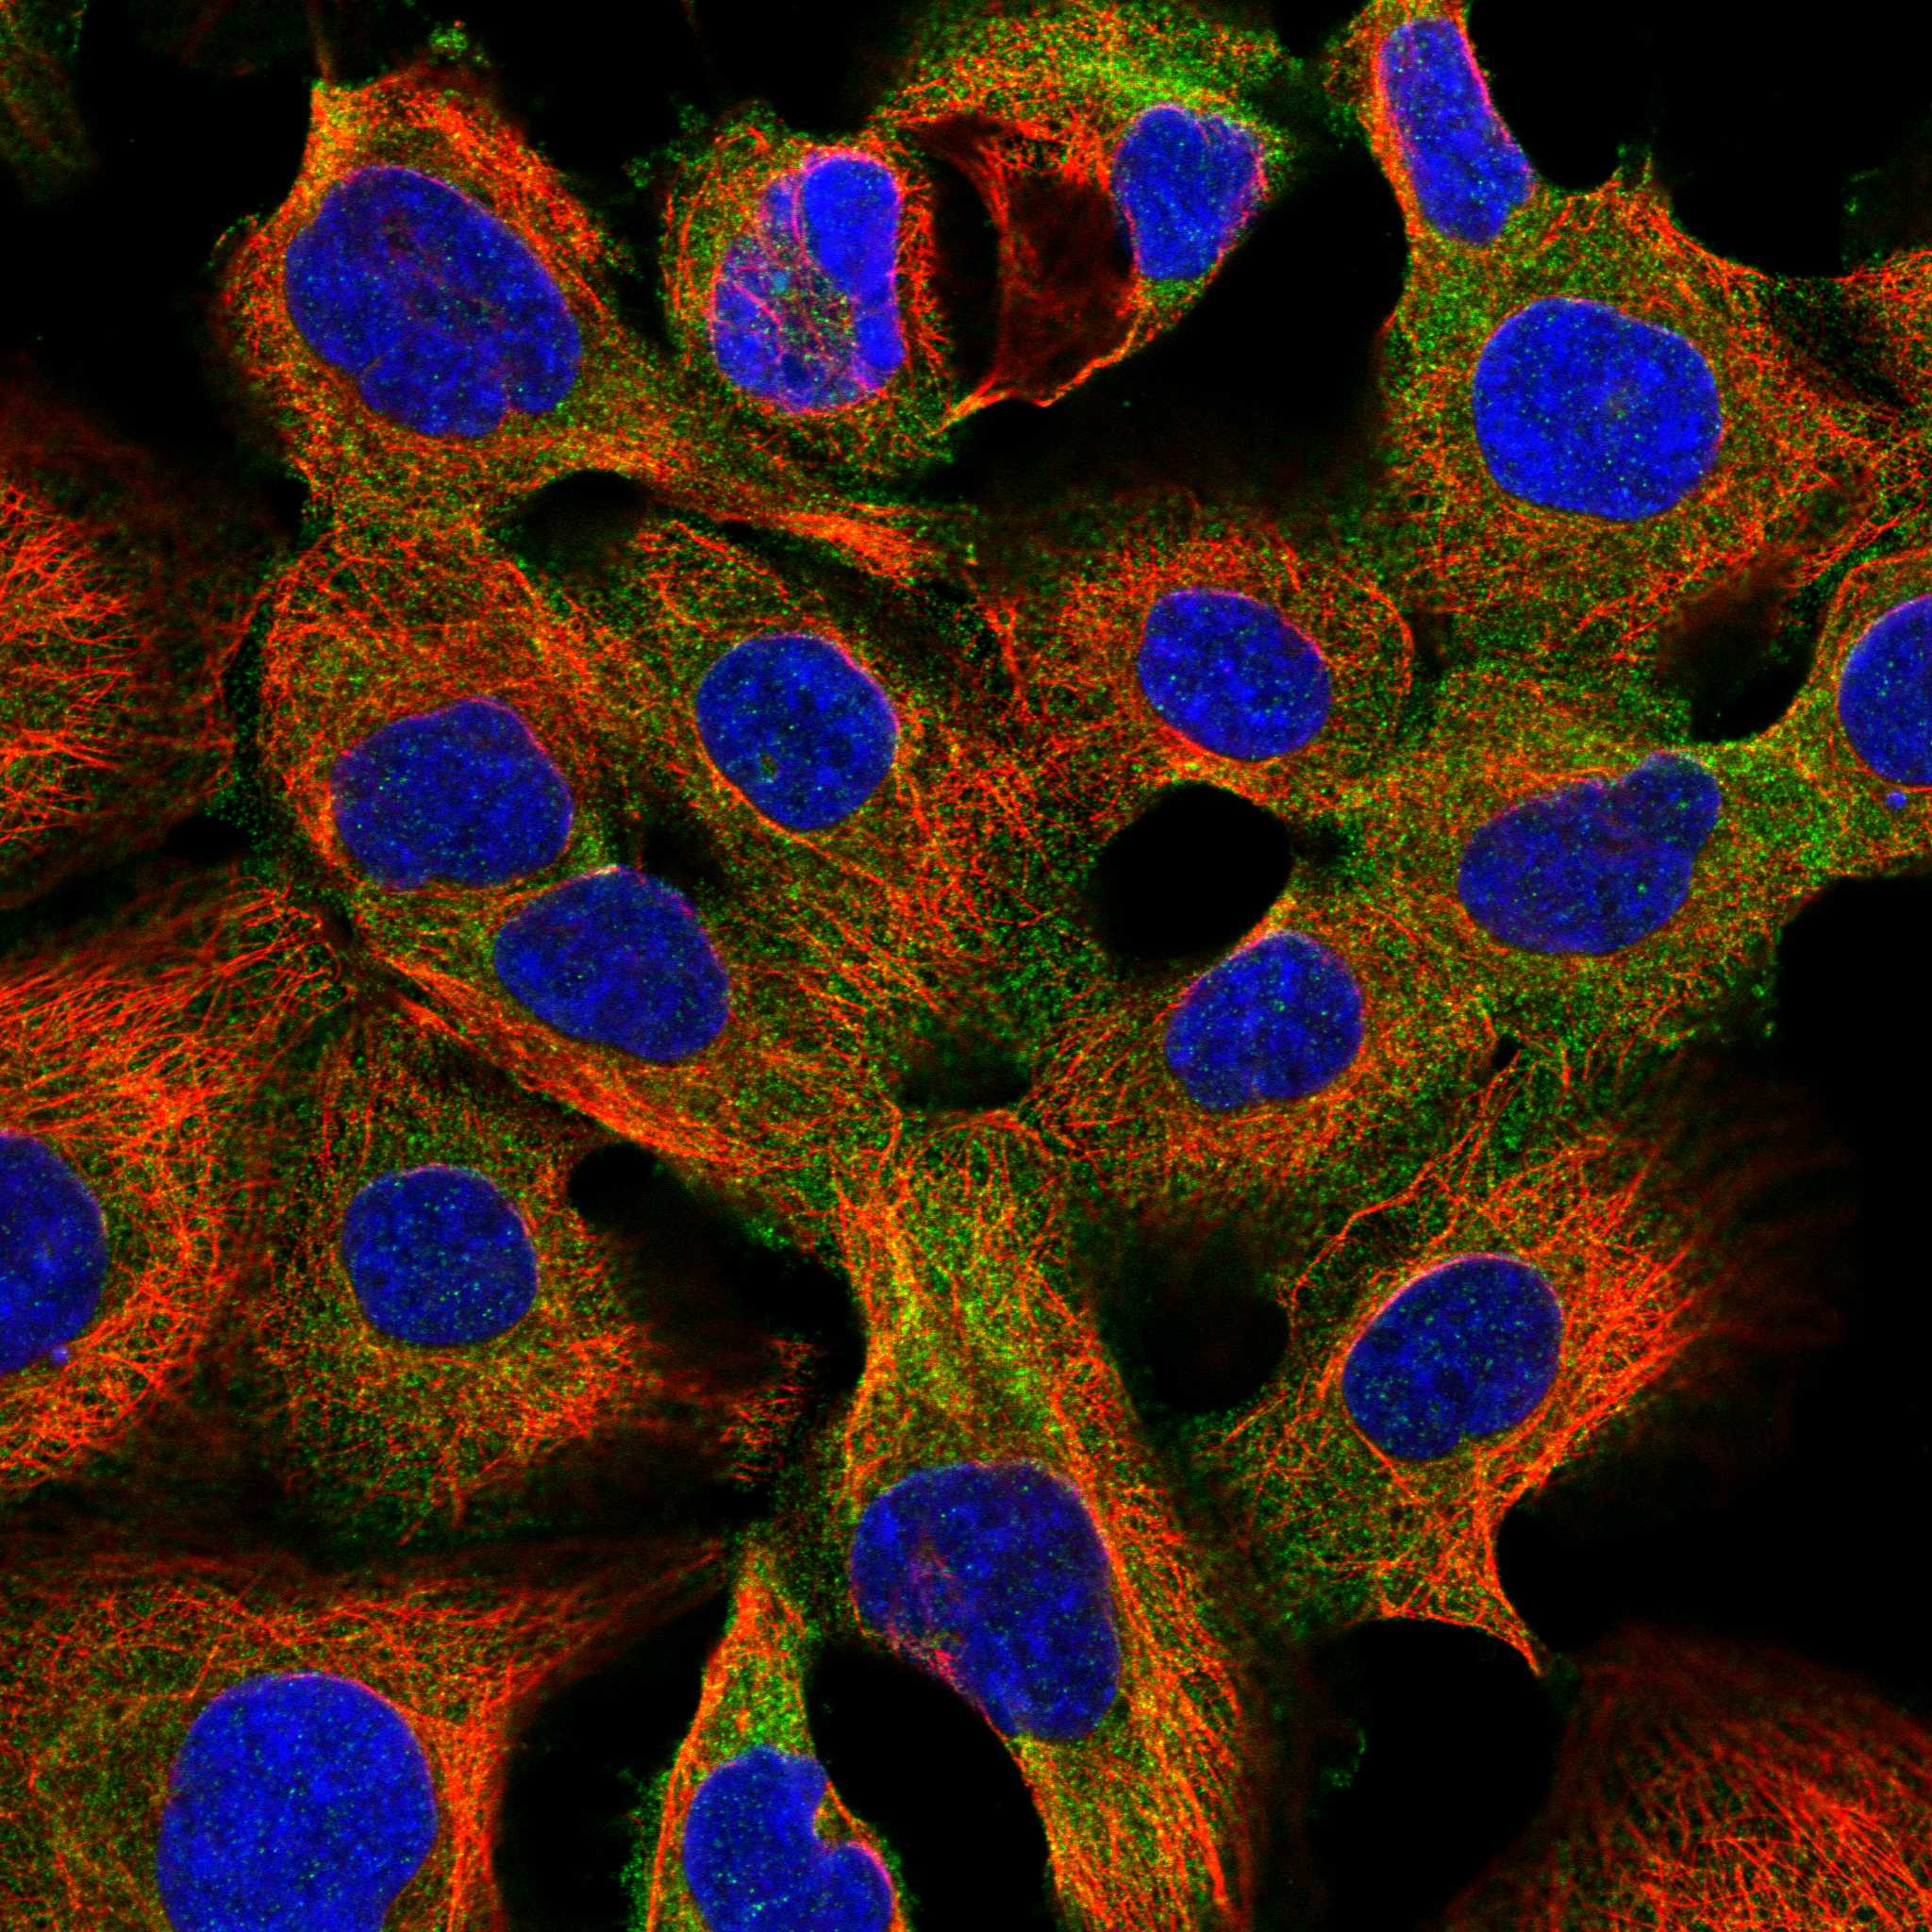
IF/ICC Q: should fluorescence match tissue IHC exactly?A: Expect mainly cytosolic signal in the reported ICC-IF setting (HPA: cytosol, Supported). HPA also lists an end piece location as approved and mitotic-spindle localization as uncertain (HPA: subcellular ICC-IF). These observations do not set a paraffin IHC scoring rule.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
The positive-control testis section appears blank.Spermatogonia may be absent from the area examined, or the antibody or detection run may have failed; HPA reports High staining specifically in spermatogonia (HPA: testis IHC).Identify spermatogonia on the counterstained section, then check the antibody run and detection controls before treating the blank result as biological absence (general IHC practice).
Only a few cells stain in a lymphoid section.The expected signal is assigned to selected populations, including germinal-center cells, rather than every cell in the section (HPA: tissue IHC profile; lymph node and tonsil IHC).Score the named population separately and compare its cytoplasmic signal with surrounding cells; avoid treating sparse staining alone as assay failure (HPA: tissue IHC; general IHC interpretation).
Brown staining covers the negative-control slide as well as the test slide.The detection system or tissue may contribute signal independently of the primary antibody; the pattern cannot be attributed to CBL on that evidence (general chromogenic IHC practice).Review the no-primary control and, when using enzyme-based detection, check the relevant endogenous-activity block and detection reagents (general chromogenic IHC practice).
Adipocytes or colon glandular cells stain strongly.Those cell populations are reported as Not detected; unexpected signal may reflect cross-reactivity or detection background (HPA: adipose tissue and colon IHC; general IHC practice).Compare the staining with a no-primary control and an HPA-listed positive population in the same run; confirm cellular morphology before assigning the signal to CBL (HPA: tissue IHC; general IHC practice).
The slide has mostly nuclear signal.Nuclear-only staining does not match the reported cytoplasmic IHC profile (HPA: tissue IHC profile). The image alone cannot identify which assay step produced it (general IHC interpretation).Recheck compartment boundaries with the counterstain, then compare the positive tissue and no-primary controls; review antibody specificity if the nuclear pattern persists (general IHC practice).
The cytoplasmic signal is too diffuse to score by cell type.Background from antibody concentration, blocking, washes, or detection can obscure a population-specific pattern (general IHC practice; HPA: tissue IHC profile).Review the antibody's IHC instructions and optimize one workflow variable at a time with positive and no-primary controls; retain the HPA-listed cell populations as the scoring reference (general IHC practice; HPA: tissue IHC).

Sample controls for CBL IHC & IF

🧪Run testis first and confirm staining in spermatogonia (High; HPA: testis, spermatogonia). Use adipose tissue as the negative tissue and expect adipocytes to be unstained (HPA: adipose tissue, adipocytes not detected); HPA does not identify a negative cell type within the testis slide, so do not assign neighboring cells as an internal negative without validation.
Positive control tissue: Testis (Spermatogonia cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show CBL in A-431, U-251MG, U2OS, RPTEC/TERT1, hTERT-RPE1 (serum starved), Sperm, KOLF2.1J, with annotated localisation: Cytosol (supported) (HPA subcellular).
Technical controls: Include no-primary (secondary-only) and host- and format-matched rabbit IgG controls (selected-SKU caption: rabbit primary), plus CBL-knockout material as a biological negative. With the caption’s biotin-based DAB detection, check the testis section for endogenous peroxidase and biotin background (selected-SKU caption: biotinylated secondary, SABC and DAB).
⚠️Feasibility: A target-specific fixation window and fixation effect are unreported, and the selected-SKU paraffin-section caption does not state the fixative (selected-SKU caption: fixative unreported). Start with heat-mediated EDTA retrieval at pH 8.0, as used in that caption, but retrieval dependency has not been established (selected-SKU caption: EDTA retrieval). The supplied evidence does not establish whether frozen sections or IF are easier; assess background and cell attribution in the testis section before scoring spermatogonia (HPA: testis, spermatogonia High).

HPA tissue IHC evidence for CBL

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — High consistency between antibody staining and RNA expression data. Paired antibodies with high similarity supports the protein profile.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Testis Spermatogonia cells High Protein (IHC) HPA →
Appendix Lymphoid tissue Medium Protein (IHC) HPA →
Bone marrow Hematopoietic cells Medium Protein (IHC) HPA →
Kidney Cells in glomeruli Medium Protein (IHC) HPA →
Lung Macrophages Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Not detected Protein (IHC) HPA →
Cervix Glandular cells Not detected Protein (IHC) HPA →
Colon Glandular cells Not detected Protein (IHC) HPA →
Section 3

Advanced CBL IHC Tips

Troubleshoot CBL staining in paraffin sections by checking retrieval, compartment, cell type and controls before comparing chromogenic scores (UniProt P22681; HPA tissue IHC).

Which retrieval condition should I try first when CBL staining is weak?
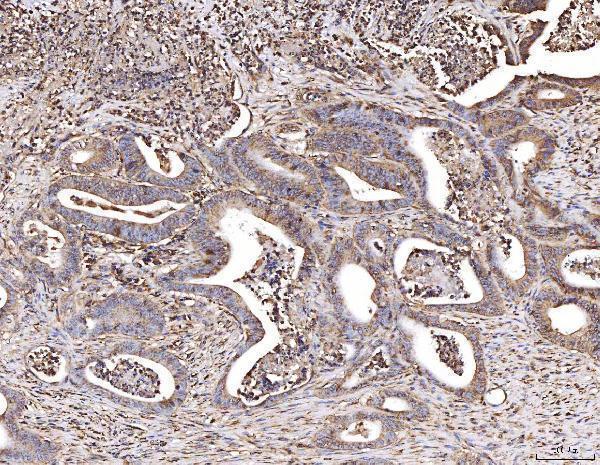
Start with heat-mediated retrieval in EDTA at pH 8.0 (datasheet PB9077). Apply the same heating and cooling conditions to test and control sections so differences in CBL signal can be assessed against tissue handling (standard IHC practice). The product image used paraffin-embedded human intestinal cancer tissue, followed by 10% goat serum blocking and 1 μg/ml primary antibody overnight at 4°C (caption PB9077). If staining remains weak, compare a second retrieval buffer on adjacent sections as a fallback, while keeping detection and exposure to DAB consistent (standard IHC practice). Judge improvement by expected cytoplasmic staining in positive cells and by background in negative controls (HPA tissue IHC; standard IHC practice).
Could fixation explain weak or patchy CBL staining in paraffin sections?
Target-specific fixation sensitivity is unknown: the selected tissue image identifies paraffin embedding but does not report its fixative (caption PB9077). Record fixative, fixation duration and processing history for each specimen before attributing differences in staining to CBL expression (standard IHC practice). Compare sections processed together and include a positive control with an expected stained cell population, such as spermatogonia or lymphoid cells (HPA tissue IHC; standard IHC practice). Keep EDTA retrieval at pH 8.0 and the catalog antibody at 1 μg/ml constant during this comparison (datasheet PB9077; caption PB9077). If signal tracks processing batches, repeat the comparison on matched sections before interpreting a biological difference (standard IHC practice).
Should CBL stain the cytoplasm, membrane or nucleus in tissue sections?
Expect predominantly cytoplasmic staining in tissue sections, including spermatogonia and subsets of immune cells (HPA tissue IHC). CBL is also annotated at the cell membrane, cilium and Golgi apparatus, and it lacks a transmembrane segment (UniProt P22681). Membrane-associated staining can therefore be plausible, particularly alongside receptor signaling, but a membrane-only pattern needs corroboration with an appropriate control (UniProt P22681 function and localisation; standard IHC practice). Treat isolated nuclear DAB staining cautiously when the expected cytoplasmic compartment is unstained (HPA tissue IHC; standard IHC practice). Compare adjacent cells and matched controls at the same counterstain and DAB development settings before assigning a compartment-specific score (standard IHC practice).
How do I assess an unexpected CBL staining pattern without a mapped epitope?
The supplied record lists one 906-aa CBL chain and no annotated isoforms, while the selected caption does not map the antibody epitope (UniProt P22681; caption PB9077). Do not assign a distinct staining pattern to an isoform or assume that this antibody recognizes a phosphorylation state (UniProt P22681; caption PB9077). CBL has documented phosphotyrosine and phosphoserine residues, so signaling state is a biological consideration, not proof of epitope masking in these sections (UniProt P22681). Compare serial sections using the same EDTA pH 8.0 retrieval and primary concentration before changing conditions (datasheet PB9077; caption PB9077; standard IHC practice). Require a second, independently characterized epitope reagent or orthogonal evidence before making an epitope-specific interpretation (standard IHC practice).
How should I check a CBL result by multiplex IF?
Use IF on a matched section as a complementary check of the chromogenic IHC pattern, with a marker identifying the expected cell population, such as spermatogonia or lymphoid cells (HPA tissue IHC; standard IF practice). Include single-stain and no-primary controls to assess channel bleed-through and tissue autofluorescence before interpreting overlap (standard IF practice). Choose a spectrally separated, preferably far-red CBL fluorophore when shorter-wavelength autofluorescence obscures signal (standard IF practice). Permeabilise sufficiently to expose cytosolic CBL, since the protein has no transmembrane segment; avoid assuming that a surface-only staining protocol reaches its intracellular epitope (UniProt P22681 topology and localisation; standard IF practice). Confirm that the IF reagent and fixation conditions work independently, because the PB9077 tissue caption documents chromogenic IHC only (caption PB9077; standard IF practice).
What should I change if CBL DAB staining is diffuse or granular?
First compare the section with a no-primary control and inspect whether precipitate, tissue edges or endogenous enzyme activity follows the apparent CBL signal (standard IHC practice). Quench endogenous peroxidase before chromogenic detection and control DAB development time across the run (standard IHC practice). The selected image used 10% goat serum blocking, 1 μg/ml primary overnight at 4°C, and biotinylated secondary for 30 minutes at 37°C (caption PB9077). If background persists, titrate the primary and strengthen washes while retaining an expected positive control (standard IHC practice; HPA tissue IHC). Prioritize a reproducible cytoplasmic pattern over uniform brown haze when judging CBL staining (HPA tissue IHC; standard IHC practice).
How should I score CBL when positive cells are unevenly distributed? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring; CBL tissue staining is described as cytoplasmic in spermatogonia and subsets of immune cells (HPA tissue IHC). For a defined population, report percentage of positive cells and an H-score from 0–300, using intensity categories applied consistently across sections (standard IHC practice). For scattered immune cells, positive-cell density per mm² may be clearer than a whole-section percentage (standard IHC practice). Normalize counts to viable tissue area or to the number of eligible cells, and exclude necrosis, folds and tissue edges by a prespecified rule (standard IHC practice). Keep retrieval, DAB development, imaging and threshold settings matched, and report compartments separately if membrane-associated signal is scored (datasheet PB9077; UniProt P22681 localisation; standard IHC practice).
How can I distinguish genuine CBL staining from tissue artefact?
A convincing result shows the expected cytoplasmic compartment in an appropriate cell population and reproduces across comparable sections (HPA tissue IHC; standard IHC practice). HPA reports high staining in spermatogonia, medium staining in lung macrophages and lymphoid populations, and no detected staining in colon glandular cells (HPA tissue IHC). Treat isolated nuclear signal, staining confined to cut edges or necrotic regions, and signal that persists without primary antibody as suspect (HPA tissue IHC; standard IHC practice). Endogenous peroxidase and uneven DAB development can mimic cellular positivity, so inspect controls before assigning a biological explanation (standard IHC practice). Membrane-associated signal can fit CBL localisation, but interpret it alongside cytoplasmic staining and cell identity rather than treating every brown membrane as specific (UniProt P22681 localisation; HPA tissue IHC; standard IHC practice).
Boster reagents

Best CBL / E3 ubiquitin-protein ligase CBL IHC Antibodies

The catalog antibodies have IHC images from human intestinal and colorectal cancer sections and mouse and rat brain sections; PB9077 also has IF data from U20S cells (catalog image captions).

Real IHC data IHC analysis of CBL using anti-CBL antibody (PB9077). CBL was detected in paraffin-embedded section of human intestinal cancer tissues. Heat mediated antigen retrieval was performed in EDTA buffer (pH8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml rabbit anti-CBL Antibody (PB9077) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC)(Catalog # SA1022) with DAB as the chromogen.
Anti-CBL Antibody ®
Cat # PB9077
Real IHC data IHC analysis of CBL using anti-CBL antibody (A00152-2). CBL was detected in a paraffin-embedded section of human colorectal cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-CBL Antibody (A00152-2) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-CBL Antibody ®
Cat # A00152-2

PB9077 has IHC images from human intestinal cancer and mouse and rat brain paraffin sections, plus an IF/ICC image from U20S cells (PB9077 image captions). A00152-2 has an IHC image from a human colorectal cancer paraffin section; its listed reactivity is human, mouse, and rat (A00152-2 image caption; catalog applications and reactivity).

Which to pick: For tissue IHC, either SKU has a paraffin-section example: PB9077 uses EDTA retrieval at pH 8.0 and 1 μg/ml primary antibody in its image caption; A00152-2 uses the same retrieval pH and 2 μg/ml in its own caption (PB9077 and A00152-2 IHC image captions). Choose PB9077 for IF/ICC because those applications and a U20S cell IF image are listed only for PB9077 among the two cards (catalog applications; PB9077 IF image caption). PB9077 has mouse and rat IHC images as well as a human example, while A00152-2 lists mouse and rat reactivity but shows only a human IHC example; both are rabbit antibodies with no clone specified, and neither IHC caption reports the fixative (catalog host, clone, reactivity, and IHC image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P22681 (CBL_HUMAN, E3 ubiquitin-protein ligase CBL).
  2. Human Protein Atlas. CBL tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. CBL subcellular location (ICC-IF): Mainly localized to the cytosol. In addition localized to the mitotic spindle and end piece..
  4. Human Protein Atlas. CBL antibody validation summary (2 antibodies).
  5. The E3 Ubiquitin Ligase Cbl-b Predicts Favorable Prognosis in Breast Cancer. Frontiers in oncology 2020 — PMC7219434.
  6. The E3 ubiquitin ligase Cbl-b improves the prognosis of RANK positive breast cancer patients by inhibiting RANKL-induced cell migration and metastasis. Oncotarget 2015 — PMC4673209.
  7. The ubiquitin ligase c-CBL is expressed in undifferentiated marmoset monkey pluripotent stem cells but is not a general stem cell marker. Primate biology 2017 — PMC7041541.
  8. Cbl-b predicts postoperative survival in patients with resectable pancreatic ductal adenocarcinoma. Oncotarget 2017 — PMC5593633.
  9. PubMed PMID:2030914 — UniProt-cited evidence.
  10. PubMed PMID:16554811 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.