CCT6A / T-complex protein 1 subunit zeta · IHC design guide

Design Immunohistochemistry for CCT6A

Plan CCT6A paraffin-section IHC around the general cytoplasmic staining reported in tissues (HPA tissue IHC). Compare high-staining colon glandular cells with ovarian stromal cells where staining was not detected, and account for the reported possibility of detecting proteins from more than one gene (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for CCT6A (IHC for CCT6A): expected localisation General cytoplasmic staining (HPA tissue IHC), antibody A09373-1, validated IHC image, and IHC protocol steps
Printable CCT6A IHC protocol sheet — expected localisation General cytoplasmic staining (HPA tissue IHC), antibody A09373-1, controls and protocol steps. Open the full CCT6A IHC guide →

CCT6A Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation General cytoplasmic staining (HPA tissue IHC)
Staining pattern Cytoplasmic staining in glandular, epithelial and neuronal cells (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Ovary
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Staining may reflect proteins from more than one gene (HPA tissue IHC)
Regulation Low tissue specificity (HPA tissue RNA)
Isoform / epitope 2 isoforms; epitope differences are unspecified (UniProt)
Section 1

Recommended CCT6A IHC & IF Protocols

The catalog antibody’s IHC-P protocol is accompanied by published CCT6A protocols for astrocytoma and Ewing sarcoma specimens (PMC8418478; PMC12174516; PMC7850773).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human breast carcinoma tissue; fixative not specified (datasheet A09373-1)
FixationImage fixative and duration unreported (datasheet A09373-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-CCT6A, 1:100-1:300 (datasheet A09373-1)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultCCT6A-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic expression. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 retrieval at 95–98 °C for 20 min (page retrieval). The astrocytoma study used microwave retrieval with EDTA for 20 min (PMC8418478).
Section 2

What Is the Expected CCT6A Staining Pattern?

CCT6A is a cytoplasmic protein with no annotated transmembrane segment (UniProt P40227: subcellular location and topology). In paraffin-section IHC, expect cytoplasmic staining in the glandular, epithelial, and neuronal cell populations reported as high by HPA (HPA: tissue IHC). HPA describes the overall pattern as general cytoplasmic expression, but rates its tissue IHC evidence Supported with medium consistency and cautions that the antibodies target proteins from more than one gene (HPA: tissue IHC reliability).

What am I looking at on my slide?
Cytoplasmic stain in colon glandular cells or bronchial respiratory epithelial cells.This matches two reported high-staining populations (HPA: colon and bronchus, High). Assess the signal within the named cells rather than treating every stained structure in the section as equally informative (general IHC practice).
Predominantly nuclear or crisp cell-surface staining, with little cytoplasmic signal.That compartment pattern conflicts with UniProt's cytoplasmic assignment and lack of a transmembrane segment (UniProt P40227: location and topology). Check whether the apparent signal follows counterstain, tissue edges, or detection background before calling it CCT6A (general IHC practice).
Strong staining confined to ovarian stromal cells instead of the expected positive population.HPA reports ovarian stromal cells as Not detected (HPA: ovary). Investigate nonspecific binding or endogenous detection activity; the HPA warning about multi-gene targeting prevents assigning an unexpected signal to CCT6A from appearance alone (HPA: tissue IHC caution; general IHC practice).
Uniform haze across cells and surrounding tissue, obscuring cell boundaries.This is difficult to score as a cytoplasmic cell pattern (general IHC practice). Compare it with a no-primary control and inspect blocking, washing, and detection conditions before interpreting tissue distribution (general IHC practice).
No stain in the expected cells of a colon section.Colon glandular cells are reported High (HPA: colon). First verify tissue integrity and the staining run with appropriate controls; a blank section alone cannot establish true CCT6A absence, especially given the Supported, medium-consistency HPA assessment (general IHC practice; HPA: tissue IHC reliability).
💡Expected CCT6A appearanceCall a result positive when cytoplasmic staining is clear in an HPA High population, such as colon glandular cells; predominantly nuclear, surface-only, or uniform background staining is discordant (HPA: colon, High and general cytoplasmic profile; UniProt P40227: topology; general IHC practice).
How each factor affects the staining
Compartment and topologyUniProt assigns CCT6A to the cytoplasm and annotates no transmembrane segment or signal peptide (UniProt P40227). These annotations support an intracellular pattern; they do not specify an exact stain intensity (UniProt P40227).
Choice of comparison tissueHPA reports High staining in several glandular, epithelial, and neuronal populations, Low in smooth muscle cells, and Not detected in ovarian stromal cells (HPA: tissue IHC). Use those observations as comparisons, not universal positivity thresholds (general IHC practice).
Antibody evidenceThree listed antibodies have Supported IHC status (HPA: HPA042996, HPA045576, HPA049949). HPA also warns of multi-gene targeting and pending external verification, so staining alone does not establish CCT6A specificity (HPA: tissue IHC reliability).
Antigen retrievalTarget-specific fixation effects are not established by the supplied assay evidence. Verify with a matched IHC source before attributing a result to fixation.
IF/ICC Q&A: Where should signal appear?In ICC-IF, HPA reports an approved cytosolic location, while cautioning that the evidence comes from antibodies targeting proteins from multiple genes (HPA: subcellular ICC-IF). Interpret this as a location reference, not independent proof of CCT6A specificity (HPA: subcellular caution).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Expected colon glandular cytoplasm is blank.A staining-run or tissue-quality problem is possible (general IHC practice); HPA reports this population High but its IHC reliability is Supported (HPA: colon; HPA: tissue IHC reliability).Check a known-positive section and run controls, then review retrieval, antibody dilution, and detection conditions without assuming target-specific fixation sensitivity (general IHC practice).
Signal is chiefly nuclear or outlines cell membranes.The pattern disagrees with cytoplasmic localisation and no annotated transmembrane segment (UniProt P40227: location and topology).Inspect counterstain and no-primary controls; reassess the compartment in intact cells before scoring a positive result (general IHC practice).
Ovarian stromal cells stain strongly.That differs from HPA's Not detected observation (HPA: ovary); nonspecific binding or endogenous detection activity is possible (general IHC practice).Compare with no-primary and detection controls, then examine whether the expected cytoplasmic pattern also appears in an HPA High population (general IHC practice; HPA: tissue IHC).
Broad brown haze obscures individual cells.Background from antibody binding, inadequate washing, or detection chemistry may prevent compartment scoring (general IHC practice).Review blocking and washes, compare a no-primary control, and adjust antibody dilution or detection conditions using controls (general IHC practice).
Smooth muscle appears weaker than nearby epithelium.Low staining in smooth muscle cells can fit the HPA tissue profile (HPA: smooth muscle, Low).Score each cell type separately and compare with an HPA High population on the run before judging the result inadequate (general IHC practice; HPA: tissue IHC).
Two antibodies produce different staining patterns.HPA rates the listed antibodies Supported and cautions that antibodies target proteins from more than one gene (HPA: antibody statuses and tissue IHC reliability).Compare compartment and cell-type patterns against UniProt and HPA, alongside controls; do not resolve the discrepancy by stain intensity alone (UniProt P40227: cytoplasm; HPA: tissue IHC; general IHC practice).

Sample controls for CCT6A IHC & IF

🧪Run colon first and require staining in its glandular cells (HPA: High in colon glandular cells). Run ovarian stroma as the negative tissue (HPA: Not detected in ovarian stroma cells); on the colon slide, use neighboring nonglandular cells to assess background, without assuming they are CCT6A-negative (HPA: colon glandular cells High; other colon cell types not reported in the supplied rows).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Ovary (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show CCT6A in A-431, PC-3, U2OS, with annotated localisation: Cytosol (approved) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and an isotype control matched to the primary antibody’s host species, clonality and concentration. Use a CCT6A knockout sample or peptide competition as a target-specific control; peptide blocking was shown for the selected antibody in a paraffin-section image (selected-SKU caption: A09373-1). For chromogenic colon IHC, quench endogenous peroxidase and check the no-primary slide for residual staining.
⚠️Feasibility: A CCT6A-specific fixation window and antigen-retrieval dependence are unreported in the supplied evidence; the selected paraffin-section caption does not state its fixative (selected-SKU caption: A09373-1). There is no supplied basis to judge frozen sections or IF easier than paraffin IHC. For IF/ICC, cytosolic signal is plausible (UniProt P40227: Cytoplasm; HPA: Cytosol approved), but interpret it cautiously because the HPA localisation summary notes antibodies targeting proteins from multiple genes; colonic endogenous peroxidase can complicate chromogenic scoring.

HPA tissue IHC evidence for CCT6A

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data. Caution, targets protein from more than one gene. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →
Caudate Neuronal cells High Protein (IHC) HPA →
Cerebral cortex Neuronal cells High Protein (IHC) HPA →
Colon Glandular cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Ovary Ovarian stroma cells Not detected Protein (IHC) HPA →
Section 3

Advanced CCT6A IHC Tips

Troubleshoot CCT6A staining in paraffin sections by checking cytoplasmic localisation, controls and processing history before interpreting staining intensity (UniProt P40227; HPA tissue IHC).

What retrieval should I try when CCT6A staining is weak in paraffin sections?
Start with citrate pH 6.0 heat-induced retrieval at 95–98 °C for 20 min (page retrieval setting). Keep section thickness, cooling and primary-antibody conditions consistent while comparing a weak run with a previously successful control section (standard IHC practice). CCT6A is cytoplasmic and has no transmembrane segment, so evaluate recovered signal in the cytoplasm rather than treating nuclear colour as evidence of better retrieval (UniProt P40227 subcellular location and topology). If staining remains weak, compare a second retrieval condition on adjacent sections and judge improvement against tissue preservation and background; no alternative buffer is established here for CCT6A (standard IHC optimisation; supplied retrieval setting).
Could fixation explain faint or uneven CCT6A staining?
The selected antibody image shows paraffin-embedded human breast carcinoma, but its caption does not state a fixative; target-specific fixation sensitivity is therefore unknown (A09373-1 tissue-IHC caption). Record the specimen's actual fixative and fixation interval, then compare sections with similar processing histories using the same retrieval and staining run (standard IHC practice). Examine weak areas for poor morphology or uneven processing before changing antibody concentration, and compare internal tissue regions where preservation is better (standard IHC practice). UniProt lists cytoplasmic localisation and several modified residues, but those annotations do not establish how fixation affects this epitope (UniProt P40227 subcellular location and modified residues).
Where should convincing CCT6A staining appear in tissue sections?
Look primarily for cytoplasmic staining: UniProt places CCT6A in the cytoplasm, while HPA reports general cytoplasmic tissue expression (UniProt P40227 subcellular location; HPA tissue IHC profile). HPA also assigns an approved cytosol location in cell imaging, although that assessment carries a warning about antibodies recognising proteins from multiple genes (HPA subcellular). In chromogenic sections, assess signal within morphologically intact cells and compare it with the counterstained nuclei and nearby unstained compartments (standard IHC practice). Predominantly nuclear or surface-restricted colour deserves investigation of background, segmentation or antibody specificity before it is reported as CCT6A localisation (UniProt P40227 subcellular location and topology; standard IHC practice).
Can this stain distinguish CCT6A isoforms or a modified epitope?
The record lists 2 CCT6A isoforms, but the supplied antibody caption gives no epitope sequence or isoform-reactivity data (UniProt P40227 isoforms; A09373-1 tissue-IHC caption). It therefore cannot establish which isoform contributes to a stained cell, even when the cytoplasmic pattern looks plausible (UniProt P40227 isoforms and subcellular location; supplied antibody evidence). UniProt records acetylated residues and phosphoserine 205, yet staining intensity alone does not identify any of those modifications (UniProt P40227 modified residues; standard IHC interpretation). For an isoform-specific claim, obtain epitope mapping and appropriate specificity evidence, then confirm that the stained compartment matches the expected cytoplasmic distribution (standard antibody validation practice; UniProt P40227 subcellular location).
How should I check a CCT6A IF signal against the chromogenic IHC result?
Treat IF/ICC as a separate assay and compare its cellular pattern with the cytoplasmic expectation used to interpret the IHC section (UniProt P40227 subcellular location; HPA tissue IHC profile). Multiplex with a marker identifying the cell population being assessed, and inspect each channel separately before attributing overlap to the same cells (standard IF practice). Choose a fluorophore whose emission avoids the specimen's strongest autofluorescence, with single-colour controls to reveal bleed-through (standard IF practice). Because CCT6A is cytoplasmic and has no transmembrane segment, optimise permeabilisation for intracellular access while checking cell morphology; the supplied IHC caption provides no IF fixation or permeabilisation conditions (UniProt P40227 subcellular location and topology; A09373-1 tissue-IHC caption).
How can I separate diffuse CCT6A staining from chromogenic background?
Diffuse cytoplasmic staining can be plausible because HPA describes general cytoplasmic expression, but its tissue assessment warns that the antibodies may recognise proteins from multiple genes (HPA tissue IHC profile and reliability description). Compare a no-primary control and appropriately processed adjacent sections for nonspecific colour, and inspect blank spaces as well as intact cells (standard IHC practice). Include a peroxidase block before chromogenic detection and check whether DAB colour persists in the control; these are general workflow checks, not CCT6A-specific validation (standard chromogenic IHC practice). The selected breast-carcinoma image includes peptide blocking, which supports an antibody-dependent signal in that image but does not prove exclusive CCT6A recognition (A09373-1 tissue-IHC caption; HPA tissue IHC reliability description).
How should I score heterogeneous CCT6A staining across sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the scored cell population and cytoplasmic compartment before measuring, since the expected distribution is cytoplasmic (UniProt P40227 subcellular location; HPA tissue IHC profile). For comparable sections, report either the percentage of positive cells or a cytoplasmic H-score that combines intensity and percentage, using the same threshold and counterstain review throughout (standard IHC scoring practice). If counting positive cells, express the result per mm² of analysable tissue and exclude empty space and necrosis consistently (standard image-analysis practice). Normalise comparisons to the eligible cell population or viable tissue area, and document batch controls because HPA reports only medium agreement between antibody staining and RNA expression (standard IHC scoring practice; HPA tissue IHC reliability description).
What evidence separates true CCT6A positivity from an artefact?
A credible result shows intracellular cytoplasmic colour in intact cells, consistent with UniProt and HPA localisation rather than a dominant nuclear or cell-surface pattern (UniProt P40227 subcellular location and topology; HPA tissue IHC profile). Check cell identity against tissue morphology: HPA reports high staining in several epithelial, glandular and neuronal populations, while ovarian stromal cells are listed as not detected (HPA tissue IHC). Discount staining confined to section edges or necrotic areas, and use a no-primary control to investigate colour caused by endogenous enzyme activity (standard IHC practice). Interpret peptide-blocked signal cautiously because the selected image demonstrates blocking in breast carcinoma, while HPA warns of possible recognition of proteins from multiple genes (A09373-1 tissue-IHC caption; HPA tissue IHC reliability description).
Boster reagents

Best CCT6A / T-complex protein 1 subunit zeta IHC Antibodies

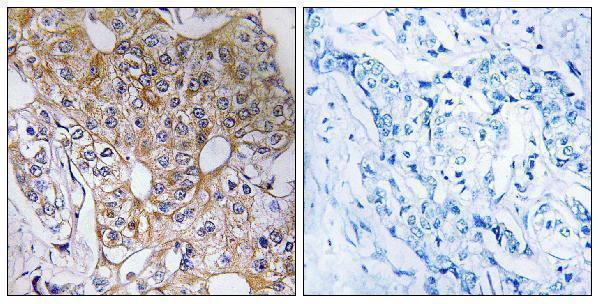
A09373-1 has an IHC image from paraffin-embedded human breast carcinoma and lists IF use (A09373-1 image caption; catalog applications). Both antibodies list human, mouse, and rat reactivity (catalog reactivity).

Real IHC data Immunohistochemistry analysis of paraffin-embedded human breast carcinoma tissue, using CCT6A Antibody. The picture on the right is blocked with the synthesized peptide.
Anti-TCP-1 zeta CCT6A Antibody
Cat # A09373-1

The rendered card is A09373-1, whose IHC image shows paraffin-embedded human breast carcinoma tissue alongside a peptide-blocked comparison (A09373-1 image caption). It also lists IF use and human, mouse, and rat reactivity, but supplies no IF image (catalog applications; catalog reactivity; catalog IF image alts).

Which to pick: For tissue IHC, pick A09373-1 when working with paraffin sections: its own image documents human breast carcinoma tissue, though the fixative is unreported (A09373-1 image caption). For IF, A09373-1 lists a 1:50 dilution; ICC validation and an IF image are not supplied (catalog IF dilution; catalog applications; catalog IF image alts). For mouse or rat IHC, both SKUs list reactivity, but the only supplied IHC image is A09373-1 on human tissue; A09373-2 is listed as polyclonal and has no IHC image (catalog reactivity; catalog IHC image alts; A09373-2 dilution raw).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P40227 (TCPZ_HUMAN, T-complex protein 1 subunit zeta).
  2. Human Protein Atlas. CCT6A tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. CCT6A subcellular location (ICC-IF): Localized to the cytosol. Caution: Based on antibodies targeting proteins from multiple genes..
  4. Human Protein Atlas. CCT6A antibody validation summary (3 antibodies).
  5. Chaperonin-containing tailless complex polypeptide 1 subunit 6A correlates with increased World Health Organization grade, less isocitrate dehydrogenase mutation, and deteriorative survival of astrocytoma patients. Journal of clinical laboratory analysis 2021 — PMC8418478.
  6. CCT6A alleviates pulmonary fibrosis by inhibiting HIF-1α-mediated lactate production. Journal of molecular cell biology 2024 — PMC11574388.
  7. Prognostic Significance of Chaperonin-Containing Tailless Complex Polypeptide 6A (CCT6A) in Ewing Sarcoma. Asian Pacific journal of cancer prevention : APJCP 2025 — PMC12174516.
  8. CCT6A, a novel prognostic biomarker for Ewing sarcoma. Medicine 2021 — PMC7850773.
  9. PubMed PMID:8034610 — UniProt-cited evidence.
  10. PubMed PMID:12853948 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.