This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic CDK10 IHC in paraffin sections using the general cytoplasmic tissue pattern (HPA tissue IHC). HPA reports high staining in liver hepatocytes and no detection in heart cardiomyocytes, but rates its tissue IHC evidence uncertain pending external verification (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | General cytoplasmic tissue staining (HPA tissue IHC) | |
| Staining pattern | Cytoplasmic staining in glandular cells and hepatocytes (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | Cerebellum+3 more · see all |
| Fixation | Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A06507) | |
| Caveat | Staining–RNA consistency is medium; verification is pending (HPA tissue IHC) | |
| Regulation | Expression regulation is unannotated (UniProt) | |
| Isoform / epitope | 7 isoforms; check epitope coverage before comparing them (UniProt) |
The catalog antibody’s IHC-P protocol is accompanied by three published CDK10 IHC protocols (PMC5604441; PMC4513615; PMC10879231).
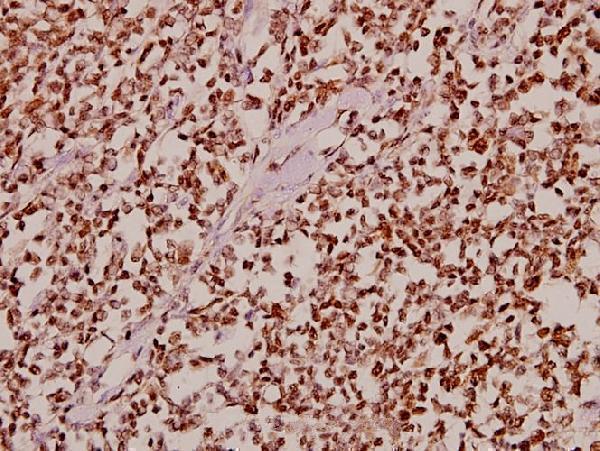
| Sample | Paraffin-embedded human tonsil carcinoma tissue; fixative not specified (datasheet A06507) |
| Fixation | Image fixative and duration unreported (datasheet A06507); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-CDK10, 1:50-1:200 (datasheet A06507) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | CDK10-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic expression. No signal in the no-primary control. |
CDK10 is annotated in the cytoplasm, cytoskeleton and cilium basal body, with no transmembrane segment (UniProt Q15131). In paraffin tissue sections, expect predominantly cytoplasmic staining in cell populations reported as positive, including liver hepatocytes and colon glandular cells (HPA: general cytoplasmic expression; High in those cells). Treat the pattern as provisional: tissue IHC reliability is Uncertain, with medium agreement between staining and RNA data (HPA: Uncertain).
| Cytoplasmic staining is prominent in hepatocytes or colon glandular cells, with interpretable cell boundaries. | This matches the reported compartment and two High staining populations (HPA: general cytoplasmic expression; High in liver hepatocytes and colon glandular cells). Compare cells within the section before assigning intensity; the HPA profile has Uncertain reliability (HPA: Uncertain). |
| Signal is exclusively nuclear, with little or no cytoplasmic staining in the same cells. | An exclusively nuclear result conflicts with the supplied location evidence (UniProt Q15131: cytoplasm, cytoskeleton and cilium basal body; HPA: general cytoplasmic expression). Check counterstain alignment and detection controls; an unexpected compartment can reflect artefact or antibody cross-reactivity (standard IHC practice). |
| Strong staining appears in cardiomyocytes or cerebellar granular layer cells. | Those populations were reported as Not detected (HPA: cardiomyocytes and cerebellar granular layer cells). Investigate antibody cross-reactivity or endogenous detection activity before calling them CDK10 positive (standard IHC practice). A discordant result warrants checking because the HPA tissue profile remains Uncertain (HPA: Uncertain). |
| Chromogen is spread across tissue or empty areas without a clear cell pattern. | Diffuse background cannot establish cytoplasmic CDK10 localisation (standard IHC practice; HPA: general cytoplasmic expression). Review the no-primary control, blocking and detection steps; background may obscure a real cell-associated signal (standard IHC practice). |
| No staining is visible in an adequately preserved liver or colon section. | Absence in reported High populations weakens confidence in this run (HPA: High in liver hepatocytes and colon glandular cells). Check the positive control and staining workflow before interpreting other tissues as negative (standard IHC practice). HPA's Uncertain rating also limits certainty about any individual specimen (HPA: Uncertain). |
| Compartment and topology (UniProt Q15131) | CDK10 has no transmembrane segment and is annotated in the cytoplasm, cytoskeleton and cilium basal body (UniProt Q15131). Use the broad cytoplasmic IHC pattern as the practical tissue expectation (HPA: general cytoplasmic expression); basal-body staining is a possible location, not an established paraffin-section readout (UniProt Q15131; HPA: general cytoplasmic expression). |
| Tissue and antibody evidence (HPA: Uncertain) | The tissue profile reports High staining in several populations but only medium agreement with RNA expression; external verification is pending (HPA: Uncertain). HPA007451 is rated Uncertain for IHC (HPA: HPA007451 IHC Uncertain). Treat control tissues as comparison points, not proof of specificity (standard IHC practice). |
| Isoforms and modification (UniProt Q15131) | Seven isoforms and a reported phosphothreonine at residue 196 are annotated (UniProt Q15131: isoforms 1–7; modified residue 196). The supplied evidence does not identify an antibody epitope or show whether these features alter IHC staining; avoid explaining discordant staining by either feature without antibody-specific evidence. |
| IF/ICC: where should signal appear? | Cytoplasmic signal is the location to assess first (UniProt Q15131: cytoplasm; HPA: general cytoplasmic expression). The HPA subcellular record supplies no main location or ICC-IF images, and HPA007451 has no ICC validation status. Treat any finer IF/ICC localisation as unconfirmed. |
| Situation | Likely cause | Next action |
|---|---|---|
| The reported positive tissue has no visible signal. | A failed staining or detection step is possible (standard IHC practice); liver hepatocytes and colon glandular cells were reported High (HPA: High). | Review the positive control, antibody application, detection reagents and counterstain on the same run (standard IHC practice). Repeat with the IHC-validated antibody's documented conditions if a run control failed (standard IHC practice). |
| Staining is nuclear only. | The observed compartment disagrees with the supplied cytoplasmic location evidence (UniProt Q15131: cytoplasm; HPA: general cytoplasmic expression). | Confirm that chromogen and nuclear counterstain are being distinguished, then review a positive tissue and no-primary control (standard IHC practice). Record the discordance rather than scoring nuclear-only signal as the expected pattern. |
| Cardiomyocytes or cerebellar granular layer cells stain strongly. | These cells were reported Not detected; cross-reactivity or endogenous detection activity is possible (HPA: Not detected; standard IHC practice). | Compare a no-primary control and check the detection system's endogenous-activity blocking step (standard IHC practice). Reassess specificity before interpreting the cells as positive; HPA tissue reliability is Uncertain (HPA: Uncertain). |
| Diffuse colour obscures cell boundaries. | Nonspecific background or detection-reagent deposit may prevent localisation from being read (standard IHC practice). | Inspect the no-primary control and review blocking, washing and chromogen development (standard IHC practice). Score only interpretable, cell-associated staining (standard IHC practice). |
| Only faint staining appears in a candidate control tissue. | Cell choice may matter: salivary glandular cells and skeletal muscle myocytes were reported Low, whereas hepatocytes were High (HPA: Low in salivary gland and skeletal muscle; High in liver). | Choose a reported High population for comparison, and score the specified cells rather than the whole tissue (HPA: High in liver hepatocytes; standard IHC practice). Keep the HPA Uncertain rating in the interpretation (HPA: Uncertain). |
| Two tissue sections yield different positive-cell patterns. | The profile spans High, Low and Not detected populations, and its tissue IHC reliability is Uncertain (HPA: tissue IHC profile; HPA: Uncertain). | Identify and compare the relevant cell populations, then review controls and staining consistency across the run (standard IHC practice). Report the observed compartment and intensity with the specific tissue and cell type, without treating every difference as a biological change. |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Uncertain — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | High | Protein (IHC) | HPA → |
| Caudate | Glial cells | High | Protein (IHC) | HPA → |
| Colon | Glandular cells | High | Protein (IHC) | HPA → |
| Epididymis | Glandular cells | High | Protein (IHC) | HPA → |
| Liver | Hepatocytes | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Cerebellum | Cells in granular layer | Not detected | Protein (IHC) | HPA → |
| Heart muscle | Cardiomyocytes | Not detected | Protein (IHC) | HPA → |
| Ovary | Follicle cells | Not detected | Protein (IHC) | HPA → |
| Placenta | Decidual cells | Not detected | Protein (IHC) | HPA → |
Troubleshoot CDK10 staining in paraffin sections by checking retrieval, controls, cellular distribution, and scoring before interpreting biological differences.
A06507 has real IHC data from paraffin-embedded human tonsil carcinoma (image caption). Human, Mouse, and Rat reactivity is listed (catalog); no IF figure is provided (catalog).
A06507 is the sole rendered SKU and is listed for IHC (catalog: applications). Its figure shows paraffin-embedded human tonsil carcinoma stained at 1:50 (image caption); Human, Mouse, and Rat reactivity is listed (catalog: reactivity).
Which to pick: Choose A06507 for paraffin-section tissue IHC because its own figure shows that preparation (image caption); the fixative is unreported (image caption). There is no catalog-supported IF/ICC choice: A06507 lists IHC as its application and provides no IF figure (catalog). For Mouse or Rat tissue, A06507 lists reactivity with both species (catalog), but its supplied IHC figure shows Human tissue only (image caption).