CENPM / Centromere protein M · IHC design guide

Design Immunohistochemistry for CENPM

Plan CENPM paraffin-section IHC around cytoplasmic staining mainly in immune cells (HPA tissue IHC). Bone marrow hematopoietic cells and spleen red-pulp cells show high staining and offer positive-control candidates (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
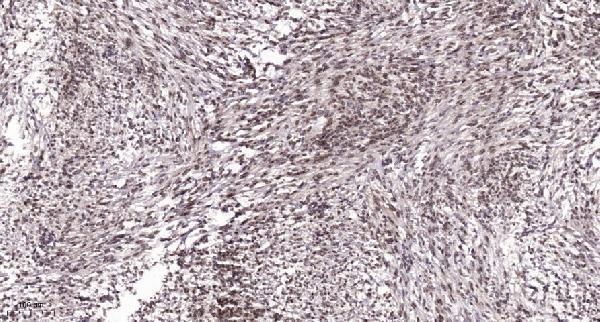
Immunohistochemistry protocol sheet for CENPM (IHC for CENPM): expected localisation Cytoplasmic in tissue immune cells (HPA tissue IHC), antibody A12987-1, validated IHC image, and IHC protocol steps
Printable CENPM IHC protocol sheet — expected localisation Cytoplasmic in tissue immune cells (HPA tissue IHC), antibody A12987-1, controls and protocol steps. Open the full CENPM IHC guide →

CENPM Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic in tissue immune cells (HPA tissue IHC)
Staining pattern Cytoplasmic staining, mainly in immune cells (HPA tissue IHC)
Antigen retrieval Tris-EDTA pH 9.0 HIER, heat-mediated (datasheet A12987-1)
Positive control ⓘ Bone marrow+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Antibody staining and RNA show medium consistency (HPA tissue IHC)
Regulation Activated CD19 B cells favor isoform 1 (UniProt)
Isoform / epitope 4 isoforms; epitope coverage is unknown (UniProt; datasheet A12987-1)
Section 1

Recommended CENPM IHC & IF Protocols

The catalog antibody’s IHC-P protocol (datasheet A12987-1) is presented alongside published CENPM staining protocols from thyroid, adrenocortical and liver tumor studies (PMC13437095; PMC11707433; PMC13615298).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human Colon cancer tissue; fixative not specified (datasheet A12987-1)
FixationImage fixative and duration unreported (datasheet A12987-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: Tris-EDTA pH 9.0 (datasheet A12987-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-CENPM, 1:50 recommended; image 1:200 (datasheet A12987-1)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultCENPM-positive staining in hematopoietic cells of bone marrow (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression, mainly in immune cells. No signal in the no-primary control.
💡Decision noteStart with heat-mediated Tris-EDTA pH 9.0 for the catalog antibody (datasheet A12987-1). For thyroid FFPE sections, citrate pH 6.0 with high-pressure heating was optimized (PMC13437095).
Section 2

What Is the Expected CENPM Staining Pattern?

In paraffin-section IHC, expect mainly cytoplasmic CENPM staining in immune cells, especially bone marrow hematopoietic cells and spleen red-pulp cells (HPA: tissue IHC). Nuclear and centromere-associated localization is also described, with cell-state-dependent distribution (UniProt Q9NSP4: subcellular location). CENPM has no transmembrane segment (UniProt Q9NSP4: topology). HPA rates the tissue staining Enhanced, while reporting only medium consistency with RNA data and staining in some unannotated structures (HPA: reliability).

What am I looking at on my slide?
Strong cytoplasmic staining in bone marrow hematopoietic cells or spleen red-pulp cells (HPA: High in both).This matches the strongest reported tissue IHC pattern (HPA: tissue IHC). Score the named cells and compartment; staining elsewhere in the section does not establish the same result.
Moderate staining in lung macrophages, lymph-node germinal-center cells, testis Sertoli cells or tonsil squamous epithelial cells (HPA: Medium in each).These are reported positive cell populations, including cells outside the predominantly immune-cell profile (HPA: tissue IHC). Interpret intensity against the specified cell type, not the tissue as a whole.
Staining appears chiefly at cell borders or in extracellular material, rather than the reported cellular compartments (HPA: cytoplasmic tissue profile; UniProt Q9NSP4: location).Treat that pattern as suspect and inspect controls and morphology. CENPM has no annotated transmembrane segment (UniProt Q9NSP4: topology); a nuclear signal alone needs care because UniProt also lists nuclear localization.
An unreported cell population stains, particularly in a region with little expected signal (HPA: tissue IHC profile).Consider nonspecific antibody binding or endogenous chromogenic detection activity; neither is established for that cell by this payload. Check whether the named HPA-positive cells stain and whether the no-primary control also develops signal.
A broad haze covers cells and tissue spaces, or bone marrow hematopoietic cells show no signal (HPA: High in bone marrow).Haze obscures compartment-based scoring; absent signal in a reported high-staining population makes the run inconclusive. Review controls and processing before interpreting a sample as CENPM-negative.
💡Expected CENPM appearanceCall a section positive when the named cells show distinct predominantly cytoplasmic staining—strong in bone marrow hematopoietic or spleen red-pulp cells (HPA: High), or moderate in the listed medium-level populations (HPA: tissue IHC); border-only or diffuse tissue-wide color is suspect (HPA: cytoplasmic profile; UniProt Q9NSP4: topology).
How each factor affects the staining
Tissue and cell selection (HPA: tissue IHC).Bone marrow hematopoietic and spleen red-pulp cells are High; lung macrophages and lymph-node germinal-center cells are Medium (HPA: tissue IHC). Select and score the annotated cells rather than treating every cell in a positive tissue as positive.
Compartment and cell state (UniProt Q9NSP4: subcellular location; HPA: tissue IHC).HPA describes mainly cytoplasmic tissue staining, while UniProt lists nucleus, cytoplasm and centromere/kinetochore, with cell-state dependence noted by similarity. A nuclear finding therefore needs context rather than automatic rejection.
Isoform expression (UniProt Q9NSP4: tissue specificity).Isoform 3 is highly expressed in spleen and resting CD19 B cells; isoform 1 is selectively expressed in activated CD19 cells (UniProt Q9NSP4). These expression statements do not identify which isoform an IHC signal detects.
Strength of tissue evidence (HPA: reliability; antibody validation).HPA reports Enhanced IHC for antibody HPA042404, but describes medium staining–RNA consistency and unannotated stained structures (HPA: reliability). Use its named cell patterns as references while reviewing unexpected staining independently.
IF/ICC applicability? (HPA: subcellular and antibody records).HPA lists no ICC validation for HPA042404, no ICC-IF images and no main subcellular location (HPA: antibody and subcellular records). UniProt locations offer a biological expectation, not an established IF staining pattern.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No chromogenic signal in bone marrow hematopoietic cells or spleen red-pulp cells (HPA: High in both).A failed staining run is possible; absence in these reported high-staining cells does not by itself show that the tested specimen lacks CENPM.Confirm that a known-positive section developed signal, then review the antibody dilution, antigen retrieval, detection reagents and counterstain using the validated IHC workflow; no target-specific retrieval condition is supplied here.
A uniform brown haze makes cellular boundaries hard to score (HPA: cytoplasmic tissue profile).Nonspecific background or detection-reagent activity can obscure the reported cell-specific pattern; the payload does not identify a CENPM-specific cause.Inspect a no-primary control, then review blocking, washes, detection exposure and counterstain as general chromogenic IHC checks. Re-score only when the named cells can be distinguished.
Adipocytes or adrenal glandular cells stain prominently (HPA: Not detected in those cells).The result conflicts with the cited HPA tissue observations; cross-reactivity or endogenous detection activity is possible, but neither is proven.Compare the same run with a reported positive tissue and a no-primary control. Record the unexpected cell type and compartment before attributing the color to CENPM.
Only membrane-edge or extracellular staining is visible (HPA: cytoplasmic tissue profile).That distribution does not fit the supplied tissue pattern or CENPM's lack of a transmembrane segment (UniProt Q9NSP4: topology).Check section morphology, background controls and whether cytoplasmic signal appears in the annotated positive cells; avoid scoring edge-only color as the expected result.
Nuclear staining appears alongside or instead of cytoplasmic color (HPA: cytoplasmic tissue profile).UniProt also lists nuclear and kinetochore localization and notes cell-state dependence by similarity (UniProt Q9NSP4: subcellular location), so compartment alone cannot settle specificity.Assess whether signal is confined to identifiable cells, compare tissue controls and report the observed compartment separately from the HPA tissue IHC pattern.
An IF/ICC image is being used to judge whether the paraffin IHC run passed (HPA: subcellular and antibody records).HPA provides no ICC-IF images or ICC validation for the listed antibody (HPA: subcellular and antibody records).Judge this IHC run against paraffin-section morphology, the HPA tissue cell patterns and its IHC controls; handle IF/ICC validation in its own guide.

Sample controls for CENPM IHC & IF

🧪Run bone marrow first and look for staining in hematopoietic cells (HPA: High in bone marrow hematopoietic cells). Use adipose tissue as the negative tissue; its adipocytes should lack specific staining (HPA: Not detected in adipose tissue adipocytes). On the bone marrow slide, cells without specific signal should show only counterstain or background; HPA does not identify a validated internal-negative marrow cell type.
Positive control tissue: Bone marrow (Hematopoietic cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA carries no ICC-IF cell line for CENPM; derive a cell-line control from the positive tissue's cell type (Hematopoietic cells) and confirm it by RNA or western blot first.
Technical controls: Include a no-primary, secondary-only control and a host-matched irrelevant IgG control: match the immunoglobulin class for a monoclonal antibody or use nonimmune IgG for a polyclonal antibody (standard IHC practice). If available, compare with CENPM-knockout material as a biological negative and block endogenous peroxidase in bone marrow before chromogenic detection (standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A12987-1 paraffin-section caption does not state the fixative (selected-SKU tissue-IHC caption). That caption uses Tris-EDTA at pH 9.0 for antigen retrieval, but does not establish that retrieval is required; no supplied evidence shows that frozen sections or IF are easier (selected-SKU tissue-IHC caption; HPA: no ICC-IF image cell lines listed). Bone marrow can have endogenous peroxidase signal, so interpret chromogenic staining against the peroxidase-blocked controls (standard IHC practice).

HPA tissue IHC evidence for CENPM

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data. Antibody staining in cells/structures not annotated, view images.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Spleen Cells in red pulp High Protein (IHC) HPA →
Lung Macrophages Medium Protein (IHC) HPA →
Lymph node Germinal center cells Medium Protein (IHC) HPA →
Testis Sertoli cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Appendix Glandular cells Not detected Protein (IHC) HPA →
Bronchus Basal cells Not detected Protein (IHC) HPA →
Cerebellum Cells in granular layer Not detected Protein (IHC) HPA →
Section 3

Advanced CENPM IHC Tips

Troubleshoot CENPM staining in paraffin sections by checking retrieval, cell identity and compartment before comparing signal intensity.

How should I retrieve CENPM antigen in paraffin sections?
Start with heat-mediated Tris-EDTA retrieval at pH 9.0 (datasheet A12987-1). The catalog antibody was used at 1:200 overnight at 4°C after this retrieval in paraffin-embedded human colon cancer (datasheet A12987-1). If staining is weak, check that the sections were fully deparaffinised and the retrieval solution reached a consistent temperature across the batch (standard IHC practice). Compare any adjusted heating time with the stated condition on adjacent sections, while monitoring tissue integrity (standard IHC practice). Interpret weak signal against a known positive cell population, since CENPM staining varies by tissue and cell type (HPA: tissue IHC).
Could fixation explain weak or uneven CENPM staining?
The selected tissue-IHC caption identifies paraffin-embedded human colon cancer but does not state its fixative (datasheet A12987-1). Target-specific fixation sensitivity is therefore unknown from the supplied evidence; neither tissue staining patterns nor CENPM topology establishes it (datasheet A12987-1; HPA: tissue IHC; UniProt Q9NSP4). Record each specimen’s fixative and fixation duration, then compare sections processed with matched retrieval and detection conditions (standard IHC practice). Check whether weak staining tracks a processing batch, tissue thickness or poor preservation before changing the primary antibody concentration (standard IHC practice). Include a positive reference section in each run to distinguish a processing problem from low expression in the specimen (standard IHC practice).
Should CENPM staining appear in nuclei or cytoplasm?
CENPM is annotated in the nucleus, cytoplasm and kinetochore domain of centromeres (UniProt Q9NSP4: subcellular location). Its reported shift toward cytoplasm in confluent or dividing cells is annotated by similarity, so do not treat that condition as proven in your section (UniProt Q9NSP4: subcellular location). Tissue IHC instead describes mainly cytoplasmic expression in immune cells (HPA: tissue IHC profile). Score nuclear and cytoplasmic chromogen separately, alongside cell identity and morphology, rather than pooling all stained pixels (standard IHC practice; HPA: tissue IHC profile). Investigate diffuse staining in unrelated cells with an antibody-omission control and a known positive reference section (standard IHC practice).
Can isoform expression explain different CENPM staining patterns?
CENPM has 4 annotated isoforms, but the supplied antibody caption does not identify its binding epitope or isoform coverage (UniProt Q9NSP4: isoforms; datasheet A12987-1). Isoform 3 is highly expressed in resting CD19 B-cells, whereas isoform 1 is selectively expressed in activated CD19 cells (UniProt Q9NSP4: tissue specificity). A difference between these populations could reflect isoform abundance, but this antibody’s staining alone cannot assign an isoform (UniProt Q9NSP4: tissue specificity; datasheet A12987-1). Request epitope mapping or isoform validation before making that assignment (standard antibody-validation practice). Meanwhile, compare cell populations using identical retrieval, dilution, detection and scoring settings (standard IHC practice).
How should I investigate CENPM by multiplex IF?
Treat IF staining as a separate optimisation, because the supplied catalog evidence describes paraffin-section chromogenic IHC rather than IF validation (datasheet A12987-1). In a section containing macrophages, pair CENPM with a spectrally distinct CD68 stain to identify a plausible positive cell population (HPA: medium staining in lung macrophages; standard IF practice). Check unstained tissue for autofluorescence and place the weaker signal in a suitably separated, longer-wavelength channel (standard IF practice). CENPM has no transmembrane segment and is annotated in intracellular compartments; choose permeabilisation appropriate to the antibody’s mapped epitope and the compartment being examined (UniProt Q9NSP4: topology and subcellular location; standard IF practice). Include single-stain controls when assessing colocalisation (standard IF practice).
How can I reduce diffuse or misleading chromogenic background?
Begin with a primary-antibody omission control and inspect staining outside intact cells, especially at section edges and damaged areas (standard IHC practice). Block endogenous peroxidase before chromogenic detection, and keep DAB development consistent across comparison sections (standard IHC practice). The selected caption used a 1:200 primary antibody overnight at 4°C and a 1:200 secondary for 45 minutes at room temperature (datasheet A12987-1). If background persists, titrate the primary antibody and review washing and blocking under matched retrieval conditions (standard IHC practice). Retain cell-specific staining as the reference: HPA describes mainly cytoplasmic expression in immune cells (HPA: tissue IHC profile).
What is a defensible way to quantify CENPM IHC? ⚠ ANSWER MARKED FOR VERIFICATION
Define the scored cell population and tissue region before measuring chromogenic signal, then keep those definitions consistent across sections (standard IHC practice). Report the percentage of positive cells and, when intensity can be scored reproducibly, an H-score based on intensity-weighted cell percentages (standard IHC practice). For dispersed positive cells, report positive-cell density per mm² of viable tissue and normalise to the area actually assessed (standard IHC practice). Separate nuclear from cytoplasmic scores because both compartments are annotated, while tissue IHC chiefly reports cytoplasmic expression in immune cells (UniProt Q9NSP4: subcellular location; HPA: tissue IHC profile). Exclude necrosis and damaged edges using the same rules for every specimen (standard IHC practice).
How do I distinguish true CENPM signal from artefact?
Assess whether staining follows intact cells in a plausible compartment: CENPM is annotated in nuclei, cytoplasm and centromeric kinetochores (UniProt Q9NSP4: subcellular location). HPA reports high staining in bone-marrow hematopoietic cells and splenic red-pulp cells, with mainly cytoplasmic tissue expression in immune cells (HPA: tissue IHC). Strong signal confined to a cut edge, necrosis or an omission-control section instead raises concern for section artefact or endogenous enzyme activity (standard IHC practice). Unexpected staining in a different cell population merits independent validation, since the tissue-IHC reliability rating reports only medium staining-to-RNA consistency (HPA: Enhanced reliability description). Interpret intensity alongside cell identity, morphology and matched controls (standard IHC practice).
Boster reagents

Best CENPM / Centromere protein M IHC Antibodies

A12987-1 has real IHC data from paraffin-embedded human colon cancer (catalog IHC caption). Human and mouse reactivity and IF use are listed, but no IF image is supplied (catalog reactivity/applications/images).

Real IHC data Immunohistochemical analysis of paraffin-embedded human Colon cancer. 1, Antibody was diluted at 1:200 (4° overnight). 2, Tris-EDTA, pH9.0 was used for antigen retrieval. 3, Secondary antibody was diluted at 1:200 (room temperature, 45min).
Anti-Centromere protein M CENPM Antibody
Cat # A12987-1

A12987-1 will render with an IHC figure from paraffin-embedded human colon cancer (catalog IHC caption). The catalog lists IHC and IF applications and human and mouse reactivity for A12987-1, but supplies no IF image (catalog applications/reactivity/images).

Which to pick: Choose A12987-1 for paraffin-section IHC: its image caption reports 1:200 primary antibody overnight at 4°C and Tris-EDTA retrieval at pH 9.0; the fixative is unreported (catalog IHC caption). For IF, A12987-1 is listed at 1:50, but no IF image or ICC application is supplied (catalog IF dilution/applications/images). For human and mouse work, A12987-1 lists both species, while its tissue image documents human colon cancer only (catalog reactivity; catalog IHC caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9NSP4 (CENPM_HUMAN, Centromere protein M).
  2. Human Protein Atlas. CENPM tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. CENPM subcellular location (ICC-IF): Highest expression in HEK293: 128.9 nTPM.
  4. Human Protein Atlas. CENPM antibody validation summary (1 antibodies).
  5. Identification of the oncogenic role of centromere protein M in non-small cell lung cancer via CDC20/MYBL2/Wnt signaling pathways. Journal of molecular histology 2025 — PMC12033124.
  6. CENPM as a biomarker and therapeutic target for lymph node metastasis in thyroid carcinoma. Frontiers in genetics 2026 — PMC13437095.
  7. Identification of CENPM as a key gene driving adrenocortical carcinoma metastasis via physical interaction with immune checkpoint ligand FGL1. Clinical and translational medicine 2025 — PMC11707433.
  8. miR-139-5p Targets CENPM to Suppress EMT and Malignant Progression of Hepatocellular Carcinoma via Regulating the Akt/mTOR Pathway and β-Catenin Nuclear Translocation. Journal of hepatocellular carcinoma 2026 — PMC13615298.
  9. PubMed PMID:16391015 — UniProt-cited evidence.
  10. PubMed PMID:12529303 — UniProt-cited evidence.
  11. PubMed PMID:14702039 — UniProt-cited evidence.