CYP4V2 / Cytochrome P450 4V2 · IHC design guide

Design Immunohistochemistry for CYP4V2

Plan paraffin section IHC with the catalog antibody’s 1:100–1:300 dilution range (datasheet A05648-1). Assess cytoplasmic hepatocyte staining while accounting for the reported low consistency between antibody staining and RNA expression (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for CYP4V2 (IHC for CYP4V2): expected localisation Cytoplasmic staining (HPA tissue IHC); ER membrane (UniProt), antibody A05648-1, validated IHC image, and IHC protocol steps
Printable CYP4V2 IHC protocol sheet — expected localisation Cytoplasmic staining (HPA tissue IHC); ER membrane (UniProt), antibody A05648-1, controls and protocol steps. Open the full CYP4V2 IHC guide →

CYP4V2 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic staining (HPA tissue IHC); ER membrane (UniProt)
Staining pattern Cytoplasmic hepatocyte staining; highest in liver (HPA tissue IHC)
Antigen retrieval Tris-EDTA pH 9.0 HIER, heat-mediated (datasheet A05648-1)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A05648-1)
Caveat Low consistency between staining and RNA expression (HPA tissue IHC)
Regulation Specific regulation unreported (UniProt)
Isoform / epitope 2 isoforms; epitope effects undetermined (UniProt)
Section 1

Recommended CYP4V2 IHC & IF Protocols

The catalog antibody’s IHC-P protocol is paired with one published CYP4V2 ocular IHC protocol (PMC9854194).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human Gastric adenocarcinoma tissue; fixative not specified (datasheet A05648-1)
FixationImage fixative and duration unreported (datasheet A05648-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: Tris-EDTA pH 9.0 (datasheet A05648-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-CYP4V2, 1:100-1:300 (datasheet A05648-1)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultCYP4V2-positive staining in glandular cells of adrenal gland (HPA tissue IHC: Medium). HPA tissue profile: Cytoplasmic expression in several different tissues, highest in the liver. No signal in the no-primary control.
💡Decision noteStart with heat-mediated Tris-EDTA pH 9.0 retrieval for the catalog antibody (datasheet A05648-1). The published formic acid retrieval used a different primary antibody (PMC9854194).
Section 2

What Is the Expected CYP4V2 Staining Pattern?

CYP4V2 is an endoplasmic reticulum membrane protein with one transmembrane segment at residues 13–33 (UniProt Q6ZWL3 topology). In tissue IHC, expect cytoplasmic staining, including in hepatocytes; HPA describes the highest tissue expression in liver (HPA tissue IHC). Treat the pattern as provisional: HPA rates the tissue antibody Approved but reports low consistency between staining and RNA expression, pending external verification (HPA tissue IHC).

What am I looking at on my slide?
Cytoplasmic chromogen in hepatocytes, with medium staining in the liver section.This matches the listed hepatocyte level and the broader cytoplasmic tissue profile (HPA tissue IHC). An endoplasmic reticulum membrane location supports a cytoplasmic appearance, but routine chromogenic IHC alone cannot prove organelle identity (UniProt Q6ZWL3 subcellular location; general IHC practice).
A predominantly nuclear or nuclear-speckle pattern replaces cytoplasmic staining in tissue IHC.Flag a compartment mismatch and investigate staining artefact or antibody specificity before scoring it as tissue IHC positivity: HPA describes cytoplasmic tissue staining, whereas UniProt places CYP4V2 at the endoplasmic reticulum membrane (HPA tissue IHC; UniProt Q6ZWL3). HPA separately reports nuclear speckles in ICC-IF, so that observation does not by itself validate nuclear tissue IHC (HPA subcellular ICC-IF).
Strong chromogen appears in adipocytes or lymph-node germinal-center cells.Those cell types are listed as not detected (HPA tissue IHC). Consider cross-reactivity or endogenous detection activity, then compare with a known-positive section and detection controls (general IHC practice). An unexpected positive is a reason to investigate; it is not proof of either cause.
A broad, poorly bounded wash of color obscures cell-to-cell differences.The result cannot establish the reported cell-specific cytoplasmic pattern (HPA tissue IHC). Review blocking, primary-antibody concentration, washing, and chromogen development as general IHC variables; use a detection-only control to assess background (general IHC practice).
No visible staining occurs in hepatocytes of a liver control section.This conflicts with the listed medium hepatocyte staining and liver-high profile (HPA tissue IHC). First check that the section and detection run worked; then review retrieval and primary-antibody conditions as general IHC practice. HPA’s low staining–RNA consistency limits how decisively one negative section can be interpreted (HPA tissue IHC).
💡Expected CYP4V2 appearanceCall a positive result when hepatocytes show discernible cytoplasmic chromogen at about the listed medium level (HPA tissue IHC); dominant nuclear-only color or strong color in HPA-listed negative cell types warrants investigation before it is called CYP4V2 (HPA tissue IHC; UniProt Q6ZWL3 subcellular location).
How each factor affects the staining
Membrane location and topologyCYP4V2 is assigned to the endoplasmic reticulum membrane and has one transmembrane segment at residues 13–33 (UniProt Q6ZWL3). Assess the reported cytoplasmic tissue pattern without claiming that a chromogenic section resolves endoplasmic reticulum membranes (HPA tissue IHC; general IHC practice).
Cell and tissue contextHPA lists medium staining in hepatocytes, cardiomyocytes, placental trophoblastic cells, and pancreatic exocrine glandular cells; lung macrophages are low, while adipocytes are not detected (HPA tissue IHC). Select and score the named cell population, not an entire organ as uniformly positive.
Strength of the tissue evidenceThe tissue profile is Approved, with low consistency between antibody staining and RNA expression and external verification pending (HPA tissue IHC). Antibody HPA029122 has IHC status Approved; no Enhanced IHC status is supplied (HPA antibodies). Treat unexpected patterns as provisional.
IF/ICC question: should nuclear speckles match tissue IHC?HPA calls nuclear speckles the main ICC-IF location, but its tissue IHC profile is cytoplasmic and HPA029122 has ICC status Uncertain (HPA subcellular ICC-IF; HPA tissue IHC; HPA antibodies). Interpret the assays separately; the ICC-IF observation does not establish the expected compartment in paraffin IHC.
Isoforms and epitope coverageUniProt lists 2 CYP4V2 isoforms and a full-length chain of residues 1–525, with no signal peptide or propeptide annotated (UniProt Q6ZWL3). The supplied record gives no antibody epitope or isoform coverage, so isoform-specific staining predictions are unsupported.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Liver control is blank in both target and comparison sections.A shared section-processing or detection failure is possible (general IHC practice); hepatocytes are expected to stain at a medium level (HPA tissue IHC).Check the run’s detection controls, section integrity, reagent sequence, and chromogen development before interpreting the CYP4V2 result (general IHC practice).
Liver control is intact, but CYP4V2 staining remains absent.Primary-antibody conditions or retrieval may be unsuitable for this run (general IHC practice); no target-specific fixation sensitivity is supplied.Review the validated IHC conditions for the antibody used and optimize retrieval or antibody concentration with a liver control (general IHC practice; HPA tissue IHC: medium hepatocytes).
Nuclei dominate the chromogenic signal in tissue sections.The result conflicts with cytoplasmic tissue IHC and the endoplasmic reticulum membrane annotation (HPA tissue IHC; UniProt Q6ZWL3); ICC-IF nuclear speckles are a separate observation (HPA subcellular ICC-IF).Inspect detection-only controls and compare the same run with hepatocyte cytoplasm before assigning CYP4V2 positivity (general IHC practice; HPA tissue IHC).
Adipocytes or lymph-node germinal-center cells stain strongly.Both are listed as not detected (HPA tissue IHC); cross-reactivity or endogenous detection activity are possibilities (general IHC practice).Compare a detection-only control and a liver positive control; address background or specificity before scoring the unexpected cells (general IHC practice; HPA tissue IHC).
Diffuse color hides the boundary between positive cells and background.Excess background can arise from blocking, antibody concentration, washing, or chromogen development (general IHC practice).Adjust those general IHC conditions one at a time and retain a liver control to check whether cytoplasmic hepatocyte staining remains visible (general IHC practice; HPA tissue IHC).
Weak staining appears in lung macrophages, with little signal elsewhere in the section.HPA lists lung macrophages as low, while its broader tissue profile has low staining–RNA consistency (HPA tissue IHC).Score the named cells and compare with a liver control rather than treating low lung signal alone as a failed assay or a validated strong positive (HPA tissue IHC; general IHC practice).

Sample controls for CYP4V2 IHC & IF

🧪Run heart muscle first; cardiomyocytes should stain (HPA: Medium in cardiomyocytes). Run adipose tissue as the negative comparator (HPA: Not detected in adipocytes); on the heart slide, assess neighboring noncardiomyocytes for background-level staining without assuming they are CYP4V2-negative.
Positive control tissue: Adrenal gland (Glandular cells, HPA Medium)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show CYP4V2 in A-431, U-251MG, U2OS, with annotated localisation: Nuclear speckles (approved) (HPA subcellular).
Technical controls: Include a no-primary (secondary-only) control, a host-species-matched isotype control for a monoclonal primary or matched normal IgG for a polyclonal primary, and knockout tissue as a biological negative. For chromogenic heart IHC, quench endogenous peroxidase and inspect the no-primary slide for tissue pigment or residual background (standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected paraffin-section caption does not state a fixative (A05648-1 caption: fixative not stated). That caption uses Tris-EDTA at pH 9.0 for retrieval and a 1:200 primary dilution overnight at 4°C; whether retrieval is required is unreported (A05648-1 caption). No matched frozen-section or IF protocol is supplied to establish which is easier; in heart muscle, evaluate pigment and endogenous peroxidase alongside the chromogenic signal (HPA: Medium in cardiomyocytes; standard IHC practice).

HPA tissue IHC evidence for CYP4V2

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells Medium Protein (IHC) HPA →
Duodenum Glandular cells Medium Protein (IHC) HPA →
Epididymis Glandular cells Medium Protein (IHC) HPA →
Gallbladder Glandular cells Medium Protein (IHC) HPA →
Heart muscle Cardiomyocytes Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Caudate Glial cells Not detected Protein (IHC) HPA →
Cerebellum Cells in granular layer Not detected Protein (IHC) HPA →
Cervix Glandular cells Not detected Protein (IHC) HPA →
Colon Endothelial cells Not detected Protein (IHC) HPA →
Section 3

Advanced CYP4V2 IHC Tips

Troubleshoot CYP4V2 staining in paraffin sections by checking retrieval, cellular pattern and controls before interpreting chromogenic signal.

What retrieval should I try first when CYP4V2 staining is weak?
Start with heat-mediated retrieval in Tris-EDTA at pH 9.0 (datasheet A05648-1). The selected paraffin-section image used that buffer with the catalog antibody at 1:200 overnight at 4°C, but reports no heating time (datasheet A05648-1). Keep the heating and cooling conditions consistent across comparison sections, and include a liver control showing hepatocyte staining (HPA: medium in hepatocytes; standard IHC practice). If signal remains weak, compare a milder retrieval condition on adjacent sections while holding antibody concentration and detection constant (standard IHC practice). Excess retrieval can damage morphology or raise background, so assess staining alongside intact tissue architecture (standard IHC practice).
Could fixation explain weak or uneven CYP4V2 staining?
The selected image identifies paraffin-embedded human gastric adenocarcinoma but does not state its fixative or fixation duration (datasheet A05648-1). Target-specific fixation sensitivity is therefore unknown; neither tissue staining patterns nor CYP4V2 membrane topology establish a preferred fixation condition (datasheet A05648-1; UniProt Q6ZWL3 topology). For weak sections, record the actual fixative, fixation interval and processing history, then compare similarly processed control tissue in the same run (standard IHC practice). Check whether uneven staining follows tissue thickness or poorly preserved regions before changing antibody concentration (standard IHC practice). Keep retrieval at Tris-EDTA pH 9.0 during that comparison so fixation remains the main variable (datasheet A05648-1; standard IHC practice).
Which cellular pattern should count as plausible CYP4V2 staining?
Expect a mainly cytoplasmic chromogenic pattern in tissue, consistent with the reported tissue profile and endoplasmic reticulum membrane annotation (HPA: cytoplasmic expression; UniProt Q6ZWL3 subcellular location). CYP4V2 has one membrane-spanning segment at residues 13–33, so diffuse nuclear DAB alone deserves scrutiny (UniProt Q6ZWL3 topology; standard IHC interpretation). HPA separately reports nuclear speckles in cultured-cell IF images, which creates a method-dependent localisation discrepancy requiring orthogonal validation (HPA: nuclear speckles approved; HPA: tissue IHC profile). Compare the compartment in hepatocytes and the specimen of interest under identical detection conditions (HPA: medium in hepatocytes; standard IHC practice). Score cytoplasmic and nuclear signal separately rather than combining them into one positive call (standard IHC practice).
How can epitope uncertainty affect CYP4V2 IHC interpretation?
CYP4V2 has 2 annotated isoforms, while the supplied product caption gives no epitope sequence or isoform coverage (UniProt Q6ZWL3 isoforms; datasheet A05648-1). Its membrane-spanning segment lies at residues 13–33, but that topology does not identify which side contains this antibody’s epitope (UniProt Q6ZWL3 topology; datasheet A05648-1). Check the antibody’s documented immunogen or epitope before claiming that staining represents both isoforms or selecting an epitope-specific permeabilisation strategy (standard IHC practice). The record lists no glycosylation sites or modified residues; this does not establish that processing cannot affect staining (UniProt Q6ZWL3 PTMs; standard IHC interpretation). Report results as catalog-antibody staining until isoform recognition is independently established (standard IHC practice).
How should I investigate CYP4V2 localisation with a separate IF assay?
Use IF as an independent localisation check; this page’s selected antibody image documents paraffin-section IHC, not an IF condition (datasheet A05648-1). Multiplex CYP4V2 with a validated hepatocyte marker when examining liver, where hepatocytes show medium tissue staining (HPA: medium in hepatocytes; standard IF practice). Choose fluorophores after checking tissue autofluorescence and include single-stain controls to assess spectral spillover (standard IF practice). CYP4V2 spans the endoplasmic reticulum membrane at residues 13–33; choose permeabilisation only after establishing which membrane side carries the antibody epitope (UniProt Q6ZWL3 topology; standard IF practice). Interpret nuclear speckles cautiously because cultured-cell IF and tissue IHC report different dominant compartments (HPA: nuclear speckles approved; HPA: cytoplasmic tissue expression).
How do I reduce diffuse DAB or tissue-associated background?
Run a no-primary control to reveal secondary-reagent, endogenous-enzyme or substrate background before adjusting CYP4V2 staining (standard IHC practice). Include an appropriate peroxidase block for chromogenic detection, then assess whether DAB develops in the no-primary section (standard IHC practice). The selected caption specifies primary antibody at 1:200 overnight at 4°C and secondary antibody at 1:200 for 45 minutes at room temperature (datasheet A05648-1). If background persists, titrate the primary antibody, optimise blocking and washes, and limit chromogen development while preserving the same retrieval condition (standard IHC practice). Compare background with cellular cytoplasmic signal in a liver control, rather than treating all brown deposits as CYP4V2 (HPA: cytoplasmic tissue expression; standard IHC practice).
What is a defensible way to quantify CYP4V2 staining across sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring; tissue IHC describes mainly cytoplasmic CYP4V2 staining (HPA: cytoplasmic expression; standard IHC practice). For a defined population, record the percentage of positive cells and staining intensity, then calculate an H-score from the fractions at each intensity (standard IHC practice). Alternatively, report positive-cell density per mm² of viable tissue when cell counts per field vary (standard IHC practice). Normalise comparisons to eligible cells or viable tissue area, and keep retrieval, imaging and DAB development consistent across sections (standard IHC practice). Report nuclear staining separately and avoid equating DAB intensity with CYP4V2 enzyme activity (HPA: nuclear speckles in IF; standard IHC interpretation).
How can I distinguish convincing CYP4V2 signal from artefact?
A convincing tissue-IHC result shows cellular cytoplasmic staining in an appropriate population and survives comparison with a no-primary control (HPA: cytoplasmic tissue expression; standard IHC practice). Hepatocytes provide a supported positive comparator, whereas HPA reports adipocytes as not detected in its tissue IHC survey (HPA: medium in hepatocytes; HPA: adipocytes not detected). Treat isolated nuclear DAB cautiously because the tissue profile is cytoplasmic, although cultured-cell IF reports nuclear speckles (HPA: tissue IHC profile; HPA: nuclear speckles approved). Exclude edge staining, necrotic regions and signal reproduced by the no-primary control, including endogenous peroxidase activity (standard IHC practice). HPA rates the tissue staining Approved but notes low agreement with RNA and pending external verification, so corroborate consequential findings independently (HPA: reliability description).
Boster reagents

Best CYP4V2 / Cytochrome P450 4V2 IHC Antibodies

A05648-1 has a real IHC image from a human paraffin section and is listed for IF and for Human, Mouse, and Rat reactivity (catalog; IHC image caption).

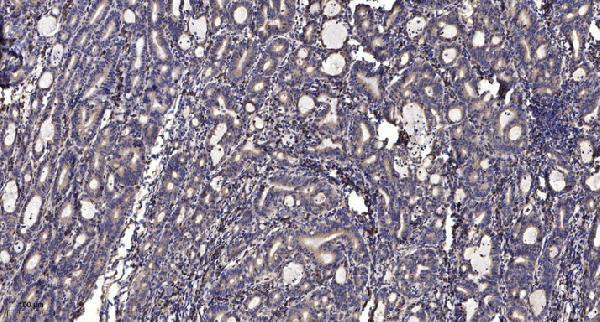
Real IHC data Immunohistochemical analysis of paraffin-embedded human Gastric adenocarcinoma. 1, Antibody was diluted at 1:200 (4° overnight). 2, Tris-EDTA, pH9.0 was used for antigen retrieval. 3, Secondary antibody was diluted at 1:200 (room temperature, 45min).
Anti-Cytochrome P450 4V2 CYP4V2 Antibody
Cat # A05648-1

A05648-1 will render with an IHC image of paraffin-embedded human gastric adenocarcinoma (IHC image caption). It is listed for IHC and IF in Human, Mouse, and Rat, but no IF image is supplied (catalog).

Which to pick: Choose A05648-1 for tissue IHC: its image shows a paraffin-embedded human gastric adenocarcinoma section, with the primary antibody at 1:200 after Tris-EDTA retrieval at pH 9.0; the fixative is unreported (IHC image caption). For IF, A05648-1 is listed at 1:50, but no IF image or ICC validation is supplied (catalog). For Mouse or Rat samples, A05648-1 is listed as reactive and is a rabbit polyclonal antibody, while its supplied IHC image documents Human tissue only (catalog; IHC image caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q6ZWL3 (CP4V2_HUMAN, Cytochrome P450 4V2).
  2. Human Protein Atlas. CYP4V2 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. CYP4V2 subcellular location (ICC-IF): Mainly localized to the nuclear speckles..
  4. Human Protein Atlas. CYP4V2 antibody validation summary (1 antibodies).
  5. A patient advocating for transparent science in rare disease research. Orphanet journal of rare diseases 2023 — PMC9854194.
  6. AAV2-mediated gene therapy for Bietti crystalline dystrophy provides functional CYP4V2 in multiple relevant cell models. Scientific reports 2022 — PMC9184470.
  7. The differential expression of omega-3 and omega-6 fatty acid metabolising enzymes in colorectal cancer and its prognostic significance. British journal of cancer 2017 — PMC5518862.
  8. Ocular cytochrome P450s and transporters: roles in disease and endobiotic and xenobiotic disposition. Drug metabolism reviews 2014 — PMC4676416.
  9. PubMed PMID:15042513 — UniProt-cited evidence.
  10. PubMed PMID:14702039 — UniProt-cited evidence.
  11. PubMed PMID:15815621 — UniProt-cited evidence.