EIF3E / Eukaryotic translation initiation factor 3 subunit E · IHC design guide

Design Immunohistochemistry for EIF3E

Plan EIF3E paraffin IHC around cytoplasmic and nuclear staining (HPA tissue IHC). Use high-staining tonsil germinal center cells and unstained skeletal myocytes as tissue references (HPA tissue IHC); the catalog antibody was used at 2 μg/ml in paraffin sections (datasheet A00481-4).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for EIF3E (IHC for EIF3E): expected localisation Cytoplasmic and nuclear tissue staining (HPA tissue IHC), antibody A00481-4, validated IHC image, and IHC protocol steps
Printable EIF3E IHC protocol sheet — expected localisation Cytoplasmic and nuclear tissue staining (HPA tissue IHC), antibody A00481-4, controls and protocol steps. Open the full EIF3E IHC guide →

EIF3E Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic and nuclear tissue staining (HPA tissue IHC)
Staining pattern General cytoplasmic and nuclear staining across cell types (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A00481-4)
Positive control ⓘ Cerebral cortex+4 more · see all
Negative control ⓘ Adipose tissue+2 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Skeletal myocytes lack detectable staining despite broad expression (HPA tissue IHC; UniProt)
Regulation Broad tissue expression (UniProt)
Isoform / epitope No annotated isoforms; chain spans residues 2–445 (UniProt)
Section 1

Recommended EIF3E IHC & IF Protocols

The catalog antibody’s IHC-P protocol (datasheet: A00481-4) accompanies published protocols for glioblastoma tissue (PMC8210094) and rat hind-limb tissue plus clinical samples (PMC9117278).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human appendiceal adenocarcinoma tissue; fixative not specified (datasheet A00481-4)
FixationImage fixative and duration unreported (datasheet A00481-4); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A00481-4); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A00481-4)
Primary antibodyRabbit anti-EIF3E, 2-5 μg/ml (datasheet A00481-4)
Primary incubationOvernight at 4 °C (datasheet A00481-4)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A00481-4)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultEIF3E-positive staining in neuronal cells of cerebral cortex (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic and nuclear expression. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet: A00481-4). The glioblastoma protocol uses Tris–EDTA pH 9 (PMC8210094).
Section 2

What Is the Expected EIF3E Staining Pattern?

EIF3E staining in paraffin sections is expected in cytoplasm and nuclei across many cell types (HPA tissue IHC: general cytoplasmic and nuclear expression; UniProt P60228: cytoplasm and nucleus). Strong examples include neuronal, squamous epithelial, germinal center, and trophoblastic cells (HPA tissue IHC: High). HPA rates its tissue IHC profile Approved, with medium consistency between antibody staining and RNA expression (HPA tissue IHC: reliability description). EIF3E has no transmembrane segment (UniProt P60228: topology).

What am I looking at on my slide?
Cytoplasmic staining, with or without visible nuclear staining, in neuronal cells of cerebral cortex or germinal center cells of lymph node.This fits the reported compartments and cell types (HPA tissue IHC: general cytoplasmic and nuclear expression; High in both cell types). Compare cells within the same section: HPA levels describe observed patterns, not a required intensity for every specimen (HPA tissue IHC: tissue profile).
A crisp plasma membrane rim or extracellular deposit dominates while cytoplasmic staining is absent.That distribution is unexpected for EIF3E (UniProt P60228: cytoplasm, nucleus; no transmembrane segment). Treat it as a possible staining artefact and check tissue morphology and controls before assigning target-specific signal (standard IHC practice). Nuclear staining alone does not meet this wrong-compartment criterion (UniProt P60228: nucleus).
Strong staining appears in adipocytes or skeletal muscle myocytes, including in areas without clearly stained nucleated cells.HPA reports EIF3E as Not detected in these cells by tissue IHC (HPA tissue IHC: adipocytes and skeletal muscle myocytes). Consider cross-reactivity or endogenous chromogen activity, then inspect a reagent control (standard IHC practice). Skeletal muscle requires caution: UniProt describes high tissue expression there (UniProt P60228: tissue specificity).
A diffuse haze covers cells and cell-free areas, obscuring compartment boundaries.This cannot establish EIF3E localisation because the expected tissue profile is cellular cytoplasmic and nuclear staining (HPA tissue IHC: profile). In chromogenic IHC, nonspecific reagent binding or incomplete control of endogenous detection activity can cause background; compare a primary-omission control and revisit blocking and detection conditions (standard IHC practice).
No staining is visible in a nominated positive tissue, including its expected positive cells.First confirm that the relevant cells are present: HPA reports High staining in cerebral cortex neuronal cells, esophageal squamous epithelial cells, lymph node and tonsil germinal center cells, and placental trophoblastic cells (HPA tissue IHC: positive cells). An absent result warrants checking the assay and tissue condition; it does not alone establish biological loss (standard IHC practice).
💡Expected EIF3E appearanceA credible positive result shows predominantly cellular cytoplasmic staining, potentially with nuclear staining, in HPA High cell populations; prominent membrane or extracellular signal is suspect (HPA tissue IHC: profile and High cell populations; UniProt P60228: topology).
How each factor affects the staining
Compartment and topologyEIF3E is assigned to cytoplasm and nucleus, including PML bodies, and has no transmembrane segment or signal peptide (UniProt P60228: subcellular location, topology, processing). These annotations support a cellular interpretation; they do not require visible PML-body puncta in every paraffin section (standard IHC interpretation).
Tissue and cell contextHPA reports High staining in selected cell populations, Medium in several glandular populations, Low in hepatocytes and cardiomyocytes, and Not detected in adipocytes or myocytes (HPA tissue IHC: listed levels). Score the named cell population rather than assigning one intensity to the whole tissue (standard IHC practice).
Evidence limitsThe HPA tissue IHC profile is Approved with medium agreement between staining and RNA data; the listed antibody HPA023973 has IHC Approved status (HPA tissue IHC: reliability; HPA antibodies: HPA023973). UniProt calls expression ubiquitous and highest in skeletal muscle, whereas HPA reports myocytes Not detected by IHC (UniProt P60228: tissue specificity; HPA tissue IHC: skeletal muscle).
IF/ICC Q: What pattern should be expected?A: HPA reports supported cytosolic localisation in ICC-IF and lists A-431 and U2OS image sets (HPA subcellular: Cytosol supported; HPA antibodies: ICC Supported). UniProt also lists nucleus and PML body, while the HPA tissue IHC profile includes nuclear staining (UniProt P60228: subcellular location; HPA tissue IHC: profile). Interpret each assay in its own context.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
High-reference cells stain weakly or remain blank.The expected cells may be absent from the sampled area, or an IHC step may have underperformed (standard IHC practice). HPA identifies neuronal, squamous epithelial, germinal center, and trophoblastic cells as High (HPA tissue IHC: positive cells).Confirm cell identity and morphology, then review the catalog antibody's IHC-P instructions and check retrieval, primary dilution, and detection controls (standard IHC practice). Do not infer an EIF3E-specific retrieval requirement from the HPA pattern.
Signal forms a sharp membrane outline instead of a cellular cytoplasmic pattern.A membrane-dominant pattern conflicts with EIF3E's reported cytoplasmic and nuclear localisation and lack of a transmembrane segment (UniProt P60228: subcellular location, topology). Nonspecific detection is a possibility (standard IHC practice).Compare a known positive cell population and a primary-omission control; review blocking and detection conditions before scoring the rim as EIF3E (standard IHC practice; HPA tissue IHC: positive cells).
Adipocytes or skeletal muscle myocytes appear strongly positive.HPA records these cells as Not detected by IHC, though UniProt reports high EIF3E expression in skeletal muscle tissue (HPA tissue IHC: negative cells; UniProt P60228: tissue specificity). Staining alone cannot resolve that discrepancy.Inspect staining within identified cells, compare a primary-omission control, and report the HPA–UniProt disagreement when interpreting myocytes (standard IHC practice; HPA tissue IHC: skeletal muscle; UniProt P60228: tissue specificity).
Brown haze obscures cells and also covers empty spaces.Diffuse chromogen can reflect background from nonspecific reagents or endogenous detection activity (standard chromogenic IHC practice); it does not match HPA's cellular localisation profile (HPA tissue IHC: profile).Use a primary-omission control, check endogenous activity blocking appropriate to the detection chemistry, and review wash and chromogen steps (standard IHC practice). Judge target staining only where cell boundaries and compartments remain interpretable.
Only nuclei stain strongly, with little discernible cytoplasm.Nuclear EIF3E is plausible (UniProt P60228: nucleus; HPA tissue IHC: nuclear expression), but the overall HPA tissue profile also includes cytoplasmic staining (HPA tissue IHC: profile). Counterstain or background may make weak cytoplasm hard to judge (standard IHC practice).Compare positive cells across the section and inspect a primary-omission control; assess cytoplasmic signal separately from counterstain before calling a nuclear-only pattern (standard IHC practice).
Staining varies sharply between regions of the same section.Different cell populations have different HPA staining levels (HPA tissue IHC: High, Medium, Low, and Not detected entries). An uneven technical result is also possible when morphology or controls vary (standard IHC practice).Identify and score the cell types in each region, then examine tissue preservation and control staining across the slide (standard IHC practice). Avoid assigning a whole-section positive or negative call from a single region.

Sample controls for EIF3E IHC & IF

🧪Run esophagus first; squamous epithelial cells should stain (HPA: High in esophageal squamous epithelial cells). Use adipose tissue as the negative, where adipocytes are not detected (HPA: Not detected in adipocytes); no internal negative cell type is established for the esophagus slide, so unstained cells should show only background and should not be treated as validated negatives (HPA: esophagus row).
Positive control tissue: Cerebral cortex (Neuronal cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show EIF3E in A-431, U2OS, with annotated localisation: Cytosol (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control, matched rabbit isotype or nonimmune IgG matched to the primary’s clonality when known, and EIF3E knockout material or peptide competition if available (caption: rabbit primary; clonality unreported; standard IHC practice). Quench endogenous peroxidase and check endogenous biotin background in esophageal sections used with the biotin-based detection system (caption: SABC/DAB; HPA: esophagus High).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the exact A00481-4 paraffin-section caption does not state a fixative (caption: fixative unreported). Heat retrieval in EDTA at pH 8.0 was used, but a requirement for retrieval was not established (caption: EDTA retrieval). Frozen-section suitability and whether IF/ICC is easier are unreported; ICC-IF images show supported cytosolic localization in A-431 and U2OS (HPA: Cytosol supported; A-431 and U2OS).

HPA tissue IHC evidence for EIF3E

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Cerebral cortex Neuronal cells High Protein (IHC) HPA →
Esophagus Squamous epithelial cells High Protein (IHC) HPA →
Lymph node Germinal center cells High Protein (IHC) HPA →
Placenta Trophoblastic cells High Protein (IHC) HPA →
Stomach Glandular cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Skeletal muscle Myocytes Not detected Protein (IHC) HPA →
Smooth muscle Smooth muscle cells Not detected Protein (IHC) HPA →
Section 3

Advanced EIF3E IHC Tips

Troubleshoot EIF3E staining in paraffin sections by checking retrieval, compartment, cell type and controls before comparing staining intensity across samples.

What retrieval should I try first for weak EIF3E staining in paraffin sections?
Start with heat-mediated retrieval in EDTA at pH 8.0 (datasheet A00481-4). The documented paraffin-section example used this retrieval before staining with 2 μg/ml antibody overnight at 4°C (caption A00481-4). If signal is weak, compare a retrieval run with the same buffer against your current run while keeping antibody concentration, detection and development conditions matched (standard IHC practice). Check a positive control alongside the specimen: HPA reports high staining in lymph-node germinal center cells, although its tissue-IHC reliability is Approved with medium consistency against RNA expression (HPA tissue IHC). Record tissue damage as well as signal, since excessive heat can reduce interpretable morphology (standard IHC practice).
Could fixation explain variable EIF3E staining between paraffin blocks?
Target-specific EIF3E sensitivity to fixation is unknown from the supplied evidence (caption A00481-4). The documented section was paraffin embedded, but its fixative was not stated; do not assign it a formalin fixation condition (caption A00481-4). Compare blocks using matched section thickness, retrieval, 2 μg/ml primary antibody and overnight incubation at 4°C where the documented procedure is applicable (caption A00481-4; standard IHC practice). Include a consistently processed positive-control section in each run, then compare staining and preserved morphology before attributing differences to fixation (standard IHC practice). Record each block's known fixation history separately so that an observed association can be tested rather than assumed (standard IHC practice).
How should I assess cytoplasmic versus nuclear EIF3E staining?
Assess cytoplasmic and nuclear staining separately: HPA describes general expression in both compartments, while UniProt lists cytoplasm and nucleus, including PML bodies (HPA tissue IHC; UniProt P60228 localisation). HPA subcellular imaging supports cytosolic localisation, so a predominantly cytosolic pattern is plausible (HPA subcellular). Use a counterstain and review cell boundaries at higher magnification before calling faint nuclear chromogen positive (standard IHC practice). Compare the pattern with a positive-control cell population, such as lymph-node germinal center cells with high HPA staining (HPA tissue IHC). Diffuse staining over stroma, empty spaces or section edges warrants a background check before compartment scoring (standard IHC practice).
Could epitope placement or modification alter the IHC pattern?
The supplied record lists 0 isoforms but does not map the catalog antibody's epitope, so an isoform-specific interpretation is unsupported (UniProt P60228 isoforms; caption A00481-4). EIF3E has a PCI domain at residues 221–398 and reported modified residues including phosphoserine 399 and phosphotyrosine 445 (UniProt P60228 domains and modified residues). Without epitope mapping, do not attribute weak paraffin-section staining to masking of a particular modified residue (UniProt P60228 modified residues; standard IHC practice). First compare retrieval and detection controls across matched sections, then seek antibody epitope information if the discrepancy persists (standard IHC practice). Interpret nuclear and cytoplasmic signals against their documented localisation rather than an assumed terminal epitope (UniProt P60228 localisation; standard IHC practice).
How can IF help investigate an uncertain EIF3E IHC pattern?
Use IF as a separate localisation check and multiplex EIF3E with a marker identifying the expected cell population, such as germinal center cells in lymph node (HPA tissue IHC; standard IF practice). HPA subcellular imaging supports cytosolic EIF3E and lists A-431 and U2OS as imaged cell lines (HPA subcellular). Because EIF3E has no transmembrane segment, permeabilise cells to assess cytosolic signal, and verify nuclear access if evaluating its reported nuclear localisation (UniProt P60228 topology and localisation; standard IF practice). Choose a far-red fluorophore when tissue autofluorescence interferes with shorter-wavelength channels, and inspect single-channel and no-primary controls (standard IF practice). Keep IF intensity separate from chromogenic IHC scores because detection and background differ between methods (standard IHC/IF practice).
What should I check when EIF3E DAB staining looks diffuse?
Start with a no-primary control and inspect whether color follows tissue edges, folds, damaged areas or the expected cells (standard IHC practice). In the documented paraffin-section procedure, blocking used 10% goat serum, followed by 2 μg/ml primary antibody overnight at 4°C (caption A00481-4). Its biotinylated secondary, streptavidin–biotin detection and DAB development make secondary-only and detection-reagent controls useful when background persists (caption A00481-4; standard IHC practice). Block endogenous peroxidase and assess endogenous biotin where relevant to this detection system (standard IHC practice). Compare the residual pattern with HPA's general cytoplasmic and nuclear expression; widespread chromogen outside identifiable cells should not be scored as EIF3E (HPA tissue IHC; standard IHC practice).
How should I quantify EIF3E staining across sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, because EIF3E can show cytoplasmic and nuclear staining (HPA tissue IHC; UniProt P60228 localisation). For chromogenic sections, record the percentage of positive cells and staining intensity, then calculate an H-score when intensity categories are reproducible (standard IHC practice). Normalise positive-cell counts to the number of eligible cells, or report positive-cell density per mm² of viable analysed tissue when counting spatial regions (standard IHC practice). Keep counterstain, illumination, DAB development and analysis thresholds consistent across the comparison (standard IHC practice). Exclude folds, edges and necrotic regions, and report cytoplasmic and nuclear scores separately rather than pooling unlike patterns (standard IHC practice).
How do I distinguish genuine EIF3E positivity from staining artefacts?
A plausible positive signal occupies identifiable cells and fits EIF3E's documented cytoplasmic or nuclear distribution (HPA tissue IHC; UniProt P60228 localisation). High HPA staining in lymph-node germinal center cells offers a reference population, whereas HPA reports EIF3E as not detected in skeletal-muscle myocytes (HPA tissue IHC). Treat staining concentrated at section edges, necrotic areas or acellular deposits as suspect, and compare no-primary and endogenous-peroxidase controls before interpreting DAB (standard IHC practice). An unexpected compartment or cell population calls for review of morphology, retrieval and detection controls before biological interpretation (standard IHC practice). HPA rates its tissue-IHC evidence Approved with medium consistency against RNA expression, so agreement across controls matters for a strong conclusion (HPA tissue IHC).
Boster reagents

Best EIF3E / Eukaryotic translation initiation factor 3 subunit E IHC Antibodies

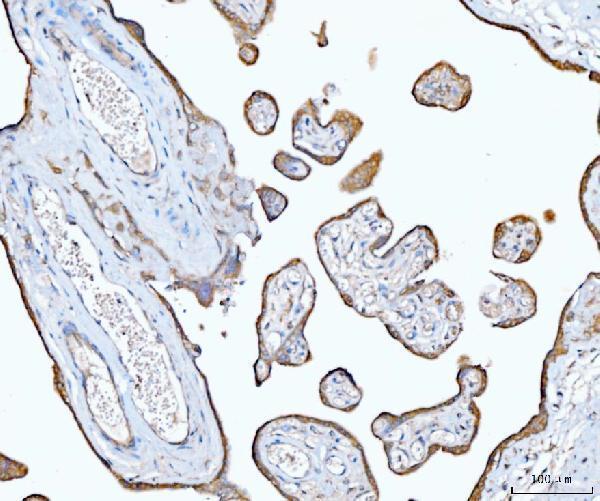
Anti-EIF3E antibodies include real IHC images from human paraffin sections of appendiceal adenocarcinoma, placenta and spleen (A00481-4 image captions); an IF/ICC antibody lists Human, Mouse and Rat reactivity (M00481 catalog).

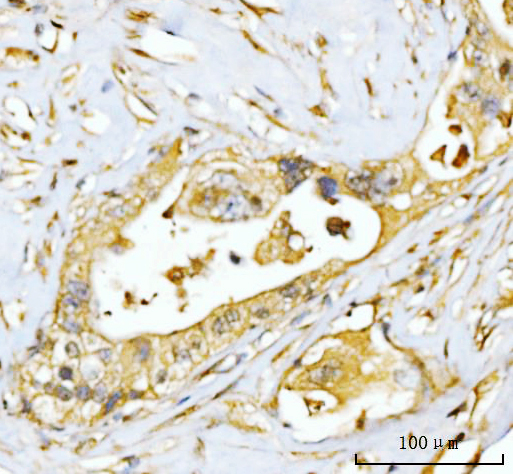
Real IHC data IHC analysis of EIF3E using anti-EIF3E antibody (A00481-4). EIF3E was detected in a paraffin-embedded section of human appendiceal adenocarcinoma tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-EIF3E Antibody (A00481-4) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-EIF3E Antibody ®
Cat # A00481-4

The rendered card is A00481-4, showing IHC staining of a human appendiceal adenocarcinoma paraffin section (A00481-4 figure caption). Additional captions document human placenta and spleen paraffin sections, with EDTA retrieval at pH 8.0 and a primary concentration of 2 μg/ml (A00481-4 image captions).

Which to pick: Choose A00481-4 for human paraffin-section IHC because its own captions document staining in those sections; the fixative is unreported (A00481-4 image captions). For IF/ICC, choose rabbit monoclonal M00481, clone 25E15; its catalog lists Human, Mouse and Rat reactivity but supplies no IF image (M00481 catalog). For broader listed species reactivity, A00481-1 includes Human, Mouse and Rat, although its paraffin-section IHC testing is specified for Human only (A00481-1 catalog).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P60228 (EIF3E_HUMAN, Eukaryotic translation initiation factor 3 subunit E).
  2. Human Protein Atlas. EIF3E tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. EIF3E subcellular location (ICC-IF): Localized to the cytosol..
  4. Human Protein Atlas. EIF3E antibody validation summary (1 antibodies).
  5. Translation reprogramming by eIF3 linked to glioblastoma resistance. NAR cancer 2020 — PMC8210094.
  6. Comparative proteomic analysis identifies differentially expressed proteins and reveals potential mechanisms of traumatic heterotopic ossification progression. Journal of orthopaedic translation 2022 — PMC9117278.
  7. Up-regulation Of EIF3e Is Associated with The Progression of Esophageal Squamous Cell Carcinoma and Poor Prognosis in Patients. Journal of Cancer 2018 — PMC5907661.
  8. Int6/eIF3e Silencing Promotes Placenta Angiogenesis in a Rat Model of Pre-eclampsia. Scientific reports 2018 — PMC5997673.
  9. PubMed PMID:9295280 — UniProt-cited evidence.
  10. PubMed PMID:9403073 — UniProt-cited evidence.
  11. PubMed PMID:8688078 — UniProt-cited evidence.