GNL3 / Guanine nucleotide-binding protein-like 3 · IHC design guide

Design Immunohistochemistry for GNL3

Plan paraffin-section GNL3 staining around the nucleolar tissue pattern (HPA tissue IHC). The catalog antibody A03283-3 has an IHC dilution of 2–5 μg/ml; compare staining intensity by cell type (datasheet A03283-3; HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for GNL3 (IHC for GNL3): expected localisation Nucleolar staining in tissue sections (HPA tissue IHC), antibody A03283-3, validated IHC image, and IHC protocol steps
Printable GNL3 IHC protocol sheet — expected localisation Nucleolar staining in tissue sections (HPA tissue IHC), antibody A03283-3, controls and protocol steps. Open the full GNL3 IHC guide →

GNL3 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nucleolar staining in tissue sections (HPA tissue IHC)
Staining pattern Nucleolar signal across tissues, including glandular cells (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A03283-3)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ None in HPA (detected in all 45 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Glomerular cells and adipocytes show low staining (HPA tissue IHC)
Regulation Higher lung levels in cancer patients (UniProt)
Isoform / epitope 2 isoforms; epitope coverage is unspecified (UniProt; datasheet A03283-3)
Section 1

Recommended GNL3 IHC & IF Protocols

The catalog antibody protocol uses EDTA pH 8.0 heat retrieval (datasheet A03283-3). The published option below reports GNL3 staining in colon cancer tissue sections (PMC5652940).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human appendiceal adenocarcinoma tissue; fixative not specified (datasheet A03283-3)
FixationImage fixative and duration unreported (datasheet A03283-3); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A03283-3); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A03283-3)
Primary antibodyRabbit anti-GNL3, 2-5 μg/ml (datasheet A03283-3)
Primary incubationOvernight at 4 °C (datasheet A03283-3)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A03283-3)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultGNL3-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Nucleolar expression in all tissues. No signal in the no-primary control.
💡Decision noteStart with EDTA pH 8.0 heat retrieval (datasheet A03283-3). The published protocol specifies 95°C for 15 min but does not identify a retrieval buffer (PMC5652940).
Section 2

What Is the Expected GNL3 Staining Pattern?

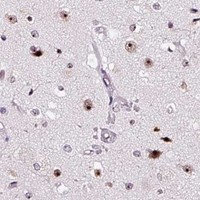
GNL3 should stain within nuclei, chiefly at nucleoli: HPA reports nucleolar expression across tissues, while UniProt places GNL3 in the nucleus and nucleolus and describes shuttling between them (HPA: tissue IHC; UniProt Q9BVP2: subcellular location). Strong examples include glandular, squamous epithelial, and Purkinje cells (HPA: High). The tissue IHC profile has Enhanced reliability, reflecting consistency between staining and RNA expression (HPA: tissue IHC). GNL3 has no transmembrane segment (UniProt Q9BVP2: topology).

What am I looking at on my slide?
Distinct nuclear puncta in glandular cells, including colon or breast; surrounding cytoplasm is comparatively clear.This fits the reported nucleolar tissue pattern and High staining in those cell types (HPA: tissue IHC). Chromogenic IHC may show nucleolar dots without resolving the finer nucleolar rim seen by ICC-IF (HPA: subcellular ICC-IF; general IHC practice).
Predominantly cytoplasmic or membranous staining, with little nuclear signal.Treat this as a compartment mismatch and investigate artefact before scoring it as GNL3 (UniProt Q9BVP2: nuclear/nucleolar location; HPA: nucleolar tissue IHC). A membrane pattern is especially discordant with the absence of a transmembrane segment (UniProt Q9BVP2: topology).
Strong staining appears mainly in a cell population outside the reported High examples, while expected nucleolar cells remain faint.Consider antibody cross-reactivity or endogenous detection activity (general IHC practice). Cell identity alone does not prove a false positive: HPA describes nucleolar expression across tissues, and its selected High examples are not an exclusive cell list (HPA: tissue IHC).
Broad, hazy color covers nuclei, cytoplasm, and surrounding tissue without distinct nucleolar contrast.Diffuse background cannot establish GNL3 localisation. Review blocking, washes, chromogen development, and the no-primary control (general IHC practice); compare any remaining cellular signal with the nucleolar pattern reported for tissue IHC (HPA: tissue IHC).
No visible nuclear signal in a documented High example, such as colon glandular cells or cerebellar Purkinje cells.First suspect a technical loss of detectable signal, then review the sample and antibody setup (general IHC practice). HPA reports these cells as High, but staining in one section is not a guaranteed intensity standard (HPA: tissue IHC).
💡Expected GNL3 appearanceCall a slide positive when appropriately identified cells show distinct nucleolar chromogenic staining, especially in HPA High cell types; diffuse cytoplasmic or membrane color without nuclear contrast is suspect (HPA: tissue IHC; UniProt Q9BVP2: location and topology; general IHC practice).
How each factor affects the staining
Subnuclear localisationUniProt reports movement between nucleus and nucleolus; HPA ICC-IF places the main signal at the nucleolar rim, with supported nuclear-body and mitotic-chromosome signals (UniProt Q9BVP2: subcellular location; HPA: subcellular ICC-IF). These finer IF findings should not be required as separately resolved features in chromogenic tissue IHC (general IHC practice).
Tissue contrastHPA rates adipocytes, glomerular cells, and splenic red-pulp cells Low, while several glandular and squamous populations are High (HPA: tissue IHC). Low is not negative: assess contrast against a documented High population and its nucleolar pattern rather than treating a Low population as a blank control (HPA: tissue IHC).
Antibody evidenceHPA036742 and HPA036743 are IHC Enhanced; CAB020770 is IHC Supported (HPA: antibodies). These validation labels support the reported pattern but do not guarantee that every staining run or specimen will reproduce it (HPA: antibodies; general IHC practice).
Detection backgroundEndogenous tissue activity can generate chromogenic color independently of primary-antibody binding (general IHC practice). Use an appropriate no-primary control and the detection system's background controls when widespread color obscures subnuclear detail (general IHC practice).
IF/ICC Q: What localisation can be expected?A: Predominantly nucleolar-rim signal, with additional nuclear-body and mitotic-chromosome localisation (HPA: subcellular ICC-IF). This is IF localisation evidence, not an extra IHC-P protocol or a requirement that a chromogenic section resolve each structure (HPA: subcellular ICC-IF; general IHC practice).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
A documented High tissue has no discernible nucleolar stain.Weak detection, an unsuitable antibody setup, or a problem with the section can remove interpretable contrast (general IHC practice).Check the positive-control section and reagent steps, then repeat using established IHC-P conditions for the chosen antibody (general IHC practice). Compare with the HPA High cell type, without assuming a fixed required intensity (HPA: tissue IHC).
The chromogen is concentrated at tissue edges or spread broadly over the section.Uneven reagent coverage, insufficient washing, or overdevelopment may create nonlocalised color (general IHC practice).Inspect the no-primary control, reagent coverage, washes, and development endpoint (general IHC practice). Score GNL3 only where cellular nuclear contrast is interpretable against the HPA nucleolar pattern (HPA: tissue IHC).
Cytoplasmic or membrane staining dominates.The observed compartment conflicts with the reported nuclear/nucleolar location and nonmembrane topology (UniProt Q9BVP2: location and topology).Check controls and antibody specificity before assigning a positive call (general IHC practice). Look for distinct nucleolar staining in an HPA High cell population on a comparable section (HPA: tissue IHC).
A Low-listed population stains visibly.HPA Low is a relative staining level, not evidence of absent GNL3 (HPA: tissue IHC).Do not use that population as a negative-control standard. Compare its compartment and strength with a documented High population, such as colon glandular cells (HPA: tissue IHC).
Strong color appears in unexpected cells but expected nuclei are faint.Cross-reactivity or endogenous detection activity is possible; HPA's High examples do not define an exclusive set of expressing cells (general IHC practice; HPA: tissue IHC).Review the no-primary control, identify the stained cell population, and check for nucleolar localisation before interpreting the signal (general IHC practice; HPA: tissue IHC).
Nuclear staining is visible, but no nucleolar rim can be resolved.A chromogenic section may not resolve the rim described by ICC-IF, even when it shows nuclear puncta (HPA: subcellular ICC-IF; general IHC practice).Judge IHC by distinct nucleolar contrast in the appropriate cells; use the separate IF/ICC guide when rim localisation needs direct assessment (HPA: tissue IHC and subcellular ICC-IF; general IHC practice).

Sample controls for GNL3 IHC & IF

🧪Run colon first and expect high staining in glandular cells (HPA: High in colon glandular cells). HPA detects GNL3 in all 45 scored tissues, so use no-primary and isotype controls in place of a negative tissue; cells without nucleolar DAB signal on the colon slide should show counterstain with minimal background, but are not validated GNL3-negative cells (HPA: no negative tissue; UniProt Q9BVP2: nucleolar localization).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: None in HPA: GNL3 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show GNL3 in A-431, U-251MG, U2OS, with annotated localisation: Nucleoli rim (enhanced) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control, a nonimmune rabbit IgG isotype control matched to the primary antibody’s clonality, and GNL3-knockout material as a biological negative (caption: rabbit primary antibody; standard IHC controls). Check endogenous peroxidase and biotin background on the colon section because the selected IHC detection uses a biotinylated secondary, streptavidin–biotin complex, and DAB (caption: detection method; standard chromogenic IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected paraffin-section caption does not state its fixative (caption: fixative unreported). The demonstrated IHC conditions use heat retrieval in EDTA at pH 8.0; this supports testing retrieval but does not establish that it is required for every specimen (caption: EDTA heat retrieval). IF/ICC has supporting localization images in A-431, U-251MG, and U2OS cells, with signal mainly at the nucleoli rim; frozen-section feasibility and a relative ease advantage are unreported, and colon background should be checked with the stated chromogenic controls (HPA: subcellular ICC-IF; caption: chromogenic detection).

HPA tissue IHC evidence for GNL3

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — High consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Breast Glandular cells High Protein (IHC) HPA →
Cerebellum Purkinje cells High Protein (IHC) HPA →
Colon Glandular cells High Protein (IHC) HPA →
Endometrium Cells in endometrial stroma Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: GNL3 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced GNL3 IHC Tips

Troubleshoot GNL3 staining by checking nucleolar localisation, section processing and detection controls (UniProt Q9BVP2; HPA tissue IHC).

What retrieval conditions should I start with for GNL3 paraffin-section IHC?
Start with heat-mediated retrieval in EDTA at pH 8.0 for paraffin-section GNL3 IHC (datasheet A03283-3). The selected image used this retrieval before 10% goat-serum blocking and 2 μg/ml primary antibody overnight at 4°C (caption A03283-3). If nucleolar staining is weak, compare controlled heating times on adjacent sections while keeping detection and counterstaining constant (standard IHC practice; HPA tissue IHC). Record heating duration and cooling conditions, because the caption does not specify them (caption A03283-3). Judge improvement by sharper nucleolar signal without diffuse nuclear or tissue-edge staining (HPA tissue IHC; standard IHC practice).
How should I handle fixation when GNL3 nucleolar staining is inconsistent?
Target-specific fixation sensitivity is unknown: the selected paraffin-section image does not state its fixative (caption A03283-3). Document fixative, fixation duration and tissue thickness for each specimen, then compare similarly processed sections before changing antibody conditions (standard IHC practice). Keep retrieval at EDTA pH 8.0 and primary incubation at 2 μg/ml overnight at 4°C while assessing processing differences (caption A03283-3). Use preserved nuclear morphology and nucleolar signal as readouts, since GNL3 is nuclear and nucleolar (UniProt Q9BVP2; HPA tissue IHC). Do not infer fixation tolerance from tissue expression patterns or GNL3 modifications (HPA tissue IHC; UniProt Q9BVP2).
Which staining pattern supports a specific GNL3 result?
Look for predominantly nucleolar chromogen within intact nuclei; tissue IHC reports nucleolar expression across tissues (HPA tissue IHC). A nucleolar-rim pattern is supported by cellular imaging, while nuclear bodies and mitotic chromosomes are additional locations (HPA subcellular). GNL3 shuttles between nucleolus and nucleus, so limited nucleoplasmic staining can be biologically plausible if morphology and controls agree (UniProt Q9BVP2; standard IHC practice). Evaluate glandular cells in colon or breast as documented high-staining compartments, and compare adjacent stromal cells within the same section (HPA tissue IHC; standard IHC practice). Diffuse cytoplasmic staining alone conflicts with the expected localisation and warrants a detection-control check (UniProt Q9BVP2; standard IHC practice).
Could isoforms or epitope masking explain discordant GNL3 IHC staining?
GNL3 has 2 reported isoforms, but the supplied antibody evidence does not map this catalog antibody’s epitope (UniProt Q9BVP2; caption A03283-3). Therefore, do not assign a negative section to isoform loss without independent isoform-specific evidence (UniProt Q9BVP2; standard IHC practice). The protein lacks a transmembrane segment and has a CP-type G domain at residues 131–312 (UniProt Q9BVP2). Its reported modified residues include acetyllysine 79 and phosphoserines 101, 490, 504 and 517, but their effects on this unmapped epitope are unknown (UniProt Q9BVP2; caption A03283-3). Compare retrieval-matched sections and an independently validated epitope before making an isoform interpretation (standard IHC practice).
How can IF help resolve ambiguous chromogenic GNL3 staining?
Use IF as a complementary localisation check: GNL3 is mainly nucleolar, with a reported nucleolar-rim pattern in cellular imaging (UniProt Q9BVP2; HPA subcellular). In colon glandular cells, multiplex GNL3 with an epithelial marker such as pan-cytokeratin to identify the expected cell population (HPA tissue IHC; standard IF practice). Choose a far-red GNL3 fluorophore if tissue autofluorescence obscures shorter wavelengths, and include single-colour and autofluorescence controls (standard IF practice). Because GNL3 is nuclear and has no transmembrane segment, permeabilise sufficiently to expose intracellular epitopes while preserving nuclear morphology; this antibody’s epitope is unmapped (UniProt Q9BVP2; caption A03283-3; standard IF practice). The paraffin IHC caption supplies no IF fixation or permeabilisation condition (caption A03283-3).
How do I distinguish GNL3 signal from chromogenic background?
Compare stained sections with a no-primary control and inspect whether brown product follows nucleoli rather than section edges or damaged areas (HPA tissue IHC; standard IHC practice). The selected method used 10% goat serum, a biotinylated secondary for 30 minutes at 37°C, an avidin-biotin complex and DAB (caption A03283-3). Include a peroxidase block and evaluate endogenous biotin when using that detection scheme; these are general chromogenic controls (standard IHC practice). If background remains broad, adjust antibody exposure against the documented 2 μg/ml overnight starting condition and assess signal-to-background on adjacent sections (caption A03283-3; standard IHC practice). Avoid calling uniform cytoplasmic deposits GNL3 solely because tissue is brown (UniProt Q9BVP2; standard IHC practice).
What should I score when comparing GNL3 across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define a positive cell by nucleolar staining within an intact nucleus before scoring intensity or area (HPA tissue IHC; standard IHC practice). Report an H-score from intensity and percentage of positive cells, or report the percentage of nucleolar-positive cells in a prespecified compartment (standard IHC practice). Normalise counts to evaluable nuclei in that same compartment and exclude necrotic or poorly preserved regions (standard IHC practice). Because glandular cells in colon and breast are reported as high-staining populations, keep cell-type composition separate from staining intensity when comparing specimens (HPA tissue IHC; standard IHC practice). Apply one threshold, counterstain setting and sampling rule across the comparison set (standard IHC practice).
When is an apparent GNL3-positive IHC result convincing?
A convincing result places chromogen in nucleoli of intact cells, consistent with tissue IHC and GNL3’s nuclear localisation (HPA tissue IHC; UniProt Q9BVP2). Interpret cell identity alongside compartment: colon glandular cells are reported high, whereas glomerular cells are reported low (HPA tissue IHC). Reject isolated edge staining, necrotic deposits and diffuse cytoplasmic colour when they fail the nucleolar-pattern and no-primary-control checks (HPA tissue IHC; standard IHC practice). The selected method uses DAB with an avidin-biotin complex, so endogenous peroxidase or biotin can produce misleading colour if controls fail (caption A03283-3; standard IHC practice). Nuclear bodies or mitotic-chromosome staining may be compatible with cellular localisation evidence but should be interpreted with morphology (HPA subcellular; standard IHC practice).
Boster reagents

Best GNL3 / Guanine nucleotide-binding protein-like 3 IHC Antibodies

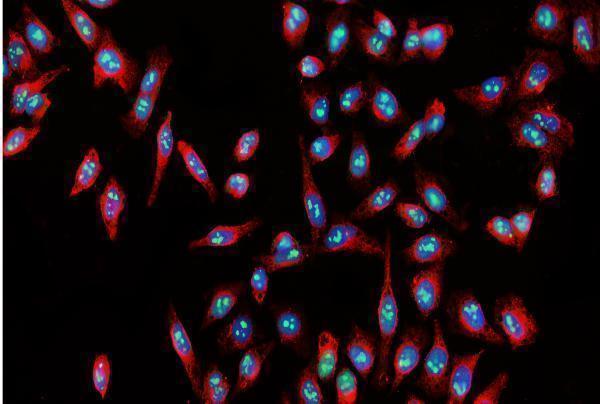
A03283-3 has IHC images from human paraffin sections and an IF image from HEP3B cells (catalog image captions). Its listed reactivity covers human, mouse and rat (catalog reactivity).

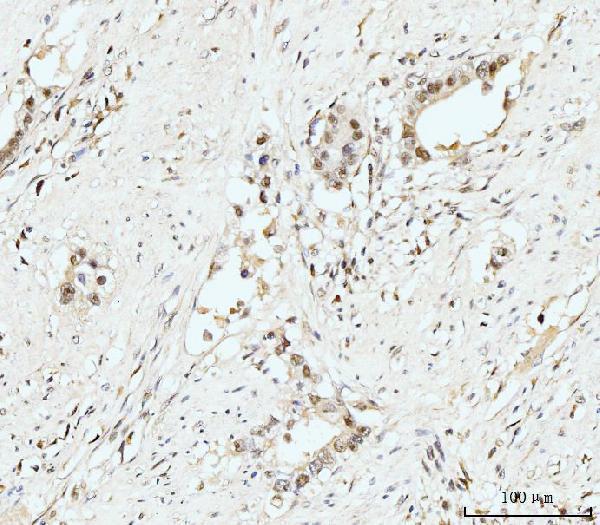
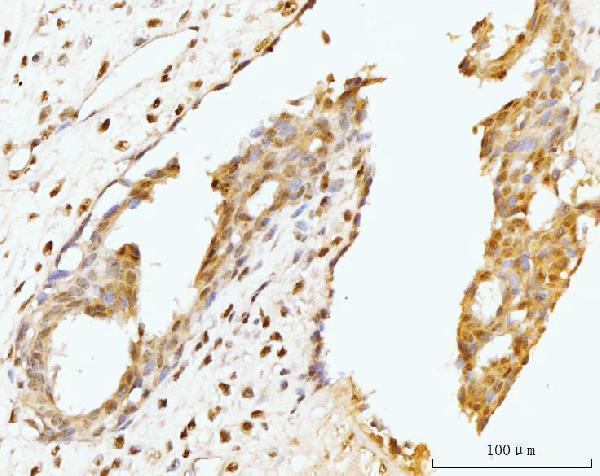
Real IHC data IHC analysis of Nucleostemin/GNL3 using anti-Nucleostemin/GNL3 antibody (A03283-3). Nucleostemin/GNL3 was detected in a paraffin-embedded section of human appendiceal adenocarcinoma tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-Nucleostemin/GNL3 Antibody (A03283-3) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-Nucleostemin/GNL3 Antibody ®
Cat # A03283-3

A03283-3 will render with its own IHC images from human appendiceal adenocarcinoma, breast cancer, colonic adenocarcinoma and gall bladder adenosquamous carcinoma paraffin sections (A03283-3 IHC image captions). Its own IF image shows HEP3B cells (A03283-3 IF image caption).

Which to pick: Choose A03283-3 for tissue IHC: its own paraffin-section captions document EDTA retrieval at pH 8.0 and 2 μg/ml primary antibody; the fixative is unreported (A03283-3 IHC image captions). For IF/ICC, A03283-3 has a HEP3B IF image, while M03283-1 is a rabbit monoclonal, clone 19G59, listed for human ICC/IF without an IF image in the payload (A03283-3 IF image caption; M03283-1 catalog applications, reactivity, clone and image list). For cross-species selection, A03283-3 lists human, mouse and rat reactivity, whereas M03283-1 lists human only; A03283-3’s shown IHC sections are human (catalog reactivity; A03283-3 IHC image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9BVP2 (GNL3_HUMAN, Guanine nucleotide-binding protein-like 3).
  2. Human Protein Atlas. GNL3 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. GNL3 subcellular location (ICC-IF): Mainly localized to the nucleoli rim. In addition localized to the nuclear bodies and mitotic chromosome..
  4. Human Protein Atlas. GNL3 antibody validation summary (3 antibodies).
  5. Upregulation of GNL3 expression promotes colon cancer cell proliferation, migration, invasion and epithelial-mesenchymal transition via the Wnt/β-catenin signaling pathway. Oncology reports 2017 — PMC5652940.
  6. GNL3 Regulates SIRT1 Transcription and Promotes Hepatocellular Carcinoma Stem Cell-Like Features and Metastasis. Journal of oncology 2022 — PMC9010172.
  7. Identification of new susceptibility loci for osteoarthritis (arcOGEN): a genome-wide association study. Lancet (London, England) 2012 — PMC3443899.
  8. OTX015 Epi-Drug Exerts Antitumor Effects in Ovarian Cancer Cells by Blocking GNL3-Mediated Radioresistance Mechanisms: Cellular, Molecular and Computational Evidence. Cancers 2021 — PMC8059141.
  9. PubMed PMID:11085516 — UniProt-cited evidence.
  10. PubMed PMID:16012751 — UniProt-cited evidence.
  11. PubMed PMID:14702039 — UniProt-cited evidence.