GPBAR1 / G protein-coupled bile acid receptor 1 · IHC design guide

Design Immunohistochemistry for GPBAR1

Plan chromogenic GPBAR1 IHC in paraffin sections with guidance on fixation, controls and scoring. Interpret the cytoplasmic tissue staining (HPA tissue IHC) alongside the annotated cell membrane location and seven-pass topology (UniProt).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for GPBAR1 (IHC for GPBAR1): expected localisation Cytoplasmic IHC; cell membrane location annotated (HPA tissue IHC; UniProt), antibody A30825, validated IHC image, and IHC protocol steps
Printable GPBAR1 IHC protocol sheet — expected localisation Cytoplasmic IHC; cell membrane location annotated (HPA tissue IHC; UniProt), antibody A30825, controls and protocol steps. Open the full GPBAR1 IHC guide →

GPBAR1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic IHC; cell membrane location annotated (HPA tissue IHC; UniProt)
Staining pattern Cytoplasmic staining in glandular and respiratory cells (HPA tissue IHC)
Antigen retrieval Tris-EDTA pH 9.0 HIER, heat-mediated (datasheet A30825)
Positive control ⓘ Appendix+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A30825)
Caveat Adipose RNA is enhanced, but adipocytes lack IHC staining (HPA tissue IHC)
Regulation Expression regulation not specified (UniProt)
Isoform / epitope 0 isoforms annotated; epitope side matters (UniProt)
Section 1

Recommended GPBAR1 IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol (datasheet A30825) with published GPBAR1 staining methods for HCC tissue (PMC9899898) and nude mouse tumor tissue (PMC9732702).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human tonsil tissue; fixative not specified (datasheet A30825)
FixationImage fixative and duration unreported (datasheet A30825); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: Tris-EDTA pH 9.0 (datasheet A30825); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-GPBAR1, 1:50 recommended; image 1:200 (datasheet A30825)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultGPBAR1-positive staining in glandular cells of appendix (HPA tissue IHC: Medium). HPA tissue profile: Cytoplasmic expression in several tissues. No signal in the no-primary control.
💡Decision noteStart with heat-mediated Tris-EDTA pH 9.0 for the catalog antibody (datasheet A30825); the HCC protocol used boiled EDTA pH 9.0 (PMC9899898).
Section 2

What Is the Expected GPBAR1 Staining Pattern?

GPBAR1 is a seven-pass cell-membrane receptor (UniProt Q8TDU6 topology). In paraffin IHC, expect staining in glandular cells of gallbladder, colon, or appendix and trophoblastic cells of placenta, each reported at medium intensity (HPA tissue IHC). HPA describes a cytoplasmic pattern across several tissues; its tissue IHC reliability is Enhanced, with medium consistency between antibody staining and RNA expression (HPA tissue IHC).

What am I looking at on my slide?
Discrete staining in gallbladder or colon glandular cells, with membrane-associated or cytoplasmic appearance.This fits the reported positive cell types and medium staining (HPA tissue IHC). Membrane association fits receptor topology (UniProt Q8TDU6); a cytoplasmic appearance also fits HPA's tissue IHC profile (HPA tissue IHC).
Predominantly nuclear signal, especially without staining in the expected cells.Nuclear localisation conflicts with the cell-membrane assignment (UniProt Q8TDU6) and HPA's cytoplasmic tissue IHC profile (HPA tissue IHC). Treat it as suspect staining and check controls before scoring it as GPBAR1.
Strong adipocyte staining while expected glandular cells show little signal.HPA reports GPBAR1 protein as not detected in adipocytes, despite tissue-enhanced adipose RNA (HPA tissue IHC). Consider antibody cross-reactivity or endogenous detection activity; RNA enrichment alone does not validate this protein pattern.
Uniform brown haze across cells, stroma, and empty areas.An indiscriminate deposit does not resemble HPA's cell-specific observations (HPA tissue IHC). Check background with a no-primary control, then review blocking, washes, detection, and counterstain using standard IHC practice.
No discernible signal in gallbladder glandular cells or placental trophoblastic cells.Both are reported at medium staining (HPA tissue IHC). First confirm that the expected cell type is present; then assess the catalog antibody's IHC-P procedure, detection reagents, and controls using standard IHC practice.
💡Expected GPBAR1 appearanceCall a positive result when glandular cells in gallbladder or colon, or placental trophoblastic cells, show discernible medium staining (HPA tissue IHC), compatible with membrane association (UniProt Q8TDU6) or HPA's cytoplasmic tissue pattern (HPA tissue IHC); diffuse field-wide or predominantly nuclear signal is suspect.
How each factor affects the staining
Subcellular referenceUniProt assigns GPBAR1 to the cell membrane and lists seven transmembrane segments (UniProt Q8TDU6). HPA reports cytoplasmic expression in tissue IHC (HPA tissue IHC). Assess both observations without requiring a sharply outlined membrane in every positive section.
Choice of comparison tissue and cellGallbladder, colon, appendix, and placenta have specified positive cell populations at medium staining; adipocytes and esophageal squamous cells are listed as not detected (HPA tissue IHC). Compare the named cells rather than whole-tissue color.
Strength of the validation evidenceHPA labels tissue IHC reliability Enhanced and records medium consistency with RNA; antibody HPA062890 is also IHC Enhanced (HPA tissue IHC; HPA antibodies). These summaries support pattern comparison but do not establish target-specific fixation sensitivity.
Reported protein featuresUniProt lists one GPBAR1 chain spanning residues 1–330, no annotated isoforms, and glycosylation sites at residues 4 and 76 (UniProt Q8TDU6). The supplied sources do not identify the antibody epitope or show how those sites affect paraffin IHC.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Expected positive tissue is blank.The sampled section may lack the named positive cells, or the IHC detection run may have failed (HPA tissue IHC; standard IHC practice).Confirm the glandular or trophoblastic cells on the section (HPA tissue IHC). Review the catalog antibody's IHC-P procedure and run a suitable positive control using standard IHC practice.
Only nuclei are strongly stained.That distribution does not match membrane localisation (UniProt Q8TDU6) or the cytoplasmic tissue IHC profile (HPA tissue IHC).Compare with a no-primary control and another reported positive tissue; inspect detection and counterstaining for artefact using standard IHC practice.
Adipocytes stain more strongly than the reported positive cells.HPA lists adipocyte protein staining as not detected, even though adipose tissue has enhanced RNA expression (HPA tissue IHC).Check the no-primary control for endogenous detection activity; reassess antibody specificity against the named positive and negative cell types (HPA tissue IHC; standard IHC practice).
Brown deposit obscures cell boundaries throughout the section.This differs from HPA's cell-resolved tissue observations (HPA tissue IHC) and is consistent with nonspecific IHC background (standard IHC practice).Review no-primary staining, blocking, washes, and detection conditions using standard IHC practice; score GPBAR1 only where the expected cells remain identifiable.
The stain looks cytoplasmic rather than sharply membranous.HPA describes cytoplasmic expression in several tissues (HPA tissue IHC), while UniProt assigns GPBAR1 to the cell membrane (UniProt Q8TDU6).Judge cell identity and control behavior alongside compartment. Do not reject a cell-specific cytoplasmic pattern solely because a continuous membrane rim is absent (HPA tissue IHC; UniProt Q8TDU6).
What should IF/ICC show?HPA's subcellular summary says membrane but provides no ICC-IF image cell lines or main-location entry (HPA subcellular ICC-IF).Use membrane localisation as the reference (UniProt Q8TDU6; HPA subcellular ICC-IF). Interpret an IF/ICC image with appropriate controls; this record supplies no image-based cell-line pattern to compare.

Sample controls for GPBAR1 IHC & IF

🧪Run appendix first and expect staining in its glandular cells (HPA: Medium in appendix glandular cells). Use adipose tissue as a biological negative, focusing on adipocytes (HPA: Not detected in adipocytes); on the appendix slide, nonglandular cells should show only background signal, but their GPBAR1 status is not established by the supplied HPA row.
Positive control tissue: Appendix (Glandular cells, HPA Medium)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA carries no ICC-IF cell line for GPBAR1; derive a cell-line control from the positive tissue's cell type (Glandular cells) and confirm it by RNA or western blot first.
Technical controls: Include a no-primary, secondary-only control and an isotype control matched to the primary antibody’s host species, immunoglobulin class and concentration (standard IHC practice). Use GPBAR1 knockout material, or immunogen-peptide competition if the peptide is available, to test specificity; block endogenous peroxidase for chromogenic detection and check appendix luminal material for nonspecific signal (standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A30825 paraffin-section caption does not state a fixative (caption: fixative unreported). The caption uses Tris-EDTA at pH 9.0 for retrieval and primary antibody at 1:200 overnight at 4 °C, but does not establish that retrieval is required (caption: A30825 tonsil IHC). The supplied evidence does not establish that frozen sections or IF/ICC are easier (HPA subcellular: no ICC-IF image-bearing cell lines); assess possible luminal debris staining in appendix against controls while evaluating cellular, membrane-associated signal (HPA: Medium in appendix glandular cells; UniProt Q8TDU6: cell membrane).

HPA tissue IHC evidence for GPBAR1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Appendix Glandular cells Medium Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Medium Protein (IHC) HPA →
Cervix Glandular cells Medium Protein (IHC) HPA →
Colon Glandular cells Medium Protein (IHC) HPA →
Gallbladder Glandular cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Caudate Glial cells Not detected Protein (IHC) HPA →
Cerebellum Cells in granular layer Not detected Protein (IHC) HPA →
Section 3

Advanced GPBAR1 IHC Tips

Troubleshoot GPBAR1 staining in paraffin sections by checking retrieval, compartment, cell identity and controls before comparing chromogenic IHC results (datasheet A30825; UniProt Q8TDU6 topology).

What retrieval should I start with for weak GPBAR1 staining in paraffin sections?
Start with heat-mediated retrieval in Tris-EDTA at pH 9.0 for paraffin sections (datasheet A30825). The selected tonsil image used this retrieval with primary antibody at 1:200 overnight at 4°C, so it is the closest documented starting condition for this antibody (caption A30825). If staining remains weak, compare retrieval duration on adjacent sections while holding antibody concentration and detection conditions constant (standard IHC practice). Check tissue preservation and include a known staining control before attributing a weak result to retrieval; the receptor has 7 transmembrane segments, but its antibody epitope is not specified here (UniProt Q8TDU6 topology; standard IHC practice).
How should I assess whether fixation is causing weak GPBAR1 IHC staining?
Target-specific fixation sensitivity is unknown: the selected tissue image describes paraffin-embedded tonsil but does not state its fixative (caption A30825). Record the fixative, time before fixation and fixation duration for each specimen, then compare sections processed under known conditions with the same retrieval and detection run (standard IHC practice). Use Tris-EDTA at pH 9.0 and the documented 1:200 primary dilution as a controlled starting point for this antibody (datasheet A30825; caption A30825). If staining differs across specimens, assess morphology and a control stain before assigning the difference to GPBAR1 abundance or fixation (standard IHC practice).
Should GPBAR1 appear at the membrane or in the cytoplasm on IHC?
GPBAR1 is annotated as a cell-membrane receptor with 7 transmembrane segments, whereas the tissue IHC profile reports cytoplasmic staining in several tissues (UniProt Q8TDU6 subcellular location and topology; HPA tissue IHC profile). Score membrane and cytoplasmic signal separately rather than treating either pattern alone as proof of specificity (standard IHC practice). Examine intact cells at high magnification and compare staining with cell identity, morphology and an appropriate control section (standard IHC practice). Diffuse cytoplasmic staining warrants particular caution because the reported HPA tissue pattern has only medium consistency with RNA expression data (HPA reliability description).
Can isoforms or epitope position explain variable GPBAR1 staining?
The supplied record lists one GPBAR1 chain spanning residues 1–330 and no annotated isoforms, so an isoform-specific staining explanation is unsupported here (UniProt Q8TDU6 processing and isoforms). Its topology places residues 284–330 on the cytoplasmic side and residues 1–21 on the extracellular side, but the catalog antibody's epitope is unspecified (UniProt Q8TDU6 topology; supplied A30825 caption). Two glycosylation sites are annotated at residues 4 and 76; their effect on this antibody's staining is unknown (UniProt Q8TDU6 glycosylation; supplied A30825 caption). Compare retrieval conditions and tissue controls before interpreting a staining change as epitope masking (standard IHC practice).
How can IF help resolve which cells carry the GPBAR1 IHC signal?
Use a companion IF experiment to test whether GPBAR1 signal overlaps a marker for the cell type suspected from the chromogenic section; HPA reports medium staining in gallbladder glandular cells and placental trophoblastic cells (HPA tissue IHC; standard IF practice). Select spectrally separated fluorophores after checking tissue autofluorescence and include single-label and no-primary controls (standard IF practice). Permeabilisation should follow the antibody epitope's membrane orientation: a cytoplasmic epitope requires access across the membrane, while an extracellular epitope may not; the catalog antibody's epitope is unspecified (UniProt Q8TDU6 topology; supplied A30825 caption; standard IF practice). Keep IF optimisation separate from the documented paraffin-section IHC conditions (caption A30825; standard IF practice).
What should I check when GPBAR1 chromogenic staining is widespread or diffuse?
First inspect the no-primary control, tissue edges and damaged regions to distinguish diffuse chromogen from cellular staining (standard IHC practice). For peroxidase-based detection, check the endogenous-peroxidase block and development time; these are general chromogenic workflow controls, not evidence of GPBAR1 expression (standard IHC practice). The selected tonsil image used primary antibody at 1:200 overnight at 4°C and secondary antibody at 1:200 for 45 minutes at room temperature, providing documented settings to compare (caption A30825). Interpret widespread signal against the receptor's membrane annotation and the reported cytoplasmic tissue IHC pattern, while retaining cell-level morphology as a check (UniProt Q8TDU6 subcellular location; HPA tissue IHC profile; standard IHC practice).
How should I score GPBAR1 staining across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring: GPBAR1 is annotated at the membrane, while HPA describes cytoplasmic tissue staining (UniProt Q8TDU6 subcellular location; HPA tissue IHC profile; standard IHC practice). Within the chosen population, record the percentage of positive cells and an intensity score of 0–3, or calculate an H-score of 0–300 using the percentages at each intensity (standard IHC practice). If counting isolated positive cells, report density per mm² of viable tissue instead (standard IHC practice). Normalise to the relevant cell count or viable tissue area, and apply the same threshold, compartment rule and imaging conditions across sections (standard IHC practice).
What evidence separates true GPBAR1 positivity from a staining artefact?
Look for reproducible cellular staining in a defined population rather than signal limited to cut edges, necrotic areas or regions with poor morphology (standard IHC practice). GPBAR1 has a cell-membrane annotation, yet HPA reports cytoplasmic tissue staining, so compartment agreement alone cannot establish specificity (UniProt Q8TDU6 subcellular location; HPA tissue IHC profile). Compare plausible cells with documented patterns, such as medium staining in colon glandular cells, while remembering that HPA reports no detection in esophageal squamous epithelial cells (HPA tissue IHC). A no-primary control, appropriate peroxidase block and consistent staining across replicate sections help identify endogenous enzyme signal and technical artefacts (standard IHC practice).
Boster reagents

Best GPBAR1 / G protein-coupled bile acid receptor 1 IHC Antibodies

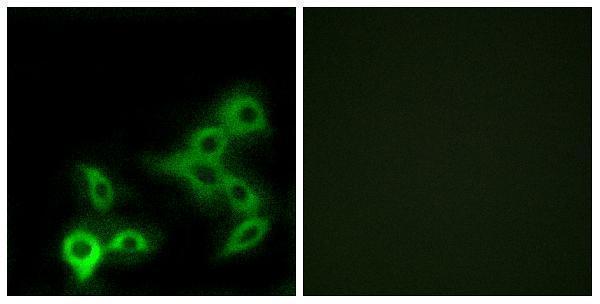
A30825 has human tonsil paraffin-section IHC data and LOVO-cell IF imagery (A30825 image captions); its listed reactivity covers human, mouse, and rat (catalog: reactivity).

Real IHC data Immunohistochemical analysis of paraffin-embedded human tonsil. 1, Antibody was diluted at 1:200(4° overnight). 2, Tris-EDTA,pH9.0 was used for antigen retrieval. 3,Secondary antibody was diluted at 1:200(room temperature, 45min).
Anti-GPBAR Antibody
Cat # A30825

A30825 will render with its human tonsil paraffin-section IHC figure, which documents 1:200 primary dilution and Tris-EDTA pH 9.0 retrieval (A30825 IHC caption). A separate image shows IF in LOVO cells with a peptide-blocked comparison (A30825 IF caption).

Which to pick: For tissue IHC, choose A30825: its own figure documents paraffin-embedded human tonsil, overnight primary incubation at 4°C, and Tris-EDTA pH 9.0 retrieval; the fixative is unreported (A30825 IHC caption). For cellular IF/ICC, A30825 has LOVO-cell IF imagery, although IF and ICC are absent from its listed applications (A30825 IF caption; catalog: applications). For cross-species work, A30825 is a rabbit polyclonal listed as reactive with human, mouse, and rat; its supplied IHC figure documents human tissue (catalog: host, clone, reactivity; A30825 IHC caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q8TDU6 (GPBAR_HUMAN, G protein-coupled bile acid receptor 1).
  2. Human Protein Atlas. GPBAR1 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. GPBAR1 subcellular location (ICC-IF): Membrane.
  4. Human Protein Atlas. GPBAR1 antibody validation summary (1 antibodies).
  5. GPBAR1 is associated with asynchronous bone metastasis and poor prognosis of hepatocellular carcinoma. Frontiers in oncology 2022 — PMC9899898.
  6. Gpbar1-mediated SIRT1-PGC-1α axis maintains mitochondrial homeostasis and mitigates renal injury in obstructive jaundice. Scientific reports 2025 — PMC12217075.
  7. Patchouli alcohol inhibits GPBAR1-mediated cell proliferation, apoptosis, migration, and invasion in prostate cancer. Translational andrology and urology 2022 — PMC9732702.
  8. The bile acid receptor GPBAR1 (TGR5) is expressed in human gastric cancers and promotes epithelial-mesenchymal transition in gastric cancer cell lines. Oncotarget 2016 — PMC5308633.
  9. PubMed PMID:12419312 — UniProt-cited evidence.
  10. PubMed PMID:12524422 — UniProt-cited evidence.
  11. PubMed PMID:12044878 — UniProt-cited evidence.