This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan HSD3B7 paraffin IHC around the reported cytoplasmic tissue staining (HPA tissue IHC) and ER membrane localization (UniProt). The catalog antibody has an IHC range of 2–5 μg/ml (datasheet A10025-1); include controls when interpreting staining because antibody staining and RNA expression show low consistency (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic tissue staining (HPA tissue IHC); ER membrane localization (UniProt) | |
| Staining pattern | Cytoplasmic staining in several tissue types (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet A10025-1) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep fixation consistent across sections. (standard IHC practice; not target-specific) | |
| Caveat | Staining shows low consistency with RNA expression (HPA tissue IHC) | |
| Regulation | No specific expression regulator annotated (UniProt) | |
| Isoform / epitope | 2 isoforms; epitope coverage is unspecified (UniProt) |
The catalog antibody’s IHC-P protocol (datasheet: A10025-1) is accompanied by a published application in human glioma paraffin sections (PMC12963632).
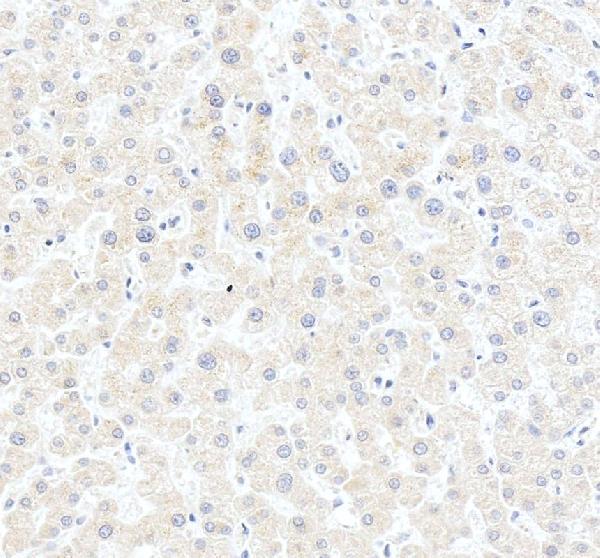
| Sample | Paraffin-embedded human liver tissue; fixative not specified (datasheet A10025-1) |
| Fixation | Image fixative and duration unreported (datasheet A10025-1); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet A10025-1); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet A10025-1) |
| Primary antibody | Rabbit anti-HSD3B7, 2-5 μg/ml (datasheet A10025-1) |
| Primary incubation | Overnight at 4 °C (datasheet A10025-1) |
| Detection | HRP-conjugated secondary, DAB chromogen (datasheet A10025-1) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | HSD3B7-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in several different tissue types. No signal in the no-primary control. |
In paraffin-section IHC, expect cytoplasmic HSD3B7 staining in glandular cells of the adrenal gland and several gastrointestinal tissues, kidney tubular cells, and lung macrophages (HPA: High in these cells). An intracellular pattern is consistent with its endoplasmic reticulum membrane annotation and two transmembrane segments (UniProt Q9H2F3 topology). HPA rates the tissue staining Approved but reports low agreement with RNA data and says external verification is pending (HPA: reliability).
| Cytoplasmic staining in kidney tubular cells, lung macrophages, or the listed glandular cells. | This matches the reported IHC distribution; HPA rates these cell groups High, except stomach glandular cells, which are Medium (HPA: tissue IHC). Score the named cells rather than assigning one intensity to an entire tissue. |
| A predominantly nuclear or extracellular deposit replaces the expected cytoplasmic pattern. | That compartment is inconsistent with the reported tissue pattern (HPA: cytoplasmic expression) and endoplasmic reticulum membrane annotation (UniProt Q9H2F3 topology). Check morphology, counterstain, and detection controls before interpreting it as HSD3B7. |
| Strong staining appears in cells reported as undetected, such as bronchial respiratory epithelium. | The result conflicts with the HPA tissue observation (HPA: bronchus respiratory epithelial cells Not detected). Cross-reactivity or detection-system activity is possible; the HPA rating and pending external verification make an independent check especially useful (HPA: reliability). |
| Color is spread across the section without clear cell boundaries or a cytoplasmic pattern. | Diffuse signal cannot establish cell-specific HSD3B7 expression. In chromogenic IHC, background from incomplete blocking, residual detection activity, or concentrated reagent can obscure the reported cell pattern (general IHC practice; HPA: cytoplasmic expression). |
| A listed High cell population has no detectable stain. | This disagrees with the HPA observation for that cell type (HPA: tissue IHC), but one negative slide does not prove absence. Review section quality, retrieval and detection conditions, and a working positive control (general IHC practice). |
| Tissue and cell selection | HPA reports High staining in adrenal, appendix, colon, duodenum, and small-intestine glandular cells, kidney tubules, and lung macrophages; stomach glandular cells are Medium (HPA: tissue IHC). Use the specified cell population when judging a control. |
| Strength of tissue evidence | The HPA tissue IHC entry is Approved, while its description reports low consistency between antibody staining and RNA expression and pending external verification (HPA: reliability). Treat a matching pattern as supporting evidence, especially when a new specimen differs. |
| RNA versus protein readout | Liver is tissue-enriched at the RNA level, but liver is not among the supplied positive IHC observations (HPA: RNA specificity; HPA: tissue IHC). RNA enrichment alone cannot specify the appearance or intensity of a liver IHC control. |
| Membrane topology and antibody access | HSD3B7 has two transmembrane segments at residues 289–309 and 311–331 (UniProt Q9H2F3 topology). That supports an intracellular membrane protein but does not identify the catalog antibody's epitope or establish an HSD3B7-specific retrieval setting. |
| Isoforms and processing | UniProt lists 2 isoforms and a chain spanning residues 1–369, with no signal peptide, propeptide, or annotated glycosylation sites (UniProt Q9H2F3). These annotations do not establish which isoforms the IHC antibody detects or predict different stain intensities. |
| IF/ICC Q: What localisation should be expected? | HPA reports an enhanced lipid-droplet localisation in ICC-IF, with images from Hep-G2, U2OS, MCF-7, and NIH 3T3 (HPA: subcellular; HPA: ICC Enhanced). This is a distinct assay observation; use the dedicated IF/ICC guide for its procedure. |
| Situation | Likely cause | Next action |
|---|---|---|
| No color in a chosen High-positive cell population. | The observed result conflicts with the HPA IHC report; a failed or weak staining run is one possible cause (HPA: tissue IHC; general IHC practice). | Verify that the target cells are present, then review the catalog antibody's IHC-P conditions, retrieval, dilution, and detection with a working positive section (general IHC practice). |
| Staining is mainly nuclear or extracellular. | The dominant compartment disagrees with HPA's cytoplasmic tissue pattern and UniProt's endoplasmic reticulum membrane location (HPA: tissue IHC; UniProt Q9H2F3). | Compare stain with cell morphology and counterstain; repeat with appropriate detection controls before scoring the unexpected compartment as positive (general IHC practice). |
| Bronchial respiratory epithelium or adipocytes stain strongly. | Those cells are reported Not detected by HPA; cross-reactivity or nonspecific color is possible, although an HPA-negative result is not proof of universal absence (HPA: tissue IHC; HPA: reliability). | Compare the suspect cells with a listed positive population on a controlled run and check a no-primary control; seek independent support for a persistent unexpected pattern (general IHC practice). |
| Color appears throughout tissue with little cellular definition. | Background can arise from staining or detection conditions and may hide a cytoplasmic pattern (general IHC practice; HPA: cytoplasmic expression). | Check reagent concentration, washes, blocking, and chromogen development against the validated IHC-P workflow; score only interpretable, cell-localized color (general IHC practice). |
| A no-primary control also develops color. | The signal can originate from endogenous detection activity or the detection reagents rather than primary-antibody binding (general chromogenic IHC practice). | Check endogenous-activity blocking and the detection reagents, then repeat the control alongside the specimen before interpreting HSD3B7 staining (general IHC practice). |
| IHC appears cytoplasmic while ICC-IF shows lipid droplets. | The reported readouts differ in compartment detail: tissue IHC is described as cytoplasmic, and ICC-IF as lipid-droplet localized (HPA: tissue IHC; HPA: subcellular). | Interpret each image within its assay and cell context; do not require paraffin-section chromogenic IHC to resolve the ICC-IF droplet pattern (HPA: tissue IHC; HPA: subcellular). |
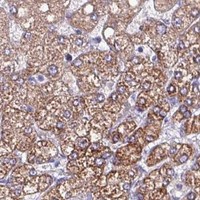
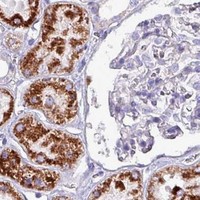
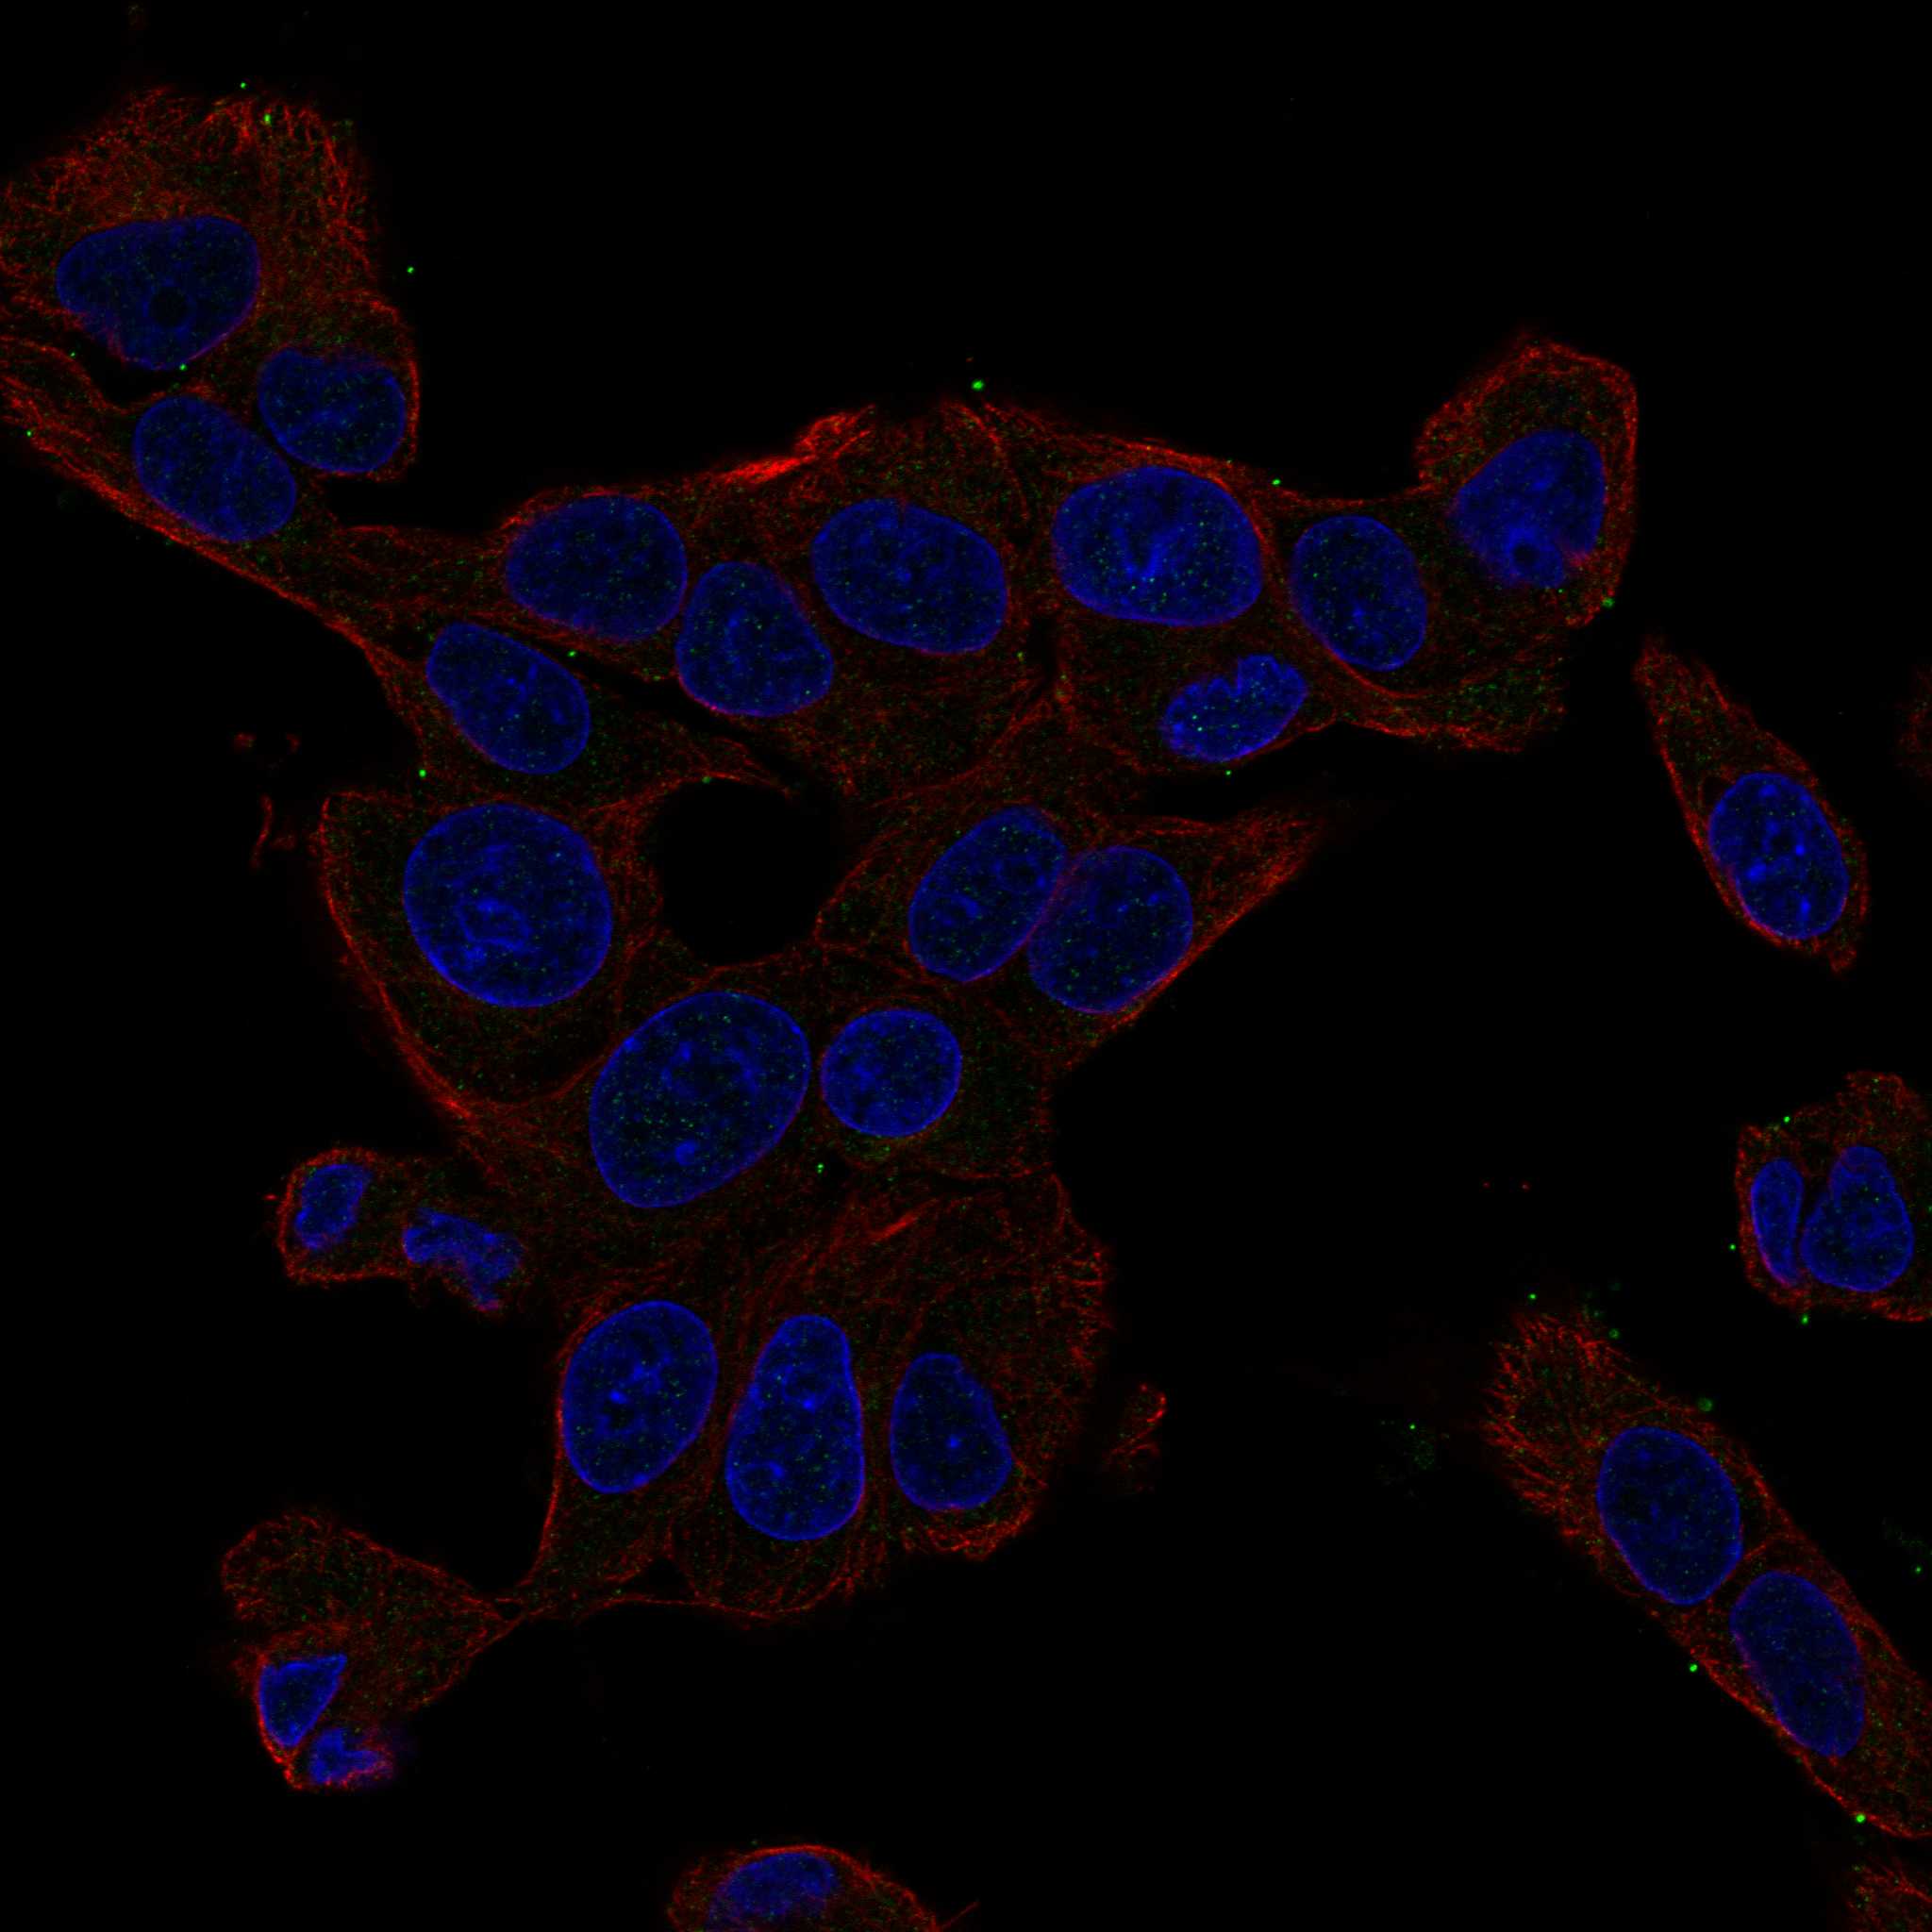

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | High | Protein (IHC) | HPA → |
| Appendix | Glandular cells | High | Protein (IHC) | HPA → |
| Colon | Glandular cells | High | Protein (IHC) | HPA → |
| Duodenum | Glandular cells | High | Protein (IHC) | HPA → |
| Kidney | Cells in tubules | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Not detected | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | Not detected | Protein (IHC) | HPA → |
| Cerebellum | Cells in granular layer | Not detected | Protein (IHC) | HPA → |
| Cervix | Glandular cells | Not detected | Protein (IHC) | HPA → |
Troubleshoot HSD3B7 staining by checking retrieval, cell identity, subcellular pattern, and controls before interpreting signal intensity.
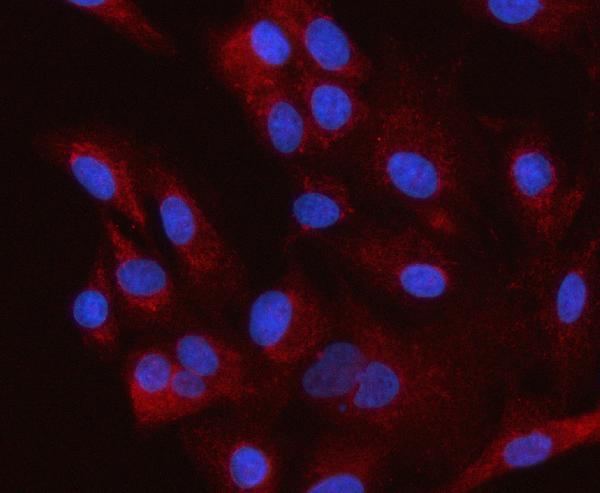
A10025-1 has IHC data from human liver paraffin sections (catalog IHC image caption) and IF data from A549 cells (catalog IF image caption); listed reactivity is human (catalog: reactivity).
A10025-1 is listed for human IHC and IF/ICC (catalog: applications and reactivity), with an IHC image from a paraffin-embedded human liver section (catalog IHC image caption). Its IF image shows staining in A549 cells (catalog IF image caption).
Which to pick: Choose A10025-1 for human paraffin-section IHC: its own image caption documents liver staining after heat retrieval in EDTA at pH 8.0; the fixative is unreported (catalog IHC image caption). For IF/ICC, A10025-1 is listed for both applications and shown staining A549 cells at 5 μg/ml; clonality is unreported (catalog: applications and clone; catalog IF image caption). No cross-species choice is supported because A10025-1 lists human reactivity only (catalog: reactivity).