This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan paraffin-section IPMK staining using the catalog antibody’s IHC dilution range of 1:100–1:300 (datasheet A06955-1). Assess cytoplasmic tissue staining while keeping the nuclear molecular annotation and the uncertain tissue IHC reliability in view (HPA tissue IHC; UniProt).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic in tissue (HPA tissue IHC); nuclear molecularly (UniProt) | |
| Staining pattern | Cytoplasmic staining in most tissues (HPA tissue IHC) | |
| Antigen retrieval | Tris-EDTA pH 9.0 HIER, heat-mediated (datasheet A06955-1) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep fixation consistent across sections (standard IHC practice; not target-specific) | |
| Caveat | Tissue staining awaits external verification (HPA tissue IHC) | |
| Regulation | Highest expression in skeletal muscle and liver (UniProt) | |
| Isoform / epitope | No annotated isoforms; one chain spans residues 2–416 (UniProt) |
Compare the catalog antibody’s IHC-P protocol (datasheet: A06955-1) with a published IPMK chromogenic IHC protocol (PMC10197106).
| Sample | Paraffin-embedded human Colon cancer tissue; fixative not specified (datasheet A06955-1) |
| Fixation | Image fixative and duration unreported (datasheet A06955-1); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: Tris-EDTA pH 9.0 (datasheet A06955-1); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-IPMK, 1:100-1:300 (datasheet A06955-1) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | IPMK-positive staining in glandular cells of adrenal gland (HPA tissue IHC: Medium). HPA tissue profile: Cytoplasmic expression in most tissues. No signal in the no-primary control. |
IPMK is a nuclear protein without a transmembrane segment (UniProt Q8NFU5). HPA ICC-IF supports nucleoplasmic localisation, while HPA tissue IHC reports cytoplasmic staining in most tissues (HPA: subcellular; HPA: tissue IHC). Expect staining in identifiable cells, including glandular, respiratory epithelial and neuronal cells reported at medium intensity (HPA: tissue IHC). Interpret the IHC pattern cautiously: its tissue-level reliability is Uncertain, pending external verification (HPA: tissue IHC).
| Nuclear staining in identifiable cells, with possible cytoplasmic staining on the IHC section. | Nuclear localisation agrees with UniProt and supported nucleoplasmic ICC-IF staining (UniProt Q8NFU5; HPA: subcellular). Cytoplasmic tissue staining has been reported, but its IHC reliability is Uncertain; record nuclear and cytoplasmic scores separately rather than treating either compartment as definitive (HPA: tissue IHC). |
| Medium staining in bronchial respiratory epithelium, cerebellar Purkinje cells or cortical neurons. | These are reported positive cell populations at Medium intensity (HPA: tissue IHC). Check that staining follows the named cells rather than every structure on the section (general IHC practice). A matching distribution supports interpretation, but it cannot independently resolve the Uncertain IHC reliability (HPA: tissue IHC). |
| A sharp membrane rim or extracellular deposit dominates the apparent signal. | That distribution conflicts with the nuclear annotation and absence of a transmembrane segment (UniProt Q8NFU5). Suspect nonspecific staining or a detection artefact; compare cell morphology and controls before assigning an IPMK score (general IHC practice). Cytoplasmic staining alone is less decisive because HPA reports it in tissue IHC (HPA: tissue IHC). |
| Strong staining appears in adipocytes or placental trophoblastic cells. | Both populations are reported Not detected by HPA tissue IHC, so strong staining there warrants a specificity check (HPA: tissue IHC). Cross-reactivity or endogenous chromogen-generating activity are possible causes (general IHC practice). A Not detected HPA result is not proof that every specimen must remain negative, particularly given Uncertain IHC reliability (HPA: tissue IHC). |
| A diffuse brown haze obscures cell boundaries, or a reported positive population has no visible signal. | Haze that does not follow cells is background, not a scorable IPMK pattern (general IHC practice). An absent signal in a reported Medium population may reflect assay performance or sample variation; the HPA observation alone does not diagnose the cause (HPA: tissue IHC). Compare a same-run control before interpreting a negative result (general IHC practice). |
| Compartment evidence | UniProt places IPMK in the nucleus, and HPA ICC-IF supports nucleoplasmic localisation; HPA tissue IHC instead describes cytoplasmic expression in most tissues with Uncertain reliability (UniProt Q8NFU5; HPA: subcellular; HPA: tissue IHC). Preserve this discrepancy when scoring. |
| Cell population and specimen choice | HPA reports Medium staining in several glandular, respiratory epithelial and neuronal populations, but Not detected in specific populations such as adipocytes and trophoblastic cells (HPA: tissue IHC). Use the reported cell type within the tissue, not the tissue name alone, to assess agreement. |
| Antibody validation | HPA037837 is Uncertain for IHC and Supported for ICC; HPA057542 has no IHC status listed and is Supported for ICC (HPA: antibodies). Supported ICC staining does not establish that either antibody yields a specific chromogenic IHC pattern (HPA: antibodies). |
| Topology and processing | No transmembrane segment or signal peptide is annotated, and no glycosylation sites are listed (UniProt Q8NFU5). These annotations give no basis to expect a membrane or secreted staining pattern; they do not establish epitope accessibility or fixation sensitivity (UniProt Q8NFU5). |
| IF/ICC Q&A: Where should IPMK appear? | Mainly in the nucleoplasm, with an additional basal-body location reported by HPA ICC-IF; the main location is Supported and the additional location Approved (HPA: subcellular). That cell-image evidence should be kept distinct from the Uncertain tissue IHC profile (HPA: tissue IHC). |
| Situation | Likely cause | Next action |
|---|---|---|
| Reported Medium-positive cells have no chromogenic signal. | The section or detection run may have failed, or that specimen may differ from the reported examples (general IHC practice; HPA: tissue IHC). | Check a same-run reported positive cell population and the detection controls; review antigen-retrieval and antibody-dilution records before calling the sample negative (general IHC practice). |
| Brown staining covers cells and empty spaces alike. | Cell-independent colour is consistent with background from the detection workflow, rather than a localised IPMK pattern (general IHC practice). | Inspect a no-primary control, wash and blocking conditions, and endogenous peroxidase quenching; score only signal that follows identifiable cells (general IHC practice). |
| A strong membrane rim is scored as IPMK. | The pattern disagrees with nuclear localisation and the lack of a transmembrane segment (UniProt Q8NFU5). | Recheck morphology and no-primary controls, then assess nuclear and cytoplasmic compartments separately; flag persistent rim staining for specificity review (general IHC practice). |
| Adipocytes or trophoblastic cells stain strongly. | Those cells are reported Not detected, though the HPA tissue IHC profile has Uncertain reliability (HPA: tissue IHC). | Check whether colour follows the named cells, inspect no-primary and endogenous-activity controls, and seek independent specificity evidence before treating it as IPMK (general IHC practice). |
| Cytoplasmic staining conflicts with the expected nuclear location. | HPA tissue IHC reports cytoplasmic expression, whereas UniProt and supported HPA ICC-IF place IPMK in the nucleus or nucleoplasm (HPA: tissue IHC; UniProt Q8NFU5; HPA: subcellular). | Report both compartments and the evidence conflict; avoid declaring cytoplasmic IHC signal either confirmed IPMK or an artefact on localisation alone (HPA: tissue IHC; HPA: subcellular). |
| Staining differs markedly between sections in one run. | Uneven section handling or detection can alter the apparent pattern (general IHC practice); HPA supplies no target-specific fixation-sensitivity finding here (HPA: tissue IHC). | Compare same-run controls and review section, retrieval, detection and counterstain records before attributing the difference to IPMK biology (general IHC practice). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Uncertain — Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | Medium | Protein (IHC) | HPA → |
| Appendix | Glandular cells | Medium | Protein (IHC) | HPA → |
| Breast | Glandular cells | Medium | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | Medium | Protein (IHC) | HPA → |
| Cerebellum | Purkinje cells | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Caudate | Glial cells | Not detected | Protein (IHC) | HPA → |
| Endometrium | Cells in endometrial stroma | Not detected | Protein (IHC) | HPA → |
| Fallopian tube | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Hippocampus | Glial cells | Not detected | Protein (IHC) | HPA → |
Use compartment-aware controls and matched processing to assess IPMK staining in paraffin sections; interpret tissue patterns cautiously (UniProt Q8NFU5; HPA tissue IHC).
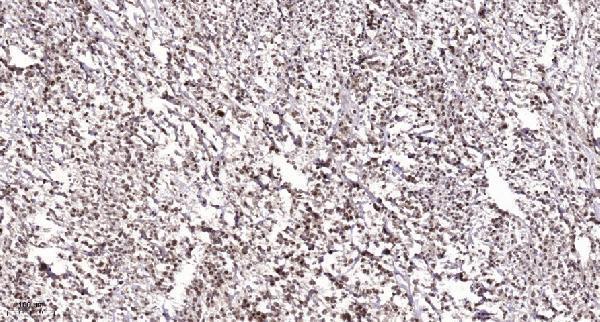
A06955-1 has a human paraffin-section IHC image (catalog image caption). IF is listed, but no IF image is provided (catalog applications; catalog IF images). Human, monkey, mouse and rat reactivity is listed (catalog reactivity).
A06955-1 will render with an IHC image from paraffin-embedded human colon cancer (catalog image caption). The same SKU lists IF among its applications and human, monkey, mouse and rat reactivity, but provides no IF image (catalog applications; catalog reactivity; catalog IF images).
Which to pick: For tissue IHC, choose A06955-1: its own image documents paraffin-embedded human colon cancer, 1:200 primary antibody overnight at 4°C, and Tris-EDTA retrieval at pH 9.0; the fixative is unreported (catalog image caption). For IF, A06955-1 lists a 1:50 dilution, but no IF image or ICC validation is provided (catalog IF dilution; catalog IF images; catalog applications). For cross-species work, A06955-1 is a polyclonal antibody with human, monkey, mouse and rat reactivity listed; its supplied IHC image documents human tissue only (catalog dilution data; catalog reactivity; catalog image caption).