This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic IHC for MRPL12 in paraffin sections using the catalog antibody (datasheet A10395-1: IHC). Use widespread granular cytoplasmic staining as a reference pattern, and interpret specificity cautiously because staining may reflect proteins from more than one gene (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Granular cytoplasm (HPA tissue IHC); mitochondrial matrix (UniProt) | |
| Staining pattern | Widespread granular cytoplasmic staining (HPA tissue IHC) | |
| Antigen retrieval | Tris-EDTA pH 9.0 HIER, heat-mediated (datasheet A10395-1) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | None in HPA (detected in all 45 tissues); use no-primary + isotype controls |
| Fixation | Keep fixation consistent across sections (standard IHC practice; not target-specific); Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A10395-1) | |
| Caveat | Staining may reflect proteins from more than one gene (HPA tissue IHC) | |
| Regulation | Low tissue specificity; no stimulus-linked change stated (HPA tissue IHC; UniProt) | |
| Isoform / epitope | No isoforms; an aa 37–44 epitope may miss the short mature form (UniProt) |
Start with the catalog antibody’s IHC-P protocol (datasheet A10395-1), then compare the published LUAD tissue protocols (PMC11441236; PMC9917664).
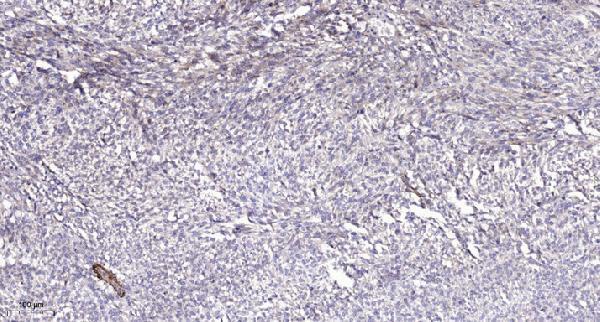
| Sample | Paraffin-embedded human Colon cancer tissue; fixative not specified (datasheet A10395-1) |
| Fixation | Image fixative and duration unreported (datasheet A10395-1); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: Tris-EDTA pH 9.0 (datasheet A10395-1); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-MRPL12, 1:50 recommended; image 1:200 (datasheet A10395-1) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | MRPL12-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Ubiquitous cytoplasmic expression with a granular pattern. No signal in the no-primary control. |
MRPL12 is a mitochondrial matrix protein without a transmembrane segment (UniProt P52815). In paraffin tissue IHC, expect granular cytoplasmic staining across many cell types, with strong staining reported in selected glandular, epithelial, hematopoietic and neuronal cells (HPA: tissue IHC). The tissue profile is Supported, with medium consistency between staining and RNA data; HPA cautions that the antibodies target proteins from more than one gene (HPA: tissue IHC).
| Fine granular cytoplasmic staining in adrenal glandular cells or bronchial respiratory epithelial cells. | This fits MRPL12's mitochondrial matrix location and HPA's ubiquitous granular cytoplasmic profile; both listed cell types stain High (UniProt P52815; HPA: tissue IHC). Judge the pattern within the identified cells, since a strong chromogen deposit alone cannot establish which protein the antibody detected (HPA: multi-gene antibody caution). |
| Predominantly nuclear, cell-surface or extracellular staining, without a granular cytoplasmic component. | Those compartments conflict with the mitochondrial matrix assignment and the reported tissue pattern (UniProt P52815; HPA: tissue IHC). Treat the result as suspect and compare it with a known-positive section and negative detection control; compartment alone does not identify the source of an artefact (standard IHC practice). |
| Strong staining in an unexpected cell population while the expected granular pattern is absent. | Check cell identity and the HPA tissue profile before calling it abnormal: expression is widespread, and the supplied tissue record lists no negative cell population (HPA: tissue IHC). If staining follows the detection reagents or lacks the expected pattern, consider cross-reactivity or endogenous detection activity (standard IHC practice; HPA: multi-gene antibody caution). |
| Uniform haze across tissue and empty spaces, obscuring individual cytoplasmic granules. | A diffuse deposit is difficult to reconcile with HPA's granular cytoplasmic profile (HPA: tissue IHC). Compare a section without primary antibody, then review blocking, washes and chromogen development as general background controls; this observation does not establish an MRPL12-specific fixation effect (standard IHC practice). |
| No detectable staining in adrenal glandular cells or bronchial respiratory epithelial cells. | Both are reported High in HPA tissue IHC, so an absent signal warrants a technical check before a biological interpretation (HPA: tissue IHC). Verify that the positive-control tissue and detection reagents worked, then review the antibody's IHC-P instructions; the supplied sources do not establish target-specific retrieval or fixation sensitivity (standard IHC practice). |
| Mitochondrial location and soluble topology | MRPL12 is assigned to the matrix and has no transmembrane segment (UniProt P52815). In IHC, assess intracellular granular cytoplasmic staining; membrane-rim staining has no support from the supplied localisation records (UniProt P52815; HPA: tissue IHC). |
| Cell population and tissue context | HPA reports Low tissue RNA specificity and a ubiquitous granular cytoplasmic protein profile, yet selected populations stain High and skeletal myocytes stain Low (HPA: tissue IHC). A weak myocyte result is therefore a poor basis for declaring a failed stain (HPA: tissue IHC). |
| Antibody attribution | Both listed antibodies have Supported IHC status, while HPA reports medium staining–RNA consistency and warns that the antibodies target proteins from more than one gene (HPA: antibody validation; HPA: tissue IHC). Pattern agreement supports interpretation but cannot, by itself, prove MRPL12-specific binding (HPA: multi-gene antibody caution). |
| Protein maturation | UniProt lists a 198-residue precursor and mature chains spanning residues 37–198 or 45–198 (UniProt P52815). Interpret staining as cellular localisation; without a supplied epitope map, these processing annotations cannot predict which form the IHC antibody detects (UniProt P52815). |
| IF/ICC comparison | For the separate IF/ICC guide: HPA reports supported mitochondrial localisation in ICC-IF and images from A-431, U-251MG and U2OS; both listed antibodies have Supported ICC status (HPA: subcellular; HPA: antibody validation). This supports a localisation cross-check, subject to HPA's multi-gene antibody caution (HPA: subcellular). |
| Situation | Likely cause | Next action |
|---|---|---|
| The positive-control section is blank. | A run-level antibody, detection or development failure is possible; adrenal glandular and bronchial respiratory epithelial cells are reported High (standard IHC practice; HPA: tissue IHC). | Check the control slide, reagent sequence and IHC-P instructions, then repeat the run with a documented positive control (standard IHC practice). Do not infer an MRPL12-specific fixation or retrieval effect from the supplied records. |
| The test section is weak, but the positive control stains. | Cell composition may explain the difference: HPA lists skeletal myocytes as Low, versus High staining in several glandular, epithelial, hematopoietic and neuronal populations (HPA: tissue IHC). | Confirm which cells were scored and compare like cell populations across sections (standard IHC practice). Report weak staining in its tissue context rather than treating every weak section as technical failure (HPA: tissue IHC). |
| Colour appears mainly over nuclei or along cell borders. | That distribution disagrees with the mitochondrial matrix assignment and HPA's granular cytoplasmic profile (UniProt P52815; HPA: tissue IHC). | Recheck focus, counterstain and cell boundaries; compare a known-positive section and a no-primary control before scoring the signal (standard IHC practice). |
| Granules are lost in widespread brown haze. | Background from detection reagents, incomplete blocking or excessive development can obscure cellular detail (standard IHC practice). | Inspect the no-primary control and review blocking, washes and development against the established IHC workflow (standard IHC practice). Score only a resolved cellular pattern that matches the reported granular cytoplasm (HPA: tissue IHC). |
| An unexpected cell population stains strongly. | MRPL12's tissue profile is broad, but antibody cross-reactivity or endogenous detection activity can also produce apparent signal (HPA: tissue IHC; standard IHC practice). HPA specifically cautions that its antibodies target proteins from more than one gene (HPA: tissue IHC). | Identify the stained cells, check whether signal is granular and cytoplasmic, and compare the no-primary control and HPA tissue observations (standard IHC practice; HPA: tissue IHC). Avoid assigning unexpected staining to MRPL12 from intensity alone (HPA: multi-gene antibody caution). |
| IHC granules and an IF/ICC image appear different. | The records describe granular cytoplasm in tissue IHC and supported mitochondrial localisation in ICC-IF; the methods display cellular detail differently (HPA: tissue IHC; HPA: subcellular; standard IHC practice). | Compare compartment and cell identity rather than requiring identical visual texture (standard IHC practice). Use the separate IF/ICC guide for IF decisions; HPA's multi-gene antibody caution applies to its localisation images (HPA: subcellular). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data. Caution, targets protein from more than one gene.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | High | Protein (IHC) | HPA → |
| Appendix | Endocrine cells | High | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | High | Protein (IHC) | HPA → |
| Breast | Glandular cells | High | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| None in HPA: MRPL12 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead. | ||||
Troubleshoot MRPL12 staining in paraffin sections by checking retrieval, granular cytoplasmic localisation, controls, and scoring consistency (UniProt P52815; HPA tissue IHC).
MRPL12 IHC is listed for human and mouse samples (catalog applications/reactivity), with a paraffin-section human colon cancer image for A10395-1 (image caption). A10395-3 also lists IF/ICC (catalog applications).
A10395-1 lists human and mouse IHC and shows staining in paraffin-embedded human colon cancer (catalog applications/reactivity; A10395-1 image caption). A10395-3 lists human, mouse, and rat reactivity for an antibody with IHC and IF/ICC applications, but has no IHC or IF image in the payload (A10395-3 catalog applications/reactivity; image alts).
Which to pick: For paraffin-section tissue IHC, choose A10395-1: its own image caption documents human colon cancer sections, 1:200 primary dilution, and Tris-EDTA retrieval at pH 9.0; the fixative is unreported (A10395-1 image caption). For IF/ICC, choose A10395-3, which lists both applications and a 1:50 IF dilution, though no IF image is supplied (A10395-3 catalog applications/dilution; image alts). For rat samples, A10395-3 is the listed option because its reactivity includes rat; it is polyclonal (A10395-3 catalog reactivity; dilution_raw).