NLRX1 / NLR family member X1 · IHC design guide

Design Immunohistochemistry for NLRX1

Plan NLRX1 staining in paraffin sections using the catalog antibody at 2–5 μg/mL (datasheet A04980-3). Use high-staining kidney tubules as a reference for the cytoplasmic, mitochondrial tissue pattern (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for NLRX1 (IHC for NLRX1): expected localisation Cytoplasmic, mitochondrial pattern (HPA tissue IHC), antibody A04980-3, validated IHC image, and IHC protocol steps
Printable NLRX1 IHC protocol sheet — expected localisation Cytoplasmic, mitochondrial pattern (HPA tissue IHC), antibody A04980-3, controls and protocol steps. Open the full NLRX1 IHC guide →

NLRX1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic, mitochondrial pattern (HPA tissue IHC)
Staining pattern High in kidney tubules; cytoplasmic, mitochondrial pattern (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A04980-3)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Cerebellum
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Staining–RNA consistency is medium (HPA tissue IHC)
Regulation Expression regulation not specified (UniProt)
Isoform / epitope 2 isoforms; epitope impact is unknown (UniProt)
Section 1

Recommended NLRX1 IHC & IF Protocols

The catalog antibody protocol uses EDTA pH 8.0 retrieval (datasheet A04980-3); the published IHC protocols below cover human skin (PMC13620316) and mouse lung (PMC9975446).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human breast cancer tissue; fixative not specified (datasheet A04980-3)
FixationImage fixative and duration unreported (datasheet A04980-3); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A04980-3); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A04980-3)
Primary antibodyRabbit anti-NLRX1, 2-5 μg/ml (datasheet A04980-3)
Primary incubationOvernight at 4 °C (datasheet A04980-3)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A04980-3)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultNLRX1-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic expression with a mitochondrial pattern. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet A04980-3); the published studies do not specify retrieval-buffer composition (PMC13620316; PMC9975446).
Section 2

What Is the Expected NLRX1 Staining Pattern?

NLRX1 is assigned to the mitochondrial outer membrane, with no transmembrane segment (UniProt Q86UT6 topology). In tissue sections, expect cytoplasmic staining with a mitochondrial pattern (HPA tissue IHC). Strong staining is reported in esophageal squamous epithelium, bronchial respiratory epithelium, kidney tubules and several glandular cell populations (HPA tissue IHC). The tissue IHC assessment is Supported, with medium consistency between antibody staining and RNA expression (HPA tissue IHC).

What am I looking at on my slide?
Granular cytoplasmic staining in the expected epithelial or glandular cells.Consistent with the reported mitochondrial pattern (HPA tissue IHC) and mitochondrial outer-membrane assignment (UniProt Q86UT6). Chromogenic IHC cannot resolve the outer membrane itself (general IHC practice).
Predominantly nuclear staining, with little cytoplasmic signal.This differs from the reported cytoplasmic mitochondrial pattern (HPA tissue IHC). Review morphology and controls before scoring nuclei as NLRX1-positive; consider nonspecific staining (general IHC practice).
Strong staining in cerebellar granular-layer cells.Unexpected: NLRX1 was not detected there (HPA tissue IHC). Consider cross-reactivity or endogenous detection activity (general IHC practice); compare with a known-positive tissue before interpreting the result.
Diffuse color across cells and surrounding tissue, obscuring cell boundaries.A diffuse field cannot establish the reported mitochondrial pattern (HPA tissue IHC). Background from detection reagents or inadequate blocking is possible; inspect the negative detection control (general IHC practice).
No staining in kidney tubules or esophageal squamous epithelium.Both are reported High (HPA tissue IHC). Check whether the run worked before calling the sample negative; absence in one section alone does not overturn the reference pattern (general IHC practice).
💡Expected NLRX1 appearanceA convincing positive is cytoplasmic staining with a mitochondrial pattern in an expected cell population, potentially strong in kidney tubules or esophageal squamous epithelium (HPA tissue IHC); dominant nuclear color or uniform field-wide color warrants investigation (general IHC practice).
How each factor affects the staining
Subcellular assignmentMitochondrial outer membrane, with no transmembrane segment (UniProt Q86UT6 topology); assess the cytoplasmic pattern at the resolution of the IHC image (general IHC practice).
Tissue and cell selectionHigh staining is reported in bronchial respiratory epithelium, kidney tubules and esophageal squamous epithelium (HPA tissue IHC). Cerebellar granular-layer cells were not detected (HPA tissue IHC).
Strength of tissue evidenceTissue IHC is Supported, with medium staining–RNA consistency (HPA tissue IHC). Treat the listed cell patterns as reference observations, not a guarantee for every specimen.
Antibody validationHPA061516 is a rabbit polyclonal antibody with Supported IHC and Supported ICC status (HPA antibodies). Those ratings do not establish that another antibody has the same specificity.
IF/ICC Q: Where should the signal appear?A: Mainly in mitochondria (HPA subcellular, supported). Plasma-membrane localization is additional and uncertain (HPA subcellular); evaluate that observation cautiously.
Isoforms and epitopeTwo isoforms and a chain spanning residues 87–975 are listed (UniProt Q86UT6). No antibody epitope is supplied, so isoform-specific detection or an effect of processing cannot be predicted.
Fixation sensitivityTarget-specific fixation sensitivity is unreported in the supplied UniProt and HPA records. Optimize section preparation with controls as a general IHC practice, without assigning an NLRX1-specific effect.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Expected positive tissue shows no chromogenic signal.The run may have failed, or assay conditions may need optimization (general IHC practice); kidney tubules and esophageal squamous epithelium are reported High (HPA tissue IHC).Check the positive control, primary-antibody step, detection reagents and counterstain. Then evaluate retrieval and dilution within the antibody's documented IHC conditions (general IHC practice).
Color is predominantly nuclear.Nuclear-dominant staining conflicts with the reported cytoplasmic mitochondrial pattern (HPA tissue IHC); nonspecific signal is possible (general IHC practice).Compare a known-positive section and a negative detection control, then reassess cell boundaries and staining distribution before scoring (general IHC practice).
Unexpectedly strong signal appears in cerebellar granular-layer cells.That population was Not detected (HPA tissue IHC). Cross-reactivity or endogenous detection activity is possible (general IHC practice).Review the negative detection control and repeat alongside an expected positive tissue. Interpret persistent staining cautiously; an HPA reference is not a universal absence guarantee.
Diffuse color makes a mitochondrial pattern unreadable.General background may obscure the cytoplasmic pattern reported by HPA (HPA tissue IHC; general IHC practice).Inspect no-primary and detection controls; review blocking, washes and detection time, then score only cells whose boundaries and intracellular distribution remain interpretable (general IHC practice).
A sample stains more weakly than the chosen positive control.HPA reports different cell-level intensities: liver hepatocytes are Low, while kidney tubule cells are High (HPA tissue IHC).Compare like cell populations and confirm the positive control worked. Record intensity and distribution separately instead of treating all tissue as equally positive (general IHC practice).
IF/ICC shows apparent plasma-membrane signal.Plasma-membrane localization is listed as additional and uncertain; the main location is mitochondria (HPA subcellular).Compare the mitochondrial signal and appropriate imaging controls before assigning localization. Treat the membrane signal as tentative (HPA subcellular; general IF practice).

Sample controls for NLRX1 IHC & IF

🧪Run bronchus first: respiratory epithelial cells should stain (HPA: High in bronchus respiratory epithelial cells). Run cerebellum as the negative tissue, focusing on granular-layer cells (HPA: Not detected in cerebellum granular-layer cells); no cell type within the bronchus slide is established as an internal negative, so use adjacent cells only to assess background (UniProt: ubiquitously expressed).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Cerebellum (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show NLRX1 in A-549, MCF-7, U2OS, with annotated localisation: Mitochondria (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and an isotype-matched rabbit IgG control at the primary antibody concentration (hero caption: rabbit primary antibody; standard IHC practice); use matched NLRX1-knockout material as a biological negative if available (standard IHC practice). For bronchus sections developed with HRP/DAB, quench endogenous peroxidase and check that pigment or luminal material is not mistaken for staining (hero caption: HRP/DAB detection; standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A04980-3 paraffin-section caption does not state the fixative (hero caption: fixative not stated). The demonstrated IHC workflow uses heat retrieval in EDTA at pH 8.0; this supports trying that condition but does not establish that retrieval is required (hero caption: EDTA pH 8.0 retrieval). Frozen-section performance is unreported, while ICC-IF images exist for A-549, MCF-7 and U2OS; the supplied evidence does not establish that either approach is easier than paraffin IHC (HPA: ICC-IF image cell lines; hero caption: paraffin-section IHC).

HPA tissue IHC evidence for NLRX1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Glandular cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →
Duodenum Glandular cells High Protein (IHC) HPA →
Esophagus Squamous epithelial cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Cerebellum Cells in granular layer Not detected Protein (IHC) HPA →
Section 3

Advanced NLRX1 IHC Tips

Troubleshoot NLRX1 staining in paraffin sections by checking retrieval, compartment pattern, controls and scoring before interpreting differences between samples.

How should I retrieve NLRX1 in paraffin sections when staining is weak?
Start with heat mediated retrieval in EDTA at pH 8.0 for the IHC validated antibody (datasheet A04980-3). A paraffin section of human breast cancer tissue was stained after this retrieval, followed by 2 μg/ml primary antibody overnight at 4°C (caption A04980-3). If signal is weak, compare retrieval heating and cooling conditions on adjacent sections while holding antibody concentration and detection constant (standard IHC practice). Inspect tissue integrity and background alongside signal, because excessive retrieval can damage morphology and complicate interpretation of cytoplasmic staining (standard IHC practice; HPA tissue IHC: general cytoplasmic expression).
Does fixation explain weak or uneven NLRX1 staining?
The selected tissue image identifies a paraffin section but does not state its fixative, so NLRX1 specific fixation sensitivity is unknown (caption A04980-3). Record the actual fixative and fixation duration for each specimen before comparing staining, and process matched sections together where possible (standard IHC practice). Begin with EDTA at pH 8.0, the documented retrieval condition for this antibody, then check whether weak areas coincide with poor morphology or uneven processing (datasheet A04980-3; standard IHC practice). Do not attribute a fixation effect to NLRX1 solely because its expected staining is cytoplasmic with a mitochondrial pattern (HPA tissue IHC: general cytoplasmic expression with a mitochondrial pattern).
What compartment pattern should count as plausible NLRX1 staining?
Expect predominantly cytoplasmic staining with a mitochondrial pattern in tissue sections (HPA tissue IHC: general cytoplasmic expression with a mitochondrial pattern). NLRX1 is assigned to the mitochondrial outer membrane and has no annotated transmembrane segment, so diffuse nuclear DAB staining alone does not fit its principal localisation (UniProt Q86UT6 topology and subcellular location). A plasma membrane location has also been reported with uncertain support; treat membrane only staining cautiously and compare it with a mitochondrial pattern in the same specimen (HPA subcellular: plasma membrane uncertain; mitochondria supported). Review a matched negative reagent control and cell morphology before calling fine brown cytoplasmic granules positive (standard IHC practice).
Could isoforms or epitope placement change the IHC pattern?
NLRX1 has 2 annotated isoforms, but the supplied antibody information does not identify its recognised epitope or establish isoform selectivity (UniProt Q86UT6 isoforms; caption A04980-3). Its annotated chain spans residues 87–975, with a NACHT domain at 160–483 and leucine rich repeat regions at 667–694 and 906–970 (UniProt Q86UT6 processing and domains). Ask for the antibody immunogen or epitope before interpreting staining differences as isoform specific, and keep EDTA at pH 8.0 constant during comparisons (datasheet A04980-3; standard IHC practice). If an epitope is unavailable, report the result as NLRX1 immunoreactivity rather than assigning it to either isoform (standard IHC interpretation).
How can IF help assess an ambiguous chromogenic NLRX1 pattern?
Use IF as a separate localisation check, since NLRX1 is mainly mitochondrial in the supplied subcellular evidence (HPA subcellular: mitochondria supported). Multiplex with a marker for the expected cell type, such as an epithelial marker when examining esophageal squamous epithelial cells, and assess signals within the same cells (HPA tissue IHC: high in esophageal squamous epithelial cells; standard IF practice). Choose fluorophores after examining unstained tissue for autofluorescence, and include single colour controls to distinguish overlapping signals (standard IF practice). Because the antibody epitope and its membrane facing side are unspecified, titrate permeabilisation against epitope accessibility while checking mitochondrial morphology; do not assume the IHC retrieval condition transfers to IF (caption A04980-3; standard IF practice).
What causes widespread brown staining without a mitochondrial pattern?
First compare the stained section with a negative reagent control and inspect whether DAB appears in structures lacking intact cells or expected cytoplasmic detail (standard IHC practice; HPA tissue IHC: mitochondrial cytoplasmic pattern). The demonstrated workflow used 10% goat serum blocking, 2 μg/ml primary antibody overnight at 4°C, and an enzyme based DAB readout (caption A04980-3). Check the peroxidase block, secondary antibody specificity, wash stringency and DAB development time when background is broad or uneven; these are general workflow variables (standard IHC practice). Recheck tissue edges and damaged regions separately before increasing the threshold for calling intact cells positive (standard IHC practice).
How should I quantify NLRX1 staining across tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, using cytoplasmic staining as the primary readout for NLRX1 (HPA tissue IHC: general cytoplasmic expression with a mitochondrial pattern). An H score combines the percentage of cells at each intensity with intensity from 0–3; alternatively, report the percentage of positive cells or positive cell density per mm² (standard IHC scoring practice). Normalise counts to the number of eligible intact cells or sampled tissue area, and apply the same threshold and imaging conditions across samples (standard IHC practice). Exclude necrotic areas and section edges using a prespecified rule, then report cell type and region alongside the score (standard IHC practice).
How do I distinguish genuine NLRX1 signal from artefact?
A plausible positive shows cytoplasmic staining with a mitochondrial pattern in intact cells, consistent with the supported tissue and subcellular observations (HPA tissue IHC: cytoplasmic mitochondrial pattern; HPA subcellular: mitochondria supported). High staining in glandular cells of the adrenal gland and low staining in liver hepatocytes provide documented cell type context, though neither establishes antibody specificity in an individual section (HPA tissue IHC: adrenal gland high; liver hepatocytes low). Treat isolated nuclear staining, edge accentuation, necrotic deposits or signal reproduced by a negative reagent control as reasons to investigate artefact (UniProt Q86UT6 subcellular location; standard IHC practice). Check peroxidase blocking when unexplained DAB persists, and base comparisons on intact cells scored under the same conditions (standard IHC practice).
Boster reagents

Best NLRX1 / NLR family member X1 IHC Antibodies

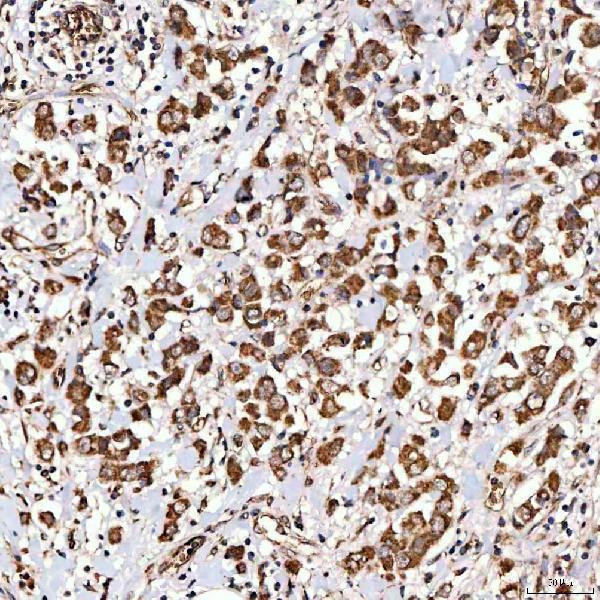
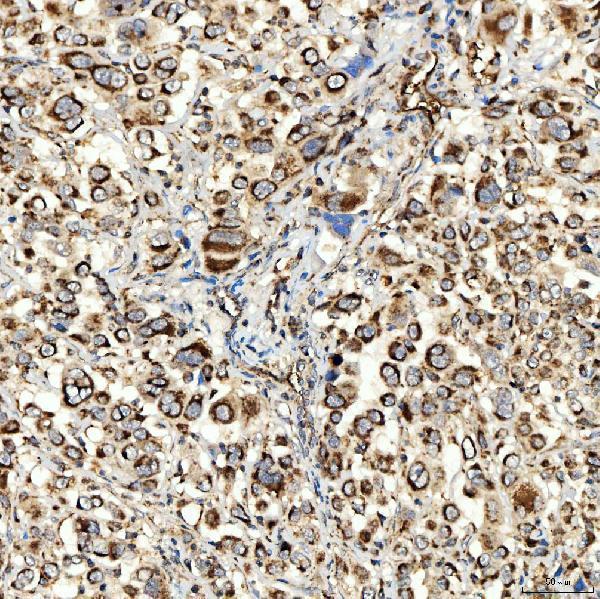
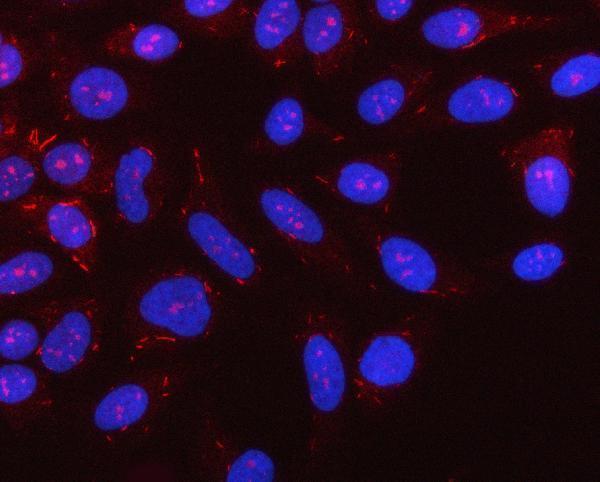
A04980-3 has IHC images from human paraffin sections and IF images from HeLa cells and human intestinal cancer sections (catalog image captions); its listed reactivity is human, mouse and rat (catalog).

Real IHC data IHC analysis of NLRX1 using anti-NLRX1 antibody (A04980-3). NLRX1 was detected in a paraffin-embedded section of human breast cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-NLRX1 Antibody (A04980-3) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-NLRX1 Antibody ®
Cat # A04980-3

A04980-3 has IHC images from paraffin sections of human breast cancer, lung adenocarcinoma and thyroid papillary carcinoma (catalog IHC captions). Its IF images show HeLa cells and a paraffin section of human intestinal cancer (catalog IF captions).

Which to pick: Choose A04980-3 for paraffin-section IHC: its IHC captions document that processing, while the fixative is unreported (catalog IHC captions). For IF/ICC, A04980-3 is listed for both applications and has corresponding cell and tissue images (catalog applications; catalog IF captions). For mouse or rat work, A04980-3 lists reactivity with both species, but the supplied IHC and IF images show human samples; clonality is unreported (catalog reactivity; catalog image captions; catalog clone field).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q86UT6 (NLRX1_HUMAN, NLR family member X1).
  2. Human Protein Atlas. NLRX1 tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. NLRX1 subcellular location (ICC-IF): Mainly localized to the mitochondria. In addition localized to the plasma membrane..
  4. Human Protein Atlas. NLRX1 antibody validation summary (1 antibodies).
  5. Repeated air pollution exposure predisposes to adverse outcomes from acute lung injury. Particle and fibre toxicology 2026 — PMC13285047.
  6. CircRNA Profiling Identifies hsa_circRNA_003201 Associated with a Predicted NLRX1-Related Regulatory Network in an Acne-Associated Inflammatory Sebocyte Model. Journal of inflammation research 2026 — PMC13620316.
  7. NLRX1 knockdown attenuates pro-apoptotic signaling and cell death in pulmonary hyperoxic acute injury. Scientific reports 2023 — PMC9975446.
  8. NLRX1 dampens oxidative stress and apoptosis in tissue injury via control of mitochondrial activity. The Journal of experimental medicine 2017 — PMC5551566.
  9. PubMed PMID:12766759 — UniProt-cited evidence.
  10. PubMed PMID:14702039 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.