This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic PARVA IHC on paraffin sections using the catalog antibody’s 0.5–1 μg/mL range (datasheet PB9555). Use tissue controls to assess the expected cytoplasmic staining, including in smooth muscle (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic staining in tissue; focal adhesions are molecular sites (HPA tissue IHC; UniProt) | |
| Staining pattern | Cytoplasmic staining, including in smooth muscle (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet PB9555) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | Adipose tissue |
| Fixation | Keep fixation consistent across sections. (standard IHC practice; not target-specific) | |
| Caveat | Hematopoietic cells can contribute signal in mixed tissue (HPA tissue IHC) | |
| Regulation | Expression varies by tissue (HPA tissue IHC) | |
| Isoform / epitope | 2 isoforms; verify epitope coverage for both (UniProt) |
Compare the catalog antibody’s IHC-P protocol (datasheet: PB9555) with one published PARVA tissue-staining protocol (PMC7947443).
| Sample | Paraffin-embedded human mammary cancer tissue; fixative not specified (datasheet PB9555) |
| Fixation | Image fixative and duration unreported (datasheet PB9555); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet PB9555); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet PB9555) |
| Primary antibody | Rabbit anti-PARVA, 0.5-1μg/ml (datasheet PB9555) |
| Primary incubation | Overnight at 4 °C (datasheet PB9555) |
| Detection | Streptavidin-biotin complex (SABC), DAB chromogen (datasheet PB9555) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | PARVA-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Ubiquitous cytoplasmic expression, including in smooth muscle. No signal in the no-primary control. |
PARVA is expected mainly in the cytoplasm and at cell adhesion structures, including focal adhesions; it has no transmembrane segment (UniProt Q9NVD7). Tissue IHC shows widespread cytoplasmic staining, including smooth muscle, with high staining in cardiomyocytes and several glandular cell populations (HPA: tissue IHC). Treat this as a guide rather than an absolute rule: HPA rates its tissue IHC data Approved, with medium consistency between staining and RNA expression (HPA: reliability).
| Cytoplasmic staining in cardiomyocytes or glandular cells, with staining in smooth muscle. | This fits PARVA's reported cytoplasmic distribution and the cell populations observed in tissue sections (HPA: tissue IHC). Cardiomyocytes and glandular cells in adrenal gland, breast, duodenum and other listed tissues are scored High; staining intensity can still vary within a section (HPA: tissue IHC). |
| Predominantly nuclear staining, with little convincing cytoplasmic signal. | A nuclear dominant result conflicts with the reported cell junction, cytoskeletal and cytoplasmic locations (UniProt Q9NVD7; HPA: subcellular). Review counterstain, detection background and controls before assigning it to PARVA. The supplied sources do not establish a nuclear IHC pattern. |
| Strong staining in adipocytes, especially if expected positive cells are weak. | Adipocytes are scored Not detected in HPA tissue IHC, so this pattern warrants checking specificity or detection background (HPA: adipose tissue). It is a warning, not proof of cross reactivity: HPA reports only medium consistency between antibody staining and RNA data (HPA: reliability). |
| Diffuse chromogen over extracellular spaces, tissue edges or the whole section. | Widespread cytoplasmic expression is expected, but deposit outside recognizable cells cannot establish PARVA localization (HPA: tissue IHC; standard IHC interpretation). Compare a no primary control and inspect the counterstain and tissue morphology to distinguish cellular signal from general background (standard IHC practice). |
| No detectable signal in intact cardiomyocytes in a heart muscle section. | Cardiomyocytes are scored High and provide a useful positive tissue reference (HPA: heart muscle). A blank result raises a technical or antibody performance question; it does not by itself establish absent PARVA. Check tissue preservation, assay controls and detection steps before interpreting other sections (standard IHC practice). |
| Tissue and cell selection | Heart muscle cardiomyocytes and several glandular populations are scored High, while adipocytes are Not detected (HPA: tissue IHC). Use cell identity when judging a section: PARVA is broadly expressed, so a tissue name alone does not identify which cells should carry the signal (HPA: tissue IHC). |
| Compartment and topology | PARVA has no transmembrane segment and is reported at focal adhesions, the cytoskeleton and in cytoplasm (UniProt Q9NVD7). These annotations support an intracellular interpretation. They do not establish that a routine chromogenic section must resolve individual focal adhesions (standard IHC interpretation). |
| Antibody evidence | The listed rabbit polyclonal antibody HPA005964 is Approved for IHC and Supported for ICC (HPA: antibodies). Overall tissue IHC reliability is Approved, with medium staining to RNA consistency (HPA: reliability). Interpret an unexpected cell pattern with controls rather than treating the approval rating as proof of specificity in every specimen. |
| Isoforms and processing | UniProt lists two PARVA isoforms, no signal peptide, no propeptide and a chain spanning residues 2–372 (UniProt Q9NVD7). These facts do not show which isoform the listed antibody recognizes or predict epitope accessibility in paraffin sections; no epitope or target specific retrieval evidence is supplied. |
| IF/ICC Q: What should a separate fluorescence assay show? | A: HPA reports supported localization mainly to actin filaments and focal adhesion sites, with additional cytosol signal in ICC IF (HPA: subcellular). That higher resolution pattern can inform interpretation, but it is separate from the chromogenic tissue IHC result and supplies no IHC protocol setting. |
| Situation | Likely cause | Next action |
|---|---|---|
| Heart muscle positive reference is blank. | The result conflicts with High cardiomyocyte staining in HPA tissue IHC (HPA: heart muscle); a failed detection step or unsuitable assay setting is possible (standard IHC practice). | Check the positive control, antibody and detection reagents, and section integrity; then review the assay's documented retrieval and dilution settings (standard IHC practice). No PARVA specific retrieval condition or dilution is supplied here. |
| Nuclei dominate the staining. | This does not match the supplied cytoplasmic, cytoskeletal and focal adhesion localization (UniProt Q9NVD7; HPA: subcellular). Counterstain or nonspecific signal may be misread (standard IHC practice). | Compare stained and no primary sections, inspect nuclear boundaries, and score only signal assigned to intact cells (standard IHC practice). Do not classify a nuclear dominant section as an expected PARVA pattern. |
| Adipocytes stain more strongly than nearby expected positive cells. | HPA scores adipocytes Not detected, making the cell distribution unexpected (HPA: adipose tissue). Cross reactivity or background is possible, but the image alone cannot distinguish them. | Confirm cell identity and compare with a no primary control and a positive tissue reference (standard IHC practice; HPA: heart muscle). Reassess the antibody result if the unexpected staining persists. |
| Brown deposit appears throughout the section, including extracellular areas. | Chromogen outside cells is not supported by PARVA's reported intracellular localization (UniProt Q9NVD7). In chromogenic IHC, nonspecific detection or endogenous enzyme activity can cause background (standard IHC practice). | Run a no primary control; review blocking, washes and the detection system, including any relevant endogenous peroxidase control (standard IHC practice). Judge PARVA only where cellular morphology remains clear. |
| Only weak cytoplasmic staining appears in a selected tissue. | HPA reports different cell level intensities: prostate glandular cells and ovarian stroma cells are Low, whereas cardiomyocytes are High (HPA: tissue IHC). Weak staining alone therefore does not establish assay failure. | Identify the stained cell type and compare it with the corresponding HPA tissue observation and an appropriate positive reference (HPA: tissue IHC; standard IHC practice). Avoid applying one intensity threshold across all tissues. |
| A punctate or peripheral pattern is difficult to interpret in paraffin IHC. | Focal adhesion and actin filament localization is supported by ICC IF, while tissue IHC is summarized as cytoplasmic (HPA: subcellular; HPA: tissue IHC). The supplied evidence does not require focal adhesions to be individually visible in chromogenic sections. | Assess the staining against cell morphology and cytoplasmic signal first (HPA: tissue IHC; standard IHC interpretation). Use the separate IF/ICC guide when the experimental question requires resolving focal adhesion sites. |

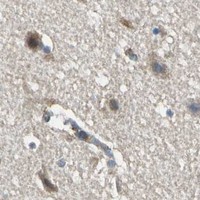


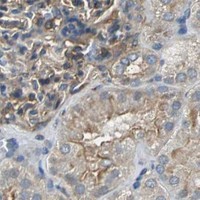


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | High | Protein (IHC) | HPA → |
| Appendix | Lymphoid tissue | High | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | High | Protein (IHC) | HPA → |
| Breast | Glandular cells | High | Protein (IHC) | HPA → |
| Duodenum | Glandular cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
Troubleshoot PARVA chromogenic IHC in paraffin sections using the catalog antibody’s tissue image, HPA staining patterns, and known protein localisation.
The IHC-validated anti-PARVA antibody PB9555 has an image from a paraffin section of human mammary cancer tissue (catalog IHC caption). Human, mouse and rat are listed as reactive species (catalog reactivity).
PB9555 will render with its own IHC image from a paraffin section of human mammary cancer tissue (catalog IHC caption). Its listed applications are IHC and WB, and its listed reactivity is human, mouse and rat; no IF image is supplied (catalog applications, reactivity and image records).
Which to pick: Choose PB9555 for paraffin-section IHC: its own caption documents staining at 1 μg/ml after EDTA pH 8.0 retrieval (catalog IHC caption). No SKU in this payload is listed for IF/ICC; PB9555 is a rabbit antibody with no clone reported (catalog applications, host and clone fields). For mouse or rat work, PB9555 lists reactivity with both species, but its IHC image documents human tissue only, and the fixative is unreported (catalog reactivity and IHC caption).