This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan PEX3 chromogenic IHC in paraffin sections using the IHC-validated antibody (datasheet A04166). Compare granular cytoplasmic staining in glandular and respiratory epithelial cells with the tissue reference, bearing in mind its medium consistency with RNA expression (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Granular cytoplasm (HPA tissue IHC); peroxisome membrane (UniProt) | |
| Staining pattern | Granular cytoplasm in glandular and respiratory epithelial cells (HPA tissue IHC) | |
| Antigen retrieval | Tris-EDTA pH 9.0 HIER, heat-mediated (datasheet A04166) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | Adipose tissue+3 more · see all |
| Fixation | Keep tissue fixation consistent across samples. (standard IHC practice; not target-specific) | |
| Caveat | Staining has medium consistency with RNA expression (HPA tissue IHC) | |
| Regulation | No specific expression regulator reported (UniProt) | |
| Isoform / epitope | No annotated isoforms or processing; epitope side may matter (UniProt) |
The catalog antibody protocol is paired with one published PEX3 chromogenic IHC protocol using mouse heart sections (PMC11217276).
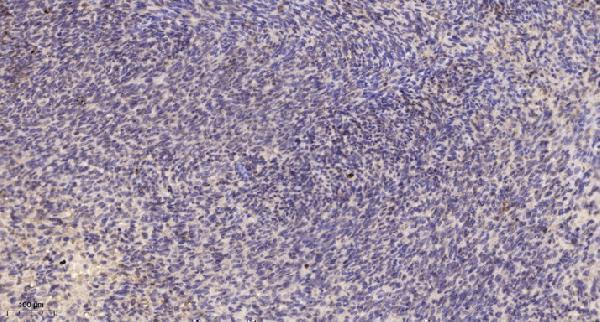
| Sample | Paraffin-embedded human uterus tissue; fixative not specified (datasheet A04166) |
| Fixation | Image fixative and duration unreported (datasheet A04166); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: Tris-EDTA pH 9.0 (datasheet A04166); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-PEX3, 1:50 recommended; image 1:200 (datasheet A04166) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | PEX3-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic expression with a granular pattern. No signal in the no-primary control. |
PEX3 is a peroxisome membrane protein with two transmembrane segments and a long cytoplasmic region (UniProt P56589 topology). In paraffin section IHC, expect granular cytoplasmic staining in several epithelial and glandular cell populations (HPA: tissue IHC profile). HPA rates the tissue pattern Supported, with medium consistency between staining and RNA expression (HPA: tissue IHC reliability).
| Granular cytoplasmic staining in kidney tubules, colon glands, or bronchial respiratory epithelium. | This fits the reported tissue pattern and cell distribution; each listed population stains High in HPA tissue IHC (HPA: kidney, colon, bronchus). The granules are compatible with peroxisomal localization (UniProt P56589: peroxisome membrane). Chromogenic granules alone do not identify individual peroxisomes, so judge them alongside cell type and controls (general IHC interpretation). |
| Predominantly nuclear staining, with little granular cytoplasmic signal. | This does not match the general granular cytoplasmic tissue IHC profile (HPA: tissue IHC profile). HPA ICC-IF reports nucleoplasm as uncertain and peroxisomes as supported (HPA: subcellular localization). Do not treat nuclear staining alone as a convincing IHC positive; review background and detection controls before attributing it to PEX3 (general IHC interpretation). |
| Strong color in a cell population HPA reports as Not detected, especially without the expected granules. | Adipocytes, bone marrow hematopoietic cells, cervical glandular cells, and soft tissue fibroblasts are listed as Not detected (HPA: tissue IHC). Unexpected staining can reflect nonspecific binding or endogenous detection activity (general IHC practice). HPA's Supported rating and medium staining–RNA consistency do not make every cell level absolute (HPA: tissue IHC reliability). |
| Diffuse color across multiple compartments, extracellular areas, or most cells. | A broad haze is difficult to reconcile with the reported granular cytoplasmic profile (HPA: tissue IHC profile). Consider nonspecific primary binding, incomplete blocking or washing, and detection background (general IHC practice). Compare the slide with a control omitting primary antibody before scoring any faint granules as positive (general IHC practice). |
| No convincing staining in an otherwise interpretable kidney tubule or colon gland section. | Those cell populations are reported High, making them useful positive comparators for this assay (HPA: kidney and colon tissue IHC). A blank result may indicate an assay or specimen problem, but does not establish that PEX3 is absent (general IHC interpretation). Check a known positive control and the staining workflow before making a biological call (general IHC practice). |
| Cell population and tissue | HPA reports High staining in several glandular or epithelial populations, Low staining in selected neuronal and squamous populations, and Not detected in specified adipocytes, hematopoietic cells, cervical glands, and fibroblasts (HPA: tissue IHC). Choose the comparison at the cell level; a tissue name alone does not assign every cell the same expected intensity (general IHC interpretation). |
| Topology and compartment | PEX3 has membrane segments at residues 16–36 and 117–140, with residues 141–373 on the cytoplasmic side (UniProt P56589 topology). This supports interpreting a granular cytoplasmic pattern with peroxisomal membrane localization; it does not identify the epitope recognized by a particular antibody (UniProt P56589 topology; HPA: tissue IHC profile). |
| Antibody evidence | Both listed rabbit polyclonal antibodies have Supported IHC status; one also has Supported ICC status (HPA: HPA042830 and HPA058006 antibody validation). Treat that as support for reported patterns, while keeping the tissue profile's medium staining–RNA consistency in view (HPA: tissue IHC reliability). No catalog antibody dilution or retrieval condition is supplied here. |
| IF/ICC Q&A | Q: What localization should an IF/ICC image support? A: Peroxisomes are supported, while nucleoplasm is uncertain (HPA: subcellular localization). HPA lists ICC-IF images for A-431, U-251MG, and U2OS and Supported ICC status for HPA042830 (HPA: subcellular localization; antibody validation). Interpret IF/ICC on its dedicated guide page. |
| Situation | Likely cause | Next action |
|---|---|---|
| Known positive tissue appears blank. | An assay or specimen issue is possible; kidney tubules and colon glands are reported High (HPA: kidney and colon tissue IHC). | Confirm the positive control, primary antibody step, detection reagents, and counterstain; then review the recorded retrieval and dilution conditions (general IHC practice). No PEX3-specific fixation sensitivity or retrieval setting is established by the supplied sources. |
| Only nuclei stain strongly. | The result diverges from granular cytoplasmic tissue IHC; nucleoplasmic ICC-IF localization is uncertain (HPA: tissue IHC profile; subcellular localization). | Compare with a no-primary control and assess whether cytoplasmic granules are independently visible (general IHC practice). Record nuclear-only staining as unresolved rather than calling it a confirmed PEX3 tissue pattern. |
| Not-detected reference cells stain strongly. | Nonspecific binding or endogenous detection activity may contribute (general IHC practice); compare the exact cell population against HPA's Not detected entries (HPA: tissue IHC). | Review a no-primary control, blocking, and detection controls; score the unexpected cells separately from nearby expected-positive cells (general IHC practice). |
| The section shows uniform haze that obscures granules. | Background from primary binding, blocking, washing, or detection can obscure the reported granular cytoplasmic pattern (general IHC practice; HPA: tissue IHC profile). | Compare with a no-primary control, then review blocking, wash steps, primary concentration, and chromogen development using the assay's recorded conditions (general IHC practice). |
| Signal is weak in a selected Low population. | Low staining is reported for hippocampal and caudate neurons, esophageal and vaginal squamous cells, ovarian follicle cells, and skin keratinocytes (HPA: tissue IHC). | Check a High reference population on a suitable control before treating weak staining as assay failure; score the Low population with the same background threshold (general IHC practice; HPA: tissue IHC cell levels). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | High | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | High | Protein (IHC) | HPA → |
| Colon | Glandular cells | High | Protein (IHC) | HPA → |
| Kidney | Cells in tubules | High | Protein (IHC) | HPA → |
| Nasopharynx | Respiratory epithelial cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Not detected | Protein (IHC) | HPA → |
| Cervix | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Soft tissue | Fibroblasts | Not detected | Protein (IHC) | HPA → |
Troubleshoot PEX3 staining in paraffin section IHC by checking retrieval, staining pattern, controls and scoring against the supplied evidence.
A04166 has real IHC data from paraffin-embedded human uterus (A04166 image caption) and lists human, mouse, and rat reactivity (catalog reactivity). No IF data are listed (catalog IF images).
A04166 lists IHC as an application and human, mouse, and rat reactivity (catalog applications/reactivity). Its IHC figure shows paraffin-embedded human uterus; no IF/ICC application or figure is listed (A04166 image caption; catalog applications/IF images).
Which to pick: For tissue IHC, choose A04166, a rabbit polyclonal antibody listed for IHC with human, mouse, and rat reactivity (catalog host/dilution_raw/applications/reactivity). Its own figure documents paraffin-embedded human uterus, Tris-EDTA pH 9 retrieval, and 1:200 primary antibody overnight at 4°C; the fixative is unreported (A04166 image caption). A04166 is the only listed cross-species option by reactivity, while no SKU has listed IF/ICC validation (catalog reactivity/applications/IF images).