PFDN1 / Prefoldin subunit 1 · IHC design guide

Design Immunohistochemistry for PFDN1

Plan PFDN1 staining in paraffin sections using the catalog antibody at 1:100–1:300 (datasheet A14133-1). Compare cytoplasmic staining in positive cell types against controls, while accounting for the reported low consistency between antibody staining and RNA expression (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for PFDN1 (IHC for PFDN1): expected localisation Mainly cytoplasmic in tissue sections (HPA tissue IHC), antibody A14133-1, validated IHC image, and IHC protocol steps
Printable PFDN1 IHC protocol sheet — expected localisation Mainly cytoplasmic in tissue sections (HPA tissue IHC), antibody A14133-1, controls and protocol steps. Open the full PFDN1 IHC guide →

PFDN1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Mainly cytoplasmic in tissue sections (HPA tissue IHC)
Staining pattern Positive cell types show mainly cytoplasmic staining (HPA tissue IHC)
Antigen retrieval Tris-EDTA pH 9.0 HIER, heat-mediated (datasheet A14133-1)
Positive control ⓘ Cerebral cortex+4 more · see all
Negative control ⓘ None in HPA (detected in all 45 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Staining has low consistency with RNA expression (HPA tissue IHC)
Regulation Low tissue RNA specificity; no regulator reported (HPA tissue RNA)
Isoform / epitope No annotated isoforms; epitope position is unspecified (UniProt)
Section 1

Recommended PFDN1 IHC & IF Protocols

The catalog antibody’s IHC-P protocol is accompanied by one published aortic-valve IHC protocol (PMC12834629).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human tonsil tissue; fixative not specified (datasheet A14133-1)
FixationImage fixative and duration unreported (datasheet A14133-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: Tris-EDTA pH 9.0 (datasheet A14133-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-PFDN1, 1:100-1:300 (datasheet A14133-1)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultPFDN1-positive staining in glial cells of cerebral cortex (HPA tissue IHC: High). HPA tissue profile: Mainly cytoplasmic expression. No signal in the no-primary control.
💡Decision noteStart with heat-mediated Tris-EDTA retrieval at pH 9.0 (datasheet A14133-1). The published aortic-valve protocol does not specify retrieval (PMC12834629).
Section 2

What Is the Expected PFDN1 Staining Pattern?

In paraffin-section IHC, expect mainly cytoplasmic PFDN1 staining, including in glial, glandular, cardiomyocyte, neuronal, trophoblastic and urothelial cells reported as High by HPA (HPA: tissue IHC). UniProt describes a chaperone-associated protein with no transmembrane segment but does not annotate its subcellular location (UniProt O60925). Treat the tissue pattern as provisional: HPA rates the IHC antibody Approved while reporting low agreement with RNA data and pending external verification (HPA: tissue IHC).

What am I looking at on my slide?
Cytoplasmic staining is strongest in the expected cells within a reference section.This fits HPA's mainly cytoplasmic IHC profile. High staining is reported in cerebral-cortex glia, heart cardiomyocytes and placental trophoblasts, among other listed cells (HPA: tissue IHC). Compare cell populations within the section; HPA's Approved rating does not make every cell or specimen uniformly positive (HPA: tissue IHC reliability).
A crisp membrane rim or nucleolar signal dominates the chromogenic IHC image.Recheck the compartment call before accepting it as PFDN1. HPA tissue IHC describes mainly cytoplasmic staining, whereas its separate ICC-IF record approves plasma-membrane and cytosolic locations and labels nucleoli uncertain (HPA: tissue IHC; HPA: subcellular ICC-IF). The ICC-IF observation does not establish a dominant membrane or nucleolar IHC pattern.
The strongest deposit lies in a cell population outside the reported pattern.Possible explanations include cross-reactivity or endogenous detection activity; morphology and controls must distinguish them (general IHC practice). HPA's cell-level observations are references, not an exhaustive list of permissible positive cells, and its antibody assessment remains pending external verification (HPA: tissue IHC reliability).
Color spreads across stroma, lumina or most cells without clear intracellular boundaries.Treat this as background until controls support specificity. In chromogenic IHC, incomplete blocking, excessive detection signal or endogenous enzyme activity can obscure cellular staining (general IHC practice). Diffuse deposit alone cannot establish the mainly cytoplasmic PFDN1 pattern reported in tissue (HPA: tissue IHC).
No convincing signal appears in a section containing a reported High-staining cell type.Check tissue identity, preservation and assay controls before calling PFDN1 absent (general IHC practice). HPA reports High staining in specified cells, such as endometrial and thyroid glandular cells, but its low RNA–staining consistency limits how strongly one negative section can be interpreted (HPA: tissue IHC).
💡Expected PFDN1 appearanceA positive chromogenic result is predominantly cytoplasmic in the specified HPA High-staining cells; conspicuous diffuse deposit or staining confined to an unexpected population needs control-based review (HPA: tissue IHC; general IHC practice).
How each factor affects the staining
Which tissue and cells are being scored?HPA reports High staining in selected cell populations across eight listed tissues and Low staining in selected populations across six others; it lists no negative tissue here (HPA: tissue IHC). Score the named cells, since a whole-section positive/negative label would discard that distinction.
How firm is the tissue reference?The available antibody is IHC Approved, yet HPA reports low consistency between staining and RNA expression and says external verification is pending (HPA: tissue IHC). Use the reported pattern as a comparison point and interpret an isolated discrepancy cautiously.
Does topology require membrane-only staining?No transmembrane segment is annotated, and UniProt describes transfer of target proteins to cytosolic chaperonin (UniProt O60925). Neither fact establishes an IHC epitope location or overrides HPA's mainly cytoplasmic tissue observation (HPA: tissue IHC).
IF/ICC Q&A: should its membrane signal set the IHC scoring rule?No. HPA approves plasma-membrane and cytosolic ICC-IF localisation, with nucleoli marked uncertain (HPA: subcellular ICC-IF). Use the tissue IHC profile for chromogenic section scoring; IF/ICC has a separate guide page (HPA: tissue IHC).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
A reported High-staining cell population is blank.The stain may have failed, or the sampled cells may not match the HPA reference; HPA's tissue pattern has limited RNA agreement (HPA: tissue IHC).Confirm cell identity and tissue integrity, then review the run's positive control, reagent delivery and detection steps before interpreting absence (general IHC practice).
The slide shows a dominant membrane outline.This differs from HPA's mainly cytoplasmic tissue IHC profile, although membrane localisation is approved in its ICC-IF record (HPA: tissue IHC; HPA: subcellular ICC-IF).Inspect the staining at cell level and compare appropriate controls; record the compartment separately from the tissue IHC reference rather than treating the IF finding as an IHC validation (general IHC practice).
Nucleoli appear more prominent than cytoplasm.HPA marks nucleolar ICC-IF localisation uncertain, and its tissue IHC profile is mainly cytoplasmic (HPA: subcellular ICC-IF; HPA: tissue IHC).Check the counterstain and omission control, then score any convincing cytoplasmic signal separately from the nucleolar appearance (general IHC practice).
Stroma or lumina carry widespread chromogen.Background from detection reagents or endogenous enzyme activity can reduce contrast between cells (general IHC practice).Inspect a primary-antibody omission control and review blocking, washes and chromogen development; accept a positive call only where cell boundaries and localisation remain interpretable (general IHC practice).
An unexpected cell type stains more strongly than the listed cells.Cross-reactivity or endogenous detection activity is possible; HPA's listed cell patterns do not establish the identity of every positive signal (HPA: tissue IHC; general IHC practice).Compare the unexpected cells with an omission control and a reported High-staining cell population in the same run, then document the difference without assigning specificity from color alone (general IHC practice; HPA: tissue IHC).
Two sections show different staining strengths.The sections may contain different proportions of the cell types HPA scored, and its IHC assessment reports low RNA–staining consistency (HPA: tissue IHC).Compare the same identified cell type at matched scoring settings and review run controls before attributing the difference to PFDN1 abundance (general IHC practice).

Sample controls for PFDN1 IHC & IF

🧪Run endometrium first and confirm staining in glandular cells (HPA: High in endometrial glandular cells). HPA detects PFDN1 in all 45 scored tissues, so there is no supported negative tissue; use no-primary and isotype controls, and treat cells without signal on the positive slide as internal background references only, not established PFDN1-negative cells (HPA: no negative rows).
Positive control tissue: Cerebral cortex (Glial cells, HPA High)
Negative control tissue: None in HPA: PFDN1 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show PFDN1 in A-431, U-251MG, U2OS, with annotated localisation: Plasma membrane (approved), Cytosol (approved) (HPA subcellular).
Technical controls: Run a no-primary (secondary-only) control and an isotype control matched to the primary antibody’s host species, immunoglobulin class and clonality; use validated PFDN1 knockout material as a biological negative, or peptide competition if the immunizing peptide is available (standard IHC practice). Check endogenous peroxidase background, especially in any blood-containing areas of the endometrial section (standard chromogenic IHC practice).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported in the supplied evidence, and the selected paraffin-section caption does not state its fixative (selected-SKU tissue-IHC caption: fixative unreported). The catalog example uses Tris-EDTA at pH 9.0 for retrieval and a 1:200 primary antibody dilution overnight at 4 °C; this gives a starting condition, but does not establish retrieval dependency (selected-SKU tissue-IHC caption). HPA has ICC-IF images in A-431, U-251MG and U2OS, but the supplied evidence does not establish that frozen sections or IF are easier than paraffin IHC; blood-associated peroxidase background is a practical consideration for endometrial chromogenic staining (HPA: ICC-IF image cell lines; standard chromogenic IHC practice).

HPA tissue IHC evidence for PFDN1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Cerebral cortex Glial cells High Protein (IHC) HPA →
Endometrium Glandular cells High Protein (IHC) HPA →
Heart muscle Cardiomyocytes High Protein (IHC) HPA →
Hippocampus Neuronal cells High Protein (IHC) HPA →
Placenta Trophoblastic cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: PFDN1 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced PFDN1 IHC Tips

Troubleshoot PFDN1 staining in paraffin sections using the catalog antibody’s tissue IHC conditions and compartment specific controls.

Which retrieval condition should I start with for PFDN1 in paraffin sections?
Start with heat-mediated Tris-EDTA at pH 9.0 for PFDN1 paraffin-section IHC (datasheet A14133-1). The catalog antibody’s human tonsil image used that buffer, followed by primary antibody at 1:200 overnight at 4°C (caption A14133-1). If signal is weak, check heating consistency, cooling, and section adhesion before changing retrieval conditions (standard IHC practice). Compare adjacent sections with identical detection and counterstaining so retrieval is the only variable (standard IHC practice). Excessively intense retrieval can damage morphology or raise nonspecific staining, so judge signal alongside preserved tissue structure (standard IHC practice).
Could fixation explain weak or uneven PFDN1 staining?
PFDN1-specific fixation sensitivity is unknown: the catalog antibody’s paraffin tonsil caption does not state a fixative (caption A14133-1). Record fixative, duration, tissue thickness, and processing history for every section before comparing staining intensity (standard IHC practice). For a controlled trial, process matched samples after documented fixation in 10% neutral buffered formalin, keeping all later steps identical (standard IHC practice). Compare a small range of fixation times appropriate to the specimen rather than assigning weak signal to a PFDN1-specific fixation effect (standard IHC practice). Use matched morphology and retrieval controls to distinguish processing variation from staining variation (standard IHC practice).
Where should PFDN1 staining appear in tissue sections?
Expect mainly cytoplasmic tissue staining when assessing PFDN1 chromogenic IHC (HPA tissue IHC: mainly cytoplasmic expression). Cell-based imaging also supports cytosol and plasma membrane localisation, while nucleolar localisation is uncertain (HPA subcellular: approved cytosol and plasma membrane; uncertain nucleoli). PFDN1 has no annotated transmembrane segment, so a membrane outline alone should not establish antibody specificity (UniProt O60925 topology). Score cytoplasmic and apparent membrane signal separately, with a consistent threshold across sections (standard IHC practice). Investigate isolated, intense nuclear or nucleolar deposits with controls before calling them biological localisation (HPA subcellular: uncertain nucleoli; standard IHC practice).
How should an unknown epitope affect PFDN1 antibody troubleshooting?
The supplied PFDN1 record lists 0 annotated isoforms and a processed chain spanning residues 2–122 (UniProt O60925 isoforms and processing). It also records N-acetylalanine at residue 2, but does not identify this antibody’s epitope (UniProt O60925 modified residues; caption A14133-1). Check the antibody’s immunogen or epitope documentation before attributing absent staining to an isoform or blocked terminus (standard IHC practice). If that information is unavailable, compare retrieval and antibody dilution on adjacent sections while holding detection constant (standard IHC practice). Avoid interpreting a changed staining pattern as epitope accessibility without an independent specificity control (standard IHC practice).
How can IF help assess the PFDN1 IHC localisation pattern?
Use IF/ICC as a separate localisation check, with a marker for the expected cell type in the chosen specimen; glial cells in cerebral cortex are one documented PFDN1-high example (HPA tissue IHC: high in glial cells). Choose a fluorophore channel after inspecting unstained tissue autofluorescence, and include single-label controls for multiplexing (standard IF practice). For a cytosolic epitope, use controlled permeabilisation; for an exposed membrane-side epitope, test whether detergent obscures the membrane outline (HPA subcellular: cytosol and plasma membrane; standard IF practice). Interpret nucleolar signal cautiously because that additional location is uncertain (HPA subcellular: uncertain nucleoli). Establish IF antibody conditions independently of the paraffin IHC caption (caption A14133-1; standard IF practice).
What should I check when PFDN1 DAB staining looks diffuse?
Compare a no-primary control and an appropriate secondary-only control to locate background from the detection system (standard IHC practice). Block endogenous peroxidase before DAB development and verify that the block works in the specimen being stained (standard IHC practice). Titrate the catalog antibody around its illustrated 1:200 primary dilution while keeping retrieval and development time constant (caption A14133-1; standard IHC practice). Check whether diffuse color follows section edges, folds, or damaged tissue rather than intact cell boundaries (standard IHC practice). Retain a modest counterstain so cytoplasmic signal can be distinguished from precipitate and tissue pigment (HPA tissue IHC: mainly cytoplasmic; standard IHC practice).
How should I quantify PFDN1 staining across tissue samples? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and viable tissue area before scoring, then apply the same rules to every section (standard IHC practice). For cytoplasmic PFDN1, an H-score combines percentages at intensity grades 0–3 into a 0–300 score (HPA tissue IHC: mainly cytoplasmic; standard IHC practice). Alternatively report the percentage of positive cells or positive-cell density per mm², stating the threshold and compartment used (standard IHC practice). Normalise cell counts to the number of eligible cells or measured viable area, and exclude folds and necrosis consistently (standard IHC practice). Keep retrieval, antibody dilution, DAB development, imaging, and observer criteria matched across groups (standard IHC practice).
How can I distinguish credible PFDN1 signal from artefact?
Favor staining in intact cell cytoplasm that is reproducible across sections and absent from no-primary controls (HPA tissue IHC: mainly cytoplasmic; standard IHC practice). High staining in cerebral-cortex glial cells or endometrial glandular cells is compatible with the reported tissue pattern, but does not alone prove specificity (HPA tissue IHC: high in those cells). Treat signal confined to section edges, necrosis, or unexpected nuclear deposits as needing further controls (standard IHC practice; HPA subcellular: nucleoli uncertain). Exclude endogenous enzyme activity with a peroxidase-block control before interpreting DAB deposits (standard IHC practice). Interpret intensity cautiously because the HPA tissue IHC profile has low agreement with RNA expression and awaits external verification (HPA tissue IHC reliability description).
Boster reagents

Best PFDN1 / Prefoldin subunit 1 IHC Antibodies

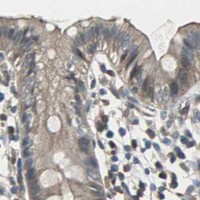
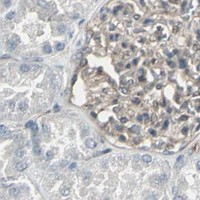
A14133-1 is listed for human and mouse IHC and IF (catalog: applications and reactivity). Its supplied image shows IHC in a human paraffin-embedded tonsil section; no IF image is supplied (catalog: image captions).

Real IHC data Immunohistochemical analysis of paraffin-embedded human tonsil. 1, Antibody was diluted at 1:200 (4° overnight). 2, Tris-EDTA, pH9.0 was used for antigen retrieval. 3, Secondary antibody was diluted at 1:200 (room temperature, 30min).
Anti-Prefoldin 1 PFDN1 Antibody
Cat # A14133-1

A14133-1 will render with its human paraffin-embedded tonsil IHC image (A14133-1 image caption). The catalog lists IHC and IF applications and human and mouse reactivity, but supplies no IF image or mouse tissue image (catalog: applications, reactivity, image captions).

Which to pick: For tissue IHC, choose A14133-1: its own caption documents a paraffin-embedded human tonsil section, 1:200 primary antibody overnight at 4°C, and Tris-EDTA retrieval at pH 9.0; the fixative is unreported (A14133-1 image caption). For IF, A14133-1 is catalog-listed at 1:50, but no IF image or ICC validation is supplied; its host is rabbit and clonality is unreported (catalog: IF dilution, image captions, host, clone). For human or mouse samples, A14133-1 is the only listed choice, with mouse support limited to catalog reactivity (catalog: reactivity; A14133-1 image caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry O60925 (PFD1_HUMAN, Prefoldin subunit 1).
  2. Human Protein Atlas. PFDN1 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. PFDN1 subcellular location (ICC-IF): Mainly localized to the plasma membrane and cytosol. In addition localized to the nucleoli..
  4. Human Protein Atlas. PFDN1 antibody validation summary (1 antibodies).
  5. PFND1 Predicts Poor Prognosis of Gastric Cancer and Promotes Cell Metastasis by Activating the Wnt/β-Catenin Pathway. OncoTargets and therapy 2020 — PMC7170631.
  6. Overexpression of Canonical Prefoldin Associates with the Risk of Mortality and Metastasis in Non-Small Cell Lung Cancer. Cancers 2020 — PMC7225921.
  7. Characterization of Proteome Features in Patients With Aortic Stenosis Using Data-Independent Acquisition-Based Proteomic Analysis. Korean circulation journal 2026 — PMC12834629.
  8. PubMed PMID:9630229 — UniProt-cited evidence.
  9. PubMed PMID:14702039 — UniProt-cited evidence.
  10. PubMed PMID:15489334 — UniProt-cited evidence.