This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan PI16 chromogenic IHC in paraffin sections around extracellular staining, mainly in prostate, urinary bladder and testis (HPA tissue IHC). Start with the IHC-validated antibody at 2–5 μg/ml (datasheet A09887-1), and interpret cellular staining in light of PI16 secretion (UniProt).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Extracellular staining in tissues (HPA tissue IHC) | |
| Staining pattern | Extracellular signal mainly in prostate, bladder and testis (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet A09887-1) | |
| Positive control | Fallopian tube+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A09887-1) | |
| Caveat | Secreted PI16 may stain away from producing cells (HPA tissue IHC) | |
| Regulation | Staining varies across tissues (HPA tissue IHC) | |
| Isoform / epitope | Two isoforms; epitope coverage is unspecified (UniProt) |
The catalog antibody’s IHC-P protocol is accompanied by two published chromogenic PI16 protocols for paraffin sections (PMC7541153; PMC7616500).
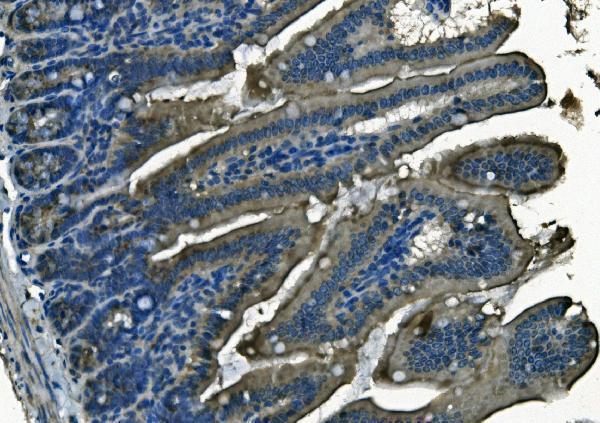
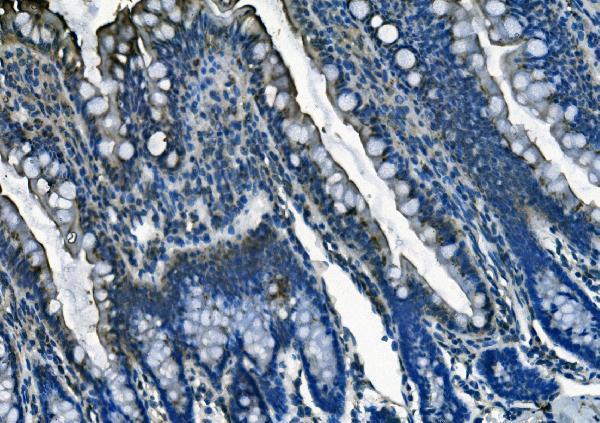
| Sample | Paraffin-embedded mouse intestine tissue; fixative not specified (datasheet A09887-1) |
| Fixation | Image fixative and duration unreported (datasheet A09887-1); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet A09887-1); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet A09887-1) |
| Primary antibody | Rabbit anti-PI16, 2-5μg/ml (datasheet A09887-1) |
| Primary incubation | Overnight at 4 °C (datasheet A09887-1) |
| Detection | Streptavidin-biotin complex (SABC), DAB chromogen (datasheet A09887-1) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | PI16-positive staining in ciliated cells (ciliary rootlets) of fallopian tube (HPA tissue IHC: High). HPA tissue profile: Extracellular positivity in several tissues, mainly in prostate, urinary bladder and testis. Additional cytoplasmic or membranous expression in a few tissues including retina. No signal in the no-primary control. |
PI16 is secreted and has no transmembrane segment (UniProt Q6UXB8 topology). In paraffin sections, expect mainly extracellular staining, particularly in prostate, urinary bladder and testis (HPA: Approved tissue IHC). HPA also records staining at ciliary rootlets in fallopian tube cells and in testis peritubular cells (HPA: High and Medium, respectively). Interpret cell boundaries cautiously because secreted protein can appear away from its producing cells (HPA: reliability description).
| Extracellular signal in prostate, urinary bladder or testis, with tissue structures still discernible. | This fits the predominant reported distribution (HPA: Approved tissue IHC). Extracellular deposits need not identify the cells that produced PI16: it is secreted, and HPA warns that RNA and protein locations may differ (UniProt Q6UXB8; HPA: reliability description). |
| Strong staining at fallopian tube ciliary rootlets, or moderate staining of testis peritubular cells. | These are specifically annotated positives (HPA: High in fallopian tube ciliated-cell rootlets; Medium in testis peritubular cells). Do not dismiss every cell-associated signal as artefact: HPA also reports limited cytoplasmic or membranous staining in some tissues (HPA: tissue profile). |
| Dominant nuclear staining, especially where the expected extracellular or rootlet pattern is absent. | A nuclear pattern is outside the reported PI16 locations (UniProt Q6UXB8: secreted; HPA: tissue and subcellular profiles). Treat it as suspect and review negative controls, counterstain, and whether the apparent signal follows recognizable tissue structures (general IHC practice). |
| Prominent staining in cells annotated as negative, such as bone-marrow hematopoietic cells or adipocytes. | That conflicts with these specific HPA annotations (HPA: Not detected in bone-marrow hematopoietic cells and adipocytes). Check for cross-reactivity or endogenous detection activity before assigning PI16 expression; an annotated negative cell population does not establish that its entire tissue is PI16-free (general IHC practice; HPA: tissue annotations). |
| Diffuse brown haze across positive and negative areas, or no signal in a known-positive structure. | Neither pattern alone establishes PI16 distribution. Haze may reflect background from blocking, detection or counterstain; absent signal may reflect a failed staining run (general IHC practice). Compare a positive structure and an annotated negative cell population on the same run before interpreting biology (HPA: tissue annotations). |
| Secretion and processing | PI16 has a signal peptide at residues 1–27 and a mature chain at 28–463, with no transmembrane segment (UniProt Q6UXB8). Extracellular staining can therefore extend beyond a producing cell; cell-associated exceptions must be judged against the HPA images (HPA: tissue profile). |
| Antibody validation | The listed antibody, HPA076574, is Approved for IHC; the supplied record does not mark it Enhanced (HPA: antibody record). Use its reported pattern as a comparison, while treating unexpected staining as a finding to verify rather than confirmed PI16 (HPA: tissue IHC). |
| Regional variation | HPA reports High fallopian tube rootlet staining, Medium testis peritubular staining, and Low staining in several glandular or tubular populations (HPA: tissue IHC). Score the named cell or structure, rather than assigning one intensity to the whole organ (HPA: tissue annotations). |
| Processing, variants and epitope | UniProt lists 2 isoforms and glycosylation sites at 114, 403 and 409 (UniProt Q6UXB8). The supplied sources give no antibody epitope or PI16-specific antigen-retrieval result; they cannot predict which variant or processed form this stain detects. |
| IF/ICC: what pattern is established? | HPA summarizes PI16 as membrane-associated and secreted but supplies no ICC-IF image or main-location annotation (HPA: subcellular record). An IF/ICC pattern therefore cannot be confirmed from this record; assess that application using its separate guide (HPA: subcellular record). |
| Situation | Likely cause | Next action |
|---|---|---|
| No staining at a fallopian tube ciliary-rootlet positive control. | The expected High structure is missing (HPA: fallopian tube tissue IHC); the run or tissue preparation may need review (general IHC practice). | Confirm the section contains identifiable ciliated rootlets, then review the IHC antibody and detection steps against the run controls (HPA: fallopian tube annotation; general IHC practice). |
| Prostate or testis shows little extracellular signal, but some cells stain. | Cellular signal alone may not reproduce the predominant extracellular profile (HPA: tissue IHC); secreted PI16 can be spatially separated from producing cells (UniProt Q6UXB8; HPA: reliability description). | Examine preserved extracellular structures and compare the same run with an annotated positive structure; do not infer production from a stained cell alone (HPA: tissue IHC; general IHC practice). |
| Brown staining is widespread, including annotated negative cells. | This may reflect nonspecific binding or endogenous detection activity (general IHC practice); HPA lists adipocytes and bone-marrow hematopoietic cells as Not detected (HPA: tissue IHC). | Review appropriate reagent-omission and detection controls, blocking, and wash steps; reassess whether signal tracks the HPA-described compartments (general IHC practice; HPA: tissue profile). |
| A strong nuclear pattern dominates the section. | That compartment does not match the secreted PI16 annotation or HPA's reported tissue pattern (UniProt Q6UXB8; HPA: tissue and subcellular profiles). | Check counterstain and detection controls, then compare the pattern with positive and annotated negative structures before scoring it as PI16 (general IHC practice; HPA: tissue annotations). |
| A low-staining glandular population appears negative. | A weak expected signal can be hard to distinguish from the run background (general IHC practice); HPA rates endometrial glandular cells Low (HPA: endometrium tissue IHC). | First verify a stronger annotated positive in the run; score the glandular population only when localized signal is distinguishable from background (HPA: tissue IHC; general IHC practice). |
| Changing antigen retrieval seems to change the result. | The supplied UniProt and HPA records do not establish PI16-specific retrieval or fixation sensitivity; a change in staining alone cannot identify its mechanism. | Compare retrieval conditions with matched positive and negative controls and preserved morphology, and report the condition used without attributing the difference to PI16 epitope masking (general IHC practice). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — At least one protein variant secreted, tissue location of RNA and protein might differ and correlation is complex. Antibody staining in cells/structures not annotated, view images.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Fallopian tube | Ciliated cells (ciliary rootlets) | High | Protein (IHC) | HPA → |
| Bronchus | Ciliated cells (ciliary rootlets) | Medium | Protein (IHC) | HPA → |
| Endometrium | Glandular cells | Low | Protein (IHC) | HPA → |
| Epididymis | Glandular cells | Medium | Protein (IHC) | HPA → |
| Retina | Nerve fiber layer | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Appendix | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Not detected | Protein (IHC) | HPA → |
| Caudate | Glial cells | Not detected | Protein (IHC) | HPA → |
| Cerebellum | Cells in granular layer | Not detected | Protein (IHC) | HPA → |
Use compartment, tissue context and matched controls to troubleshoot PI16 staining in paraffin sections; the antibody’s tissue caption does not identify a fixative.
The catalog includes one anti-PI16 antibody with IHC images from paraffin sections of mouse and rat intestine and human bladder and pancreatic cancer tissue (catalog IHC captions).
A09887-1 is listed for IHC and reactivity with human, mouse, rat and monkey (catalog applications; catalog reactivity). Its images document IHC in mouse and rat intestine and human bladder and pancreatic cancer paraffin sections; no IF image is supplied (catalog IHC captions; catalog IF images).
Which to pick: For tissue IHC, choose A09887-1 for the paraffin-section samples documented in its own captions; the fixative is unreported (catalog IHC captions). No listed SKU has IF/ICC validation or an IF image (catalog applications; catalog IF images). For cross-species IHC, A09887-1 has documented human, mouse and rat IHC examples; monkey is listed as reactive but has no monkey IHC image (catalog IHC captions; catalog reactivity).