This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic PLK2 IHC on paraffin sections using the catalog antibody at 0.5–1 μg/mL (datasheet A02881). Assess cytoplasmic staining in glandular cells and account for its low consistency with RNA expression (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Predominantly cytoplasmic in tissue (HPA tissue IHC) | |
| Staining pattern | Cytoplasmic in most tissues; high in glandular cells (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6 HIER, heat-mediated (datasheet A02881) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | None in HPA (detected in all 45 tissues); use no-primary + isotype controls |
| Fixation | Keep fixation consistent (standard IHC practice; not target-specific); Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A02881) | |
| Caveat | Staining has low consistency with RNA expression (HPA tissue IHC) | |
| Regulation | p53 induction suggests a stress response (UniProt) | |
| Isoform / epitope | 2 isoforms; confirm epitope coverage (UniProt) |
The catalog antibody’s IHC-P protocol (datasheet A02881) is accompanied by four published PLK2 IHC protocols (PMC7300400; PMC12460256; PMC5487358; PMC7504392).
| Sample | Paraffin-embedded human tonsil tissues; fixative not specified (datasheet A02881) |
| Fixation | Image fixative and duration unreported (datasheet A02881); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: Citrate pH 6, 20 min (datasheet A02881) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet A02881) |
| Primary antibody | Rabbit anti-PLK2, 0.5-1μg/ml (datasheet A02881) |
| Primary incubation | Overnight at 4 °C (datasheet A02881) |
| Detection | Streptavidin-biotin complex (SABC), DAB chromogen (datasheet A02881) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | PLK2-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in most tissues. No signal in the no-primary control. |
PLK2 staining in paraffin sections is expected mainly in the cytoplasm of glandular, respiratory epithelial and neuronal cells, depending on tissue (HPA: cytoplasmic expression in most tissues; HPA: High in the listed cells). Centrosomal or dendritic localization is biologically plausible (UniProt Q9NYY3: subcellular location). PLK2 has no transmembrane segment (UniProt Q9NYY3: topology). Interpret staining cautiously: HPA rates tissue IHC Approved but reports low consistency with RNA expression (HPA: reliability).
| Cytoplasmic staining in colon glandular cells or bronchial respiratory epithelial cells. | This matches reported high staining in those cells (HPA: High in colon glandular cells; HPA: High in bronchial respiratory epithelial cells). Judge intensity against neighboring cells and the no-primary control (general IHC practice). |
| Predominantly nuclear staining in a paraffin section, with little cytoplasmic signal. | This differs from the reported tissue IHC profile and warrants review of controls (HPA: cytoplasmic expression in most tissues). Nuclear signal alone is not proof of an artefact: ICC-IF also reports approved nucleoplasmic localization (HPA: subcellular location). |
| Strong staining in a cell population outside the reported high-staining populations. | Check whether the signal follows tissue structure and survives control review; cross-reactivity or endogenous chromogenic activity is possible (general IHC practice). HPA reports low tissue specificity, so an unlisted cell type cannot be declared PLK2-negative (HPA: RNA specificity). |
| Uniform haze across cells, extracellular space and blank regions. | A pattern without cell boundaries is difficult to assign to PLK2 (general IHC practice). Review no-primary staining, blocking, washing and detection conditions before interpreting intensity; HPA's cytoplasmic profile does not validate diffuse background (HPA: tissue IHC profile). |
| No staining in colon glandular cells or cerebellar Purkinje cells. | Those cells are reported High, so absent signal calls for a check of section quality, retrieval, antibody and detection workflow (HPA: High in colon glandular cells; HPA: High in Purkinje cells; general IHC practice). It does not alone establish absent PLK2 expression. |
| Tissue and cell context | High staining is reported in several glandular populations, bronchial respiratory epithelium and selected neurons; adipocytes and chondrocytes are reported Low (HPA: tissue IHC). These are comparison points, not universal positive or negative controls. |
| Subcellular context | UniProt places PLK2 in cytoplasm, centrosomes, centrioles and dendrites (UniProt Q9NYY3: subcellular location). Its centrosomal distribution changes from early G1 to S phase (UniProt Q9NYY3); routine chromogenic IHC may not resolve individual centrioles (general IHC practice). |
| Protein form and topology | PLK2 has two reported isoforms and a 1–685 amino-acid chain, with no signal peptide, propeptide or transmembrane segment (UniProt Q9NYY3: isoforms, processing and topology). The payload does not identify the catalog antibody's epitope, so isoform coverage cannot be assigned. |
| Strength of IHC evidence | HPA calls tissue IHC Approved while noting low consistency between staining and RNA expression; CAB009624 is IHC Approved, whereas HPA069329 has no listed IHC status (HPA: reliability; HPA: antibodies). Approval does not settle every discordant cell-level result. |
| IF/ICC question: should its pattern match paraffin IHC? | Not necessarily. ICC-IF reports approved nucleoplasm, mitochondria and cytosol locations (HPA: subcellular location), while tissue IHC is described as mainly cytoplasmic (HPA: tissue IHC profile). Compare compartments within each application and its controls (general IHC practice). |
| Antigen retrieval and fixation | Retrieval conditions can affect paraffin IHC generally (general IHC practice). No source here reports PLK2-specific fixation sensitivity or an epitope-specific retrieval requirement; do not attribute a weak or absent PLK2 result to either without controlled comparison. |
| Situation | Likely cause | Next action |
|---|---|---|
| A reported High population has no signal. | The section, antibody incubation, retrieval or detection may have failed (general IHC practice); a single negative section does not overturn the reported High pattern (HPA: tissue IHC). | Run a reported High tissue alongside the sample, inspect tissue preservation and verify each detection step (HPA: tissue IHC; general IHC practice). Optimize retrieval empirically; no PLK2-specific setting is supplied. |
| Nuclear staining dominates the paraffin section. | This diverges from HPA's mainly cytoplasmic tissue profile, although nucleoplasm is an approved ICC-IF location (HPA: tissue IHC; HPA: subcellular location). | Review the no-primary control and the distribution across cell types; report nuclear and cytoplasmic signals separately (general IHC practice). Avoid calling nuclear signal either confirmed PLK2 or artefact from compartment alone. |
| Strong signal appears in an unexpected cell population. | Cross-reactivity or endogenous detection activity is possible (general IHC practice). Low tissue RNA specificity also limits claims that unlisted cells must be negative (HPA: RNA specificity). | Check morphology and no-primary staining, then compare with a reported High cell population in the same run (general IHC practice; HPA: tissue IHC). Record the discordant population without assigning identity from stain alone. |
| Diffuse stain obscures cell boundaries. | Background from nonspecific binding, insufficient washing or detection chemistry can obscure localization (general IHC practice). This cannot be equated with HPA's cytoplasmic profile (HPA: tissue IHC). | Inspect no-primary and reagent controls; review blocking, washing and detection exposure as general workflow variables (general IHC practice). Reassess only where cytoplasm can be distinguished from extracellular background. |
| Chromogen develops in a no-primary section. | Primary-antibody-independent detection, including endogenous activity, can produce signal (general IHC practice). Its presence cannot support a PLK2-specific call. | Identify the detection chemistry and use its appropriate endogenous-activity control; adjust blocking or detection conditions as needed (general IHC practice). Re-evaluate sample staining after control signal is resolved. |
| A high-intensity tissue shows little discernible centrosomal puncta. | HPA describes broad cytoplasmic tissue staining, while UniProt's centrosomal localization is subcellular and cell-cycle dependent (HPA: tissue IHC; UniProt Q9NYY3: subcellular location). | Score the supported cell-type and cytoplasmic pattern first (HPA: tissue IHC). Do not require resolved centrioles for a positive chromogenic section; optical resolution and section plane limit puncta assessment (general IHC practice). |

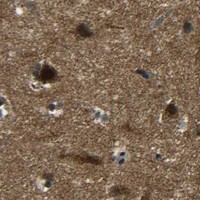
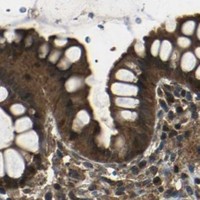


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | High | Protein (IHC) | HPA → |
| Appendix | Glandular cells | High | Protein (IHC) | HPA → |
| Breast | Glandular cells | High | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | High | Protein (IHC) | HPA → |
| Cerebellum | Purkinje cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| None in HPA: PLK2 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead. | ||||
Troubleshoot PLK2 staining in paraffin sections by checking retrieval, compartment, controls and cell-level scoring before interpreting chromogenic signal.
Two anti-PLK2 antibodies have paraffin-section IHC images from human tonsil, human lung cancer, and rat intestine and brain; PA2131 also has a chromogenic ICC image from A549 cells (catalog image captions).
A02881 has a paraffin-section IHC image from human tonsil (A02881 IHC caption). PA2131 has paraffin-section IHC images from human lung cancer, rat intestine, and rat brain, plus a DAB-based ICC image from A549 cells (PA2131 image captions).
Which to pick: For tissue IHC, choose A02881 for its human tonsil example or PA2131 for its human and rat tissue examples; neither IHC caption reports the fixative (each SKU’s IHC caption). For ICC, PA2131 lists that application and shows a chromogenic A549 example; fluorescent IF validation is unreported (PA2131 applications and ICC caption). For cross-species IHC, PA2131 has human and rat tissue images; both antibodies list human, mouse, and rat reactivity, but neither has a mouse IHC image in this payload (catalog reactivity; each SKU’s IHC captions).