This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan PRCP staining in paraffin sections around the granular cytoplasmic pattern observed in tissues (HPA tissue IHC). Kidney tubules offer a high-staining reference (HPA tissue IHC), but staining intensity needs cautious interpretation because antibody staining and RNA expression show low consistency (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Granular cytoplasm observed (HPA tissue IHC); lysosome expected (UniProt) | |
| Staining pattern | Granular cytoplasm in most tissues; high in kidney tubules (HPA tissue IHC) | |
| Antigen retrieval | Tris-EDTA pH 9.0 HIER, heat-mediated (datasheet A04829-1) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep fixation consistent across sections (standard IHC practice; not target-specific) | |
| Caveat | Staining and RNA show low consistency; verify independently (HPA tissue IHC) | |
| Regulation | Staining-linked regulation unspecified (UniProt) | |
| Isoform / epitope | 2 isoforms; mature chain 46–496; epitope map unknown (UniProt) |
The catalog antibody IHC-P protocol is followed by published PRCP staining protocols from three articles (PMC6180013; PMC5567309; PMC9639567).
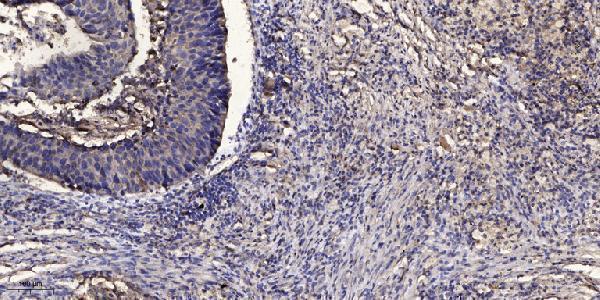
| Sample | Paraffin-embedded human Squamous cell carcinoma of lung tissue; fixative not specified (datasheet A04829-1) |
| Fixation | Image fixative and duration unreported (datasheet A04829-1); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: Tris-EDTA pH 9.0 (datasheet A04829-1); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-PRCP, 1:50 recommended; image 1:200 (datasheet A04829-1) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | PRCP-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression with a granular pattern in most tissues. No signal in the no-primary control. |
PRCP is a lysosomal protein with no transmembrane segment (UniProt P42785). In paraffin tissue sections, expect granular cytoplasmic staining, especially in adrenal glandular cells, kidney tubule cells, splenic red pulp cells and cerebellar molecular-layer cells (HPA: High in each; granular cytoplasmic pattern in most tissues). Interpret intensity cautiously: HPA rates the tissue IHC profile Approved but reports low agreement with RNA expression and pending external verification (HPA: reliability description).
| Granular cytoplasmic signal in kidney tubule cells or adrenal glandular cells. | This fits the reported distribution (HPA: High in both cell populations; granular cytoplasmic pattern). Score the specified cells and their intracellular pattern together; staining anywhere in a positive tissue alone does not establish specificity (standard IHC practice). |
| Predominantly nuclear, sharply membranous or uniform extracellular staining. | These compartments do not match the expected granular cytoplasm (HPA: tissue IHC profile) or lysosomal localisation (UniProt P42785). Treat an isolated wrong-compartment signal as suspect; review controls and antibody localisation before calling it PRCP (standard IHC practice). |
| Strong staining in adipocytes, bronchial respiratory epithelium or bone-marrow hematopoietic cells. | Those specific populations are reported as Not detected (HPA: tissue IHC). Check morphology and controls; staining may reflect cross-reactivity or chromogenic detection background rather than demonstrated PRCP expression (standard IHC practice). |
| Diffuse colour across cells and surrounding tissue, with little cell-specific granularity. | That appearance obscures the reported granular cytoplasmic pattern (HPA: tissue IHC profile). Compare a no-primary control and review blocking, washing and chromogen development; these are general IHC background checks, not documented PRCP-specific effects (standard IHC practice). |
| No signal in an otherwise interpretable kidney tubule or adrenal glandular positive control. | Both cell populations are reported High (HPA: tissue IHC), so absence raises a technical concern. Check that the control tissue contains the relevant cells and that primary antibody, retrieval and detection steps worked (standard IHC practice); HPA does not establish PRCP-specific fixation sensitivity. |
| Cell population and reference intensity | Use cell-level comparators: kidney tubules, adrenal glandular cells, splenic red pulp cells and cerebellar molecular-layer cells are High; breast myoepithelial cells and cortical glia are Medium (HPA: tissue IHC). A low or negative call for one cell population cannot be generalized to every cell in its tissue. |
| IHC evidence strength | The tissue profile is Approved, while agreement between staining and RNA is low and external verification is pending (HPA: reliability description). One antibody has IHC Approved status; the separate ICC antibody has ICC Supported status (HPA: antibody validation). Interpret unexpected strong staining with independent controls. |
| Processing and epitope position | PRCP has a signal peptide at residues 1–21, a propeptide at 22–45 and a mature chain at 46–496 (UniProt P42785). If the catalog antibody's epitope is known, compare its position with these regions; the supplied record gives no epitope, so it cannot predict that antibody's staining of processed protein. |
| IF/ICC Q&A: what localisation is expected? | Supported vesicular staining is reported in U2OS ICC-IF images (HPA: subcellular profile). That supports an intracellular punctate interpretation alongside UniProt's lysosomal annotation (UniProt P42785); it does not establish that every fluorescent punctum is a lysosome or supply an IF/ICC protocol. |
| Retrieval and detection choices | No PRCP-specific retrieval condition or dilution is supplied. For paraffin chromogenic IHC, follow the catalog antibody's validated IHC-P directions and include suitable controls when optimizing retrieval and detection (standard IHC practice); do not infer a PRCP fixation effect from HPA staining levels. |
| Situation | Likely cause | Next action |
|---|---|---|
| Positive control has no detectable granular cytoplasmic stain. | A missing target-cell population or a failed antibody, retrieval or detection step is possible (HPA: High in kidney tubules and adrenal glandular cells; standard IHC practice). | Confirm the relevant cells are present, then check the catalog antibody's IHC-P directions, reagent performance and positive control on the same run (standard IHC practice). |
| Colour persists in a no-primary control. | Primary-independent chromogenic activity or nonspecific detection background is possible (standard IHC practice). This control cannot identify PRCP expression. | Review endogenous enzyme blocking where applicable, secondary detection, washes and chromogen timing; repeat the no-primary control alongside tissue sections (standard IHC practice). |
| Strong nuclear or cell-surface signal dominates. | The compartment conflicts with granular cytoplasmic tissue staining and lysosomal annotation (HPA: tissue IHC; UniProt P42785). | Check tissue morphology and control slides, then reassess antibody specificity before scoring the signal as PRCP (standard IHC practice). |
| Adipocytes or bronchial epithelial cells stain strongly. | Those populations are Not detected in the reference profile (HPA: tissue IHC); cross-reactivity or detection background is possible (standard IHC practice). | Compare the same run's positive and no-primary controls, and record the discrepancy at cell level rather than reclassifying the entire tissue (standard IHC practice). |
| Only diffuse weak colour is visible in a positive tissue. | Weak diffuse colour is difficult to distinguish from background and lacks the reported granularity (HPA: tissue IHC profile). | Inspect a matched negative control, optimize routine washing and development, and score only reproducible cell-associated staining (standard IHC practice). |
| IHC and ICC-IF seem to give different compartments. | HPA reports granular cytoplasm in tissue IHC and supported vesicles in ICC-IF; these descriptions are compatible at different viewing scales (HPA: tissue and subcellular profiles). | Compare intracellular localisation within each preparation and use its own controls; do not transfer an ICC-IF validation status or protocol to paraffin IHC (HPA: antibody validation; standard IHC practice). |
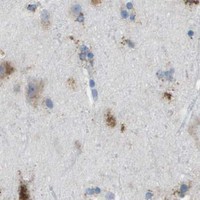
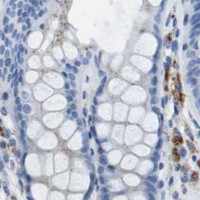
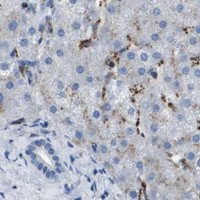
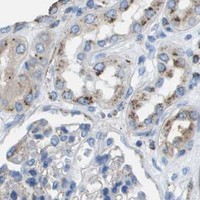


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | High | Protein (IHC) | HPA → |
| Cerebellum | Cells in molecular layer | High | Protein (IHC) | HPA → |
| Kidney | Cells in tubules | High | Protein (IHC) | HPA → |
| Spleen | Cells in red pulp | High | Protein (IHC) | HPA → |
| Breast | Myoepithelial cells | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Appendix | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Not detected | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | Not detected | Protein (IHC) | HPA → |
| Cervix | Glandular cells | Not detected | Protein (IHC) | HPA → |
Troubleshoot PRCP staining in paraffin sections by checking retrieval, compartment, controls and scoring before interpreting chromogenic signal.
A04829-1 is listed for human and mouse IHC and IF (catalog: applications, reactivity); its real IHC image shows paraffin-embedded human lung squamous cell carcinoma (IHC image caption).
A04829-1 has an IHC image from paraffin-embedded human lung squamous cell carcinoma (IHC image caption). It is listed for human and mouse IHC and IF, but no IF image is supplied (catalog: applications, reactivity, IF image alts).
Which to pick: For tissue IHC, choose A04829-1: its image caption documents paraffin sections, Tris-EDTA retrieval at pH 9.0, and primary antibody at 1:200 overnight at 4°C; the fixative is unreported (IHC image caption). For IF, A04829-1 is listed, but ICC validation and an IF image are unreported (catalog: applications, IF image alts). For cross-species work, A04829-1 lists human and mouse reactivity, though the shown IHC tissue is human; the antibody is rabbit-hosted and its clonality is unreported (catalog: reactivity, host, clone; IHC image caption).