This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan PRIM1 staining in paraffin sections using the IHC-validated antibody and its documented dilution range (datasheet: A30648, 1:100–1:300). Compare the reported cytoplasmic pattern across tissues while accounting for the tissue evidence’s uncertain reliability (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic staining reported; reliability uncertain (HPA tissue IHC) | |
| Staining pattern | Cytoplasmic staining in most tissues; cell type varies (HPA tissue IHC) | |
| Antigen retrieval | Tris-EDTA pH 9.0 HIER, heat-mediated (datasheet A30648) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep fixation consistent across sections. (standard IHC practice; not target-specific) | |
| Caveat | Breast adipocytes stain; adipose adipocytes do not (HPA tissue IHC) | |
| Regulation | S-phase role; expression trend unreported (UniProt) | |
| Isoform / epitope | No isoforms annotated; one 1–420 chain (UniProt) |
Compare the catalog antibody's IHC-P protocol (datasheet A30648) with published PRIM1 staining conditions for human liver and mouse specimens (PMC7903777).
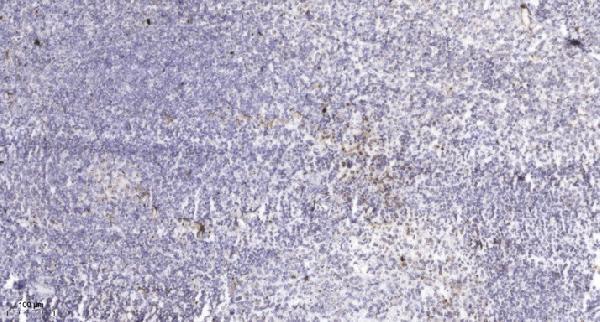
| Sample | Paraffin-embedded human tonsil tissue; fixative not specified (datasheet A30648) |
| Fixation | Image fixative and duration unreported (datasheet A30648); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: Tris-EDTA pH 9.0 (datasheet A30648); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-PRIM1, 1:100 - 1:300 (datasheet A30648) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | PRIM1-positive staining in glandular cells of adrenal gland (HPA tissue IHC: Medium). HPA tissue profile: Cytoplasmic expression in most tissues. No signal in the no-primary control. |
Expect predominantly cytoplasmic PRIM1 staining in many tissues, including glandular cells in colon and hematopoietic cells in bone marrow, where HPA reports medium signal (HPA tissue IHC: cytoplasmic profile; medium staining). PRIM1 has no transmembrane segment (UniProt P49642 topology). Treat this as a provisional pattern: the tissue IHC assessment is Uncertain and awaits external verification (HPA tissue IHC: reliability).
| Cytoplasmic staining in colon glandular cells or bone marrow hematopoietic cells. | This fits the reported compartment and medium staining in those cell populations (HPA tissue IHC: cytoplasmic profile; colon and bone marrow). Compare cells within the section before scoring intensity; the HPA pattern is provisional because its reliability is Uncertain (HPA tissue IHC: reliability). |
| Strong nuclear-only staining, with little or no cytoplasmic signal. | Flag a possible localisation artefact and check controls before calling it PRIM1: HPA describes predominantly cytoplasmic tissue staining, while UniProt supplies no subcellular annotation (HPA tissue IHC: profile; UniProt P49642 subcellular record). PRIM1's role in DNA synthesis alone does not validate a nuclear-only IHC pattern (UniProt P49642 function). |
| Strong staining confined to a cell population reported as undetected, such as parathyroid glandular cells. | Consider antibody cross-reactivity or endogenous detection activity, then compare a control section and the expected cell population (HPA tissue IHC: parathyroid glandular cells not detected; general IHC practice). An HPA nondetection is a comparison point, not proof that every specimen must be negative (HPA tissue IHC: Uncertain reliability). |
| Diffuse color across cells, stroma, and blank areas, obscuring cell boundaries. | Treat the pattern as background until controls support a cellular signal; widespread deposit does not match HPA's cell-level cytoplasmic profile (HPA tissue IHC: profile). Inspect background on a section processed without primary antibody and review blocking, washes, and chromogen development (general chromogenic IHC practice). |
| No signal in a section expected to contain positive cells. | First confirm that the section contains the relevant cells: HPA reports medium staining in colon glandular cells and bone marrow hematopoietic cells (HPA tissue IHC: positive cells). If they are present, review antibody and detection controls before interpreting the blank section; the reference pattern remains Uncertain (HPA tissue IHC: reliability; general IHC practice). |
| Tissue and cell population | Expected staining depends on the sampled cells: HPA reports medium signal in colon glandular cells and bone marrow hematopoietic cells, low signal in lung alveolar cells, and no detected signal in parathyroid glandular cells (HPA tissue IHC: cell-level observations). Choose comparison areas by cell identity rather than whole-organ color (general IHC practice). |
| Confidence in the reference pattern | The tissue IHC assessment is Uncertain and pending external verification; the listed rabbit polyclonal antibody, HPA040010, also has Uncertain IHC status (HPA tissue IHC: reliability; HPA antibody validation). Use the reported pattern as a guide for controls, not as an independently established specificity standard (HPA: Uncertain assessments). |
| Protein architecture and cell cycle | PRIM1 is a 420-amino-acid chain without a signal peptide or transmembrane segment, and UniProt lists no isoforms (UniProt P49642 processing, topology, isoforms). HPA notes that transcript variation correlates with the cell cycle, which may inform comparisons between cell populations but does not establish a tissue IHC intensity rule (HPA subcellular summary). |
| IF/ICC Q&A: Is a distinct PRIM1 compartment established for fluorescence images? | No: HPA lists no main subcellular location and no cell lines with ICC-IF images (HPA subcellular record). Its cytoplasmic profile comes from tissue IHC, so verify any fluorescence localisation with assay controls rather than treating that profile as an independently confirmed IF pattern (HPA tissue IHC: profile; general IF practice). |
| Situation | Likely cause | Next action |
|---|---|---|
| Colon glandular cells or bone marrow hematopoietic cells appear blank. | The relevant cells may be absent from the viewed area, or the IHC run may have failed; both are checks to make before interpreting a blank slide (HPA tissue IHC: reported positive cells; general IHC practice). | Confirm cell identity and morphology, then review a known-performing positive control, primary-antibody step, detection reagents, and development (general chromogenic IHC practice). Do not infer PRIM1-specific fixation sensitivity; none is reported in the supplied UniProt or HPA records. |
| Every compartment shows diffuse brown staining. | Nonspecific background or excessive chromogen development is possible when color lacks a cell-defined distribution (general chromogenic IHC practice); HPA reports a cytoplasmic cellular profile (HPA tissue IHC: profile). | Compare the section processed without primary antibody; check blocking, wash adequacy, and development time, then reassess whether cytoplasmic cell staining remains distinguishable (general chromogenic IHC practice). |
| The section shows only nuclear staining. | That localisation conflicts with the predominantly cytoplasmic tissue IHC profile; UniProt does not annotate a definitive PRIM1 compartment (HPA tissue IHC: profile; UniProt P49642 subcellular record). | Check the negative control, morphology, and staining in reported positive cell populations before scoring; record a persistent nuclear-only result as discordant with the provisional HPA pattern (general IHC practice; HPA tissue IHC: Uncertain reliability). |
| Parathyroid glandular cells stain strongly. | HPA lists these cells as not detected, so cross-reactivity or endogenous detection activity is plausible; HPA's tissue assessment is Uncertain (HPA tissue IHC: parathyroid glandular cells, reliability; general IHC practice). | Compare a section without primary antibody and a reported positive cell population; inspect endogenous detection activity using controls appropriate to the chosen detection chemistry (general chromogenic IHC practice). |
| A low-signal sample is scored as negative. | HPA lists low staining in lung alveolar cells and several other populations, so faint cell-associated color can be difficult to distinguish from background (HPA tissue IHC: low observations; general IHC practice). | Score identified cells against background and a control on the same run; report an equivocal result if the signal cannot be separated reliably (general IHC scoring practice). |
| Different tissues give apparently conflicting results. | HPA reports medium staining in breast adipocytes but no detected staining in adipocytes from adipose tissue, illustrating variation in its sampled contexts (HPA tissue IHC: breast and adipose tissue). | Record tissue and cell identity for each slide and compare each observation with its matching HPA entry; avoid treating one tissue's result as a universal adipocyte expectation (HPA tissue IHC: cell-level observations). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Uncertain — Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | Medium | Protein (IHC) | HPA → |
| Appendix | Glandular cells | Medium | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Medium | Protein (IHC) | HPA → |
| Breast | Adipocytes | Medium | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Caudate | Glial cells | Not detected | Protein (IHC) | HPA → |
| Cerebellum | Cells in granular layer | Not detected | Protein (IHC) | HPA → |
| Hippocampus | Glial cells | Not detected | Protein (IHC) | HPA → |
| Lymph node | Germinal center cells | Not detected | Protein (IHC) | HPA → |
Use the catalog antibody’s paraffin section result as a starting point, and interpret PRIM1 staining cautiously because the reported tissue pattern awaits external verification (caption A30648; HPA reliability).
Two anti-PRIM1 antibodies have paraffin-section IHC images from human tissue (catalog IHC captions); both list human, mouse and rat reactivity (catalog reactivity), while A30648 also lists IF/ICC (catalog applications).
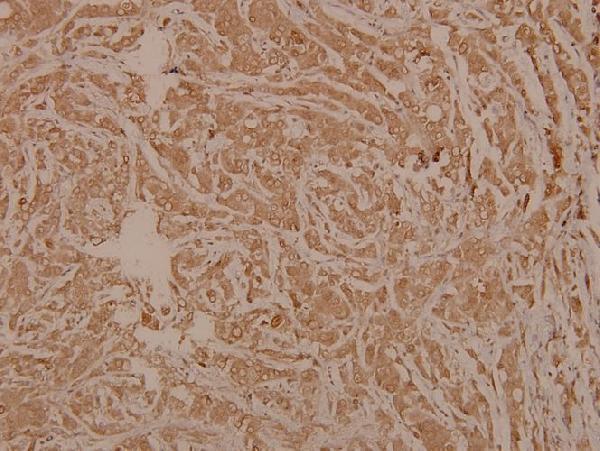
A30648 will render with IHC data from paraffin-embedded human tonsil (A30648 IHC caption); its listed applications include IF and ICC (A30648 catalog applications), but no IF image is supplied (A30648 catalog images). A09694-2 will render with IHC data from paraffin-embedded human breast carcinoma (A09694-2 IHC caption); IHC is listed, but IF/ICC is not (A09694-2 catalog applications).
Which to pick: For tissue IHC, choose A30648 if you want an image caption documenting Tris-EDTA retrieval at pH 9.0 and a 1:200 primary dilution (A30648 IHC caption); A09694-2 also has paraffin-section IHC data at 1:100 (A09694-2 IHC caption). For IF/ICC, choose A30648 because those applications are listed for it (A30648 catalog applications); both antibodies are rabbit polyclonals listing human, mouse and rat reactivity, so either is a cross-species IHC candidate (catalog host, clonality, reactivity and applications). Both image captions identify paraffin-embedded tissue, but neither reports the fixative (A30648 and A09694-2 IHC captions).