This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan PRRT2 chromogenic IHC in paraffin sections using cerebellar granular-layer cells and cortical neuropil as positive controls (HPA tissue IHC). Keep fixation consistent and score the observed cytoplasmic CNS signal (HPA tissue IHC), while treating synaptic-membrane localization as a molecular expectation (UniProt).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic CNS staining (HPA tissue IHC); synaptic membranes are a molecular expectation (UniProt) | |
| Staining pattern | Cytoplasmic signal in cerebellar granular-layer cells and cortical neuropil (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Cerebellum+1 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep fixation consistent across sections (standard IHC practice; not target-specific); Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A02707) | |
| Caveat | Brain staining varies by cell type: caudate glia are not detected (HPA tissue IHC) | |
| Regulation | Expression regulation is not annotated (UniProt) | |
| Isoform / epitope | 3 isoforms; cytoplasmic/extracellular epitope unknown (UniProt) |
The catalog antibody’s IHC-P protocol is followed by three published PRRT2 immunoperoxidase protocols: paraffin and cryostat sections, human tissue microarrays, and mouse vibratome sections prepared for electron microscopy.
| Sample | Tissue sections; selected-image fixative not specified (standard IHC workflow) |
| Fixation | Image fixative and duration unreported (datasheet A02707); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-PRRT2, 1:100–1:500 starting range (standard) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | PRRT2-positive staining in cells in granular layer of cerebellum (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in CNS. No signal in the no-primary control. |
PRRT2 is associated with synaptic and other neuronal membranes, with a transmembrane segment at residues 318–338 (UniProt Q7Z6L0 topology and subcellular location). In tissue IHC, expect cytoplasmic staining in the CNS, especially granular-layer cells in cerebellum and neuropil in cerebral cortex (HPA: High in both; tissue IHC reliability: Enhanced). Interpret the slide at the resolution of chromogenic IHC rather than requiring a sharp membrane outline.
| Strong staining in cerebellar granular-layer cells and cerebral-cortex neuropil (HPA: High in both). | This matches the reported CNS pattern (HPA: cytoplasmic expression in CNS). The neuropil result fits PRRT2's synaptic and neuronal-process locations (UniProt Q7Z6L0 subcellular location); a crisp cell-border outline is not required in chromogenic sections (general IHC practice). |
| Predominantly nuclear staining, with little of the expected CNS pattern (HPA: High in cerebellar granular-layer cells and cortical neuropil). | Treat this as a localisation mismatch: UniProt places PRRT2 at neuronal membranes, synapses and vesicle membranes, without a nuclear location (UniProt Q7Z6L0 subcellular location). Review specificity and staining controls before scoring it as PRRT2 (general IHC practice). |
| Strong signal in a cell type reported as undetected, such as adipocytes in adipose tissue (HPA: Not detected). | This conflicts with the cited tissue observation (HPA: adipose-tissue adipocytes, Not detected). Cross-reactivity or endogenous detection activity is possible, not proven; compare a control section and the expected CNS pattern before assigning target expression (general IHC practice). |
| Diffuse colour across cells and tissue spaces, without a recognisable granular-layer or neuropil pattern (HPA: High in those sites). | Uniform background limits interpretation of the compartment and cell type (general IHC practice). Inspect the negative detection control and blocking and wash conditions; diffuse colour alone does not reproduce the reported PRRT2 tissue distribution (HPA: cytoplasmic CNS profile). |
| No convincing staining in cerebellar granular-layer cells or cerebral-cortex neuropil (HPA: High in both). | A known-positive comparison has failed relative to the HPA tissue pattern. Check section integrity, retrieval, antibody incubation and detection with appropriate controls (general IHC practice); this result alone cannot establish absence of PRRT2 in the specimen. |
| Tissue and cell selection (HPA: tissue IHC). | Cerebellar granular-layer cells and cerebral-cortex neuropil provide reported high-signal references (HPA: High in both). Adipose-tissue adipocytes and adrenal glandular cells are reported as undetected (HPA: Not detected); use these comparisons by cell type, not as proof that every cell in those tissues lacks PRRT2. |
| Compartment and section resolution (UniProt Q7Z6L0 topology; HPA: tissue IHC). | PRRT2 has a transmembrane segment at 318–338 and annotated neuronal membrane and vesicle locations (UniProt Q7Z6L0). HPA describes cytoplasmic CNS staining in tissue IHC (HPA: profile). At chromogenic resolution, assess the reported tissue pattern without demanding a continuous plasma-membrane rim (general IHC practice). |
| IHC antibody validation (HPA: antibody records). | HPA014447 and HPA048045 are listed as IHC Enhanced (HPA: antibody records), while the tissue profile has Enhanced reliability from staining and RNA consistency (HPA: reliability description). These labels support comparison with the reported pattern; they do not establish specificity for every preparation or staining condition (general IHC practice). |
| Isoforms and epitope coverage (UniProt Q7Z6L0). | UniProt lists 3 isoforms (UniProt Q7Z6L0 isoforms). The supplied evidence gives no antibody epitope or isoform coverage, so an unexpected result cannot be attributed to a particular isoform from these records alone; confirm the IHC-validated antibody's documented target region before making an isoform claim. |
| IF/ICC comparison (HPA: subcellular ICC-IF). | Q: Should IF/ICC look identical to tissue IHC? A: HPA reports supported plasma-membrane localisation by ICC-IF, with images from AF22, SH-SY5Y and U2OS (HPA: subcellular ICC-IF). Tissue IHC instead reports cytoplasmic CNS staining (HPA: tissue IHC); compare each preparation with its own evidence. |
| Situation | Likely cause | Next action |
|---|---|---|
| Positive-control CNS section is blank despite reported high staining (HPA: cerebellar granular-layer cells; cortical neuropil). | An assay step may have failed; absence of colour alone does not identify which step (general IHC practice). | Check section integrity and reagent controls, then review retrieval, primary-antibody incubation and chromogenic detection in sequence (general IHC practice). Do not call the test specimen negative until the positive control works. |
| Staining is mainly nuclear, unlike annotated neuronal membrane locations (UniProt Q7Z6L0). | The localisation conflicts with the UniProt annotation; nonspecific staining or interpretation error is possible (general IHC practice). | Recheck the counterstain and cellular boundaries, compare the positive CNS control, and assess an appropriate primary-antibody control (general IHC practice). Record the nuclear signal as unresolved until specificity is supported. |
| Strong colour appears in adipose-tissue adipocytes reported as undetected (HPA: Not detected). | Cross-reactivity or endogenous detection activity could contribute; the HPA comparison alone cannot distinguish them (general IHC practice). | Compare a primary-omission control and the expected CNS-positive section, and review endogenous-activity blocking appropriate to the detection chemistry (general IHC practice). |
| The whole section has diffuse colour that obscures the reported CNS pattern (HPA: cytoplasmic CNS profile). | Nonspecific antibody binding, incomplete blocking or inadequate washing may elevate background (general IHC practice). | Inspect the control section, then optimise blocking, wash conditions and the IHC-validated antibody's documented working dilution (general IHC practice); no target-specific dilution is supplied here. |
| Neuropil stains, but individual neuronal membrane outlines are indistinct (HPA: cerebral-cortex neuropil, High). | Chromogenic tissue IHC may not resolve fine synaptic membranes individually (general IHC practice), although UniProt annotates synaptic membrane locations (UniProt Q7Z6L0). | Score the reported neuropil distribution and its controls (HPA: cerebral-cortex neuropil, High); avoid treating lack of a crisp membrane rim alone as a failed result (general IHC practice). |
| A low-signal tissue appears positive, such as lung macrophages or kidney tubular cells (HPA: Low in both). | Low reported staining can be genuine, while background can be harder to distinguish at low intensity (HPA: Low; general IHC practice). | Interpret the named cell type and compartment against control sections, and compare with high-signal CNS tissue (HPA: cerebellar granular-layer cells and cortical neuropil, High); avoid scoring the entire organ as uniformly positive. |



Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — High consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Cerebellum | Cells in granular layer | High | Protein (IHC) | HPA → |
| Cerebral cortex | Neuropil | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Appendix | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Not detected | Protein (IHC) | HPA → |
| Breast | Adipocytes | Not detected | Protein (IHC) | HPA → |
Use compartment-aware controls and matched tissue processing to troubleshoot PRRT2 staining in chromogenic paraffin-section IHC (UniProt Q7Z6L0 localisation; standard IHC practice).
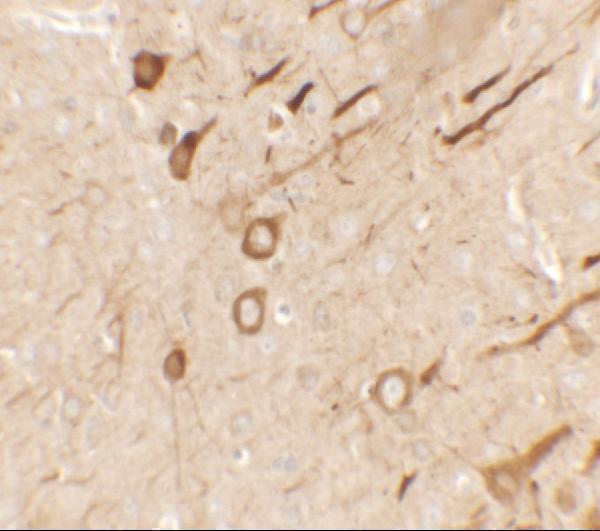
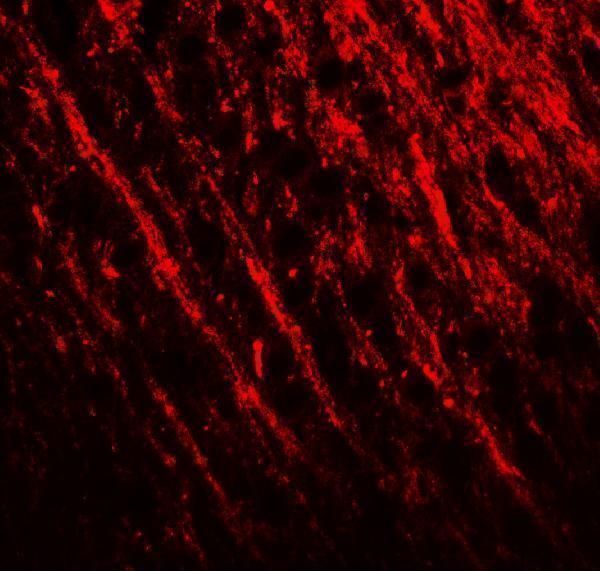
A02707 has rat-brain IHC and IF images (catalog image captions); its listed applications include IHC-P and IF, with Human, Mouse, and Rat reactivity (catalog applications and reactivity).
A02707 will render with an IHC image of rat brain tissue at 2.5 μg/ml (IHC image caption). Its IF image shows rat brain tissue at 20 μg/ml (IF image caption); the catalog lists Human, Mouse, and Rat reactivity (catalog reactivity).
Which to pick: Choose A02707 for tissue IHC-P (catalog applications); its IHC image shows rat brain tissue, but the caption does not report the fixative (IHC image caption). Choose A02707 for tissue IF (catalog applications; IF image caption); ICC validation is not listed (catalog applications). For other species, A02707 lists Human, Mouse, and Rat reactivity, while the supplied IHC and IF images show rat tissue (catalog reactivity; IHC and IF image captions).